Recovery and Outcome Expectations Post Stroke
Study these flashcardsFree · spaced repetition · iPhone, Android, Mac & web
All cards
1
How are Neurons impacted in stroke
primary or direct damage to neurons resulting in neuronal death
disrupts afferent and efferent connectivity
disrupts afferent and efferent connectivity
2
Diaschisis
an indirect effect
-damage to one area impacts connections to other healthy brain areas
-causes the other healthy brain areas to have decreased neuronal activity and metabolic dysfunction
-so initial deficits are a combination of the actual damage and then the healthy areas being like wtf
-presents as loss of function, impedes neural reorganization
3
Disruption of Interhemispheric Excitatory and Inhibitory Balanc
indirect effect
each side supposed to activate itself, and inhibit other hemisphere
acute (1 week): decreased same side activation/inhibition
subacute (6 mos): spontaneous recovery, risk of healthy side becoming overactive
chronic (>6mos): restore balance, but risk of continued overactivity from healthy side impacting recovery
4
brain attempts to restore lost function through
neural reorganization
5
recovery
involved repair or redundancy
adaptive plasticity
adaptive plasticity
6
compensation
involves perilesional and distant areas
leads to incomplete recovery or maladaptive plasticity
leads to incomplete recovery or maladaptive plasticity
7
what areas are we trying to stimulate with recovery?
the peripheral tissue of the lesion
restore/create new connections
restore/create new connections
8
Neuroplasticity
the capacity of the brain to reorganize - remodeling and functional recovery!
-happens in reponse to activity and task specific training
-aka learning and skill acquisition
-at the level of synapses, dendrites, axons, and cortex
-happens in reponse to activity and task specific training
-aka learning and skill acquisition
-at the level of synapses, dendrites, axons, and cortex
9
mechanisms of recovery and regeneration
resolution of neural shock/diaschisis
denervation super-sensitivity
recruitment/ unmasking of silent synapses
regenerative and reactive sprouting
denervation super-sensitivity
recruitment/ unmasking of silent synapses
regenerative and reactive sprouting
10
resolution of neural shock
edema reduction around injury
synapse recovery
restore impulses and neural blood flow
resolution of diaschisis
occurs over days to weeks
-low capacity functional intervention
synapse recovery
restore impulses and neural blood flow
resolution of diaschisis
occurs over days to weeks
-low capacity functional intervention
11
Denervation Supersensitivity
post synaptic response to the loss of synaptic inputs
changes in post synaptic membrane that makes the neuron more sensitive to neurotransmitters (good bc theres not much left, #upregulation, #desperate)
changes in post synaptic membrane that makes the neuron more sensitive to neurotransmitters (good bc theres not much left, #upregulation, #desperate)
12
Recruitment/ unmasking of silent synapses
-recruitment of previously silent synapses
-suggests structural synapses are present in many areas of the brain that may not be functional because of competition within neuronal pathways
-appears to be a "use-dependent" competition among neurons for synaptic connections
-suggests structural synapses are present in many areas of the brain that may not be functional because of competition within neuronal pathways
-appears to be a "use-dependent" competition among neurons for synaptic connections
13
Regenerative and Reactive Sprouting
-surviving neurons generate new axons (axonal sprouting and dendritic remodeling) to replace connections lost due to infarc
-target denervated areas, supporting the restoration of disrupted circuits and contributing to regained motor and sensory functions
-takes weeks to months, usually less effective, leads to dysfunction
how? specific motor stimulation
-target denervated areas, supporting the restoration of disrupted circuits and contributing to regained motor and sensory functions
-takes weeks to months, usually less effective, leads to dysfunction
how? specific motor stimulation
14
Cortical Remapping
resolution of diaschisis
restoration of interhemispheric balance
many neural networks and cortical reorganization
shifting of functional representations of motor and sensory systems to other areas
can be adaptive or maladaptive
restoration of interhemispheric balance
many neural networks and cortical reorganization
shifting of functional representations of motor and sensory systems to other areas
can be adaptive or maladaptive
15
Functional levels after stroke
immediately after - irreversible injury
-> then reversible dysfunction, lower levels of function initially
-> with remapping comes up to a new functional level which is better than immediately post stroke but still below baseline
improved through targeted therapy
-> then reversible dysfunction, lower levels of function initially
-> with remapping comes up to a new functional level which is better than immediately post stroke but still below baseline
improved through targeted therapy
16
the nature of the reorganization depends on
the motor experience
17
what promotes skill acquisition?
salient, intensive, goal directed task practice
18
what does endurance training and exercise do?
increase density of blood vessels in motor cortex-> angiogenesis
facilitates growth factors (BDNF)
facilitates growth factors (BDNF)
19
what does strength training do?
increase the number of synapses at the level of the spinal cord
(not cortical mapping)
(not cortical mapping)
20
why can compensation be not great?
it interferes with recovery and results in persistent behavioral deficits after a brain injury
21
neural recovery vs compensation
restoring fxn in neural tissue initially lost due to injury vs
residual neural tissue takes over a function due to injury
residual neural tissue takes over a function due to injury
22
impairment recovery vs compensation
restoring ability to isolate movement patterns in SAME manner as prior to injury vs performing movements in a manner different from how it was performed prior to injury
23
activity limitation recovery vs compensation
restoring the ability to perform a task the same way vs not
24
learned non use
secondary response over time
affected limb is used less often
compensatory strategies develop which negatively impacts recovery
affected limb is used less often
compensatory strategies develop which negatively impacts recovery
25
discharge destination decisions are
multifactorial and biopsychosocial determinants
objective: potential recovery, ambulation ability, discharge destination
objective: potential recovery, ambulation ability, discharge destination
26
High dose vs Low dose therapy
higher dose = more recovery
not time dependent
not time dependent
27
specialized actue and inpatient care outcomes
rapid assessment and diagnosis
hyperacute access to interventions
physiologic and nuerologic monitoring to reduce complications
Early and intensive rehab and secondary prevention
improved outcomes at 1 year
reduced rates of death or institutionalization
outcomes improved with >2 hours/day of rehab care
hyperacute access to interventions
physiologic and nuerologic monitoring to reduce complications
Early and intensive rehab and secondary prevention
improved outcomes at 1 year
reduced rates of death or institutionalization
outcomes improved with >2 hours/day of rehab care
28
National Health Institute of Health Stroke Scale (NIHSS)
quantitative assessment tool to measure acute stroke related neurologic deficits at the body structure and function level
29
NIHSS Scoring
Very severe: >25
Severe: 15-24
Mild to mod severity: 5-14
Mild: 1-5
Severe: 15-24
Mild to mod severity: 5-14
Mild: 1-5
30
NIHSS discharge cutoffs
<5: d/c home
6-13: acute rehab
>14: long term care
6-13: acute rehab
>14: long term care
31
average LOS in acute care
4.7 days
32
In patient Rehab demographics
18-54
male
white ppl
private insurance
ambulate with assist
larger hospitals or stroke unit
male
white ppl
private insurance
ambulate with assist
larger hospitals or stroke unit
33
SNF demographics
>55
more co-morbidities
Black, hispanic
medicare, medicaid
unable to ambulate
more co-morbidities
Black, hispanic
medicare, medicaid
unable to ambulate
34
environmental factors influencing discharge
accessibility at home and workplace
35
personal factors influencing discharge
family care capacity
marital/partner status
cognition and depression
low level of illness acceptance
limited self efficacy
marital/partner status
cognition and depression
low level of illness acceptance
limited self efficacy
36
priorities of recovery and outcome prediction
manage patient expectations
tailor rehabilitation goals
use time and resources most effectively for the best outcomes
tailor rehabilitation goals
use time and resources most effectively for the best outcomes
37
prognosis is related to what 2 things?
health condition
patient goals
patient goals
38
prognosis focuses on what parts of the ICF?
activity and participation
39
Prognosis is based on what factors?
available evidence based predictive factors
modifiers: previous activity and endurance levels, previous engagement and success with PT, access to rehab, support
modifiers: previous activity and endurance levels, previous engagement and success with PT, access to rehab, support
40
motor arm is predicitive of
hand function and ADL domains
41
Motor leg is predictive of
gait function and health related QOL indicators
42
>75 is predictive of
discharge location
older -> care facility more likely
older -> care facility more likely
43
aphasia is associated with
lower functional recovery and HRQOL
44
Imaging used to determine recovery potential
T1 weighted anatomical imaging
Diffuse tensor imaging
functional MRI
Diffuse tensor imaging
functional MRI
45
T1 weighted anatomical imaging
useful for locating lesion
extent of lesion overlap with posterior limb of internal capsule -> motor impairment
overlap between lesion and CST -> upper limb recovery potential
Severe white matter disease or hemorrhagic transformation -> poor outcomes
extent of lesion overlap with posterior limb of internal capsule -> motor impairment
overlap between lesion and CST -> upper limb recovery potential
Severe white matter disease or hemorrhagic transformation -> poor outcomes
46
Diffuse tensor imaging
useful for assessing structural integrity of white matter pathways
greater damage -> greater impairment
strong predictor of upper limb recovery
measures at 3 weeks post stroke -> UE function at 6 mos
greater damage -> greater impairment
strong predictor of upper limb recovery
measures at 3 weeks post stroke -> UE function at 6 mos
47
Functional MRI
cortical activity during voluntary movement of paretic limb -> reduction of impairment
functional connectivity between cortical and subcortical areas -> capacity for reorganization
functional connectivity between cortical and subcortical areas -> capacity for reorganization
48
upper limbs reovery post stroke stats
most people have upper limb dysfunction, and about half stays 5 years post stroke
49
lower upper limb function is associated with
lower subjective well being and HRQOL
50
PREP 2 algorithm for predicting reovery potential
prediction made based off evidence that sparing of descending white matter pathways is related to bettwe upper limb recovery
identifies 4 subsets of recovery potential
efficient for half of stroke individuals
identifies 4 subsets of recovery potential
efficient for half of stroke individuals
51
PREP 2 algorithm steps
1. Safe score: sum MRC and MMT grades at 72 hours post stroke
2. Transcranial Magnetic Stimulation
-test functional integrity of corticospinal pathways originating from lesioned primary motor cortex
+ response = good recovery potential
2. Transcranial Magnetic Stimulation
-test functional integrity of corticospinal pathways originating from lesioned primary motor cortex
+ response = good recovery potential
52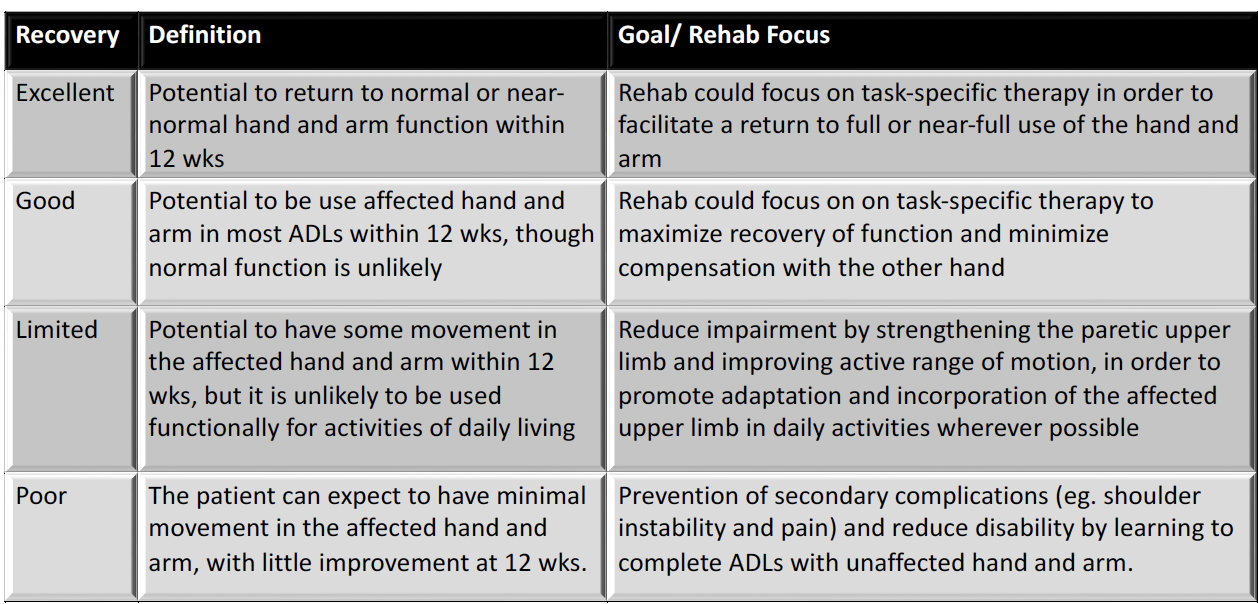
Image occlusion: name the hidden labels
53
Image occlusion: name the hidden labels
54
Image occlusion: name the hidden labels
55
Image occlusion: name the hidden labels
56
Image occlusion: name the hidden labels
57
Image occlusion: name the hidden labels
58
Image occlusion: name the hidden labels
59
Image occlusion: name the hidden labels
60
sitting balance measures significantly correlate with
TUG score at 4 months post stroke
61
Outcome measures for assessing sitting balance and cutoff
Sitting Balance Scale (28.5)
Trunk Impairment Scale (16.5)
Trunk Control Test (82)
Postural Assessment for Stroke Scale (10.5)
Trunk Impairment Scale (16.5)
Trunk Control Test (82)
Postural Assessment for Stroke Scale (10.5)
62
Trunk Control Test
4 items:
scores
4 items:
scores
4 items: rolling weak vs strong side, supine to sit, sitting balance
0 - unable
12 - able but not typical
25 - able "normally"
>=50: recovery of walking
<40: higher potential to be non-ambulatory
0 - unable
12 - able but not typical
25 - able "normally"
>=50: recovery of walking
<40: higher potential to be non-ambulatory
63
TCT scores inversely correlate with
LOS and 10MWT
64
Reintegration to Normal Living Index
+ correlation between TCT and
65
Postural Assessment Scale for Stroke (PASS-TC)
how many items?
scores
what its looking at
how many items?
scores
what its looking at
5 items - postural control
supine to sit and sitting items
items are scored 0-3
strong correlation with ADL function at 6 months
12.5/36: independent ambulation >10m at discharge from inpatient rehab
>17.5: acute stage is predictive of a high functional potential of recovery
supine to sit and sitting items
items are scored 0-3
strong correlation with ADL function at 6 months
12.5/36: independent ambulation >10m at discharge from inpatient rehab
>17.5: acute stage is predictive of a high functional potential of recovery
66
Up to 85% of individuals post stroke regain walking independence by
6 months
67
Individuals that require assist to walk early post stroke are
less likely to regain independence
68
level of ambulation can predict
discharge destination and level of participation and disability post stroke
69
most common goal post stroke
independent walking
70
parts of recovery of walking independence
lower limb motor impairment
stroke severity
trunk control and balance
lower limb sensory impairment
stroke severity
trunk control and balance
lower limb sensory impairment
71
Time to Walking Independently after Stroke (TWIST) algorithm
predicts at week 1 post stroke time to independent walking
includes:
TCT: static and dyn trunk control
MRC strength grade hip extension
determines probability for independent ambulation at 6 months
includes:
TCT: static and dyn trunk control
MRC strength grade hip extension
determines probability for independent ambulation at 6 months