Parkinson's Disease
Réviser ces flashcardsGratuit · répétition espacée · iPhone, Android, Mac et web
Toutes les cartes
1
On
Good Motor Function
2
Off
tremor, rigidity (stiffness), bradykinesia (slowness) or balance problems
3
On with dyskinesia
able to move but have involuntary or unintentional movements
4
Delayed on
medication takes a long time to start working after you take it
5
Early wearing off
medication stops working before the time of the next dose
6
Parkinson's Disease
is a neurodegenerative disorder that causes both motor and nonmotor symptoms and increases in prevalence with age
7
Epidemiology
● PD is a multifactorial disease
● Age is the biggest risk factor for PD
○ Median age of onset being 60 years of age
● Incidence of the disease rises with age to 93.1/100,000 in age groups 70-79
● Higher prevalence in Europe, North American, and South America compared with African, Asian, and Arabic countries
○ Expect 17 million patients with PD by 2040
● Per the CDC, PD is the second most common neurodegenerative disorder after Alzheimer’s Disease
8
Health Disparities
● Black and African Americans, and people of lower socioeconomic status experience greater disease severity and disability compared with white patients
● Black and African Americans with PD are diagnosed at later PD stages than white people with PD
○ Less likely to be prescribed dopaminergic medications, but more likely to be given antipsychotic medications
● Can result in:
○ Missed early diagnosis
○ Greater disease severity at first prevention
○ Impact finances and quality of life due to missed work, lost wages, early forced retirement and family caregiver burden
9
Neuropathology
PD occurs when neurons in the substantia nigra die or become impaired. These cells produce the
neurotransmitter dopamine which allows smooth, coordinated function of body muscles and movement.
neurotransmitter dopamine which allows smooth, coordinated function of body muscles and movement.
10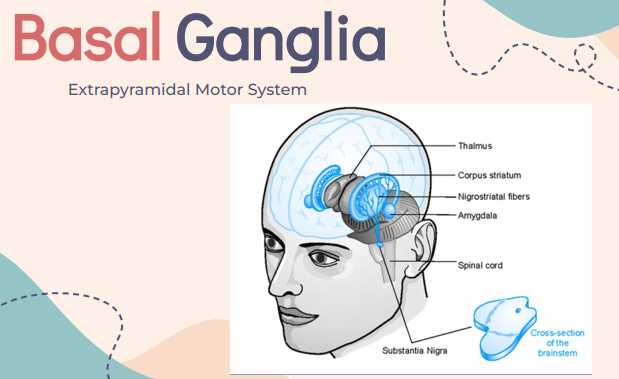
Occultation d’image : retrouve les étiquettes masquées
11
Occultation d’image : retrouve les étiquettes masquées
12
Occultation d’image : retrouve les étiquettes masquées
13
Occultation d’image : retrouve les étiquettes masquées
14
Occultation d’image : retrouve les étiquettes masquées
15
Extrapyramidal Motor System
● Extrapyramidal System (EPS) functions:
○ Postural tone adjustment
○ Control of the movements that are originally voluntary, but then become autonomic through exercise and learning (writing)
○ Inhibition of involuntary movements (hyperkinesis), which are particularly evident in extrapyramidal diseases
○ Control of reflexes that accompany the response to affective and attentive situations (e.g., reactions)
● Controls autonomic activities but also influences voluntary motility through a tonic function
16
Pathophysiology
● Degeneration found in multiple locations often prior to the substantia nigra:
○ Spinal Cord
○ GI tract
● Abnormalities in several neurotransmitters
● Lewy bodies
○ Spinal Cord
○ GI tract
● Abnormalities in several neurotransmitters
● Lewy bodies
17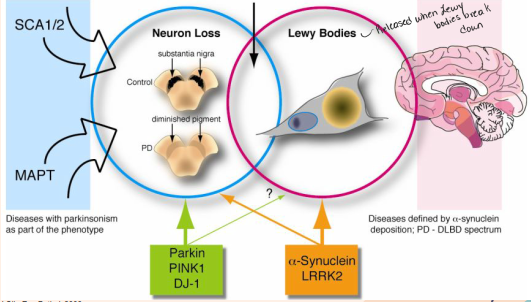
Occultation d’image : retrouve les étiquettes masquées
18
Occultation d’image : retrouve les étiquettes masquées
19
Occultation d’image : retrouve les étiquettes masquées
20
Occultation d’image : retrouve les étiquettes masquées
21
Occultation d’image : retrouve les étiquettes masquées
22
Occultation d’image : retrouve les étiquettes masquées
23
Etiology
● Idiopathic
● Genetic predisposition: mutation on multiple genes
● Oxidative Stress → increased free radical cell death →
○ Increased MAO-B metabolism
○ Decreased glutathione clearance of free radicals
● Increased excitatory amino acids
● Mitochondrial dysfunction
● Inflammation
● Environmental toxins (e.g., carbon monoxide, pesticides, etc)
24
Occultation d’image : retrouve les étiquettes masquées
25
Occultation d’image : retrouve les étiquettes masquées
26
Occultation d’image : retrouve les étiquettes masquées
27
Occultation d’image : retrouve les étiquettes masquées
28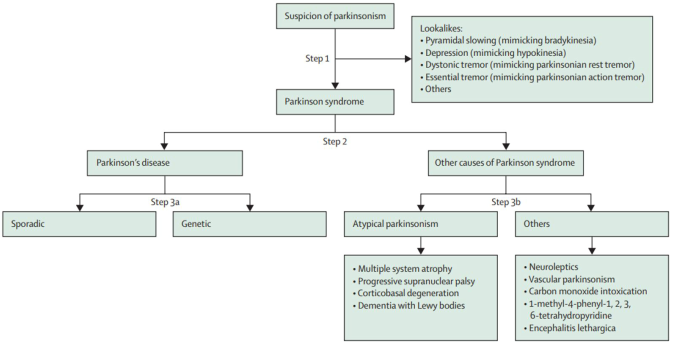
Occultation d’image : retrouve les étiquettes masquées
29
Occultation d’image : retrouve les étiquettes masquées
30
Occultation d’image : retrouve les étiquettes masquées
31
Occultation d’image : retrouve les étiquettes masquées
32
Occultation d’image : retrouve les étiquettes masquées
33
Two types of symptoms
Motor (TRAP)
Non-motor (SOAP)
Non-motor (SOAP)
34
Main motor symptoms (TRAP)
Tremor - pill rolling, starts unilaterally
Akinesia - Bradykinesia, Mask-like face, microphagia, and freezing
Rigidity - Stooped posture, Flexed head
Postural Instability - Gait problems (increased fall risk), due to loss of reflexes and rigidity
Akinesia - Bradykinesia, Mask-like face, microphagia, and freezing
Rigidity - Stooped posture, Flexed head
Postural Instability - Gait problems (increased fall risk), due to loss of reflexes and rigidity
35
Non-motor symptoms (SOAP)
Sleep Problems - Insomnia, RLS, REM, Behavior Disorder
Other - Fatigue, Speech, Swallowing, Seborrhea, Pain, Weight loss, Vision Problems, Restlessness, Dental problems
Autonomic Dysfunction - Drooling, Constipation, Sexual Dysfunction, Urinary frequency and retention, Decreased BP, Temp Regulation
Psychological Problems - Depression, Psychosis/vivid dreams, Anxiety, Apathy, Dementia
36
Non-Motor Symptoms Questionnaire (NMSQ)
● Enables clinicians to complete a comprehensive assessment
● Patient-based screening tool designed to draw attention to non-motor symptoms
● NOT designed to assess symptom severity or measure treatment effect
● 30 questions
● Patient-based screening tool designed to draw attention to non-motor symptoms
● NOT designed to assess symptom severity or measure treatment effect
● 30 questions
37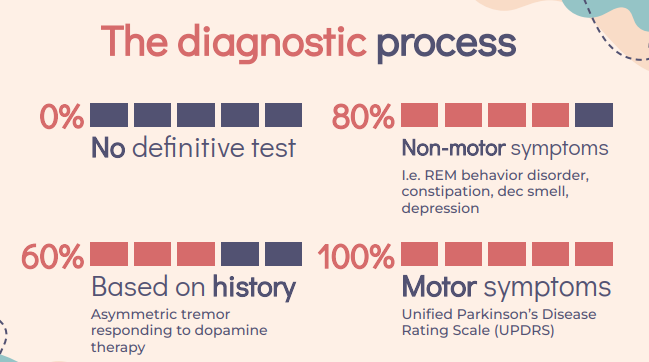
Occultation d’image : retrouve les étiquettes masquées
38
Occultation d’image : retrouve les étiquettes masquées
39
On
Good Motor Function
40
Parkinson’s Disease Progression
● The widely used Hoehn and Yahr staging scale covers progression of many motor symptoms, but does not address wide-ranging non-motor symptoms
● The Unified Parkinson’s Disease Rating Scale (UPDRS) measures motor symptoms and non-motor symptoms
○ Administer every 6-12 months
○ 4 parts:
■ Mentation
■ Activities of daily living
■ Motor performance
■ Complications of therapy
● The Unified Parkinson’s Disease Rating Scale (UPDRS) measures motor symptoms and non-motor symptoms
○ Administer every 6-12 months
○ 4 parts:
■ Mentation
■ Activities of daily living
■ Motor performance
■ Complications of therapy
41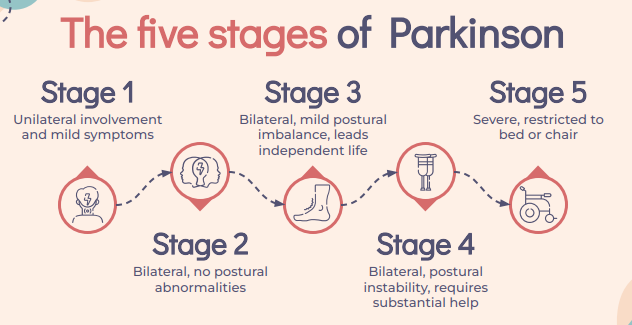
Occultation d’image : retrouve les étiquettes masquées
42
Occultation d’image : retrouve les étiquettes masquées
43
Occultation d’image : retrouve les étiquettes masquées
44
Occultation d’image : retrouve les étiquettes masquées
45
Occultation d’image : retrouve les étiquettes masquées
46
PD PResentation Differences
● Tremor-Dominant (TD) PD
○ May include levodopa-resistant tremor
● Postural Instability/Gait Difficulty (PIDG)
○ Characterized by bradykinesia, rigidity, and Parkinsonian gait
● Young-Onset Parkinson’s Disease (YOPD)
○ Symptoms begin at age 50 or earlier
● Juvenile Parkinsonism
○ Presents before age 21
○ May include levodopa-resistant tremor
● Postural Instability/Gait Difficulty (PIDG)
○ Characterized by bradykinesia, rigidity, and Parkinsonian gait
● Young-Onset Parkinson’s Disease (YOPD)
○ Symptoms begin at age 50 or earlier
● Juvenile Parkinsonism
○ Presents before age 21
47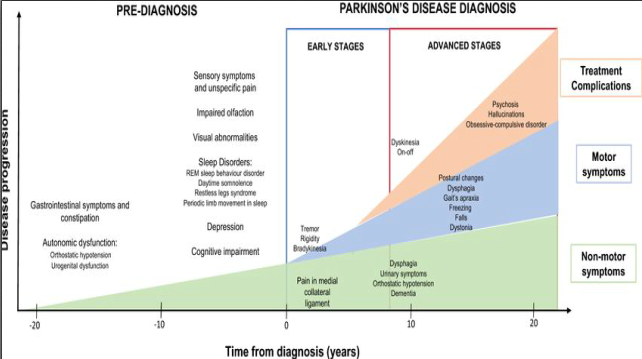
Occultation d’image : retrouve les étiquettes masquées
48
Occultation d’image : retrouve les étiquettes masquées
49
Occultation d’image : retrouve les étiquettes masquées
50
Occultation d’image : retrouve les étiquettes masquées
51
Occultation d’image : retrouve les étiquettes masquées
52
Goals of Therapy
Delay disease progression if possible. There are no disease modifying drugs
Reduce the incidence and severity of symptoms
Improve Activities of Daily Living
Minimize complications of drug therapy
Reduce the incidence and severity of symptoms
Improve Activities of Daily Living
Minimize complications of drug therapy
53
Non-Pharmacologic Treatments
● Nutritional evaluation and diet modification
● Exercise/Physical therapy
● Occupational therapy
● Speech therapy
● Education, counseling or support groups
● Surgery
○ Deep brain stimulation
○ Levodopa gel via jejunostomy tube
○ Focused ultrasound beams to the Thalamus
● Exercise/Physical therapy
● Occupational therapy
● Speech therapy
● Education, counseling or support groups
● Surgery
○ Deep brain stimulation
○ Levodopa gel via jejunostomy tube
○ Focused ultrasound beams to the Thalamus
54
PD Exercise Recommendations
● Regular exercise is the only treatment shown to slow progression
● Aerobic Activity: 3x/week
○ Improves posture, flexibility, core strength, and balance
○ Includes walking, jogging, bicycling, boxing, etc
● Strength Training
○ Improves posture, reduce muscle atrophy or increase core strength
● Blance, Agility, and Multitasking-focused exercises: 2-3x/week
○ Multidirectional stepping, weight shifting, yoga
● Stretching: daily
○ Static stretching for all major muscle groups
○ Dynamic stretching: prior to intense exercise
55
Rehabilitation Therapy
● Can have a major impact on the well-being of patients with PD
● Physical Therapy with a physical therapist (PT) in neurological experience
○ Full functional evaluation, recommend tailored, effective exercise interventions that include gait and balance training, aerobic exercise, resistance training and flexibility
● Occupational Therapy with an occupational therapist (OT) in neurological disorders
○ Can address difficulties PD symptoms cause with daily task participation, such as eating, dressing, bathing, driving, and working
● Speech Therapy with a speech-language pathologist (SLPs) in neurological disorders
○ Assess and treat cognitive-related changes and evaluate and treat swallowing disorders; address speech and language deficits
56
Surgical Options
● Considered when medications are no longer enough to manage PD symptoms
● Duopa
○ A form of carbidopa/levodopa delivered directly into the intestine in gel form
○ Improve absorption and reduce “off times”
● Deep Brain Stimulation (DBS) surgery
○ Can help with medication-resistant tremor, dyskinesia, and worsening of symptoms during medication wearing off times
○ Requires surgical placement of leads transcranially attached to a chest battery
● Focused Ultrasound
○ Can improve on-medication tremor, but can only be performed unilaterally
○ Highly-focused ultrasound beams to burn the thalamus while using MRI to aim and monitor the extent of the lesion
57
Deep Brain Stimulation
● Battery-powered neurostimulator
● Can select different target areas of the brain
● NOT effective for: gait, postural instability, autonomic symptoms
● Complications:
○ Infections, speech problems, dysotnicpostures, depression, suicide attempts, cognitive decline
● Can select different target areas of the brain
● NOT effective for: gait, postural instability, autonomic symptoms
● Complications:
○ Infections, speech problems, dysotnicpostures, depression, suicide attempts, cognitive decline
58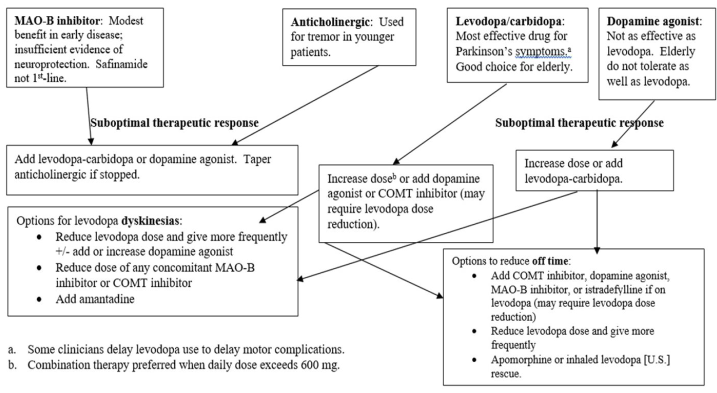
Occultation d’image : retrouve les étiquettes masquées
59
Occultation d’image : retrouve les étiquettes masquées
60
Occultation d’image : retrouve les étiquettes masquées
61
Occultation d’image : retrouve les étiquettes masquées
62
Occultation d’image : retrouve les étiquettes masquées
63
Occultation d’image : retrouve les étiquettes masquées
64
Occultation d’image : retrouve les étiquettes masquées
65
Occultation d’image : retrouve les étiquettes masquées
66
Occultation d’image : retrouve les étiquettes masquées
67
Levodopa with Carbidopa
● Levodopa
○ Converted to dopamine by DDC
○ Administered with carbidopa to prevent conversion of L-Dopa to DA outside of the brain
● Carbidopa: blocks DDC metabolism of levodopa
○ Helps more levodopa to get into the brain because less is metabolized
○ Minimizes peripheral side effects
○ 70-100 mg/day needed to inhibit DDC
● Side Effects:
○ Low blood pressure, dizziness, nausea, confusion, hallucinations, insomnia
● Initial treatment may be better tolerated in the elderly compared to other agents
68
Occultation d’image : retrouve les étiquettes masquées
69
Occultation d’image : retrouve les étiquettes masquées
70
Occultation d’image : retrouve les étiquettes masquées
71
Occultation d’image : retrouve les étiquettes masquées
72
Occultation d’image : retrouve les étiquettes masquées
73
Occultation d’image : retrouve les étiquettes masquées
74
Less variation in levodopa levels means...
less motor fluctuations
75
Rytary
● Dose conversion from immediate-release levodopa-carbidopa not 1:1
● May need prior authorization due to increased cost
● Bioavailability: ~70% of IR
● Cmax is 30% of IR
● Minimal doses available when wanting to switch products
● May need prior authorization due to increased cost
● Bioavailability: ~70% of IR
● Cmax is 30% of IR
● Minimal doses available when wanting to switch products
76
Inbrija
● Breath actuated inhaler
● Indicated for the intermittent treatment of off episodes in patients with Parkinson’s disease treated with levodopa/carbidopa
● Improves motor symptoms and may improve delayed gastric emptying time
● Side effects: cough, URI, nausea
○ May cause sputum discoloration
● Avoid in patients with respiratory diseases
● Maximum daily dose is 420 mg
● Maximum dose per off episode is 84 mg
77
Non-Motor Symptoms
● Depression: SSRI, TCA, pramipexole
● Psychosis: Quetiapine, Pimavanserin, Clozapine
● Dementia: Cholinesterase inhibitors (may decrease falls, rivastigmine
● Seborrhea: dandruff shampoos, topical steroids
● Postural hypotension: droxidopa
● Dyskinesia: related-sweating (B-blockers)
● Sleep disorders: depends on etiology
● Nausea: smaller, more frequent, low-fat meals with plenty of water
78
Counseling Points for Carbidopa/Levodopa
● Administer with food to minimize nausea
○ Avoid high protein foods
● Administered on empty stomach to maximize effect
● Taper dose to minimize risk of neuroleptic malignant syndrome
● Brown, black, or dark discoloration of bodily fluids
● Contraindicated with non-selective MAO inhibitors (2-week washout period
*** Any drug that affects dopamine receptors should be tapers
79
Carbidopa/Levodopa Interactions
- Iron binds to LD and decreaseabsorption (space by 2 hours)
- Vitamin C increases absorption so it is often added when making theliquid Sinemet
- Vitamin C increases absorption so it is often added when making theliquid Sinemet
80
Catechol-o-methyltransferase Inhibitors
● Increase dopamine concentrations by decreasing metabolism of dopamine
● Extends duration of action of levodopa →
○ Increasing “on” time (decrease “off” by ~ 1 hr)
○ Decreasing wearing off effects
● Maximized effect when used with dopa-decarboxylase inhibitors (carbidopa)
● ONLY used with levodopa/carbidopa
● Extends duration of action of levodopa →
○ Increasing “on” time (decrease “off” by ~ 1 hr)
○ Decreasing wearing off effects
● Maximized effect when used with dopa-decarboxylase inhibitors (carbidopa)
● ONLY used with levodopa/carbidopa
81
Occultation d’image : retrouve les étiquettes masquées
82
Occultation d’image : retrouve les étiquettes masquées
83
Occultation d’image : retrouve les étiquettes masquées
84
COMT Inhibitor Adverse Effects
Diarrhea
Dyskinesia
Hallucinations
Orange discoloration of bodily fluid
Sleepiness (sleep attacks)
Nausea, vomiting, anorexia
Dyskinesia
Hallucinations
Orange discoloration of bodily fluid
Sleepiness (sleep attacks)
Nausea, vomiting, anorexia
85
COMT Drug Interactions
● Entacapone
○ CYP1A2, 2A6, 2C9, 2C19, 2D6, 2E1, & 3A at high concentrations
■ 2C9: monitor INR with warfarin initiation
● Tolcapone
○ No significant CYP interactions
■ 2C9: monitor INR with warfarin initiation
● Non-selective MAO: tranylcypromine, phenelzine
○ May potentiate hypertensive crisis or serotonin syndrome through
increased levels of catecholamines (NE and 5H)
● Selective MAO-Is (selegiline and rasagiline) are safe!
86
Monoamine Oxidase-B (MAO-B) Inhibitors
● Work by irreversible inhibition of dopamine metabolism
● No direct effect at the dopamine receptor
● Duration of effect depends on time to regenerate MAO
● At normal doses: selective for MAO-B →
○ Minimal risk of of tyramine interactions
● Neuroprotective effects not proven, but possible
● No direct effect at the dopamine receptor
● Duration of effect depends on time to regenerate MAO
● At normal doses: selective for MAO-B →
○ Minimal risk of of tyramine interactions
● Neuroprotective effects not proven, but possible
87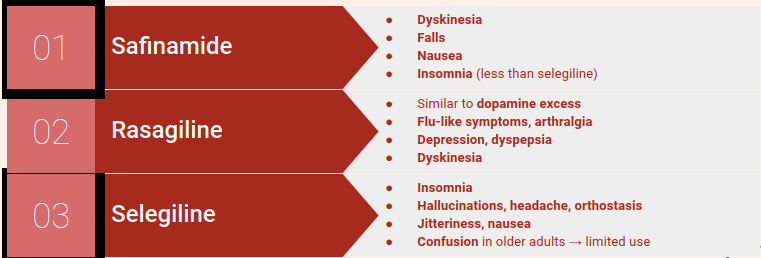
Occultation d’image : retrouve les étiquettes masquées
88
Occultation d’image : retrouve les étiquettes masquées
89
Occultation d’image : retrouve les étiquettes masquées
90
MAOI-B Drug Interactions
● Rasagiline
○ Metabolized by CYP1A2
● Selegiline
○ Metabolized by CYP2B6 and 2C19
● Safinamide
○ CYP iso-enzymes play a minor role
○ Severe hepatic impairment
○ Metabolized by CYP1A2
● Selegiline
○ Metabolized by CYP2B6 and 2C19
● Safinamide
○ CYP iso-enzymes play a minor role
○ Severe hepatic impairment
91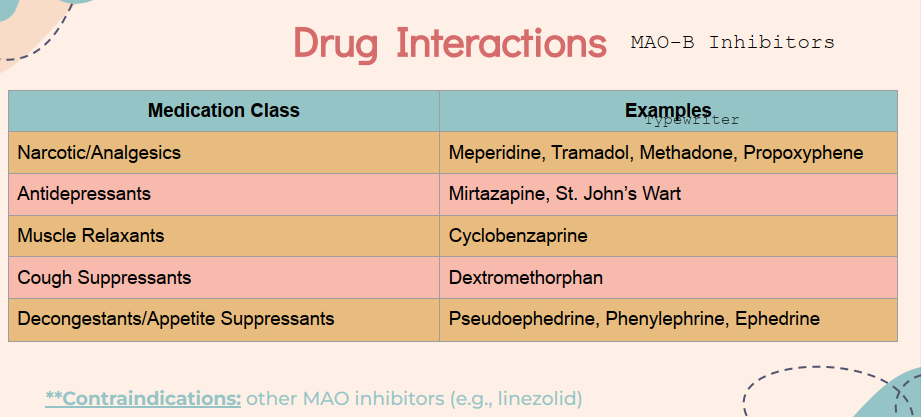
Occultation d’image : retrouve les étiquettes masquées
92
Occultation d’image : retrouve les étiquettes masquées
93
Occultation d’image : retrouve les étiquettes masquées
94
Occultation d’image : retrouve les étiquettes masquées
95
Occultation d’image : retrouve les étiquettes masquées
96
Occultation d’image : retrouve les étiquettes masquées
97
Dopamine Receptor Agonists
● Commonly used for initial treatment in younger patients, and
eventually in most patients
○ Not as effective as levodopa for motor control
● Act similarly to dopamine at the dopamine receptor
● With disease progression, treatment will be directed at both
reducing “off” periods and limiting dyskinesias
eventually in most patients
○ Not as effective as levodopa for motor control
● Act similarly to dopamine at the dopamine receptor
● With disease progression, treatment will be directed at both
reducing “off” periods and limiting dyskinesias
98
Dopamine Agonist Adverse Effects
● Somnolence, orthostasis, hallucinations, dyskinesias
● Dizziness, nausea, vomiting, dry mouth, constipation
● Rotigotine patch: application site reactions
● Pramipexole: postural deformity (bent spine, dropped head)
● Apomorphine: severe nausea, vomiting, hypotension
● Dizziness, nausea, vomiting, dry mouth, constipation
● Rotigotine patch: application site reactions
● Pramipexole: postural deformity (bent spine, dropped head)
● Apomorphine: severe nausea, vomiting, hypotension
99
Dopamine Agonist Drug Interactions
● Ropinirole (CYP1A2)
○ Antibiotics (ciprofloxacin, ketoconazole, rifampin)
○ Antidepressants (fluvoxamine)
○ Epilepsy drugs (carbamazepine, phenobarbital)
● Pramipexole
○ Ulcer treatments (cimetidine, ranitidine)
○ Heart medications (diltiazem, verapamil)
○ Antibiotics (ciprofloxacin, ketoconazole, rifampin)
○ Antidepressants (fluvoxamine)
○ Epilepsy drugs (carbamazepine, phenobarbital)
● Pramipexole
○ Ulcer treatments (cimetidine, ranitidine)
○ Heart medications (diltiazem, verapamil)
100
Dopamine Agonist Counseling Points
● Administer slow titrations due to orthostasis, dizziness, sleepiness
● Rotigotine: apply once daily at the same time each day to the stomach, thigh, hip, side of the body, shoulder or upper arm
○ Do not use the same site for at least 14 days
○ Remove the patch before an MRI
○ Avoid in patients with a sulfa allergy
● Apomorphine
○ Must be started with a test dose in a medical office
○ For emesis prevention: give trimethobenzamide or a similar antiemetic, 3 days prior to initial dose
101
Amantadine
● Blocks dopamine reuptake into presynaptic neurons →
○ Increases dopamine release from presynaptic fibers
● Primarily used to treat dyskinesias associated with peak-dose of levodopa/carbidopa
● Side effects: somnolence, psychosis, compulsive behaviors
○ Dizziness, orthostatic hypotension, dry mouth, insomnia
○ Livedo reticularis: reddish skin reaction
○ May aggravate seizures
● Decrease dose with renal impairment
102
Amantadine Drug Interactions
● Careful observation with medications for congestion, narcolepsy, and ADHD due to dyskinesia risk
● Increases the effect of drugs used for arrhythmias
● Medications used for high blood pressure may increase levels
● Inactivated influenza vaccine should be given
○ Live should not be administered within 2 weeks before or within 48 hours after administration
● Increases the effect of drugs used for arrhythmias
● Medications used for high blood pressure may increase levels
● Inactivated influenza vaccine should be given
○ Live should not be administered within 2 weeks before or within 48 hours after administration
103
Anticholinergic Agents
● Centrally-acting anticholinergics have anticholinergic and antihistamine effects
● Primarily used for tremor
● Includes benztropine and trihexyphenidyl
● Avoid use in elderly
● Anticholinergic side effects
○ Dry mouth, constipation, urinary retention, blurred vision, somnolence, confusion
● Primarily used for tremor
● Includes benztropine and trihexyphenidyl
● Avoid use in elderly
● Anticholinergic side effects
○ Dry mouth, constipation, urinary retention, blurred vision, somnolence, confusion
104
Anticholinergic Drug Interactions
● Benztropine, trihexyphenidyl
○ Medicines that cause sleepiness
○ Medications that reduce motility of the GI tract
● Hypertensive crisis
○ Antihistamines
○ Anti-seizure drugs
○ Medicine for sleep or anxiety
○ Muscle relaxants
○ Narcotic pain relievers containing codeine
○ Medicines that cause sleepiness
○ Medications that reduce motility of the GI tract
● Hypertensive crisis
○ Antihistamines
○ Anti-seizure drugs
○ Medicine for sleep or anxiety
○ Muscle relaxants
○ Narcotic pain relievers containing codeine
105
Adenosine Antagonist
● Used in combination levodopa/carbidopa to reduce “off” episodes
● Istradefylline®
● Side effects: hallucinations, dyskinesias, nausea, constipation
○ Less risk of dyskinesias and compulsive behavior
● Drug Interactions: CYP3A4
● Istradefylline®
● Side effects: hallucinations, dyskinesias, nausea, constipation
○ Less risk of dyskinesias and compulsive behavior
● Drug Interactions: CYP3A4
106
Treatment of Advance Disease
Increasing non-motor symptoms
Increasing motor fluctuations
Increasing motor fluctuations
107
Response Fluctuations (MADD)
● Motor Fluctuations
○ Wearing off: dose wears off early
○ Random on/off - unpredictable offs
○ Freezing (motor block) tends to occur suddenly & exacerbated by anxiety
● Akathisia (motor restlessness)
○ Uncontrollable movements
● Dystonia (sustained or spasmodic muscle contraction)
○ Too little dopamine
● Dyskinesia (abnormal involuntary movements)
○ Chorea (dance-like movements): too much dopamine
○ Diphasic dyskinesia: increasing and decreasing dopamine
○ Evaluate with Dyskinesia scale (4-point scale)
108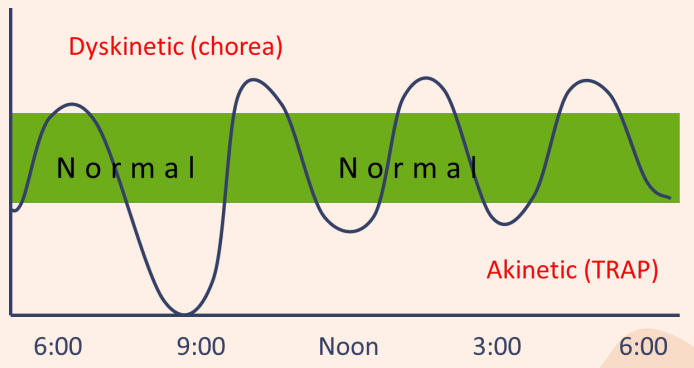
Levodopa Therapy Motor Fluctuations
109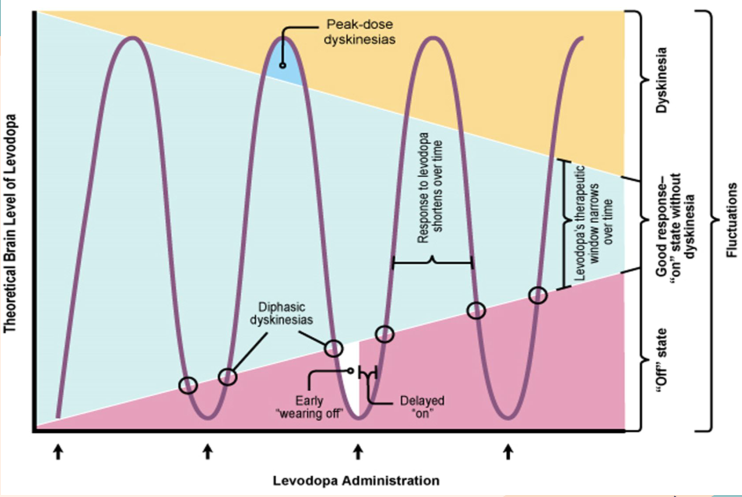
Occultation d’image : retrouve les étiquettes masquées
110
Occultation d’image : retrouve les étiquettes masquées
111
Occultation d’image : retrouve les étiquettes masquées
112
Occultation d’image : retrouve les étiquettes masquées
113
Managing Motor Complications
● Assess timing of medications with meals
● Adjust timing of medications to maximize “on” time
● Add or Change dosage forms
○ Longer acting (add CR to IR)
○ Quicker onset (add liquid)
● Add COMT, Istradefylline, MAO-B inhibitor, or dopamine agonist (decrease off time 0.5-2 hf)
● Adjust timing of medications to maximize “on” time
● Add or Change dosage forms
○ Longer acting (add CR to IR)
○ Quicker onset (add liquid)
● Add COMT, Istradefylline, MAO-B inhibitor, or dopamine agonist (decrease off time 0.5-2 hf)
114
Wearing off Treatments
● Levodopa onset 30 minutes or longer
○ Half-life is 0.75-1.5 hours
● If half-life levodopa is 1 hour, add carbidopa = 1.5 hours
○ + COMT = 2-2.5 hours
● CR levodopa has delayed onset about 2 hours + IR = 3 hours
● Rytary onset is 1 hour and duration is 4-5 hours
● Note: duration may be longer for patients with higher DA stores
● Onset is longer for those with delayed GI motility
115
Rescue Therapy for Off Episodes of Hypomobility
● Intermittent use in patients being treated with Sinemet
○ Liquid Sinemet (crush IR and place in carbonated beverage)
○ Inbrija → good for those with delayed gastric emptying
○ Apomorphine
■ Apokyn: SC injection
■ Knymobi: SL film
○ Liquid Sinemet (crush IR and place in carbonated beverage)
○ Inbrija → good for those with delayed gastric emptying
○ Apomorphine
■ Apokyn: SC injection
■ Knymobi: SL film
116
Non-Motor Symptoms (how to treat)
● Depression: SSRI, TCA, pramipexole
● Psychosis: Quetiapine, Pimavanserin, Clozapine
● Dementia: Cholinesterase inhibitors (may decrease falls, rivastigmine
● Seborrhea: dandruff shampoos, topical steroids
● Postural hypotension: droxidopa
● Dyskinesia: related-sweating (B-blockers)
● Sleep disorders: depends on etiology
● Nausea: smaller, more frequent, low-fat meals with plenty of water
● Psychosis: Quetiapine, Pimavanserin, Clozapine
● Dementia: Cholinesterase inhibitors (may decrease falls, rivastigmine
● Seborrhea: dandruff shampoos, topical steroids
● Postural hypotension: droxidopa
● Dyskinesia: related-sweating (B-blockers)
● Sleep disorders: depends on etiology
● Nausea: smaller, more frequent, low-fat meals with plenty of water
117
Non-Motor Symptoms Scale
In addition to dopamine, serotonergic, adrenergic and cholinergic pathways may also be affected
Adjust PD medications to improve “on” time
Promote non-pharmacologic treatments
Pick agents that do not worsen PD
Adjust PD medications to improve “on” time
Promote non-pharmacologic treatments
Pick agents that do not worsen PD
118
Non-Motor: Other
● Constipation: start non-stimulant laxatives, belly rub (I love U) and diet.
Use stimulants PRN
● Bladder dysfunction:
○ Frequency: decrease evening fluids, add medications (i.e. oxybutynin, tolterodine) - refer
○ Retention: stop anticholinergics, add medications (i.e. terazosin, doxazosin) - refer
● Sexual dysfunction: DC medications that decrease sexual function, add
medications (i.e. tadalafil, sildenafil) - refer
● Sialorrhea: anticholinergics
● Hypotension: both medication-induced and disease-related
● Falls: strategies to minimize falls, minimize drugs that increase fall risk
119
Parkinson’s Disease Depression
● Depression: (up to 60% of patients) may be part of the disease
● No class of antidepressant is preferred over another
○ Consider comorbidities (insomnia, hypersomnia, and sexual dysfunction) when choosing an agent
● Select antidepressant classes (SSRI and TCA) have been associated with drug-induced tremors
● Exercise therapy benefits
● No class of antidepressant is preferred over another
○ Consider comorbidities (insomnia, hypersomnia, and sexual dysfunction) when choosing an agent
● Select antidepressant classes (SSRI and TCA) have been associated with drug-induced tremors
● Exercise therapy benefits
120
Parkinson’s Disease Psychosis
● Includes delusions and paranoia
● Single greatest risk factor for nursing home placement in PD patients
● Attributable to Lewy Body disease, drug therapy, or a combination of the two
● Stopping levodopa is typically not an option
○ Remove second-line drugs like anticholinergics, amantadine, MAO, COMT
● Single greatest risk factor for nursing home placement in PD patients
● Attributable to Lewy Body disease, drug therapy, or a combination of the two
● Stopping levodopa is typically not an option
○ Remove second-line drugs like anticholinergics, amantadine, MAO, COMT
121
Parkinson’s Disease Psychosis Treatment
● Typical antipsychotics block DA: use quetiapine or clozapine
○ Quetiapine: conflicting case for efficacy
○ Clozapine: weekly monitoring for leukopenia and agranulocytosis
● Pimavanserin (Nuplazid®): inverse agonist of serotonin receptors $5HT_2A and 5HT_2C$
○ FDA indication for PD psychosis
○ Less orthostatic changes in BP
○ Watch for QTc prolongation
○ Dispensed via especially pharmacy, expensive, treatment form
122
Occultation d’image : retrouve les étiquettes masquées
123
Occultation d’image : retrouve les étiquettes masquées
124
Occultation d’image : retrouve les étiquettes masquées
125
Occultation d’image : retrouve les étiquettes masquées
126
Patient Instructions
● Do not stop medications, but taper
● Support groups and education → degenerative disease
● Increase physical activity
● Know your medications
● Discuss driving
● Notify doctors of any adverse effects
● Support groups and education → degenerative disease
● Increase physical activity
● Know your medications
● Discuss driving
● Notify doctors of any adverse effects
Plus de flashcards : Médecine et santé
A pajzsmirigy göbös megbetegedései, pajzsmirigytumorokMédecine et santé · HongroisRitikeBird Wing AnatomyMédecine et santé · AnglaisAJRespiratory System and InfectionsMédecine et santé · AnglaiskarebearNeurologyMédecine et santé · AnglaisExaltedW6: Consciousness and SleepMédecine et santé · Anglaisun étudiant OutLearnFactors Affecting Performance - CORE 2Médecine et santé · AnglaisAndyWeek 8: Circulatory SystemMédecine et santé · AnglaisEliazarB6 - NervesMédecine et santé · AnglaisAnaïsSIG CodesMédecine et santé · AnglaisAveryThoracic Wall Overview Part 1Médecine et santé · Anglaisjocyt9Medicine in Britain: 1250-Present DayMédecine et santé · AnglaisLemMuschi skeletci CNP “C.S”Médecine et santé · RoumainRyan
Tous les decks : Médecine et santé
Révise ces decks dans l’app
Gratuit sur iPhone, Android, Mac et le web. Ajoute n’importe quel deck à ton compte en un tap.

