Headaches Part 2
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Headache Epidemiology
Migraine is the 3rd most prevalent disease in this world
• One of the most common complaints encountered by
healthcare practitioners and among the top 5 reasons given by
adults 18 to 44 years of age for visiting US emergency
departments.
• 20.7% women and 9.7% men in the US have 1+ migraine
headaches per year.
• 1 or more TTH occurs in 38% to 86% of men and women per
year
• For cluster headaches, the ratio if 4:1 (Male: Female), 65% of
patients have a history of smoking.
2
Types of Headaches
• Primary Headaches
• Migraine
• Tension-type
• Cluster
• Secondary Headaches
• Tumor
• Trauma
• Infection
• Withdrawal
• Migraine
• Tension-type
• Cluster
• Secondary Headaches
• Tumor
• Trauma
• Infection
• Withdrawal
3
Diagnostic Workup
- • Associated Symptoms
• Frequency
• Duration
• Onset
Triggers
• Predictable?
• Better/worse?
• Sleep?
Rule Out Secondary Causes
• Imaging: CT, MRI, MRA, MRV
• Lumbar Puncture
• Frequency
• Duration
• Onset
Triggers
• Predictable?
• Better/worse?
• Sleep?
Rule Out Secondary Causes
• Imaging: CT, MRI, MRA, MRV
• Lumbar Puncture
4
SNNOOP10 for Secondary Headaches
mnemonic for identifying secondary headaches.
- Systemic: fever, weight loss, fatigue (infection, metastatic cancer, HIV, immunosuppression)
• Neurologic: altered consciousness, focal deficits (encephalitis, stroke)
• Neoplasm history
• Onset: sudden, thunderclap (hemorrhage)
• Older Age (>50): new, progressive (temporal arteritis)
• Pattern Change, Position, Papilledema: (tumor, intracranial pressure), Precipitated by sneezing, coughing, or exercise, Progressive, Pregnancy, Painful eye with autonomic features, Post-trauma, Pathology of the immune system, Painkiller overuse
LIFE THREATENING!!!
5
Medication Associated with Headaches
Adverse Effect
• Nitrates (nitroglycerin),
• BP medications: calcium channel blockers, ACE inhibitors, alpha- and beta-
adrenergic agnoists/blockers
• Medications for erectile dysfunction: Sildenafil (Viagra), vardenafil (Levitra,
Staxyn), tadalafil (Cialis) and avanafil (Stendra)
• Estrogen
• If Abruptly Withdrawn
• Caffeine, opioids, amphetamines, estrogen
• Due to Overuse
• General analgesics (butalbital, NSAIDs, aspirin)
• Anti-migraine (triptan, ergots)
6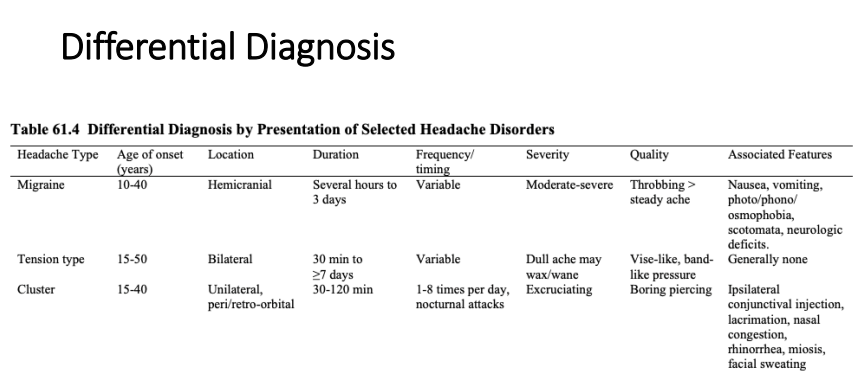
Bildverdeckung: nenne die verdeckten Beschriftungen
7
Bildverdeckung: nenne die verdeckten Beschriftungen
8
Bildverdeckung: nenne die verdeckten Beschriftungen
9
Bildverdeckung: nenne die verdeckten Beschriftungen
10
Bildverdeckung: nenne die verdeckten Beschriftungen
11
Bildverdeckung: nenne die verdeckten Beschriftungen
12
4 Phases of Migraine
1. Premonitory Symptoms (77%)
▪ Onset: Hours to days before headache onset
Symptoms Include:
• Neurologic: Allodynia, photophobia, phonophobia, hyperosmia, difficulty concentrating
• Psychological: Anxiety, depression, fatigue, irritability, drowsiness
• Autonomic: Polyuria, diarrhea, constipation
• Constitutional: Food cravings, decreased food intake, stiffened neck, increased thirst
2. Aura (25%)
▪ Onset: Up to 60 minutes before headache
• Gradual development over 5 minutes
▪ Symptoms Include:
• Visual: Disturbances (i.e., flashes/shimmers of light, partial vision loss)
• Sensory/Motor: Paraesthesias of face and arms (i.e., aphasia, weakness, hemiparesis)
3. Headache
▪ Onset: Gradual, with peak intensity over minutes to hours
• Last 4 to 72 hours
▪ Symptoms Include:
• Gastrointestinal: Nausea, vomiting
• Sensory: Photophobia, phonophobia, osmophobia
• Psychological: Impaired concentration, fatigue, dizziness, irritability
4. Postdrome/Resolution
▪ Symptoms Include:
• Psychological: Exhaustion, irritability, impaired concentration, euphoric
13
Classification of Migraines
• Episodic Migraine
• <15 headache days/month
• Chronic Migraine
• ≥ 15 headache days/month for > 3 months, with ≥ 8 headaches that have features of migraine headaches
• Status Migrainosus
• Migraine > 72 hr
• <15 headache days/month
• Chronic Migraine
• ≥ 15 headache days/month for > 3 months, with ≥ 8 headaches that have features of migraine headaches
• Status Migrainosus
• Migraine > 72 hr
14
Migraine Risk Factors
• Female gender
• Age 25-50
• Low education status
• Depression
• Obesity
• Stress
• Caffeine overuse
• Age 25-50
• Low education status
• Depression
• Obesity
• Stress
• Caffeine overuse
15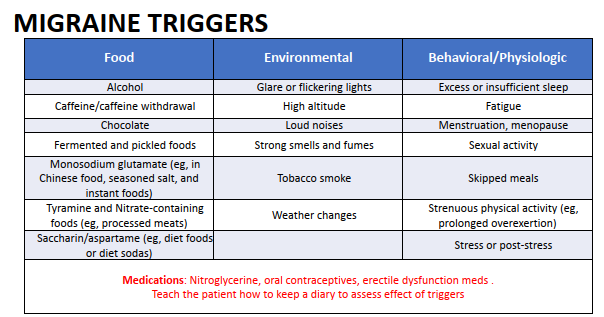
Bildverdeckung: nenne die verdeckten Beschriftungen
16
Bildverdeckung: nenne die verdeckten Beschriftungen
17
Bildverdeckung: nenne die verdeckten Beschriftungen
18
Bildverdeckung: nenne die verdeckten Beschriftungen
19
Bildverdeckung: nenne die verdeckten Beschriftungen
20
Bildverdeckung: nenne die verdeckten Beschriftungen
21
Bildverdeckung: nenne die verdeckten Beschriftungen
22
Bildverdeckung: nenne die verdeckten Beschriftungen
23
Bildverdeckung: nenne die verdeckten Beschriftungen
24
Bildverdeckung: nenne die verdeckten Beschriftungen
25
Bildverdeckung: nenne die verdeckten Beschriftungen
26
Bildverdeckung: nenne die verdeckten Beschriftungen
27
Bildverdeckung: nenne die verdeckten Beschriftungen
28
Bildverdeckung: nenne die verdeckten Beschriftungen
29
Non-pharmacologic Measures
Acute
• Ice to head
• Rest in dark, quiet environment
Prevention
• Trigger avoidance
• Behavioral: CBT, biofeedback
Headache Diary
• Frequency, severity, duration
• Identify triggers
Lifestyle
• Regular sleep, exercise
• Avoid smoking, caffeine
• Aerobic exercise, biofeedback, other forms of relaxation training
Neuromodulation Devices
• eTNS: external trigeminal nerve stimulator
• REN: remote electrical neuromodulation
• nVNS: noninvasive vagus nerve stimulator
30
Migraine Abortive Treatment
Abortive Treatment = acute, symptomatic treatment
General Analgesics
• NSAIDS, ASA, APAP
Migraine-Specific
• Triptans: 5-HT1B,1D receptor agonists
• Dihydroergotamine: 5-HT1 receptor agonist
• Lasmiditan: 5HT1F agonist
• Gepants: small-molecule CGRP antagonists
Other Options
• Anti-emetics
• Corticosteroids
• Muscle relaxants for select patients
General Analgesics
• NSAIDS, ASA, APAP
Migraine-Specific
• Triptans: 5-HT1B,1D receptor agonists
• Dihydroergotamine: 5-HT1 receptor agonist
• Lasmiditan: 5HT1F agonist
• Gepants: small-molecule CGRP antagonists
Other Options
• Anti-emetics
• Corticosteroids
• Muscle relaxants for select patients
31
Selecting an Abortive Agent
• Headache severity
• Time: Onset and Duration of headache (route of administration)
• Effectiveness
• Patient preference
• Contraindications/adverse effect profile
• Time: Onset and Duration of headache (route of administration)
• Effectiveness
• Patient preference
• Contraindications/adverse effect profile
32
General Analgesic (OTC)
Indication: Infrequent/mild-moderate acute migraine episodes
Agents:
• Efficacy enhance when combined with caffeine
• Combination agents
• Excedrin® Acetaminophen (APAP) + aspirin (ASA) + caffeine 250mg/250mg/65mg- for 18
yrs or older Max 2 per day
• Fioricet® APAP + butalbital + caffeine (avoid)
• Acetaminophen
• Aspirin – irreversible inhibitor of the enzyme cyclooxygenase (COX1 and 2)
• NSAIDS:
• Reversible inhibition of the enzyme cyclooxygenase (COX1 and 2)
• OTC: ibuprofen, naproxen
33
ACETAMINOPHEN and Aspirin
Indication: acute migraine episode (off-label use)
MOA: Aspirin irreversible inhibits the cyclooxygenase (COX) pathways
Acetaminophen not clear (weak inhibit COX, inhibit serotonergic pathways)
Efficacy: Acetaminophen (paracetamol-international name) or Aspirin as a monotherapy usually not effective enough
Combinations:
• Caffeine- improves analgesic effect, may work faster
• Butalbital- a sedative, avoid as increased risk of chronic migraine, overuse HA
• Oxycodone - Percodan (ASA) & Percocet (APAP); avoid as increased risk of chronic migraine, overuse HA
34
NSAIDS
Indication: acute migraine episode. MOA- Reversible inhibition of COX 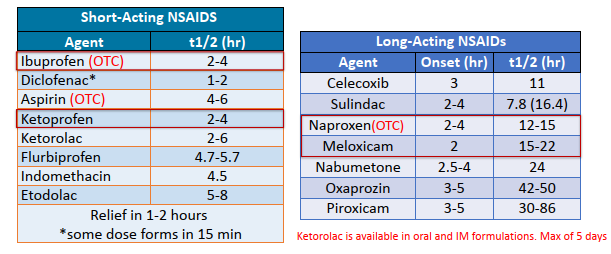
35
Adverse Effects of Chronic Analgesics
• Limit use to minimize risk of medication overuse headache (< 10 days/mo
for migraine specific meds, < 15 days/mo for acetaminophen/aspirin/NSAIDS)
• Cardiovascular ADRS: Can increase the risk of a heart attack, stroke and high blood pressure
• Can increase risk for bleeding (i.e. Gastroduodenal ulcer)
for migraine specific meds, < 15 days/mo for acetaminophen/aspirin/NSAIDS)
• Cardiovascular ADRS: Can increase the risk of a heart attack, stroke and high blood pressure
• Can increase risk for bleeding (i.e. Gastroduodenal ulcer)
36
Triptans
Mechanism: 5-HT1B,1D Receptor Agonists (inhibit the release of vasoactive and pro-
inflammatory neuropeptides including calcitonin-gene-related peptide (CGRP));
vasoconstriction of intracranial arteries. Inhibit nociceptive neurotransmission and plasma
protein extravasation by activating 5-HT1B,1D receptors in the descending brainstem pain-
modulating pathways; block neurogenic inflammation
Indication: 1st Line for moderate-severe acute migraine episodes
▪ Specific CNS activity compared to general analgesics
Use: 1 dose PRN for migraine; may repeat in 2 hr
▪ Key efficacy measure: 100% symptom and pain reduction in < 2 hours
Limit: 2 doses/day, 2 days/week
▪ Note: Triptan use for > 10 days/month can lead to rebound or daily headache
37
Triptan ADRs and Contraindications
ADRs: Paresthesia, dizziness, flushing, warmth, “triptan sensations”
(tightness; pressure in chest/throat), GI distress
Warnings: Evaluate cardiovascular risk factors prior to initiation because triptans can cause vasoconstriction. Watch for medication overuse. Monitor patients with seizure history
Contraindications:
• Cardiovascular: history of ischemic or vasospastic heart disease, MI, angina or accessory pathway arrhythmia;
• Cerebrovascular: history of stroke, TIA, or hemiplegic/basilar migraine
• Other: peripheral vascular disease, uncontrolled HTN, ischemic bowel disease, smoking, hepatic or renal dysfunction
• Triptans should not be used within 24 hours of the use of an ergotamine preparation or a different triptan
38
Triptan Comparisons
• Faster Onset (0.25-2hrs) but shorter duration (half-life <4 hr except eletriptan =4hr)
• Sumatriptan, zolmitriptan, rizatriptan, almotriptan, eletriptan
• Slower Onset (>1-2hr) but less headache recurrence
• Naratriptan(onset 1-3 hr; half-life 6 hrs); frovatriptan (onset 2-3 hr; half-life 26 hrs)
In comparison to sumatriptan 100mg:
• Lower adverse events: naratriptan(2.5mg), almotriptan(12.5 mg), frovatriptan(2.5mg)
• Better 2-hr pain response: eletriptan(80mg), rizatriptan(10mg), almotriptan(12.5mg)
• Lower recurrence rate: frovatriptan(2.5mg), eletriptan(40mg) (slightly long half-life)
39
Triptans (Other Admin Routes)
Indication: Patients with nausea and/or vomiting
Onset: SQ (10 min) < IN (15-30 min) < SL (30 min)
• Subcutaneous injection (SQ): Sumatriptan
• Intranasal inhalation (IN): Sumatriptan, zolmitriptan
• Sublingual (SL): Rizatriptan, zolmitriptan
Onset: SQ (10 min) < IN (15-30 min) < SL (30 min)
• Subcutaneous injection (SQ): Sumatriptan
• Intranasal inhalation (IN): Sumatriptan, zolmitriptan
• Sublingual (SL): Rizatriptan, zolmitriptan
40
Triptan DDIs
SSRI/SNRI
• Risk of Serotonin Syndrome (low)
Ergot derivative/other triptan within 24 hours
• Contraindicated
• Affected Medications: all in class
MAOI administration within 2 weeks
• Contraindicated
• Affected Medications: Sumatriptan, Rizatriptan, Zolmitriptan
CYP3A4 inhibitors
• Screen medication list
• Affected Medications: Almotriptan, Eletriptan
Propranolol
• Increases concentration of rizatriptan, zolmitriptan, frovatriptan, eletriptan
41
Sumatriptan/Naproxen (Treximet)
Mechanism: 5-HT1B,1D receptor agonist + long acting NSAID
Use: 1 dose (85mg/500mg) PRN for migraine; may repeat in 2 hours
• Combination tablet approved for episodic migraine only
Efficacy of Combination:
• Sumatriptan/naproxen was superior in achieving 24-hour pain relief endpoint compared to monotherapy with either agent
• Decreased incidence headache recurrence in 24 hours
ADRS: No difference in ADR occurrence with combo
42
Ergots
Indication: moderate-severe acute migraine episodes
MOA: non-selective 5-HT receptor agonist
Agents:
Ergotamine tartrate (SL, Ergot/Caffeine suppository combo) Not recommended: more
ADRs, less effective
Dihydroergotamine (DHE) (Intranasal, IV, Subcutaneous, IM injection)
• Preferred over ergotamine: Proven effective, less ADRs, faster IN/IM route
• Place in Therapy: Patients who experienced rebound headache with triptans;
patients who experienced medication overuse headaches
• Intravenous DHE for chronic intractable migraine headache or status migrainosus
• Combine with an antiemetic if administer intravenously and consider adding with
other routes as well
43
Ergots ADRs and Contraindications
ADRs: N/V, vasospasm, ischemia, fibrotic valves, stroke, hemorrhage, ergotism
(gangrene of extremities), abdominal pain
Contraindications
• Renal/hepatic failure, cardiac (ischemia, MI, angina), hemiplegic/basilar
migraine, peripheral vascular disease (Raynaud’s), uncontrolled hypertension,
pregnancy, breastfeeding
DDIs
• Potent CYP3A4 inhibitors (i.e protease inhibitors, azole antifungals, and some
macrolide antibiotics).
• Vasoconstrictors (peripheral or central)
• Serotonin modulators (separate 24-hr from triptan)
44
Lasmiditan (Reyvow)
▪ MOA: 5HT1F agonist
▪ Advantage: lacks vasoconstrictor activity
▪ Current role- when cardiovascular risk factors caution use of triptans or failed 2 triptans
▪ Dose: 50 mg, 100 mg, or 200 mg orally, as needed
• No more than one dose should be taken in 24 hours
• If the 50 mg dose does not work take 100mg in a subsequent attack
▪ CNS depression: Wait 8 hours after dosing before driving or operating machinery
▪ May be taken with or without food
▪ Controlled substance (C-V) Some potential for abuse due to euphoria
▪ The safety of treating an average of more than 4 migraine attacks in a 30-day period has not been established
• Risk of rebound may be greater if used 10 or more days per month
45
Calcitonin Gene-related Peptide receptor antagonist (CGRP)
Agents:
▪ Ubrogepant (Ubrelvy®) – Dec 2019 for acute treatment of migraine
▪ Rimegepant (Nurtec®) – Feb 2020 for acute; off-label for prevention
▪ Investigational: Zavegepant (IN formulation) and Atogepant (prevention)
• Avoid use in severe renal impairment (Ubrogepant) and hepatic impairment (Rimegepant)
• Consider for patients who have failed two triptans or cannot use triptans. May have less
risk of medication overuse headache
Safety & Efficacy- need more long-term post marketing studies and comparison studies with
triptans.. Prevents 1-2 episodic migraine/mo vs placebo. 25% of patients have at least 50%
decrease in migraine days/mo
46
Ubrogepant
Acute:
• Start with 50 to 100 mg as a single oral dose (time to peak ~ 1.5 hrs)
• May repeat once based on response and tolerability after ≥2 hours. Maximum dose: 200 mg per 24 hours
• Half-life ~5 to 7 hours.
• The safety of treating >8 migraines/month has not been established.
Pharmacokinetic Considerations: Metabolized by CYP3A4 also
BCRP/ABCG2, OATP1B1/1B3 (SLCO1B1/1B3), P-glycoprotein/ABCB1 (minor)
Do not use with strong CYP3A4 inhibitors
ADRs: Drowsiness, nausea, dry mouth
Cost: ~\$100 per tablet
47
Rimegepant
• Acute treatment: 75 mg orally - disintegrating tablet as a single dose; maximum:
75 mg/24 hours. Onset < 2 hours Effect should last ~ 48 hours
• Migraine prevention (off-label use): Oral: 75 mg every other day. May take 4
weeks to have full effect.
• Metabolism/Transport Effects Substrate of CYP3A4 (major), BCRP/ABCG2, CYP2C9 (minor), P-glycoprotein/ABCB1 (minor)
• Avoid with strong CYP3A4 inhibitors/inducers
• ADRS: Nausea (2%) <1% for skin rash, hypersensitivity reaction, dyspnea
• Cost: 1 tablet > \$100
48
Antiemetics
Mechanism: Dopamine Receptor Antagonist
Indication: Monotherapy or adjunctive to abortive treatment in patients with refractory headaches
▪ Severe nausea/vomiting
▪ Efficacy for migraines
• Increased response and absorption of analgesics
Agents: IV/PO metoclopramide, prochlorperazine, chlorpromazine, droperidol
Indication: Monotherapy or adjunctive to abortive treatment in patients with refractory headaches
▪ Severe nausea/vomiting
▪ Efficacy for migraines
• Increased response and absorption of analgesics
Agents: IV/PO metoclopramide, prochlorperazine, chlorpromazine, droperidol
49
Corticosteroids
Most commonly used as a rescue agent for status migrainosus
Dexamethasone 10 to 25mg IV or IM x1 in combination with patient’s standard abortive therapy
• Reduction in migraine occurrence for up to 72 hours (NNT: 9)
• No additional benefit for immediate headache relief
Prednisone: Addition of oral prednisone did not prove to be beneficial in prevention of recurrent headaches
50
Migraine Abortive Treatment
EARLIER IS BETTER!
Efficacy: Pain or symptom-free at 2 hours post-dose
• Without recurrence
• 20-80% response to an NSAID or triptan, depending on agent
Individualized Response
• e.g. if fail 1 triptan, can try another
Combination Therapy
• Inadequate response to monotherapy
• Any 2 agents from different classes (e.g. NSAID + triptan)
51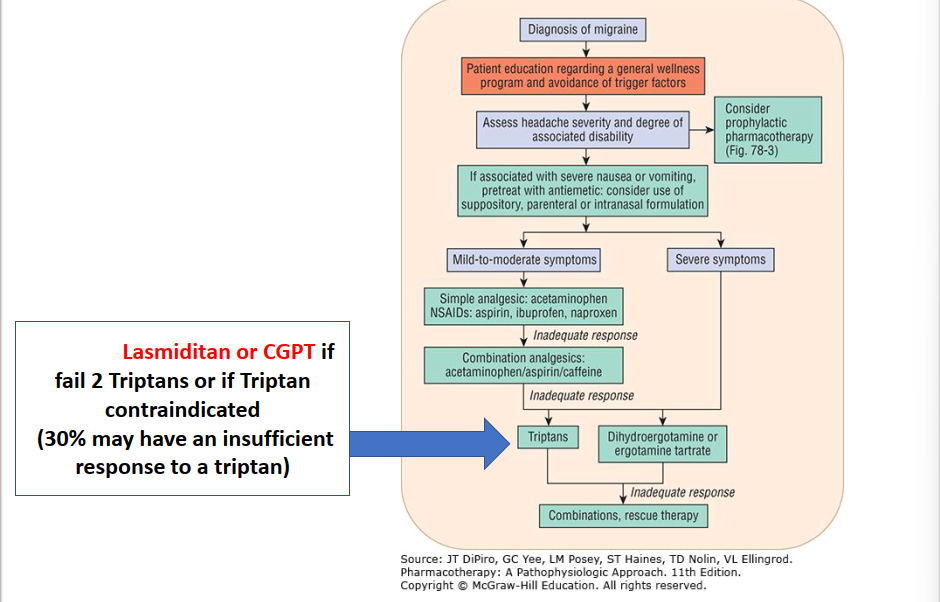
Bildverdeckung: nenne die verdeckten Beschriftungen
52
Bildverdeckung: nenne die verdeckten Beschriftungen
53
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Bildverdeckung: nenne die verdeckten Beschriftungen
55
Bildverdeckung: nenne die verdeckten Beschriftungen
56
Bildverdeckung: nenne die verdeckten Beschriftungen
57
Bildverdeckung: nenne die verdeckten Beschriftungen
58
Bildverdeckung: nenne die verdeckten Beschriftungen
59
Bildverdeckung: nenne die verdeckten Beschriftungen
60
Bildverdeckung: nenne die verdeckten Beschriftungen
61
Bildverdeckung: nenne die verdeckten Beschriftungen
62
Bildverdeckung: nenne die verdeckten Beschriftungen
63
Bildverdeckung: nenne die verdeckten Beschriftungen
64
Bildverdeckung: nenne die verdeckten Beschriftungen
65
Bildverdeckung: nenne die verdeckten Beschriftungen
66
Bildverdeckung: nenne die verdeckten Beschriftungen
67
Bildverdeckung: nenne die verdeckten Beschriftungen
68
Bildverdeckung: nenne die verdeckten Beschriftungen
69
Bildverdeckung: nenne die verdeckten Beschriftungen
70
Bildverdeckung: nenne die verdeckten Beschriftungen
71
Bildverdeckung: nenne die verdeckten Beschriftungen
72
Bildverdeckung: nenne die verdeckten Beschriftungen
73
Bildverdeckung: nenne die verdeckten Beschriftungen
74
Bildverdeckung: nenne die verdeckten Beschriftungen
75
Bildverdeckung: nenne die verdeckten Beschriftungen
76
Bildverdeckung: nenne die verdeckten Beschriftungen
77
Bildverdeckung: nenne die verdeckten Beschriftungen
78
Bildverdeckung: nenne die verdeckten Beschriftungen
79
Bildverdeckung: nenne die verdeckten Beschriftungen
80
Bildverdeckung: nenne die verdeckten Beschriftungen
81
Bildverdeckung: nenne die verdeckten Beschriftungen
82
Bildverdeckung: nenne die verdeckten Beschriftungen
83
Bildverdeckung: nenne die verdeckten Beschriftungen
84
Bildverdeckung: nenne die verdeckten Beschriftungen
85
Bildverdeckung: nenne die verdeckten Beschriftungen
86
Bildverdeckung: nenne die verdeckten Beschriftungen
87
Bildverdeckung: nenne die verdeckten Beschriftungen
88
Bildverdeckung: nenne die verdeckten Beschriftungen
89
Bildverdeckung: nenne die verdeckten Beschriftungen
90
Bildverdeckung: nenne die verdeckten Beschriftungen
91
Bildverdeckung: nenne die verdeckten Beschriftungen
92
Bildverdeckung: nenne die verdeckten Beschriftungen
93
Emergent Migraine Treatment
Moderate to severe migraine, particularly if the migraine is accompanied by
vomiting or significant nausea
• sumatriptan 6 mg SQ, or
• parenteral antiemetic agent (metoclopramide 10 mg or prochlorperazine (10
mg) with of diphenhydramine (12.5 to 25 mg IV every hour up to two doses) to prevent akathisia and other dystonic reactions, or
• dihydroergotamine (DHE 45) 1 mg IV combined with IV metoclopramide 10 in patients without ischemic vascular disease involving cardiac, cerebrovascular, or peripheral circulations.
Consider adjunctive treatment with IV or intramuscular dexamethasone (10 to 24
mg) to reduce the risk of early headache recurrence
94
Nonpharmacologic, Herbs, and Supplements
Therapeutic lifestyle measures:
• good sleep hygiene, routine meal schedules, regular exercise, and management of migraine
triggers are appropriate for all patients with migraine.
Herbs/supplements: no longer recommended or need more study
• 2012 AAN Guidelines in 2012 from the AAN concluded that Petasites (butterbur) feverfew,
magnesium and riboflavin are probably effective.
Nonpharmacologic: may be beneficial
Neuromodulation: use electric current or a magnetic field to centrally or peripherally stimulate
the nervous system to minimize pain
3 devices (eTNS, nVNS, and sTMS) acleared for monotherapy or adjunctive therapy for
preventive migraine treatment
3 devices (nVNS, REN, and sTMS) are cleared for the acute and preventive treatment of migraine
in adolescents between 12-17 years of age
95
Migraine Prevention Medications
Indications:
• Frequent or long-lasting migraine headaches
• Migraine attacks that cause significant disability or diminished quality of life
despite appropriate acute treatment
• If needing acute therapy more than twice per week
• Contraindication to acute therapies
• Failure of acute therapies
• Serious adverse effects of acute therapies
• Risk of medication overuse headache
• Menstrual migraine
96
Selecting a Preventitive Agent
• Patient Preference
• Contraindications/adverse effects
• Take ADVANTAGE of side effect profile (i.e. topiramate for obesity)
• Comorbidities
• Depression, seizures, hypertension
• Note: doses for migraine prophylaxis may be suboptimal for other indications
• Combining agents from different classes may improve efficacy
• Goals of Treatment:
• Reduce frequency, duration, and severity of migraine attacks/headache days
• Reduce by 50% within 3 months of starting preventative treatment
• Improve response to acute treatments
• Reduce overuse of abortive medications
97
Preventive Agents Medication Classes
• Antidepressants
• Anticonvulsants
• Beta blockers
• Botulinum Toxin (Botox®)
• CGRP Antagonists
• Anticonvulsants
• Beta blockers
• Botulinum Toxin (Botox®)
• CGRP Antagonists
98
Antidepressants
Agents: Amitriptyline, venlafaxine
Considerations for therapy/ADRs:
Amitriptyline: 1st or 2nd line
Increased number of trials showed its efficacy (compared to venlafaxine)
Nortriptyline may be used if need less ADR but lack of controlled trial
ADRs: Dizziness; dry mouth; sedation (give at bedtime; if too sedating, can use
nortriptyline); weight gain; orthostatic hypotension; QT prolongation; lower seizure
threshold
Venlafaxine extended-release: 2nd line
May be beneficial in patients with co-morbid depression and anxiety disorders
ADRs: Hypertension; insomnia; worsened anxiety
Avoid with MAOI use within 12 days. Caution in patients with seizures
99
Antiepileptics
Agents: Topiramate, valproate
• Topiramate is FDA-indicated for migraine prevention
• Proven efficacy for chronic migraine prevention
Considerations for Therapy/ADRs:
• Topiramate:
• Known teratogen (causes cleft palate)
• ADRs: Weight loss; kidney stones; cognitive delay (difficulty finding words, concentrating); drowsiness; paresthesia
• Dose adjustment for renally impaired patients
• Valproate:
• Known teratogen (causes spina bifida; decreased IQ)
• ADRs: Headache; nausea; weight gain, hepatotoxicity;
thrombocytopenia; alopecia
100
Antihypertensives
• Agents: metoprolol, propranolol, timolol, candesartan, lisinopril
• Metoprolol and propranolol are FDA-indicated for migraine prevention
• Metoprolol, propranolol, and timolol are 1st-line (reduce at least a 50% reduction in migraine
frequency (atenolol and nadolol may be effective)
• Candesartan and lisinopril are 2nd-3rd line (reduce migraine days around 25%)
• Nicardipine and verapamil are 3rd line (poor evidence for verapamil)
• Considerations for Therapy/ADRs:
• Caution in patients with comorbidities (i.e., asthma, diabetes, thyroid disease)
• ADRs: Bradycardia, hypotension, depression, weight gain, dizziness (decreased exercise
tolerance)
• Beta-Blockers good in patients with comorbid HTN or angina
• If taking rizatriptan limit dose to 5 mg/dose if taking propranolol
• The dose of rizatriptan must be adjusted downward in patients who take propranolol, since propranolol increases rizatriptan levels by 70%
101
Botulinum Toxin
• Can cut 2 more headaches/mo compared to placebo ( Prevents, on average, 8 to 9
headache days and migraine/probable migraine days a month (vs 6 to 7 for placebo)
• Indicated for patient with 15 or more headaches days per month, with headaches lasting
4 or more hours per day in patients 18 and older. (It is not approved for 14 or fewer headache days a month.)
• Administered every 3 months.
• BOTOX® may cause serious side effects:
• Problems swallowing, speaking, or breathing, due to weakening of associated
muscles
• Loss of strength and all-over muscle weakness, double vision, blurred vision and
drooping eyelids, hoarseness or change or loss of voice, trouble saying words clearly,
loss of bladder control, trouble breathing, and trouble swallowing
• Do not drive a car, operate machinery until familiar with the effects
102
Calcitonin Gene-Related Peptide (CGRP) antagonists
Large molecules in the form of monoclonal antibodies directed against the CGRP receptor or ligand
Agents:
• Erenumab (Aimovig®) monthly SubQ self-injection
• Fremanezumab (Ajovy®) monthly SubQ self-injection, (quarterly option)
• Galcanezumab (Emgality®) monthly SubQ self-injection
• Eptinezumab (Vyepti®) 30 min IV infusion in clinic
ADR: Injection site reactions; CGRP causes vasodilation and could have cardiovascular effects
(studies excluded pts with CV risk factors). Erenumab reports of HTN and constipation
Use: Due to cost, Consider for patients with adherence issues, side effects, poor response, or
drug interaction concerns with oral agents. Can be combined with oral agents. Special
authorizations needed. (after 8-week trial of 2 or more other agents)
103
Cyprohepatdine
• Third-line agent
• 2 mg BID may be as effective as propranolol 40 mg BID
• Antihistamine that impacts serotonin, comes in a syrup, and may help kids sleep
• ADRs: Weight gain and sedation
• Considerations: Use caution in patients taking MAOIs or CNS depressants, patients involved in activities requiring alertness and coordination, patients in whom anticholinergic effects are
undesirable
• Considered safe in pregnancy
104
Considerations for When to Discontinue Preventative Treatment
Migraine headaches may improve independent of treatment. If the headaches are well
controlled, slowly taper the drug if possible. Many patients experience continued relief
with either a lower dose or cessation of the medication.
• Efficacy ("success") demonstrated for patients that:
• Use medication for at least 2 months at target or maximally tolerated dose
• Decrease in migraine attack frequency or number of headache days per month is reduced by 50% or more
• After 6 to 12 months of successful prophylactic therapy:
• Consider tapering and discontinuing the prophylactic medication
• If headache frequency increases as dose is reduced, increase dose and use slower taper
105
Menstrual-Associated Migraines (MAM)
Agents: Triptan or long-acting NSAID (naproxen)
Given daily for 3 days prior to and throughout menstrual cycle
Evidence (all off-label):
• “A” [Effective]: Frovatriptan
• “B” [Probably effective]: Naratriptan, zolmitriptan
• Other triptans studied: Rizatriptan, almotriptan
• Rizatriptan was only agent to demonstrate two-hour pain relief and 24-hour sustained pain relief
106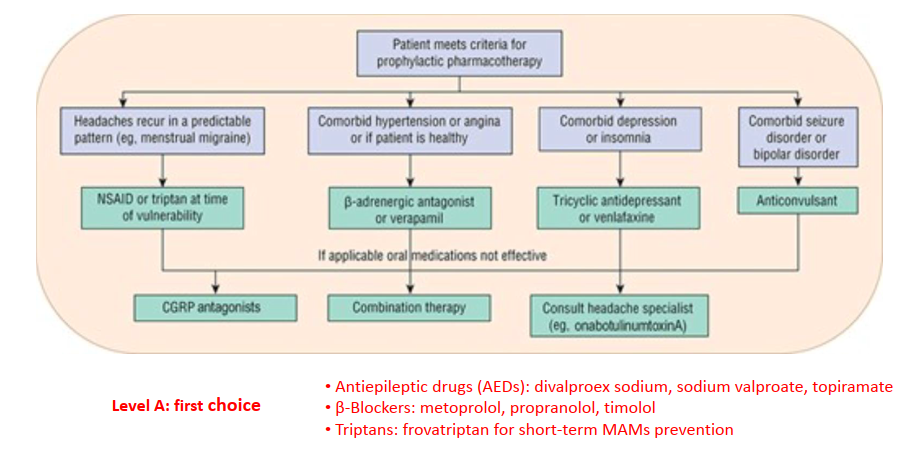
Bildverdeckung: nenne die verdeckten Beschriftungen
107
Bildverdeckung: nenne die verdeckten Beschriftungen
108
Bildverdeckung: nenne die verdeckten Beschriftungen
109
Bildverdeckung: nenne die verdeckten Beschriftungen
110
Bildverdeckung: nenne die verdeckten Beschriftungen
111
Bildverdeckung: nenne die verdeckten Beschriftungen
112
Bildverdeckung: nenne die verdeckten Beschriftungen
113
Bildverdeckung: nenne die verdeckten Beschriftungen
114
Bildverdeckung: nenne die verdeckten Beschriftungen
115
Bildverdeckung: nenne die verdeckten Beschriftungen
116
Bildverdeckung: nenne die verdeckten Beschriftungen
117
Bildverdeckung: nenne die verdeckten Beschriftungen
118
Bildverdeckung: nenne die verdeckten Beschriftungen
119
Bildverdeckung: nenne die verdeckten Beschriftungen
120
Bildverdeckung: nenne die verdeckten Beschriftungen
121
Bildverdeckung: nenne die verdeckten Beschriftungen
122
Bildverdeckung: nenne die verdeckten Beschriftungen
123
Bildverdeckung: nenne die verdeckten Beschriftungen
124
Bildverdeckung: nenne die verdeckten Beschriftungen
125
Bildverdeckung: nenne die verdeckten Beschriftungen
126
Bildverdeckung: nenne die verdeckten Beschriftungen
127
Bildverdeckung: nenne die verdeckten Beschriftungen
128
Bildverdeckung: nenne die verdeckten Beschriftungen
129
Bildverdeckung: nenne die verdeckten Beschriftungen
130
Bildverdeckung: nenne die verdeckten Beschriftungen
131
Bildverdeckung: nenne die verdeckten Beschriftungen
132
Bildverdeckung: nenne die verdeckten Beschriftungen
133
Bildverdeckung: nenne die verdeckten Beschriftungen
134
Bildverdeckung: nenne die verdeckten Beschriftungen
135
Bildverdeckung: nenne die verdeckten Beschriftungen
136
Medication Overuse Headache
≥ 15 headache days/month
Overuse of acute headache medications for > 3 months
APAP, NSAIDs: > 15 days/month
Triptan, ergot, combination medication: > 10 days/month
Most offending agents: butalbital and Narcotics
Diagnose in addition to chronic tension or migraine
Overuse of acute headache medications for > 3 months
APAP, NSAIDs: > 15 days/month
Triptan, ergot, combination medication: > 10 days/month
Most offending agents: butalbital and Narcotics
Diagnose in addition to chronic tension or migraine
137
Management of Medciation-Overuse Headache
Management:
Abortive Therapy Plan:
• Discontinue offending agent
• Switch to another abortive agent in a different class
• Taper over 2-4 weeks
• Cross-titrate with another abortive agent in a different class
• Newly initiated abortive agent should be used no more than 2
days per week
Preventative Therapy Plan: Initiate medication (controversial, limited data that prevention therapy will have an impact as takes several weeks to work)
138
Tension Type Headaches (TTH)
Most common headache type. Yearly prevalence rates for episodic TTH are ~80
percent
Unlike migraine: Generally, No nausea/vomiting, photophobia or phonophobia
≥ 2 of the following symptoms:
▪ Location: Bilateral
▪ Type of Pain: pressing or tightness; non pulsating
▪ Intensity: mild to moderate
NOT aggravated by physical activity (walking up stairs & similar routines)
Despite its frequency, few placebo-controlled preventive therapeutic trials have been conducted in TTH
139
TTH Classifcation
Infrequent episodic: < 1 headache/month
Frequent episodic: 1-14 headaches/month, for at least 3 months or more
Chronic: ≥ 15 headaches/month, for at least 3 months or more
Frequent episodic: 1-14 headaches/month, for at least 3 months or more
Chronic: ≥ 15 headaches/month, for at least 3 months or more
140
TTH Management
Non-Pharmacologic: CBT, acupuncture, heat/ice, massage, rest, and biofeedback
▪ Many patients have comorbid sleep problems, anxiety, stress, or depression
▪ Check for teeth clinching at night (mouth night guard)
Acute Treatment: OTC analgesics
▪ NSAIDS, aspirin, acetaminophen (less effective but preferred if pregnant)
▪ If poor response to monotherapy add (i.e two tablets of combined acetaminophen 250 mg, aspirin 250 mg, and caffeine 65 mg)
▪ On average, limit medication to ten days per month and 2 doses per day- to minimize overuse headache risk
141
TTH Prevention
Tricyclic antidepressants:
• Amitriptyline)- [1st Line]: 10-12.5 mg nightly, then increase by 10-12.5 mg every 2-3 weeks to max 100-125mg/d
• Increased risk of cardiac conduction abnormality and arrhythmia
• Weight gain and sedation
• Nortriptyline- less sedating (mild to moderate). Weight gain
• Protriptyline- nonsedating, the mild stimulating effect can worsen anxiety and
panic disorders. Weight loss.
• Less evidence: mirtazapine, venlafaxine, tizanidine, gabapentin, topiramate
• SSRIs: not effective
• Behavioral therapies: CBT, relaxation, biofeedback, regulate
sleep/exercise/meals
142
Cluster Headache
• At least 5 attacks fulfilling the criteria:
• Severe or very severe unilateral orbital, supraorbital, and/or temporal pain lasting 15-180 minutes (without treatment)
• Either one or both of the following:
1. a sense of restlessness or agitation
2. At least one symptom, ipsilateral to side of headache: Forehead and facial sweating,
flushing, sensation of fullness in the ear, lacrimation, nasal congestion and/or rhinorrhea,
OR eyelid edema
• Attacks happen anywhere from eight per day to every other day for more
than half of the time when active
• Half the patients may also have associated symptoms similar to
migraine(photophobia, phonophobia)
143
Cluster Headache Types
• Episodic: occurring in periods lasting from 7 days to 1 year, separated by pain-free periods lasting at least 3 months. Generally, 6-12 weeks with attacks more common in spring and autumn.
• Chronic: Occurring without a remission period, or with remission lasting <3 months, for at least a year
• Triggers: alcohol, foods with nitrates, Nitroglycerine, strong odors,
• Chronic: Occurring without a remission period, or with remission lasting <3 months, for at least a year
• Triggers: alcohol, foods with nitrates, Nitroglycerine, strong odors,
144
Cluster Headache Management
• Acute:
• 100% oxygen: 6-10 liters per minute administered by face mask
• Sumatriptan SQ/IN, Zolmitriptan IN at pain onset
• Prevention: (in order of preference). Treat for up to 4 weeks after an attacks have settled, then gradually taper:
1. Verapamil for episodic or chronic cluster headache - 1st line
2. Topiramate, melatonin
3. Lithium carbonate for episodic and chronic cluster headache attacks check cp 12
hr after dose, every 1-2 mo. (0.4-1.2 mEq (mmol)/L ) Requires regular monitoring
• Used as resort option when alternatives fail or are contraindicated
4. Galcanezumab (Emgality)-approved for episodic cluster, \$\$, no long-term data
145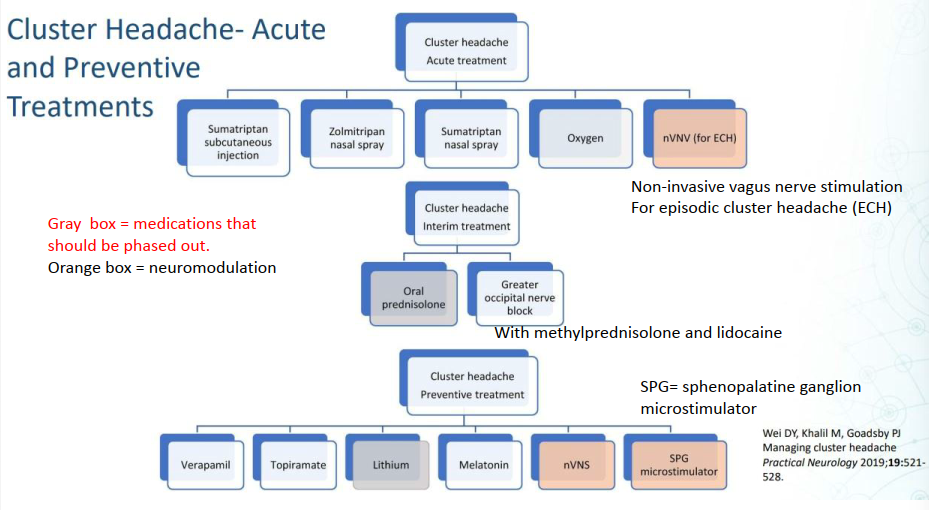
Bildverdeckung: nenne die verdeckten Beschriftungen
146
Bildverdeckung: nenne die verdeckten Beschriftungen
147
Bildverdeckung: nenne die verdeckten Beschriftungen
148
Bildverdeckung: nenne die verdeckten Beschriftungen
149
Bildverdeckung: nenne die verdeckten Beschriftungen
150
Bildverdeckung: nenne die verdeckten Beschriftungen
Mehr Karteikarten
CHEM 101 Test 2 soil, metals and paintsNaturwissenschaften · EnglischEmanexperience and perception idiomsGeschichte und Geisteswissenschaften · Lateinanya€urazy czaszkowo mózgowe cz.1 WSTĘPPolnischczyzowComputer OrganizationInformatik · EnglischJoshuaschéma FranzösischOcéanePrehistoric Artworks and DatesGeschichte und Geisteswissenschaften · EnglischAvaVocabulary Sets 25-26 (SAT Style)SprachenMilesintro lecture 1Naturwissenschaften · EnglischKrisMedCardsChem 121 MemorizationNaturwissenschaften · EnglischVioletictInformatik · EnglischKidistSociology Test #1Psychologie und Gesellschaft · EnglischRohanMetabolismo energéticoSpanischLuisa
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

