Sedative-Hypnotics, Lithium
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Benzodiazepines
• Commonly used sedatives/anxiolytics
• Other uses: xenobiotic-induced seizures, sedative–hypnotic withdrawal, and psychomotor agitation
• MOA: Enhances the inhibitory effect of GABA on neuronal excitability by increased neuronal membrane permeability to chloride ions. This shift in chloride results in hyperpolarization (a less excitable state) and stabilization
• Benzodiazepine receptors linked to GABA-A receptors. These receptors are the primary mediators of inhibitory neurotransmission in the brain
2
$GABA_A$ Receptor
Gated Chloride channel
• The benzodiazepine binding site is located at the interface of an α and a γ subunit
• Benzodiazepine receptors linked to GABA-A receptors. These receptors are the primary mediators of inhibitory neurotransmission in the brain
• Some nomenclature term GABAA receptors with α1 isoforms as benzodiazepine type 1 (BZ1) receptors and those with predominance of α2, α3, and α5 isoforms as benzodiazepine type 2 (BZ2) receptors
3
Benzodiazepines and Propylene Glycol Toxicity
• Propylene glycol is a solvent used to deliver IV lorazepam and diazepam
• Propylene glycol toxic effects include hyperosmolality, increased anion gap metabolic acidosis, acute kidney injury, and sepsis-like syndrome
• Treatment includes hemodialysis to remove propylene glycol
• Prevention is best achieved by limiting the dose of propylene glycol infused (some hospitals limit lorazepam drip to < 24 hours)
• Of note, IV midazolam infusions do not contain propylene glycol
4
Benzodiazepines in ICU Sedation
• Ex. Continuous infusion for mechanical ventilation
• ↑ risk delirium, prolonged sedation, mechanical ventilation or ICU days compared to agents such propofol or dexmedetomidine
• Benzodiazepines PK contributing to prolonged sedation
• Large Vd with lipophilicity → accumulation in lipid-rich areas such as the central nervous system and adipose tissue → slowly re-release into plasma
• Many metabolized via CYP P450 system, some with active metabolites
• Age and/or disease changes to liver and renal function → drug accumulation
5
GABA-Receptor Acting (Benzo-Like) Sleep Aids
• Examples: zolpidem, zaleplon, eszopiclone
• MOA: Selectively bind the α1 subunit on GABA-A receptors and thus cause primarily sedation and not anxiolysis at therapeutic doses
• Safety Warnings
• Risk of fall specially in age ≥ 65 (Beer’s criteria)
• Hallucinations and “dream-like” confusion
• Withdrawal/rebound insomnia
• MOA: Selectively bind the α1 subunit on GABA-A receptors and thus cause primarily sedation and not anxiolysis at therapeutic doses
• Safety Warnings
• Risk of fall specially in age ≥ 65 (Beer’s criteria)
• Hallucinations and “dream-like” confusion
• Withdrawal/rebound insomnia
6
Melatonin Receptor Agonists
• Examples: melatonin, tasimelton, ramelteon
• MOA: selective agonisms of melatonin receptors MT1 and MT2 within the suprachiasmic nucleus of the hypothalamus, an area responsible for determination of circadian rhythms and synchronization of the sleep-
wake cycle
• Adverse effects are usually mild and include drowsiness, dizziness, fatigue, and headache.
• Does not seem to be associated with withdrawal or rebound insomnia
7
Antihistamines (used for sleep, anxiety)
• Examples: diphenhydramine, doxylamine (ingredient in Nyquil, OTC sleep aid), hydroxyzine
• Also on Beer’s Criteria list for potentially inappropriate medication use in older adults esp. when used as a hypnotic
• MOA: Disrupts wake-promoting histaminergic neurotransmission from the tuberomammillary nucleus within the hypothalmus by antagonism of the H1 receptor. Activity at muscarinic, serotonergic, and dopaminergic receptors in the brain may also produce anxiolytic effects.
8
Sedative-Hypnotics and Beer’s Criteria
American Geriatrics Society/Beer’s Criteria
• Highlights potentially inappropriate medication use and drug interactions in older adults
• Identifies medication classes that may have an unfavorable balance of benefits and harms compared with alternative treatment options (esp. for disease states such as insomnia)
• Warnings regarding most sedative-hypnotics (risks of falls/delirium) and lithium (especially in the setting of polypharmacy)
9
Non-Benzodiazepine IV Sedatives in Critical Care
• ER/ICU Use – Not all inclusive
• Sedation for Rapid Sequence Intubation (Bolus – IV Push)
• Etomidate
• Ketamine
• Propofol
• Sedation for Mechanically Ventilated Patients (Continuous IV Infusion)
• Propofol
• Dexmedetomidine
• Sedation for Rapid Sequence Intubation (Bolus – IV Push)
• Etomidate
• Ketamine
• Propofol
• Sedation for Mechanically Ventilated Patients (Continuous IV Infusion)
• Propofol
• Dexmedetomidine
10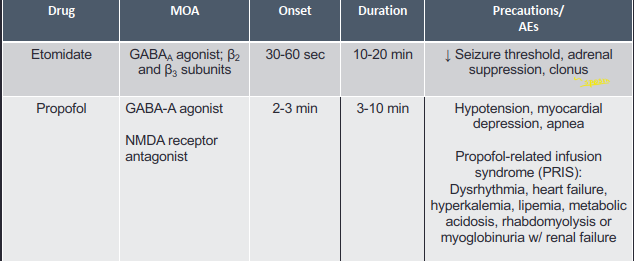
Bildverdeckung: nenne die verdeckten Beschriftungen
11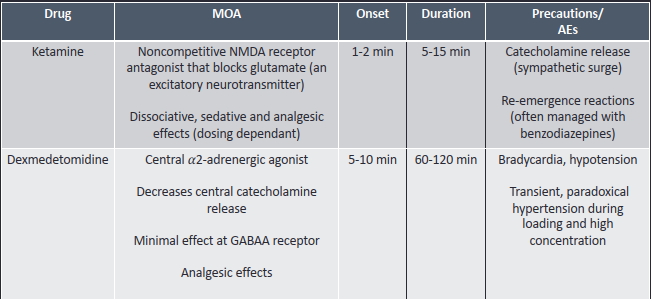
Bildverdeckung: nenne die verdeckten Beschriftungen
12
Bildverdeckung: nenne die verdeckten Beschriftungen
13
Strategies to Reduce Over-Sedation, ICU delirium
• Pain management and restorative sleep
• Sedative choice - avoidance of continuous infusion benzodiazepines in preference of propofol or dexmedetomidine
• Continuous intravenous hypnotics combined with daily interruption of sedatives
• Continuous titration of hypnotics according to predefined goals of comfort and consciousness, with frequent patient assessments and prescription changes -preference for maintaining light levels of sedation in allowable disease states
• Use of alternatives to continuous intravenous hypnotics (including IV bolus or enteral route hypnotics)
14
Ketamine for Excited Delirium in Pre-Hospital Setting
• Pro: IM Ketamine maybe useful to quickly sedate patients who may be at danger to self and/or others (safety data in procedural sedation though this is a more controlled settings)
• Cons: If a catecholamine surge is at least partially responsible for the medical and psychiatric symptoms of delirious victims, then ketamine might exacerbate the underlying problem by acting as a stimulant of the cardiovascular system (also limited safety data in the less controlled setting of law enforcement/paramedics use)
• Cons: If a catecholamine surge is at least partially responsible for the medical and psychiatric symptoms of delirious victims, then ketamine might exacerbate the underlying problem by acting as a stimulant of the cardiovascular system (also limited safety data in the less controlled setting of law enforcement/paramedics use)
15
Lithium
• Used for prophylaxis and treatment of bipolar disorder
• Ability to improve both the manic and the depressive symptoms, as well as augment the therapeutic efficacy of other approaches that have failed to achieve symptom remission
• Narrow therapeutic index – needs monitoring
• Ability to improve both the manic and the depressive symptoms, as well as augment the therapeutic efficacy of other approaches that have failed to achieve symptom remission
• Narrow therapeutic index – needs monitoring
16
Lithium Pharmacology
Alters cation transport across nerve/muscle cell membranes
Influences serotonin and/or norepinephrine reuptake
Inhibits secondary messenger system
Increases glutamate clearance
Enhances neurotropic factor expression
Inhibits activity of apoptotic glycogen synthase kinase
Influences serotonin and/or norepinephrine reuptake
Inhibits secondary messenger system
Increases glutamate clearance
Enhances neurotropic factor expression
Inhibits activity of apoptotic glycogen synthase kinase
17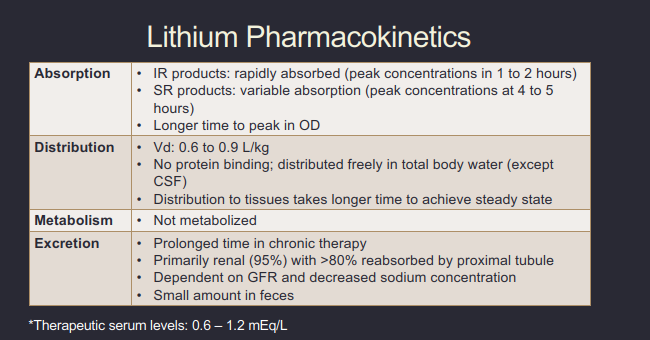
Bildverdeckung: nenne die verdeckten Beschriftungen
18
Bildverdeckung: nenne die verdeckten Beschriftungen
19
Bildverdeckung: nenne die verdeckten Beschriftungen
20
Bildverdeckung: nenne die verdeckten Beschriftungen
21
Lithium Toxicity Risk Factors
Older age (↓ GFR)
Drug interactions
Decreased sodium intake
Low-output heart failure
Drug interactions
Decreased sodium intake
Low-output heart failure
22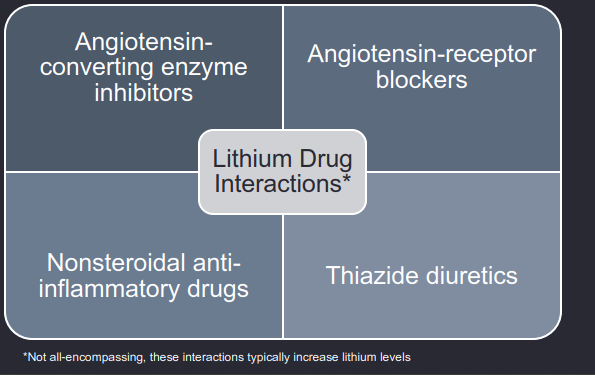
Bildverdeckung: nenne die verdeckten Beschriftungen
23
Bildverdeckung: nenne die verdeckten Beschriftungen
24
Bildverdeckung: nenne die verdeckten Beschriftungen
25
Bildverdeckung: nenne die verdeckten Beschriftungen
26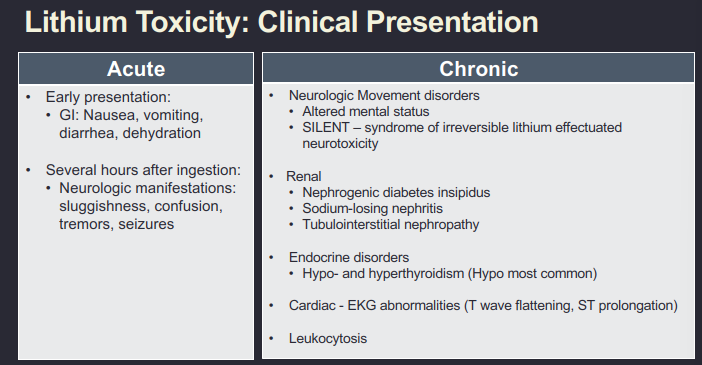
Bildverdeckung: nenne die verdeckten Beschriftungen
27
Bildverdeckung: nenne die verdeckten Beschriftungen
28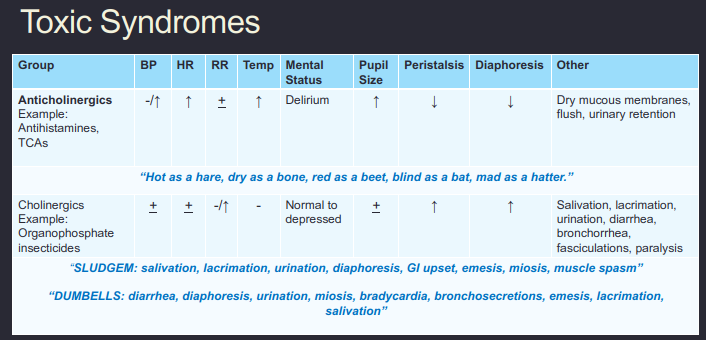
Bildverdeckung: nenne die verdeckten Beschriftungen
29
Bildverdeckung: nenne die verdeckten Beschriftungen
30
Bildverdeckung: nenne die verdeckten Beschriftungen
31
Bildverdeckung: nenne die verdeckten Beschriftungen
32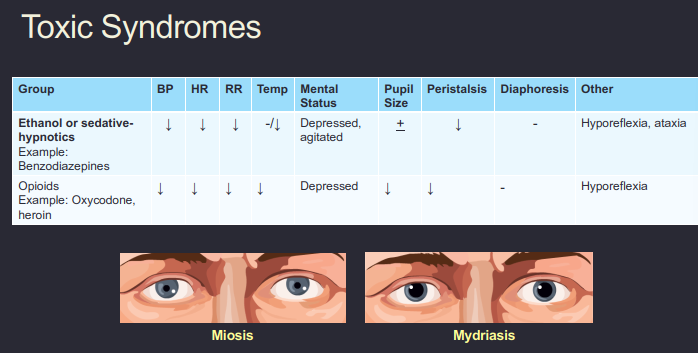
Bildverdeckung: nenne die verdeckten Beschriftungen
33
Bildverdeckung: nenne die verdeckten Beschriftungen
34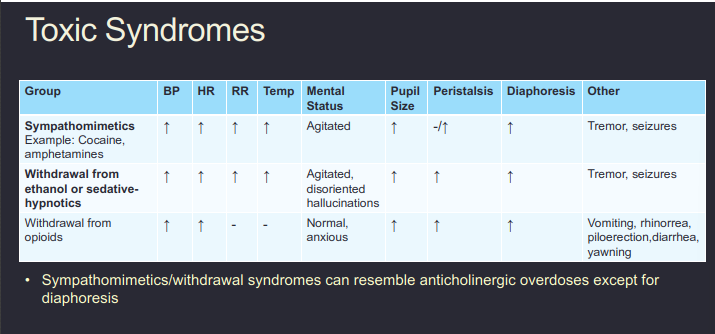
Bildverdeckung: nenne die verdeckten Beschriftungen
35
Bildverdeckung: nenne die verdeckten Beschriftungen
36
Bildverdeckung: nenne die verdeckten Beschriftungen
37
Using Toxicology Tests
• Rationale
• To confirm or exclude suspected toxic exposure (qualitative tests) and intensity of exposure
(quantitative tests)
• Limitations
• Qualitative tests (Tox Screen)
• False positives and false negatives
• Use of metabolites for detection suggests recent drug use but not current toxicity
• Many dangerous substances can still be missed …
• Quantitative tests (APAP level, digoxin level, etc)
• Need to be specifically ordered
• Determination of “toxic levels” multifactorial – timing of drug level relative to time ingestion and patient
factors (e.g. phenytoin and hypoalbuminemia or renal dysfunction)
38
Quantitative Serum Assays
Typically used for lithium
39
Qualitative Urine Assays
Typically used for benzodiazepines
40
Dection time for benzodiazepines
2-10 days; sertraline may cause false positives
41
Benzodiazepines and Urine Tox Screens
• Many benzodiazepines not detected in standard urine screenings for drugs of abuse (most look for oxazepam metabolite)
• Benzodiazepines such as alprazolam, clonazepam, lorazepam, midazolam, and triazolam are not detected by any screening test that relies on the detection of oxazepam
• Benzodiazepine-like "z" drugs used as sleep aids, such as eszopiclone, zaleplon, zolpidem, and zopiclone not routinely detected
• Benzodiazepines such as alprazolam, clonazepam, lorazepam, midazolam, and triazolam are not detected by any screening test that relies on the detection of oxazepam
• Benzodiazepine-like "z" drugs used as sleep aids, such as eszopiclone, zaleplon, zolpidem, and zopiclone not routinely detected
42
Lithium Levels and Toxicity
• In acute ingestions, lithium concentration used as a marker of exposure and response to therapy (ie. using serial levels to check therapy efficacy) but not necessarily as a determinant of toxicity or treatment
• Use history, symptoms, and clinical signs, rather than the absolute lithium concentration, should guide therapy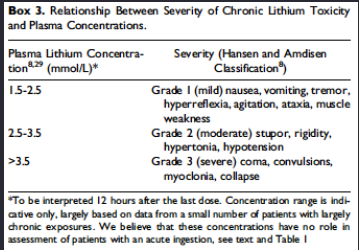
• Use history, symptoms, and clinical signs, rather than the absolute lithium concentration, should guide therapy
43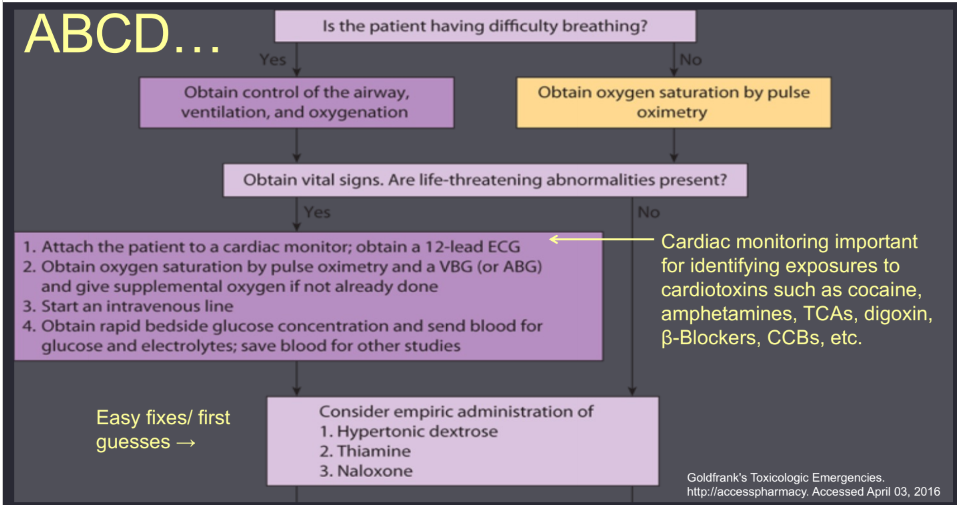
Bildverdeckung: nenne die verdeckten Beschriftungen
44
Bildverdeckung: nenne die verdeckten Beschriftungen
45
Bildverdeckung: nenne die verdeckten Beschriftungen
46
Bildverdeckung: nenne die verdeckten Beschriftungen
47
Bildverdeckung: nenne die verdeckten Beschriftungen
48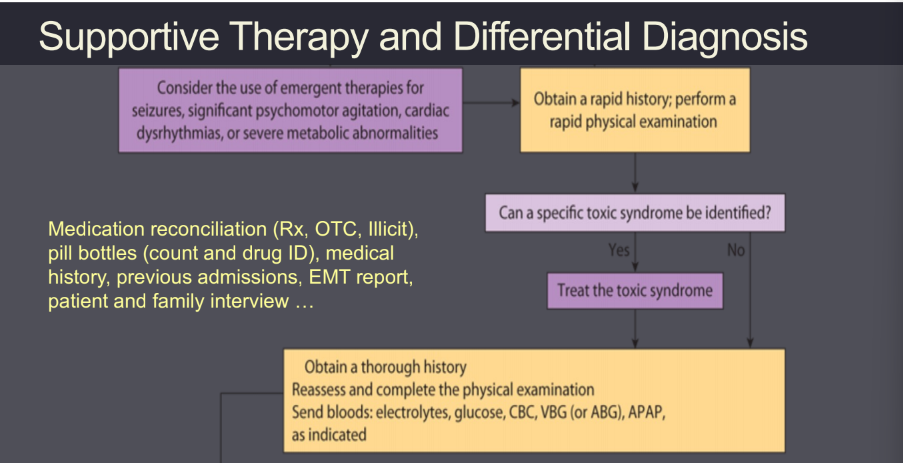
Bildverdeckung: nenne die verdeckten Beschriftungen
49
Bildverdeckung: nenne die verdeckten Beschriftungen
50
Bildverdeckung: nenne die verdeckten Beschriftungen
51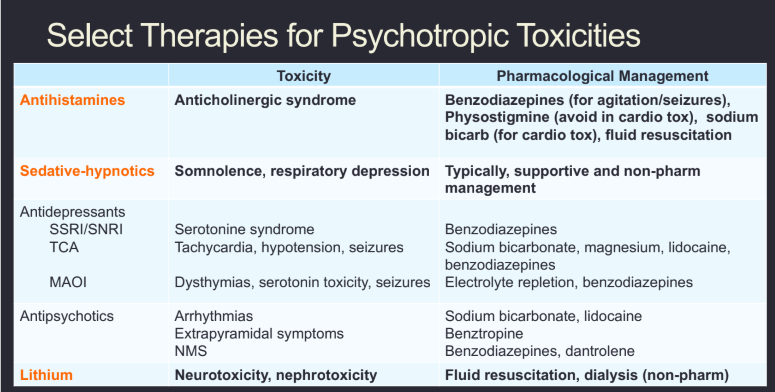
Bildverdeckung: nenne die verdeckten Beschriftungen
52
Bildverdeckung: nenne die verdeckten Beschriftungen
53
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Activated Charcoal
Indications:
• Consider for patients ingesting a potentially toxic amount of poison
• Time from ingestions < 60 min (benefit undetermined in > 60 mins)
Contraindications:
• Unprotected or compromised airways (unconscious and not intubated)
• Increased risk or increased severity of aspiration (ingestion of hydrocarbons) or GI hemorrhage or perforation
• Does not bind well, do not use for:
• Alcohol (ethanol, methanol, isopropyl alcohol, glycols, and acetone)
• Metals (lithium, iron)
• Cyanide and other rapid-acting medications
• Hydrocarbons (petroleum distillates and plant hydrocarbons such as pine
oil) due to increase risk of aspiration
55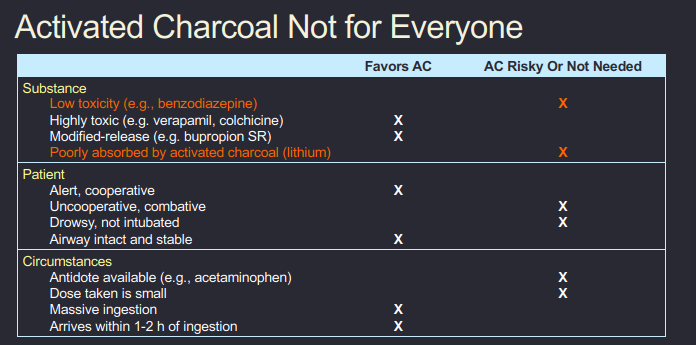
Bildverdeckung: nenne die verdeckten Beschriftungen
56
Bildverdeckung: nenne die verdeckten Beschriftungen
57
Whole Bowel Irrigation (WBI)
Technique:
• Oral or nasogastric administration of polyethylene glycol electrolyte lavage solution (PEG-ELS or Go-Lytely)
Indications:
• Ingestions involving large acute ingestions sustained-release preparations of lithium (not chronic toxicity)
• Ingestions of large amounts of iron
• Removal of ingested packets of illicit drugs
Contraindications:
• Unprotected or compromised airway
• Hemodynamic instability
• Uncontrollable vomiting
• Bowel perforation, obstruction, or ileus
• Significant GI hemorrhage
58
Diuresis
• Use of isotonic sodium-containing solutions such as NS or lactated ringers with or without diuretic
• Loop diuretics have theoretical benefit in reducing lithium reabsorption but little evidence supporting efficacy, ironically loop diuretic use is a risk factor for lithium toxicity and is mentioned in Beer’s Criteria
• ↑ GFR can result in ↑ excretion of low-molecular weight drugs such as lithium
• Loop diuretics have theoretical benefit in reducing lithium reabsorption but little evidence supporting efficacy, ironically loop diuretic use is a risk factor for lithium toxicity and is mentioned in Beer’s Criteria
• ↑ GFR can result in ↑ excretion of low-molecular weight drugs such as lithium
59
Sodium Polystyene Sulfonate
Ion exchange resin for mgmt. of hyperkalemia may decrease lithium absorption – however, impractical to use due large volumes needed for acute poisonings
60
Dialysis
• Lithium has several physical properties that make it an easily dialyzable
• Small
• Unbound to plasma proteins
• Small volume of distribution (0.8-1.2 L/kg)
• Relatively slow endogenous clearance (15-20 mL/min)
• Small
• Unbound to plasma proteins
• Small volume of distribution (0.8-1.2 L/kg)
• Relatively slow endogenous clearance (15-20 mL/min)
61
Flumazenil for BZD Overdose
• Mechanism: Competitive antagonist at the benzodiazepine-receptor binding site on GABA
needed
• Onset of action: 1-2 minutes
• PK Considerations
• T1/2 range: 41 – 79 min
Limitations
• Rare morbidity and mortality associated with bzd use
• Not consistently shown to reverse bzd respiratory ↓
• In bzd-dependent patients, flumazenil may precipitate withdrawal, including seizures
• In multidrug ingestions, flumazenil may remove protective of effect of bzd and unmask cardiac arrhythmias and seizures
62
Flumazenil for Sleep Aids
• Flumazenil also reverses the hypnotic and cognitive effects of some sleep aids
• Examples: Zolpidem, Zaleplon, Zopiclone, and Eszopiclone
• Bind preferentially to the benzodiazepine site subtype in the brain that contains the $GABA_A$ α1 subunit.
• Have lower affinity for benzodiazepine sites that contain the other α isoforms; therefore, they have potent hypnotic effects with less potential for dependence and antiepileptics properties
• Flumazenil reversal of these agents may be safer here than in the case of benzodiazepines given the lack of antiepileptic effects
63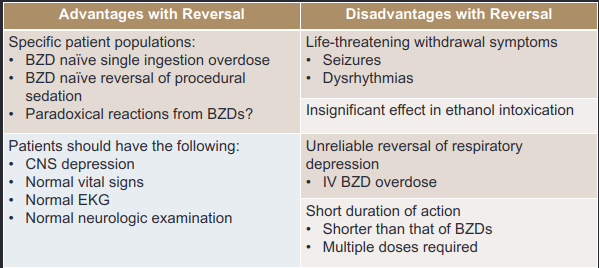
Bildverdeckung: nenne die verdeckten Beschriftungen
64
Bildverdeckung: nenne die verdeckten Beschriftungen
65
Bildverdeckung: nenne die verdeckten Beschriftungen
66
Bildverdeckung: nenne die verdeckten Beschriftungen
67
Flumazenil Contraindications
Seizure History
Current Seizure Treatment
Co-ingestion that provokes seizures or arrhythmias
Long-term BZD Use
Evidence of TCA use on EKG
Hypoxia
Hypoventilation
Hypotension
Head Trauma
Current Seizure Treatment
Co-ingestion that provokes seizures or arrhythmias
Long-term BZD Use
Evidence of TCA use on EKG
Hypoxia
Hypoventilation
Hypotension
Head Trauma
68
Flumazenil Indications
Pure benzodiazepine or benzo-like sleep aid with:
CNS depression
Normal vital signs, including SaO2
Normal ECG findings
Otherwise normal neurologicexam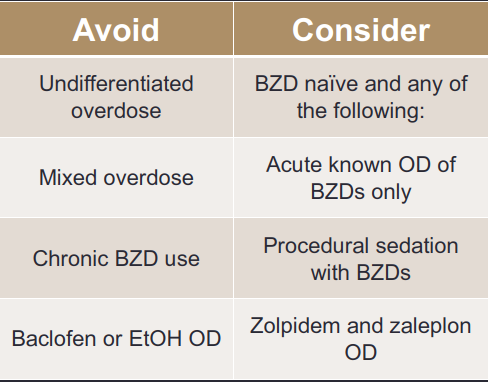
CNS depression
Normal vital signs, including SaO2
Normal ECG findings
Otherwise normal neurologicexam
69
Benzodiazepines for Drug-Induced Seizures
• Unlike in traumatic or epileptic seizure disorders which arise from a localized seizure focus, drug-induced seizures result from a global ↓ in seizure threshold, either from a decrease in GABAergic tone or an increase in excitatory amino acid neurotransmission
• Therefore, non–sedative–hypnotic antiepileptics such as phenytoin are likely to be ineffective and should be avoided
• Second-line agents – phenobarbital, propofol if not controlled by benzodiazepines (with appropriate management of airway, ventilation, and circulation)
• Therefore, non–sedative–hypnotic antiepileptics such as phenytoin are likely to be ineffective and should be avoided
• Second-line agents – phenobarbital, propofol if not controlled by benzodiazepines (with appropriate management of airway, ventilation, and circulation)
70
Common Adult Benzodiazepines Doses for Seizures
• Lorazepam (Ativan) 2-4 mg IV
• Diazepam (Valium) 5-10 mg IV
• Midazolam (Versed) 5-10 mg IV
• Diazepam (Valium) 5-10 mg IV
• Midazolam (Versed) 5-10 mg IV
71
IV Lorazepam for Seizure Control
• Benzodiazepine of choice in status
• Time to stop seizures 2-10 mins
• Slower than diazepam or midazolam but lasts longer (6-24 hrs)
• Diazepam and midazolam have high lipid solubility and can therefore rapidly cross the blood-
brain barrier.
• But because of subsequent redistribution of the drug into adipose tissue, duration of CNS activity
may be shorter than lorazepam.
• Seizure control within 20 mins AND
• Maintenance of seizure free activity next 40 mins
• Lorazepam equivalent to diazepam + phenytoin
• Lorazepam superior to phenytoin alone
72
Lorazepam
• IV lorazepam often kept in the fridge to increase shelf life
• Delayed of onset may lead to “dose-stacking” and prolonged sedation in some disease states
• Delayed of onset may lead to “dose-stacking” and prolonged sedation in some disease states
73
Midazolam
• Preferred for intramuscular (IM midazolam shown to be at least as safe and effective as intravenous
lorazepam for prehospital seizure cessation), intranasal or buccal therapy.
• Also preferred if continuous infusion of a benzodiazepine is required for refractory status (IV formulation does not contain propylene glycol).
• Generally, too short acting for withdrawal management (also no tablet form)
• However, fast and short acting may make this drug a consideration for psychomotor agitation with cocaine
74
Diazepam
• Preferred for rectal administration (ex. home use in children)
• Rapid effect and active metabolites may prolong duration making it favorable for mild-moderate withdrawal
management
• Rapid effect and active metabolites may prolong duration making it favorable for mild-moderate withdrawal
management
75
Bildverdeckung: nenne die verdeckten Beschriftungen
76
Bildverdeckung: nenne die verdeckten Beschriftungen
77
Bildverdeckung: nenne die verdeckten Beschriftungen
78
Bildverdeckung: nenne die verdeckten Beschriftungen
Mehr Karteikarten: Medizin und Gesundheit
Glaucoma and Otitis ExternaMedizin und Gesundheit · EnglischbaileeLecture 3 - ImmunopathyMedizin und Gesundheit · EnglischkarebearACLSMedizin und Gesundheit · EnglischwoahkathyAcute Heart FailureMedizin und Gesundheit · EnglischAveryCushing's and Addison'sMedizin und Gesundheit · EnglischcathsimsNeuro FinalMedizin und Gesundheit · EnglischZZLeprosy (Hansen's DiseaseMedizin und Gesundheit · EnglischKatlynKEEnterotoxicosisMedizin und Gesundheit · EnglischcaeChapter 2: SuffixesMedizin und Gesundheit · EnglischJulieNeck AnatomyMedizin und Gesundheit · EnglischSaraChapter 14: Cranial NervesMedizin und Gesundheit · EnglischLucieChapter 2: The Human Body in Health and DiseaseMedizin und Gesundheit · Englischfortwinny
Alle Decks: Medizin und Gesundheit
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

