Pathoma Chapters 1-3: Growth Adaptations & Cell Injury
Réviser ces flashcardsGratuit · répétition espacée · iPhone, Android, Mac et web
Les 300 premières cartes sur 371
1
An increase in stress on an organ leads to?
An increase in organ size by hypertrophy or hyperplasia.
2
By what three general processes does cellular hypertrophy occur?
Gene activation Increased Protein synthesis
Increased production of organelles.
Increased production of organelles.
3
By what general mechanism does hyperplasia occur?
Production of new cells from stem cells.
4
Is the pregnant uterus an example of hypertrophy or hyperplasia?
Both
5
What is a permanent tissue? Can a permanent tissue grow? What are the (3) permanent tissues?
A permanent tissue is one that cannot make new cells (no lingering stem cells/progenitors).
Permanent tissues can only grow by hypertrophy.
Skeletal muscle, cardiac muscle, and nerve.
Permanent tissues can only grow by hypertrophy.
Skeletal muscle, cardiac muscle, and nerve.
6
How does the heart respond to persistent hypertension? What are the two basic types of cardiac hypertrophy and what causes them?
Being a permanent tissue, it grows via hypertrophy.
Pressure overload → concentric hypertrophy (sarcomeres added in parallel. HCM)
Volume overload → eccentric hypertrophy (sarcomeres added in sequence. DCM)
Pressure overload → concentric hypertrophy (sarcomeres added in parallel. HCM)
Volume overload → eccentric hypertrophy (sarcomeres added in sequence. DCM)
7
What concern exists with endometrial hyperplasia? What hyperplastic process doesn't carry this same concern?
As a general rule: pathologic hyperplasias increase risk for cancer.
Endometrial hyperplasia is a pathologic hyperplasia (caused by excess estrogen secretion) that carries a risk for progression to dysplasia and eventually cancer.
BPH is a type of pathologic hyperplasia does not increase the risk for cancer (is an exception to the rule)
Endometrial hyperplasia is a pathologic hyperplasia (caused by excess estrogen secretion) that carries a risk for progression to dysplasia and eventually cancer.
BPH is a type of pathologic hyperplasia does not increase the risk for cancer (is an exception to the rule)
8
What are three examples of "decreases in stress" that lead to atrophy?
Decreased hormonal stimulation (breast atrophy) Disuse (muscle atrophy)
Decreased nutrient\/blood supply (kidney atrophy)
Decreased nutrient\/blood supply (kidney atrophy)
9
What cellular changes does atrophy represent?
Decrease in size and number of cells
10
How is cell number decreased in an atrophic process?
Apoptosis
11
In what two ways is cell size reduced in atrophy?
Ubiquitin-proteosome degradation of the cytoskeleton and autophagy of cellular components.
12
What is ubiquitin-proteosome degradation?
Proteins (in atrophic processes, intermediate filaments of the cytoskeleton) are tagged with ubiquitin and destroyed by proteosomes.
13
How does autophagy occur in atrophy?
Autophagic vacuoles engulf cellular components that are no longer needed.These vacuoles then fuse with lysosomes.
14
What does a change in stress on an organ lead to?
Metaplasia
15
What is metaplasia?
A change in cell type, most commonly involving surface epithelium (changing to a type more suitable to handle the change in stress)
16
Describe the metaplastic process observed in Barrett esophagus:
Change from non-keratinizing stratified squamous (handles friction of food bolus) to non-ciliated columnar with goblet cells (better for handling acid).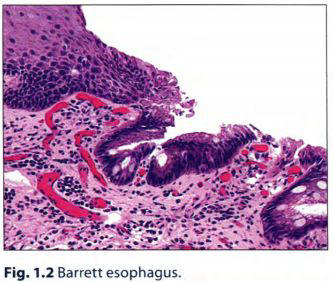
17
How does metaplasia occur?
Reprogramming of stem cells
18
Is metaplasia reversible?
Yes, in theory, with the removal of the stressor.
19
How do you treat Barrett esophagus?
Remove the stressor, i.e. treat the acid reflux
20
Are we concerned about metaplastic processes?
Yes - metaplasia can progress to dysplasia and eventually cancer
21
Does all metaplasia lead to cancer? Can you name a metaplastic process that has 0% chance of causing cancer?
Though most types of metaplasias can theoretically progress to cancer (e.g. Barrett esophagus->adenocarcinoma), many do not.
Apocrine metaplasia of breast has no propensity for malignant transformation
Apocrine metaplasia of breast has no propensity for malignant transformation
22
What processes is vitamin A essential for?
It's necessary for differentiation of specialized epithelial surfaces (e.g. conjunctiva), and essential for the maturation of certain immune cells (such as neutrophils).
*Note: also helps reduce mortality in measles
*Note: also helps reduce mortality in measles
23
Describe the pathological effects of vitamin A deficiency:
Deficiency of vitamin A results in metaplastic specialized epithelium. For example, the squamous epithelium of the conjunctiva undergoes metaplasia into stratified keratinizing squamous epithelium. This is keratomalacia.
Vitamin A is also important for maturation of immune cells. Remember that retinoic acid (vitmain A derivative) is important for neutrophil maturation (remember, ATRA is used to treat APL).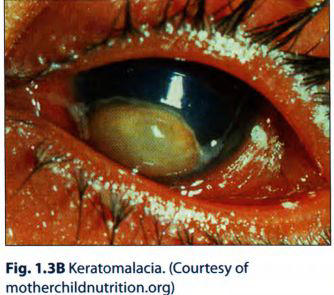
Vitamin A is also important for maturation of immune cells. Remember that retinoic acid (vitmain A derivative) is important for neutrophil maturation (remember, ATRA is used to treat APL).
24
What is myositis ossificans?
Inflammation of the skeletal muscle induces metaplastic change in the connective tissue of the muscle to produce bone.
*Note: it's clinically important to differentiate this process from osteosarcoma. myositis ossificans is clearly detached from bone on imaging. osteosarcoma would not be.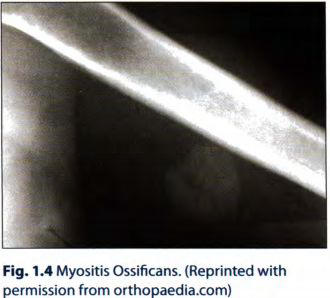
*Note: it's clinically important to differentiate this process from osteosarcoma. myositis ossificans is clearly detached from bone on imaging. osteosarcoma would not be.
25
What is dysplasia?
Disordered cellular growth. Often refers to proliferation of precancerous cells.
26
What pathologic proliferation is a precursor to cervical cancer? How is it categorized?
Cervical intraepithelial neoplasia (CIN), which is a dysplastic process.
A: CIN1: dysplastic cells in lower 1/3 of epithelium
B: CIN2: dysplastic cells in lower 2/3 of epithelium
C: CIN3: dysplastic squamous cells throughout full thickness of epithelium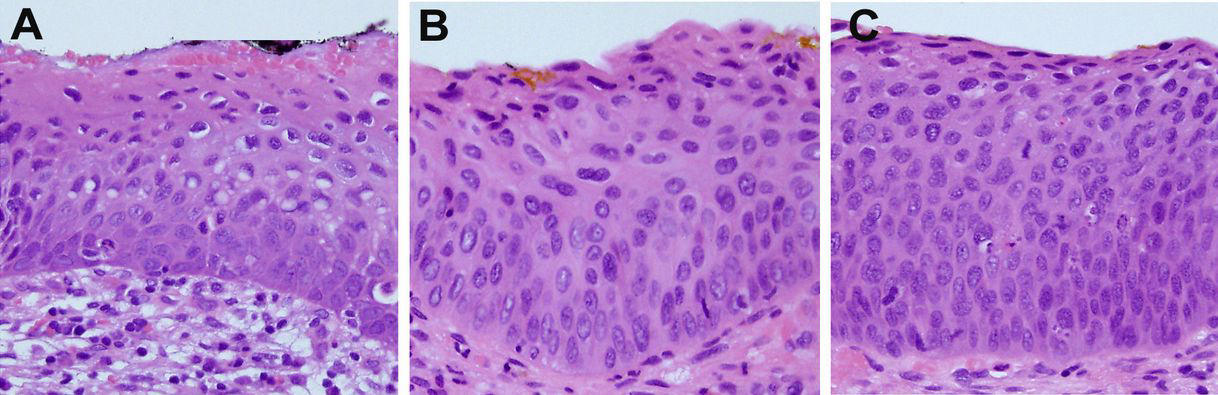
A: CIN1: dysplastic cells in lower 1/3 of epithelium
B: CIN2: dysplastic cells in lower 2/3 of epithelium
C: CIN3: dysplastic squamous cells throughout full thickness of epithelium
27
What processes can precede a dysplastic process?
Longstanding pathologic hyperplasia (e.g. endometrial hyperplasia) or metaplasia (e.g. Barrett esophagus)
28
Is dysplasia reversible?
Yes, in theory, with alleviation of the stress. If it persists it can progress to carcinoma, which is irreversible.
29
What is aplasia? Example?
Failure of cell production during embryogenesis (e.g. unilateral renal agenesis).
30
What is hypoplasia? Example?
Decrease in cell production during embryogenesis, resulting in a small organ (e.g. streak ovary in Turner syndrome).
31
When does cellular injury occur?
When a stress exceeds the cell's ability to adapt
32
Which is more susceptible to ischemic injury: neurons or skeletal myocytes?
Neurons are highly susceptible (3-5 minutes), skeletal muscle is fairly resistant (long periods of time).
33
How does the rapidity of a stressor affect the response of the cells (e.g. ischemia)?
Slowly developing ischemia (e.g. renal artery atherosclerosis) will lead to atrophy.
Acute ischemia (e.g. renal artery embolus) will result in injury.
Acute ischemia (e.g. renal artery embolus) will result in injury.
34
What are 5 common causes of cellular injury?
InflammationNutritional deficiency (or excess)
Hypoxia
Trauma
Genetic mutations
Hypoxia
Trauma
Genetic mutations
35
How does hypoxia cause cellular injury?
Oxygen is the final electron acceptor in the ETC of oxidative phosphorylation, so hypoxia hinders ATP production, disabling important cell functions.
36
What is ischemia?
Reduced blood flow through an organ.
37
What 3 pathologies/pathologic states can cause ischemia?
Decreased arterial perfusion (e.g. atherosclerosis).Decreased venous drainage (e.g. Budd Chiari)
Shock - generalized hypotension resulting in poor tissue perfusion
Shock - generalized hypotension resulting in poor tissue perfusion
38
What is hypoxemia (be numerically specific)?
A low partial pressure of O2 in the blood (i.e. PaO2 < 60 mm Hg)
39
List 4 causes of hypoxemia:
High altitude (decreased PaO2)Hypoventilation (increased PaCO2 decreases PaO2)
Diffusion defect (e.g. pulmonary fibrosis)
V/Q mismatch (R-L shunt, atelectasis)
Diffusion defect (e.g. pulmonary fibrosis)
V/Q mismatch (R-L shunt, atelectasis)
40
3 general causes of hypoxia (in a tissue):
HypoxemiaReduced carrying capacity of blood (anemia)
Ischemia (infarct or hypovolemic shock)
Ischemia (infarct or hypovolemic shock)
41
When does decreased O2 carrying capacity arise? Examples?
With hemoglobin loss or dysfunction. Examples include anemia and CO poisoning.
42
How does CO poisoning reduce O2 carrying capacity?
CO binds Hb more avidly than O2 does.
43
What are the PaO2 and SaO2 in anemia? CO poisoning?
Anemia: both normal.
CO Poisoning: PaO2 normal, SaO2 decreased.
CO Poisoning: PaO2 normal, SaO2 decreased.
44
Common exposures to CO?
Smoke from fires and exhast from cars or gas heaters (common suicide attempt).
45
What's the classic physical finding in CO poisoning? Other findings?
Cherry-red appearance of skin. The early sign of expsure is headache. Significant exposure leads to coma and death.
46
What is methemoglobinemia?
When Fe2+ is oxidized to Fe3+, RBCs can't bind O2.
47
PaO2 and SaO2 in methemoglobinemia?
PaO2 normal, SaO2 decreased. Similar to CO poisoning
Anemia: normal PaO2, normal SaO2
Anemia: normal PaO2, normal SaO2
48
Under what conditions does methemoglobinemia occur?
With oxidant stress (e.g. sulfa and nitrate drugs) and in newborns (immature Fe-reducing enzymes).
49
What's the classic finding in methemoglobinemia?
Chocolate-colored blood.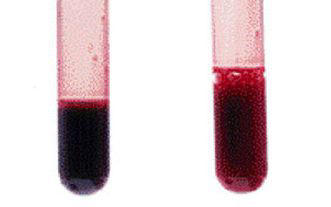
50
Tx for methemoglobinemia?
Intravenous methylene blue helps reduce Fe3+ to Fe2+.
51
What cellular functions does low ATP affect? Consequences?
Na+-K+ pumps, resulting in Na/H2O buildup and swelling
Ca2+ pumps, resulting in Ca2+ buildup in cytosol (can activate hydrolytic lysosomal enzymes)
Aerobic glycolysis, resulting in a switch to anaerobic glycolysis and lactic acid buildup, denaturing proteins and precipitating DNA.
Ca2+ pumps, resulting in Ca2+ buildup in cytosol (can activate hydrolytic lysosomal enzymes)
Aerobic glycolysis, resulting in a switch to anaerobic glycolysis and lactic acid buildup, denaturing proteins and precipitating DNA.
52
Is cellular injury reversible? What's the hallmark of reversible injury?
It is in the initial phase. The hallmark is cellular swelling.
53
What histologic findings indicate reversible injury?
Loss of microvilli and membrane blebbing indicate cytosol swelling.
Dissociation of ribosomes and decreased protein synthesis indicate RER swelling
*These changes are reversible
Dissociation of ribosomes and decreased protein synthesis indicate RER swelling
*These changes are reversible
54
What is the hallmark of irreversible cellular injury?
Membrane damage.
55
What are the consequences of specific membranes in the cell being damaged?
-Plasma membrane damage results in leakage of cytosolic enzymes into the serum (e.g. cardiac troponin) and additional Ca++ entering the cell.
-Mitochondrial membrane damage results in loss of ETC (innter mito membrane) and cytochrome c leaking into the cytosol (activates apoptosis)
-Lysosome membrane damage results in hydrolytic enzymes leaking into the cytosol, which then become activated by the high intracellular Ca++.
-Mitochondrial membrane damage results in loss of ETC (innter mito membrane) and cytochrome c leaking into the cytosol (activates apoptosis)
-Lysosome membrane damage results in hydrolytic enzymes leaking into the cytosol, which then become activated by the high intracellular Ca++.
56
What is the morphologic hallmark of cell death? How does it occur?
Loss of the nucleus
By condensation (pyknosis)
fragmentation (karyorrhexis), and
dissolution (karyolysis)
*Remember:
Swelling = reversible injury
Membrane damage = irreversible injury
Loss of nucleus = death
By condensation (pyknosis)
fragmentation (karyorrhexis), and
dissolution (karyolysis)
*Remember:
Swelling = reversible injury
Membrane damage = irreversible injury
Loss of nucleus = death
57
What are the 2 types of cell death?
Necrosis (murder) and apoptosis (suicide).
58
Describe the main differences between necrosis and apoptosis
Apoptosis is self-initiated, necrosis is not. Necrosis involves a large group of cells and is followed by acute inflammation.
Necrosis is always pathologic, never physiologic.
Necrosis is always pathologic, never physiologic.
59
Describe coagulative necrosis
Necrosis where the organ and cell structures are preserved by coagulation of proteins. The nucleus disappears though. The necrotic tissue remains firm.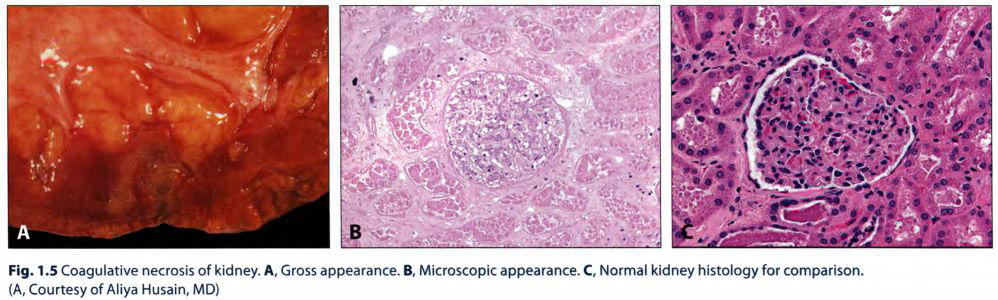
60
When and where does coagulative necrosis occur?
Ischemic infarction in any organ but the brain.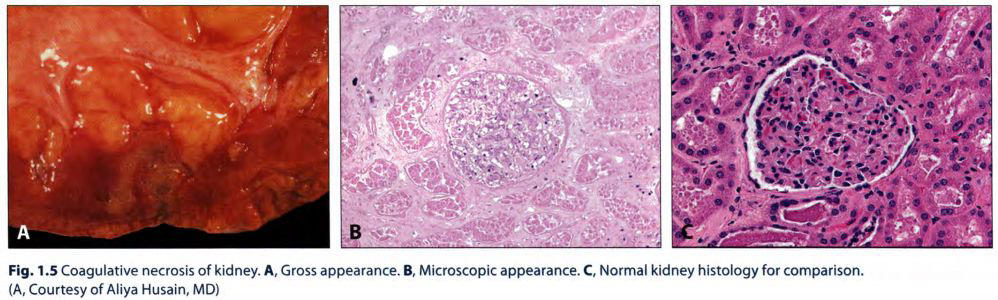
61
How do you recognize an organ that has undergone coagulative (vs. other) necrosis?
It will have maintained its shape. The infarcted area is often wedge-shaped and pale.
62
When does red infarction arise? Examples?
When blood re-enters a loosely organized tissue (e.g. an organ that has undergone coagulative necrosis). Examples include testicular and pulmonary infarctions.
*Note that red infarcts are actually defined as infarcts in the venous drainage of a tissue or in a tissue with dense collaterals/dual blood supply
*Note that red infarcts are actually defined as infarcts in the venous drainage of a tissue or in a tissue with dense collaterals/dual blood supply
63
What is liquefactive necrosis?
Necrotic tissue that becomes liquefied by enzymatic lysis of cells and proteins.
64
When and where does liquefactive necrosis occur (3)?
Any time an organ is exposed to proteolytic enzymes.
It occurs in the brain - enzymes of the microglial cells;
in abscesses - enzymes from neutrophils;
and in pancreatitis - liquification of parenchyma (autodigestion)
It occurs in the brain - enzymes of the microglial cells;
in abscesses - enzymes from neutrophils;
and in pancreatitis - liquification of parenchyma (autodigestion)
65
When does acute inflammation arise?
It is the result of either infection or necrosis
66
What type(s) of necrosis are associated with the pancreas?
Fat and liquefactive
67
What are the types of necrosis?
Coagulative, liquefactive, gangrenous, caseous, fat, and fibrinoid.
68
What is gangrenous necrosis?
Coagulative necrosis that resembles mummified tissue (dry gangrene). If superimposed infection of the dead tissue occurs, liquefactive necrosis ensues (wet gangrene).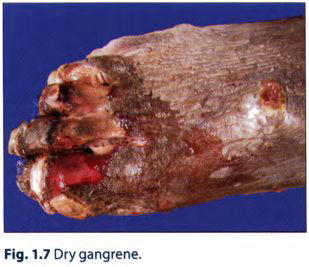
69
Where does gangrenous necrosis most often occur (2 places)?
It is characteristic of ischemia of the lower limb and GI tract.
70
Describe caseous necrotic tissue
Soft and friable, cottage cheese appearance.
71
When does caseous necrosis occur? What is it?
It is characteristic of granulomatous inflammation due to tuberculous or fungal infection. It's a combination of coagulative and liquefactive necrosis.
72
What is fat necrosis?
Necrotic adipose tissue with a chalky-white appearance due to the deposition of Ca.
73
Where and how does fat necrosis occur?
Trauma to fat (e.g. breast) and pancreatitis-mediated damage of peripancreatic fat. These 2 processes release fatty acids, which then bind Ca in saponification.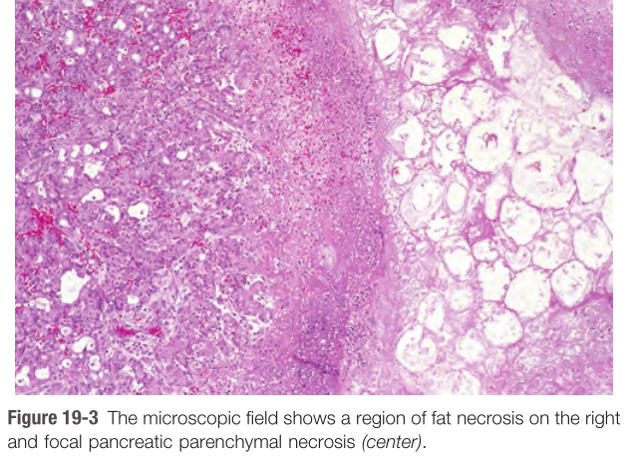
74
What is dystrophic calcification?
Calcium deposition in the context of normal calcium levels
75
What does fat necrosis have to do with dystrophic calcification?
Saponification is an example of dystrophic calcification (Ca deposits on dead tissue). The necrotic tissue acts as a nidus for calcification.
76
What are the serum Ca and P levels in dystrophic calcification? metastatic calcification?
Dystrophic (e.g. saponification): Ca and P levels are normal. Deposition occurs where there is a nidus, for example dead tissue.
Metastatic (e.g. hyperPTH → nephrocalcinosis): Ca and P levels are high, leading to deposition in normal tissues
Metastatic (e.g. hyperPTH → nephrocalcinosis): Ca and P levels are high, leading to deposition in normal tissues
77
What's the differential for Ca2+ deposits in the breast?
Carcinoma in situ or fat necrosis.
78
Why might a patient with fat necrosis think they have breast cancer?
The release of fatty acids can sometimes lead to a giant cell reaction, in which the patient might present with a mass consisting of fat, giant cells, and calcification.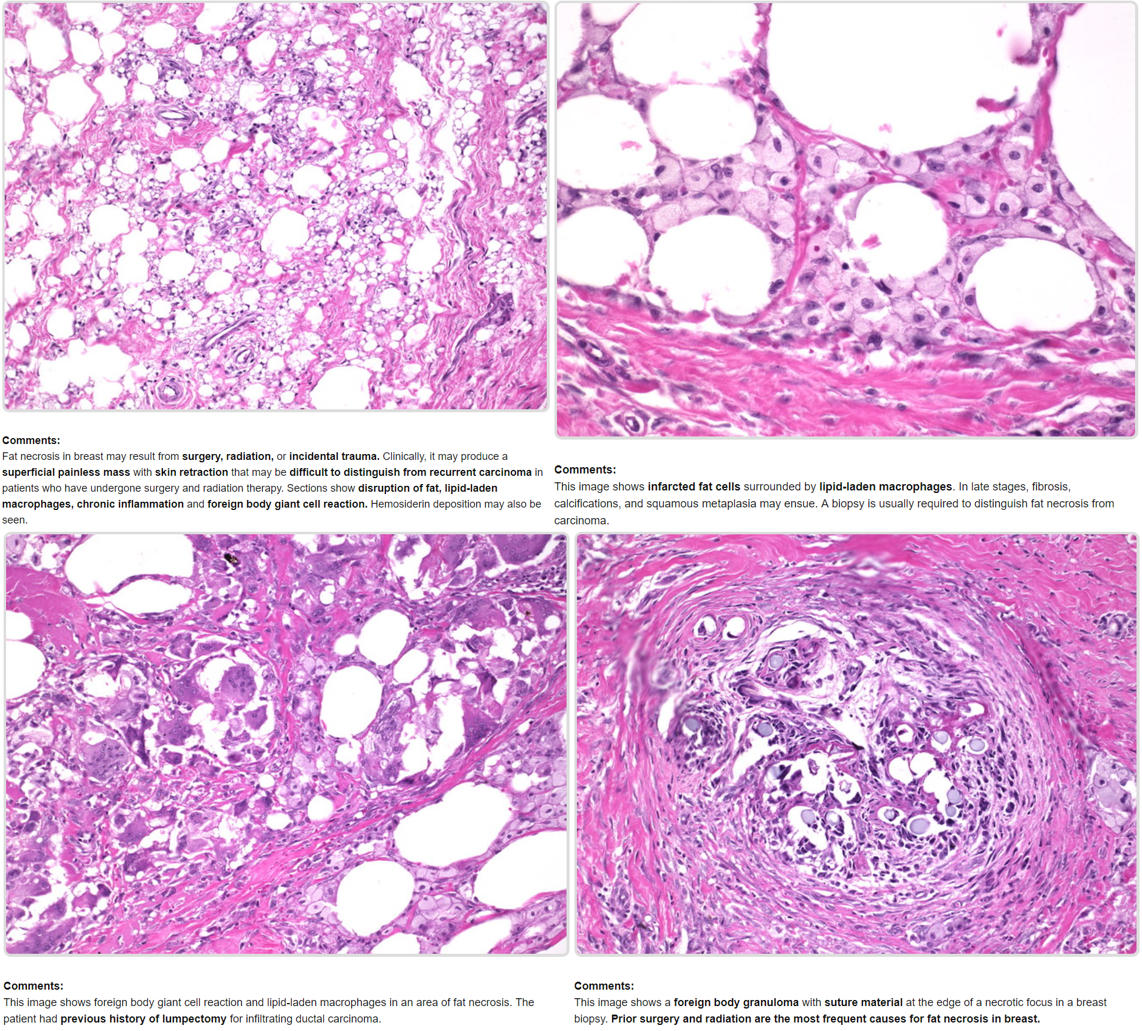
79
What is fibrinoid necrosis?
Necrotic damage to the blood vessel wall causes proteins (including fibrin) to leak into the wall.
80
How do you identify fibrinoid necrosis?
It stains bright pink.
81
For what two general pathologies can fibrinoid necrosis occur?
Characteristic of malignant hypertension and vasculitis.
82
What is malignant hypertension?
More commonly referred to as "hypertensive emergency" - defined as a BP of 180/120 or greater with papilledema. Presence of end organ damage would be called a "hypertensive crisis"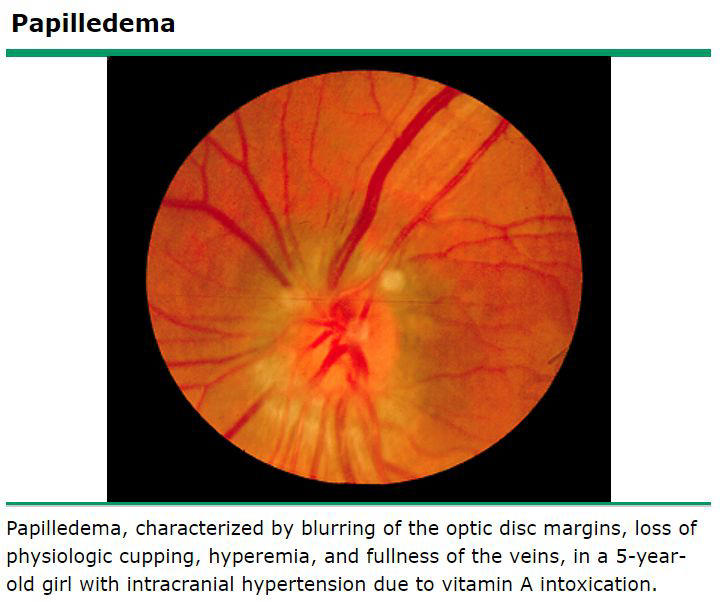
83
What kind of necrosis would pre-eclampsia lead to?
Fibrinoid necrosis of the placental vessels.
*Pre-eclampsia- pregnancy complication characterized by high blood pressure and signs of damage to another organ system.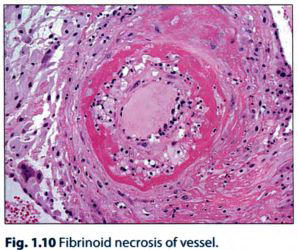
*Pre-eclampsia- pregnancy complication characterized by high blood pressure and signs of damage to another organ system.
84
What is a free radical?
A chemical species with unpaired electrons in its outer orbit
85
What is apoptosis?
Energy dependent, genetically programmed cell death involving single cells or groups of cells.
*Apoptosis takes ATP!!!
*Apoptosis takes ATP!!!
86
Three examples of physiologically appropriate apoptosis?
Endometrial shedding during menstruation.Removal of cells during embryogenesis (e.g. malfunction -> syndactyly)
CD8 T cell-mediated killing of virally infected cells.
CD8 T cell-mediated killing of virally infected cells.
87
Describe the morphologic changes in the apoptotic process
As the dying cell shrinks, the cytoplasm becomes more eosinophilic (pink).
The nucleus condenses (pyknosis) and fragments (karyorrhexis),
and then apoptotic bodies fall (apoptosis means "falling of leaves" in greek) from the cell and are removed by macrophages.
The nucleus condenses (pyknosis) and fragments (karyorrhexis),
and then apoptotic bodies fall (apoptosis means "falling of leaves" in greek) from the cell and are removed by macrophages.
88
What are the main enzymatic mediators of apoptosis? How do they work?
Caspases, which activate proteases and endonucleases.
89
In what 3 ways can caspases be activated?
Via 3 pathways:1. Intrinsic mitochondrial pathway (cytochrome c)
2. Extrinsic receptor-ligand pathway (FAS ligand)
3. Cytotoxic CD8+ T cell-mediated pathway (granzyme)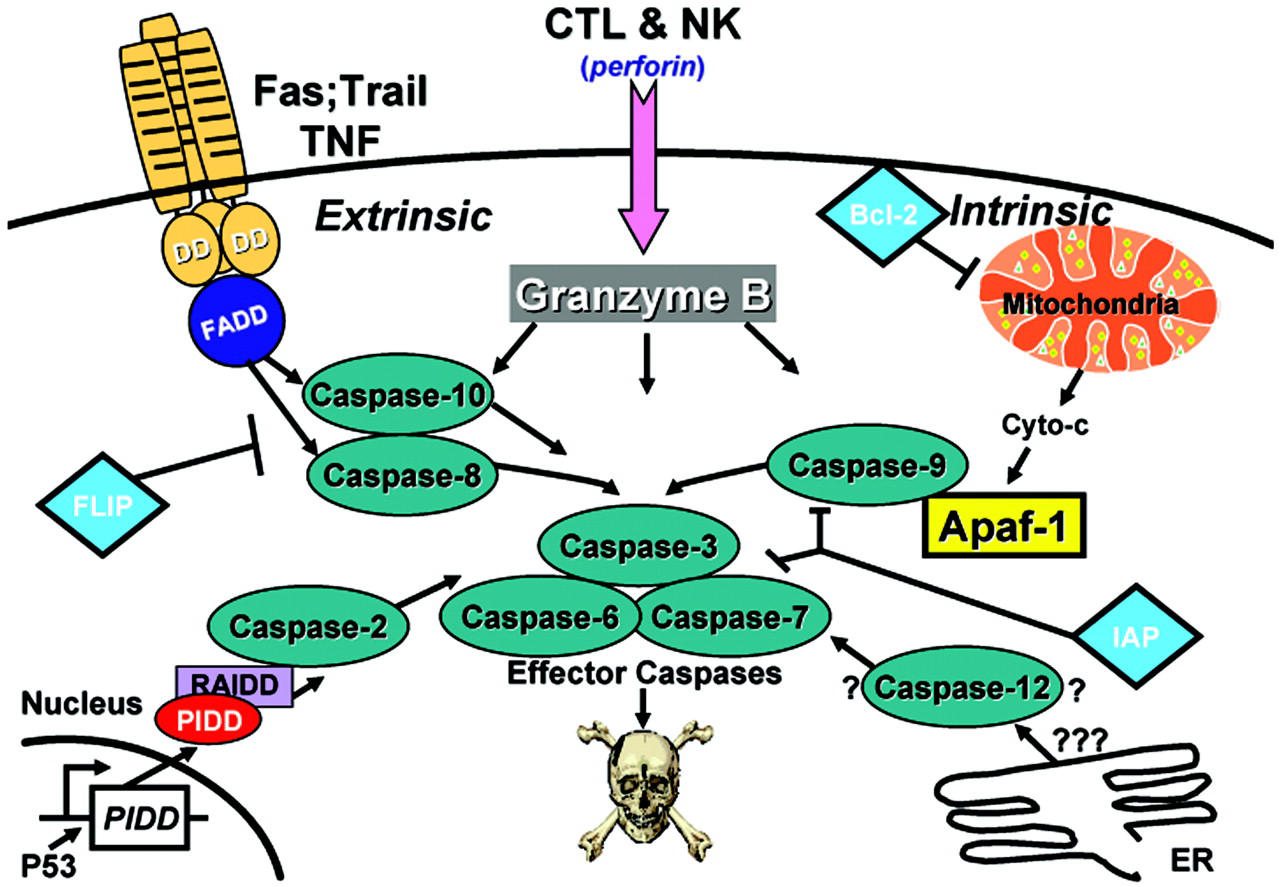
2. Extrinsic receptor-ligand pathway (FAS ligand)
3. Cytotoxic CD8+ T cell-mediated pathway (granzyme)
90
What is Bcl2?
It stabilizes the mitochondrial membrane by binding to Bax/Bak, in order to inhibit leakage of cytochrome c into the cytosol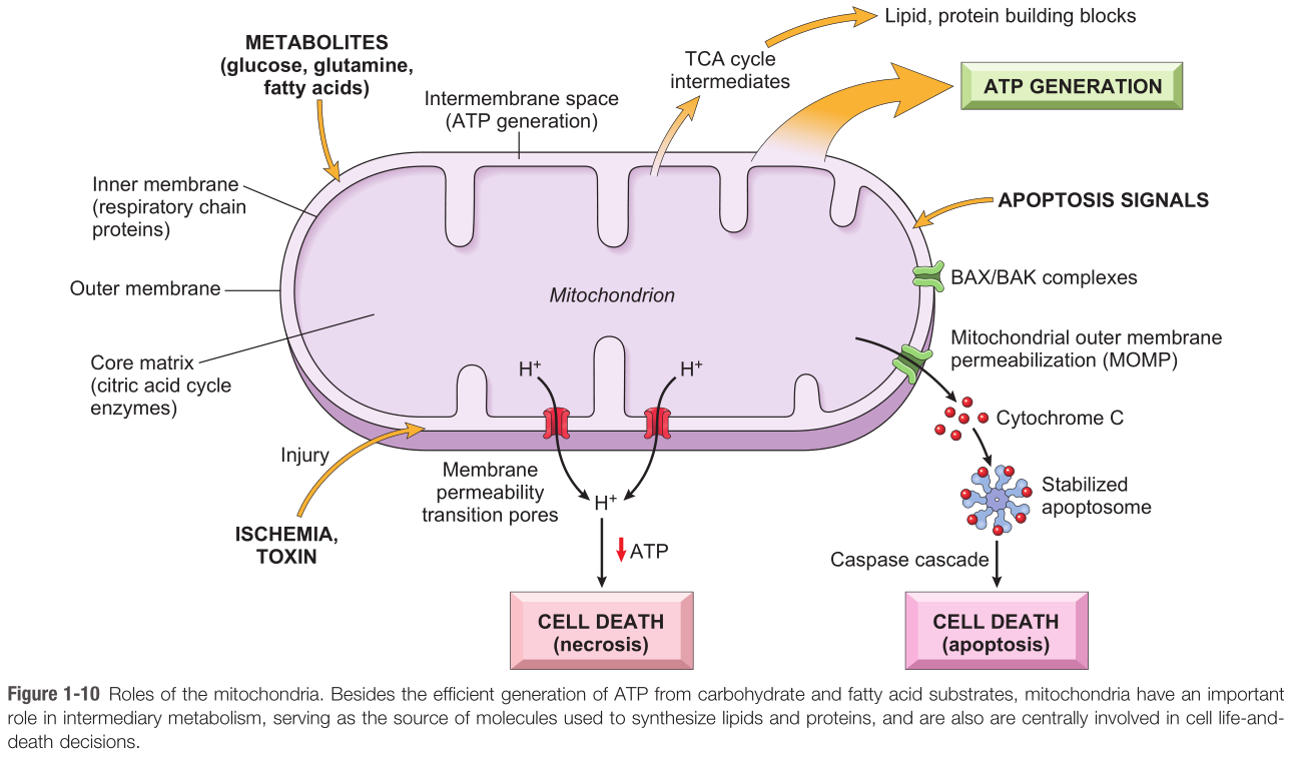
91
What kinds of events lead to the inactivation of Bcl2? What's the consequence?
Cellular injury,DNA damage,
or loss of hormonal stimulation.
Inactivation of Bcl2 allows cytochrome c to leak from the inner mitochondrial matrix into the cytoplasm and activate caspases.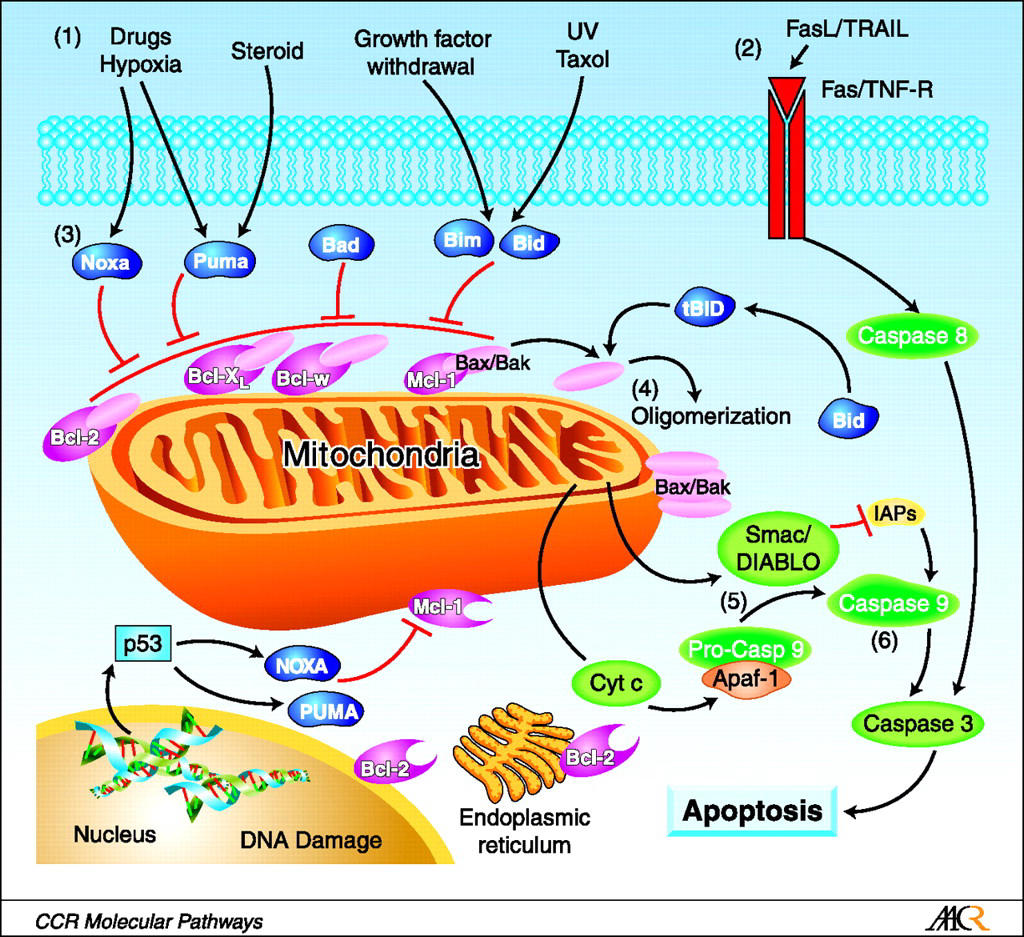
or loss of hormonal stimulation.
Inactivation of Bcl2 allows cytochrome c to leak from the inner mitochondrial matrix into the cytoplasm and activate caspases.
92
What is the extrinsic receptor-ligand pathway? How does CD95 play a role?
FAS ligand binds FAS death receptor (CD95) on the target cell, activating caspases.
Alternatively, TNF binds the TNF receptor on the target cell, activating caspases.
Alternatively, TNF binds the TNF receptor on the target cell, activating caspases.
93
What is the cytotoxic CD8 T cell-mediated pathway?
CD8 T cells secrete perforins, which create pores in the membrane of target cells. They then secrete granzymes, which can enter through the pores and activate caspases. This is how CD8 T cells kill virally infected cells.
94
When does apoptosis occur in aberrant T cell maturation?
Negative selection in the thymus, which assesses whether or not the T cell binds too avidly to self-Ag.
If it does, FAS ligand is expressed, binds FAS death receptor, apoptosis.
Positive selection, on the other hand, tests to make sure that the T cell can properly bind self-Ag on MHC.
+selection: do you bind?
-selection: do you bind too strongly?
If it does, FAS ligand is expressed, binds FAS death receptor, apoptosis.
Positive selection, on the other hand, tests to make sure that the T cell can properly bind self-Ag on MHC.
+selection: do you bind?
-selection: do you bind too strongly?
95
What are the 2 ways a cytotoxic T cell kills cells expressing foreign Ag?
FAS-induced apoptosis and perforin pathway.
*Just a note to remember that FAS ligand is a cytokine of the TNF family
*Just a note to remember that FAS ligand is a cytokine of the TNF family
96
What process is involved in physiologic free radical generation?
Oxidative phosphorylation
97
What enzyme transfers electrons to O2, the final electron acceptor?
Cytochrome c oxidase (complex IV).
(Inhibited by cyanide and CO)
(Inhibited by cyanide and CO)
98
What are the free radicals produced in oxidative phosphorylation? How many accepted electrons does each radical state represent?
O2 + 1 electron=superoxide (O2-)2=hydrogen peroxide (H2O2)
3=hydroxyl radical (*OH)
4=water (H2O) (not a free radical, just here for completion's sake)
3=hydroxyl radical (*OH)
4=water (H2O) (not a free radical, just here for completion's sake)
99
When does pathologic generation of free radicals arise (5 scenarios)?
Ionizing radiation, inflammation,
metals accumulation,
drugs and chemicals,
reperfusion after ischemic injury
metals accumulation,
drugs and chemicals,
reperfusion after ischemic injury
100
How does ionizing radiation generate free radicals?
Water is hydrolyzed to hydroxyl free radical (•OH)
101
What is the most damaging free radical?
Hydroxyl (*OH)
102
How does inflammation generate free radicals?
NADPH oxidase generates superoxide during oxygen dependent killing by neutrophils.
103
Which metals create free radicals? Through which reaction?
Copper and iron. Fenton reaction.
104
How do drugs and chemicals create free radicals?
The P450 system can generate free radicals in the process of metabolism (e.g. of acetaminophen).
105
How do our bodies eliminate free radicals (3 modalities)?
Antioxidants (glutathione, vitamins A, C, E) Enzymes (glutathione peroxidase, catalase, SOD)
Metal carrier proteins (transferrin and ceruloplasmin)
Metal carrier proteins (transferrin and ceruloplasmin)
106
What antioxidants do our bodies use?
Glutathione, vitamins A, C, E, etc.
107
What enzymes do our bodies use to eliminate free radicals? Mechanism of each?
Superoxide dismutase (mitochondria) converts superoxide (O2-) → H2O2
Glutathione peroxidase (mitochondria): GSH+free radical → GSSG and H2O
Catalase (peroxisomes) converts H2O2 → O2 and H2O
Glutathione peroxidase (mitochondria): GSH+free radical → GSSG and H2O
Catalase (peroxisomes) converts H2O2 → O2 and H2O
108
What are 2 examples of metal carrier proteins that reduce free radical damage?
Transferrin and ceruloplasmin
109
What is the mechanism of tissue damage in hemochromatosis and Wilson dz?
Free radical damage
110
What 2 key features will indicate an apoptotic cell?
Small nucleus, pink cytoplasm.
111
What is CCl4 and what is its significance? What cellular and gross changes will be seen?
It's an organic solvent used in dry cleaning. It's converted to CCl3 (a free radical) by the P450 system. Results in cell injury with swelling of RER; as ribosomes detach, protein synthesis is impaired. This decreases apolipoprotein production, leading to fatty changes in the liver as fat can't be mobilized.
112
How does reperfusion injury work? How will you detect it?
As blood returns to ischemic tissue, O2-derived free radicals further damage the tissue (burst of oxidative respiration)
For example, in an MI, cardiac enzymes will rise (e.g. troponin). When you reperfuse (cath), they will continue to rise rather than fall.
For example, in an MI, cardiac enzymes will rise (e.g. troponin). When you reperfuse (cath), they will continue to rise rather than fall.
113
What is amyloidosis?
Misfolded proteins get deposited in the extracellular space, damaging tissues.
114
What are the shared features among all amyloid?
β pleated sheet structure
Congo red staining/apple green birefringence under polarized light: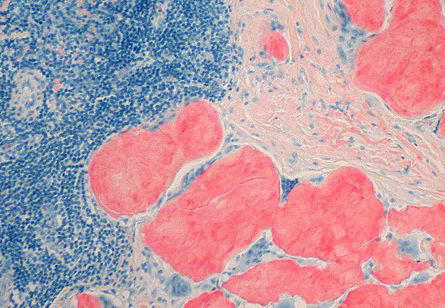
Congo red staining/apple green birefringence under polarized light:
115
Where does amyloid deposition occur (types)?
Can be systemic (Primary AL or Secondary AA)
or localized.
or localized.
116
What is primary amyloidosis? What conditions is it associated with?
Systemic deposition of AL amyloid, which is derived from Ig light chain. It's associated with plasma cell dyscrasias (e.g. multiple myeloma).
117
What is secondary amyloidosis?
Systemic deposition of AA amyloid, which is derived from serum amyloid-associated protein (SAA).
SAA is an acute phase reactant, meaning that in chronic inflammatory states, development of secondary amyloidosis is possible
SAA is an acute phase reactant, meaning that in chronic inflammatory states, development of secondary amyloidosis is possible
118
What is SAA (serum amyloid associated) protein? In what three conditions is it increased?
An acute phase reactant that is increased in
chronic inflammatory states,
malignancy, and
Familial Mediterranean Fever (FMF).
chronic inflammatory states,
malignancy, and
Familial Mediterranean Fever (FMF).
119
What's the main difference between acute and chronic inflammation?
Acute = neutrophil mediatedchronic = lymphocyte mediated
120
What is acute inflammation? When does it occur?
Edema and neutrophils in response to infection (to eliminate the pathogen) or tissue necrosis (to clear necrotic debris).
121
Acute inflammation: rapidity of response? Specificity?
Rapid response at the expense of specificity - for example, neutrophils, though quick to arrive on the scene, are fairly destructive to everything around them.
122
What cells possess toll-like receptors (TLRs) and what do they do?
TLRs are present on many cells of the innate immune system; canonically macrophages and dendritic cells. However, most immune cells carry TLRs.
They are activated by pathogen-associated molecular patterns (PAMPs)
They are activated by pathogen-associated molecular patterns (PAMPs)
123
What TLR co-receptor is canonically present on macrophages? What does it recognize?
CD14. Recognizes LPS on the outer membrane of gram(-) bacteria.
*Note that CD14 is a co-receptor for TLR4
1: T
4: R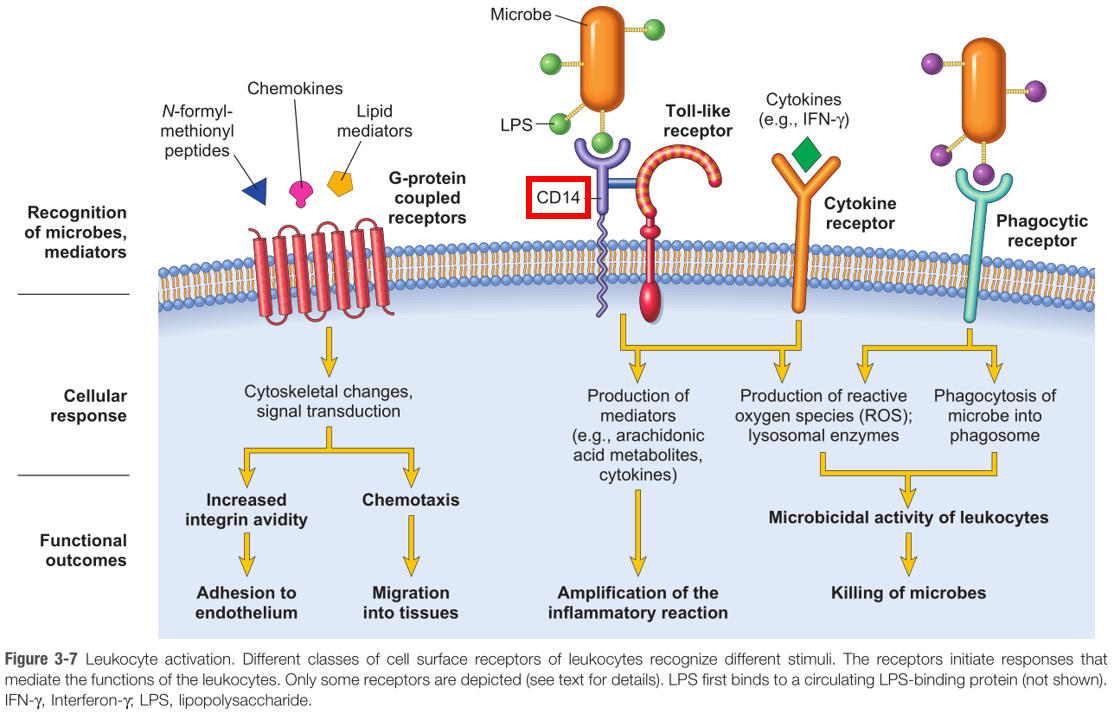
*Note that CD14 is a co-receptor for TLR4
1: T
4: R
124
TLR activation leads to what downstream molecular effects?
Upregulation of NFkB,
...which is a nuclear transcription factor that activates immune response genes responsible for producing a number of immune mediators (most importantly, TNF)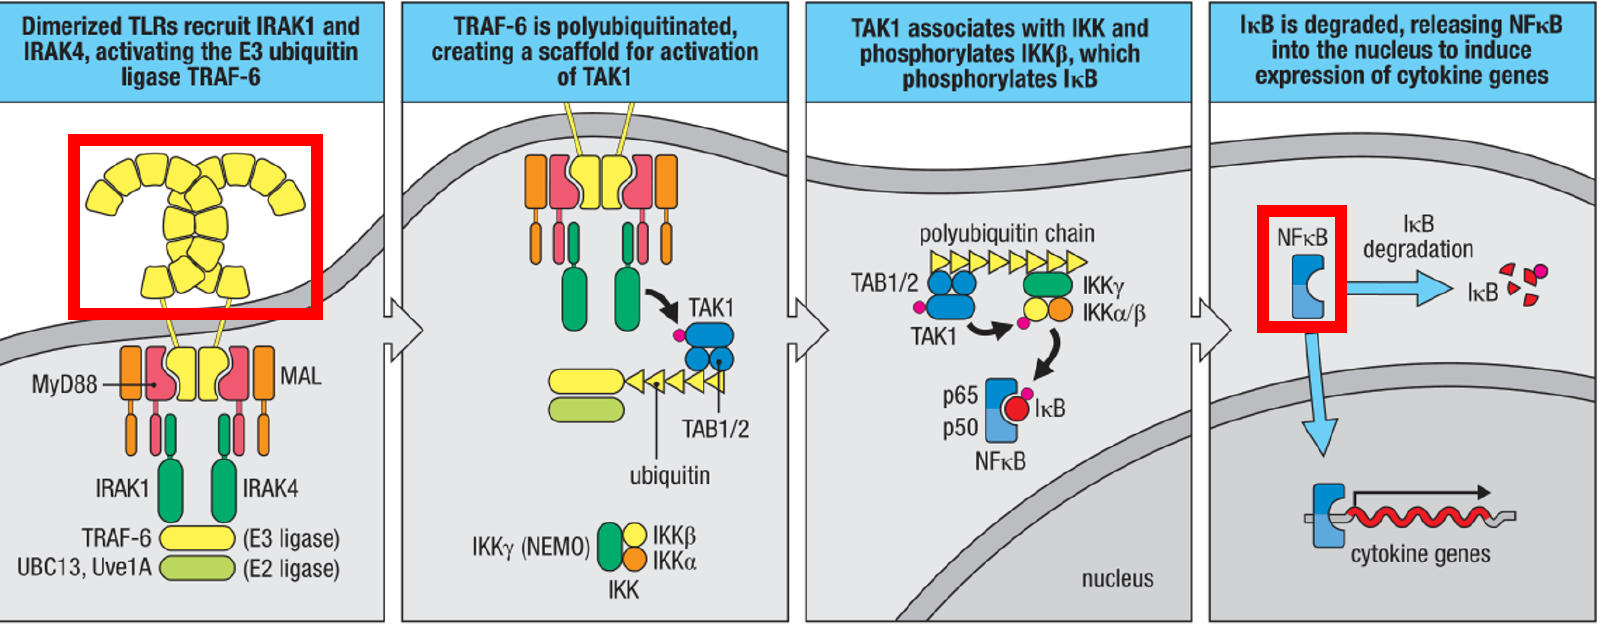
...which is a nuclear transcription factor that activates immune response genes responsible for producing a number of immune mediators (most importantly, TNF)
125
Do B lymphocytes ever express TLRs?
Yes. TLRs 1,3,4,6,9 - you get the idea - all found on B lymphocytes
126
Cyclooxygenase produces what immune mediators, and from what substrate? What do they do?
Prostaglandins I2, D2, and E2. Arachidonic acid is substrate.
All three mediate vasodilation and increased vascular permeability.
E2 also mediates pain.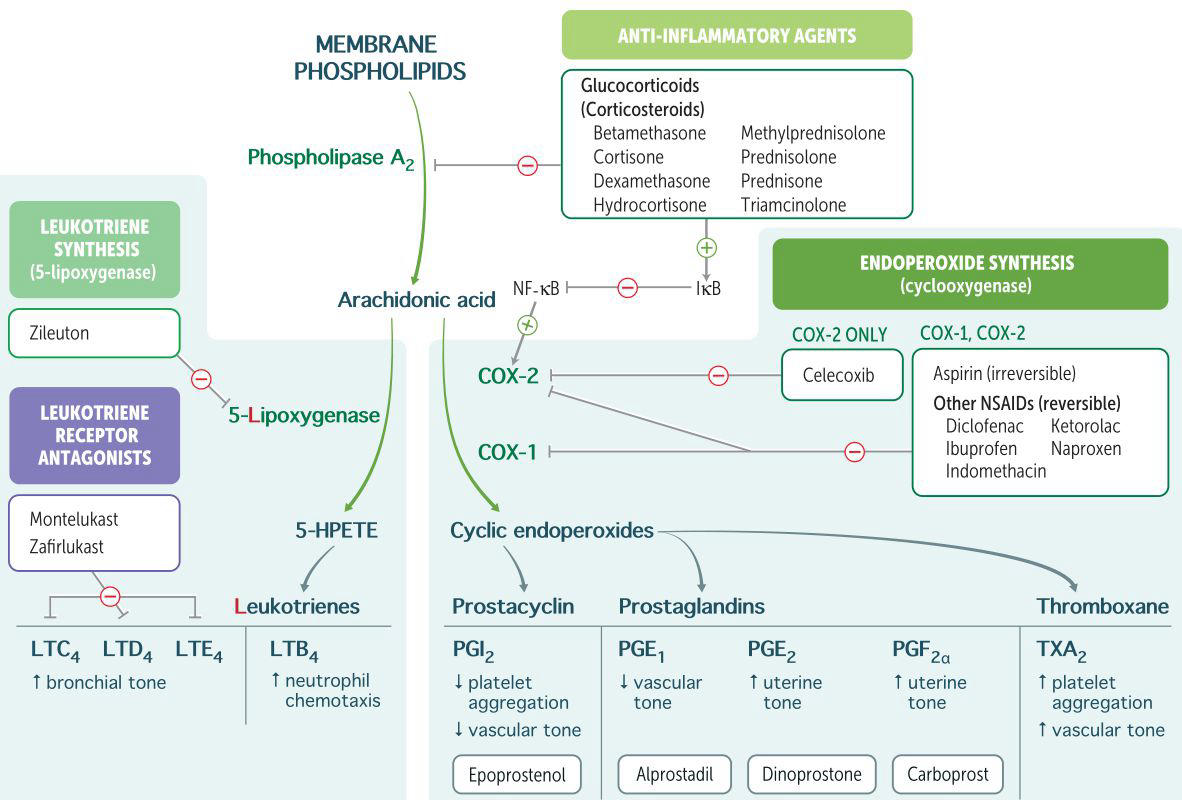
All three mediate vasodilation and increased vascular permeability.
E2 also mediates pain.
127
What immune factors does 5-lipoxygenase produce, and from what substrate? What do they do?
Leukotrienes B4, C4, D4, E4. From arachidonic acid.
B4 attracts and activates neutrophils.
C4, D4, and E4 mediate vasoconstriction, bronchospasm, and increased vascular permeability (all consequences of smooth muscle contraction)
B4 attracts and activates neutrophils.
C4, D4, and E4 mediate vasoconstriction, bronchospasm, and increased vascular permeability (all consequences of smooth muscle contraction)
128
What are the 2 main mediators of pain?
PGE2 and bradykinin.
129
What are the 2 functions of PGE2?
Mediates fever (synthesized in hypothalamus to increase temperature setpoint) and pain (sensitizes nerve endings)
130
What 4 mediators that attract neutrophils?
LTB4, IL-8, C5a, and bacterial products.
131
Where are mast cells located?
They are widely distributed throughout connective tissue.
132
What 3 processes can activate mast cells?
Tissue trauma
C3a and C5a
or cross-linking of cell-surface IgE by antigen
C3a and C5a
or cross-linking of cell-surface IgE by antigen
133
Compare and contrast the immediate and delayed responses of mast cells to activation:
Immediate response: release of pre-formed histamine granules, which cause vasodilation and increased vascular permeability at the post-capillary venule
Delayed response: arachidonic metabolite production, particularly leukotrienes, to maintain the acute inflammatory response.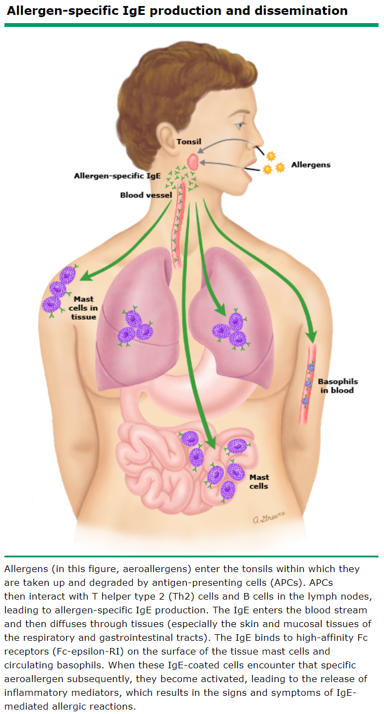
Delayed response: arachidonic metabolite production, particularly leukotrienes, to maintain the acute inflammatory response.
134
What is the complement system?
Proinflammatory serum proteins that "complement" inflammation
135
Describe the final pathway of complement activation:
Pathways converge on:
production of C3 convertase (mediates C3 → C3a & C3b)
C3 convertase then produces C5 convertase (mediates C5 → C5a & C5b)
C5b then complexes with C6-C9 to form the membrane attack complex (MAC).
production of C3 convertase (mediates C3 → C3a & C3b)
C3 convertase then produces C5 convertase (mediates C5 → C5a & C5b)
C5b then complexes with C6-C9 to form the membrane attack complex (MAC).
136
Describe the classical pathway of complement activation:
C1 binds IgG or IgM that is bound to antigen.
"GM makes classic cars."
"GM makes classic cars."
137
Describe the alternative pathway of complement activation:
Microbial products directly activate complement (C3 to C3a and C3b)
138
Describe the mannose-binding lecithen (MBL) pathway of complement activation:
MBL binds to mannose on microbes and activates complement
139
What are the anaphylatoxins and what do they do?
C3a and C5a trigger mast cell degranulation.
140
Two functions of C5a?
Anaphylatoxin - causes mast cell degranulation (vasodilation, increased vascular permeability)
Acts as a chemoattractant for neutrophils.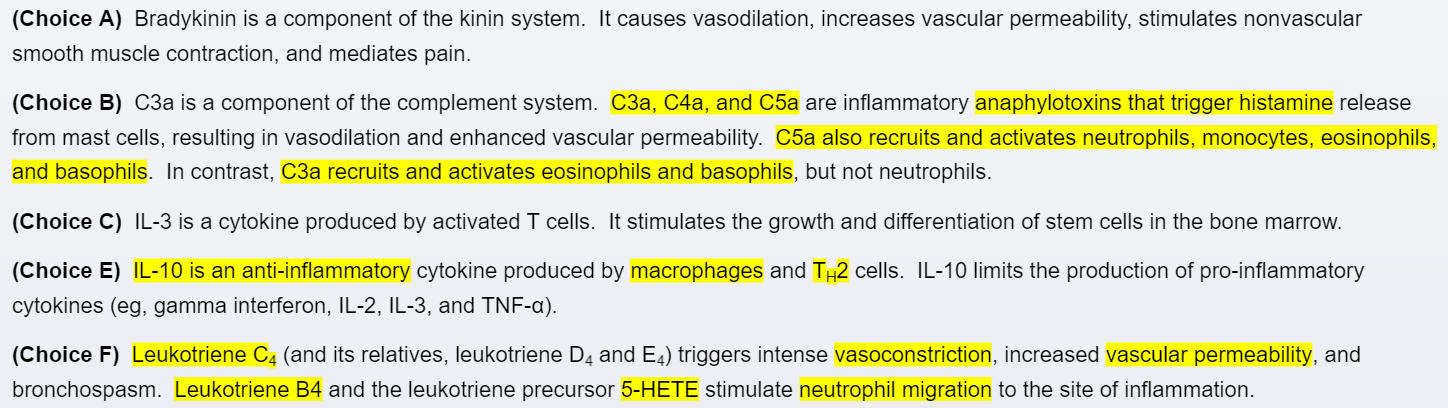
Acts as a chemoattractant for neutrophils.
141
One function of C3b?
Opsonin for phagocytosis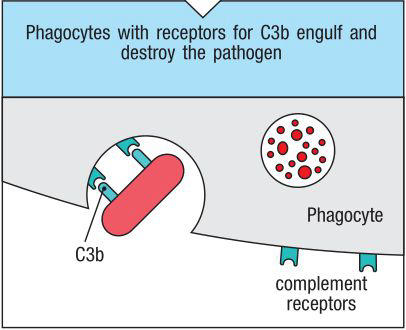
142
Function of MAC?
Creates a hole in the cell membrane; lysis
143
What is Hageman factor? How is it activated? What 3 functions does it carry out once activated?
Factor XII. It is an inactive proinflammatory protein produced in the liver.
It is activated upon exposure to tissue factor. In turn it then:
1) Activates the coagulation and fibrinolytic systems
2) Activates complement
3) Activates kinin system
It is activated upon exposure to tissue factor. In turn it then:
1) Activates the coagulation and fibrinolytic systems
2) Activates complement
3) Activates kinin system
144
Describe the kinin system:
Kinin cleaves high molecular weight kininogen (HMWK) to bradykinin...
...which mediates vasodilation,
increased vascular permeability (similar to histamine),
as well as pain.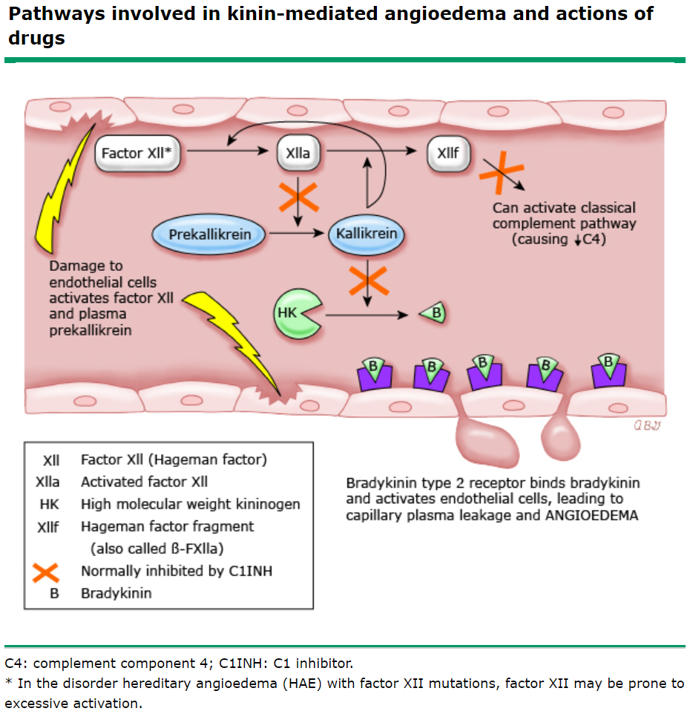
...which mediates vasodilation,
increased vascular permeability (similar to histamine),
as well as pain.
145
What are the 5 cardinal signs of inflammation?
Rubor, calor, dolor, tumor, fever
146
What causes rubor and calor? Three key mediators?
Vasodilation (due to relaxation of arteriolar smooth muscle).
Key mediators are histamine, prostaglandins, and bradykinin.
Key mediators are histamine, prostaglandins, and bradykinin.
147
What causes tumor? Two key mediators?
Leakage of fluid from post-capillary venules into the interstitial space (exudate).
Key mediators are histamine (endothelial cell contraction) and tissue damage (endothelial cell disruption).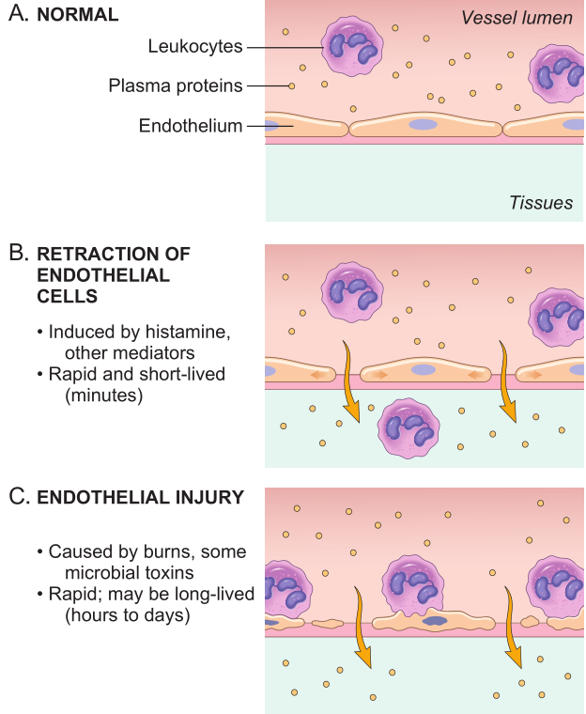
Key mediators are histamine (endothelial cell contraction) and tissue damage (endothelial cell disruption).
148
2 key mediators of dolor (pain)?
PGE2 and bradykinin, which sensitize sensory nerve endings.
149
Describe the pathway by which pyrogens induce fever:
Pyrogens (e.g. LPS) cause macrophages to release IL-1 and TNF, which increase COX activity in perivascular cells of the hypothalamus. This increases PGE2 production, raising the temperature set point.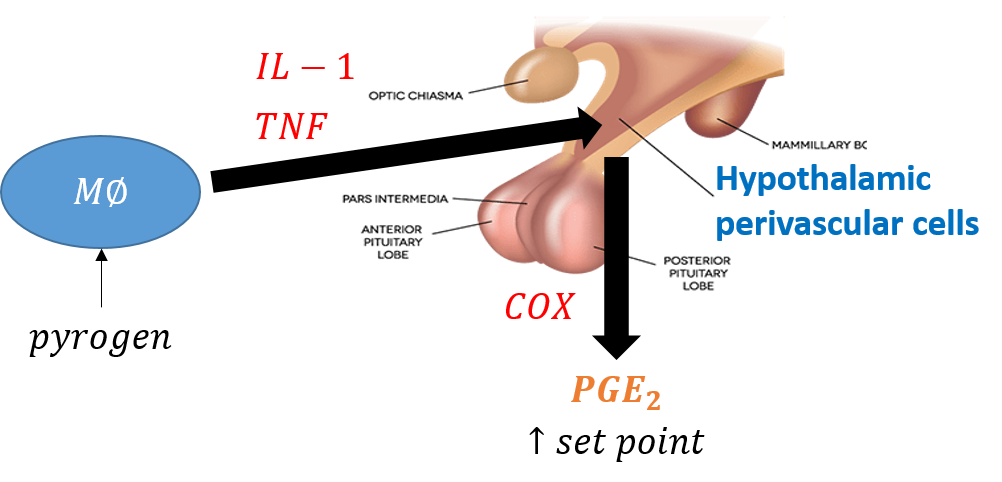
150
What are the (7) steps of neutrophil arrival and function?
1. Margination2. Rolling
3. Adhesion
4. Transmigration and chemotaxis
5. Phagocytosis
6. Destruction of phagocytosed material
7. Resolution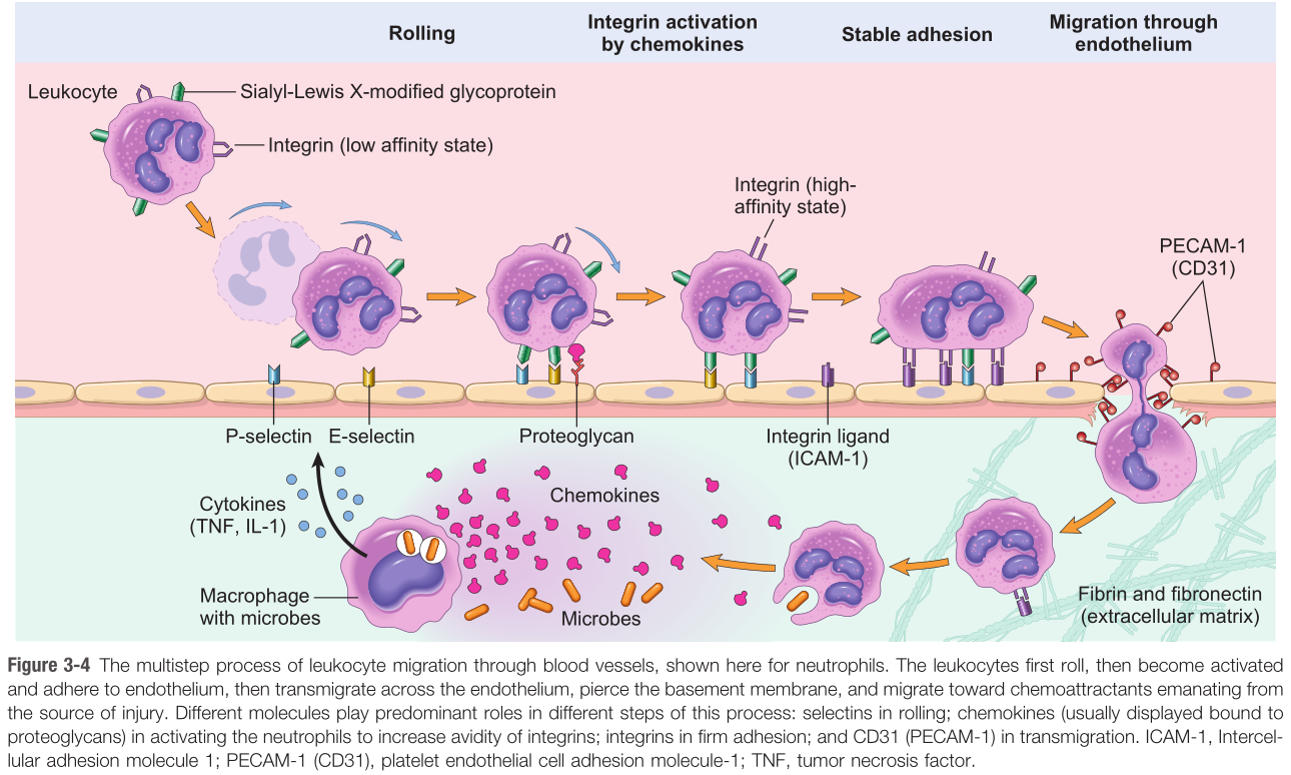
3. Adhesion
4. Transmigration and chemotaxis
5. Phagocytosis
6. Destruction of phagocytosed material
7. Resolution
151
How does margination mechanistically occur?
1) Vasodilation slows the blood flow in postcapillary venules
2) Decreased velocity causes cells to marginate from center of flow to periphery
2) Decreased velocity causes cells to marginate from center of flow to periphery
152
What are the 3 steps that induce leukocyte rolling?
1) P-selectin release (mediated by histamine
2) E-selectin release (induced by TNF and IL-1)
3) Selectins bind sialyl Lewis X on leukocytes
...and then rolling occurs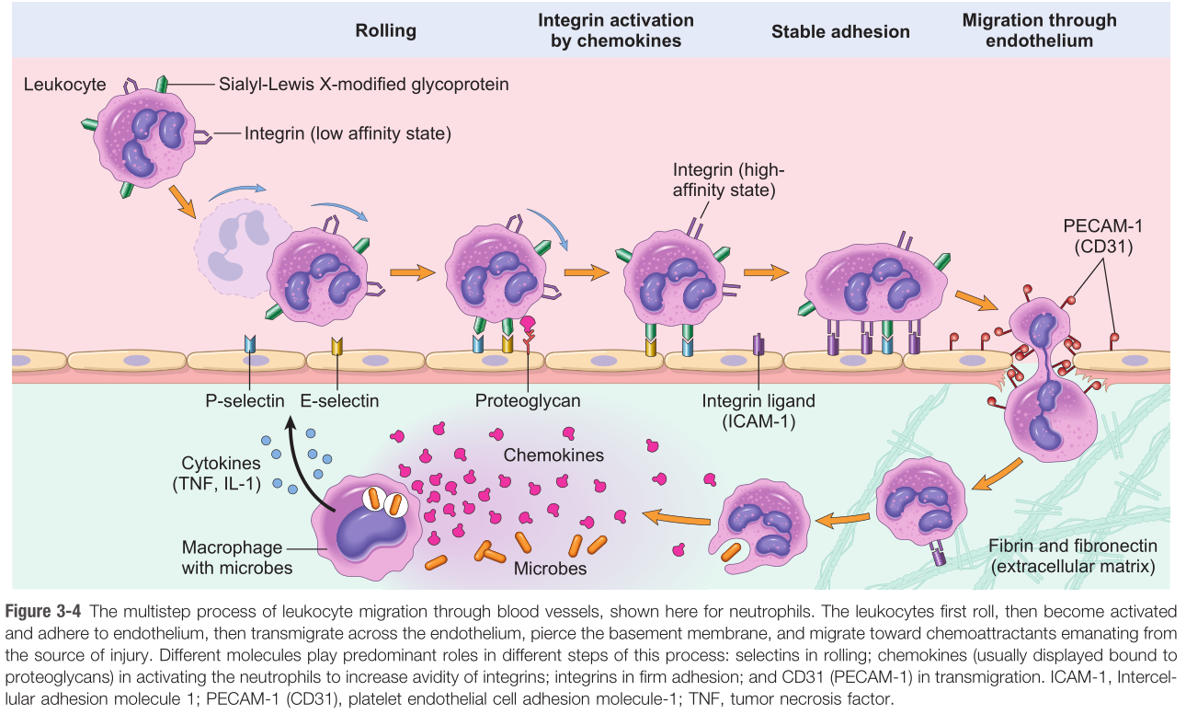
2) E-selectin release (induced by TNF and IL-1)
3) Selectins bind sialyl Lewis X on leukocytes
...and then rolling occurs
153
How does adhesion occur (leukocyte) (be specific with which cytyokines upregulate which receptors)?
1) Cellular adhesion molecules (ICAM and VCAM) are upregulated on endothelium by TNF and IL-1.
2) Integrins are upregulated on leukocytes by C5a and LTB4.
3) Interaction between -CAMs and integrins results in firm adhesion.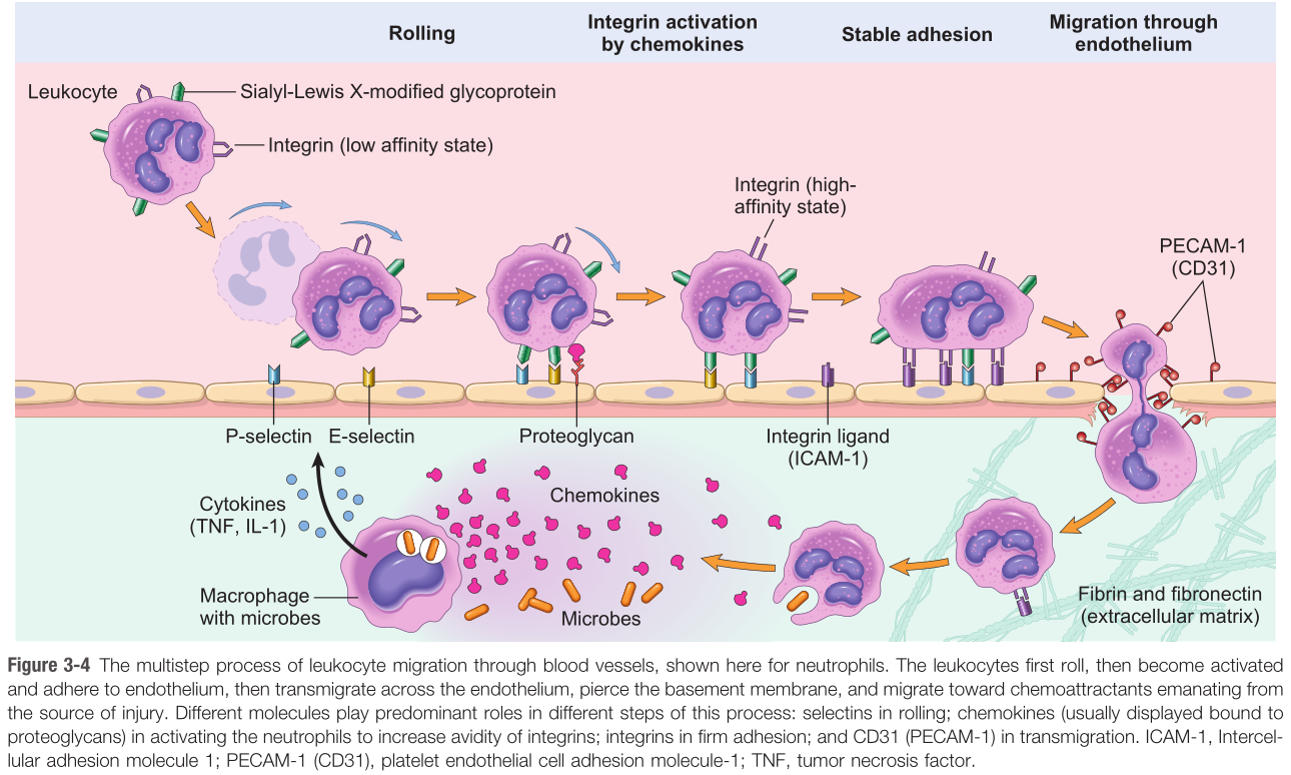
2) Integrins are upregulated on leukocytes by C5a and LTB4.
3) Interaction between -CAMs and integrins results in firm adhesion.
154
What two substances are released from Weibel-Palade bodies?
von Willebrand factor, P-selectin
155
What is leukocyte adhesion deficiency? What specific molecules are involved?
An autosomal recessive defect in β2-integrin subunit (aka CD 18), shared by LFA-1 and Mac-1 integrins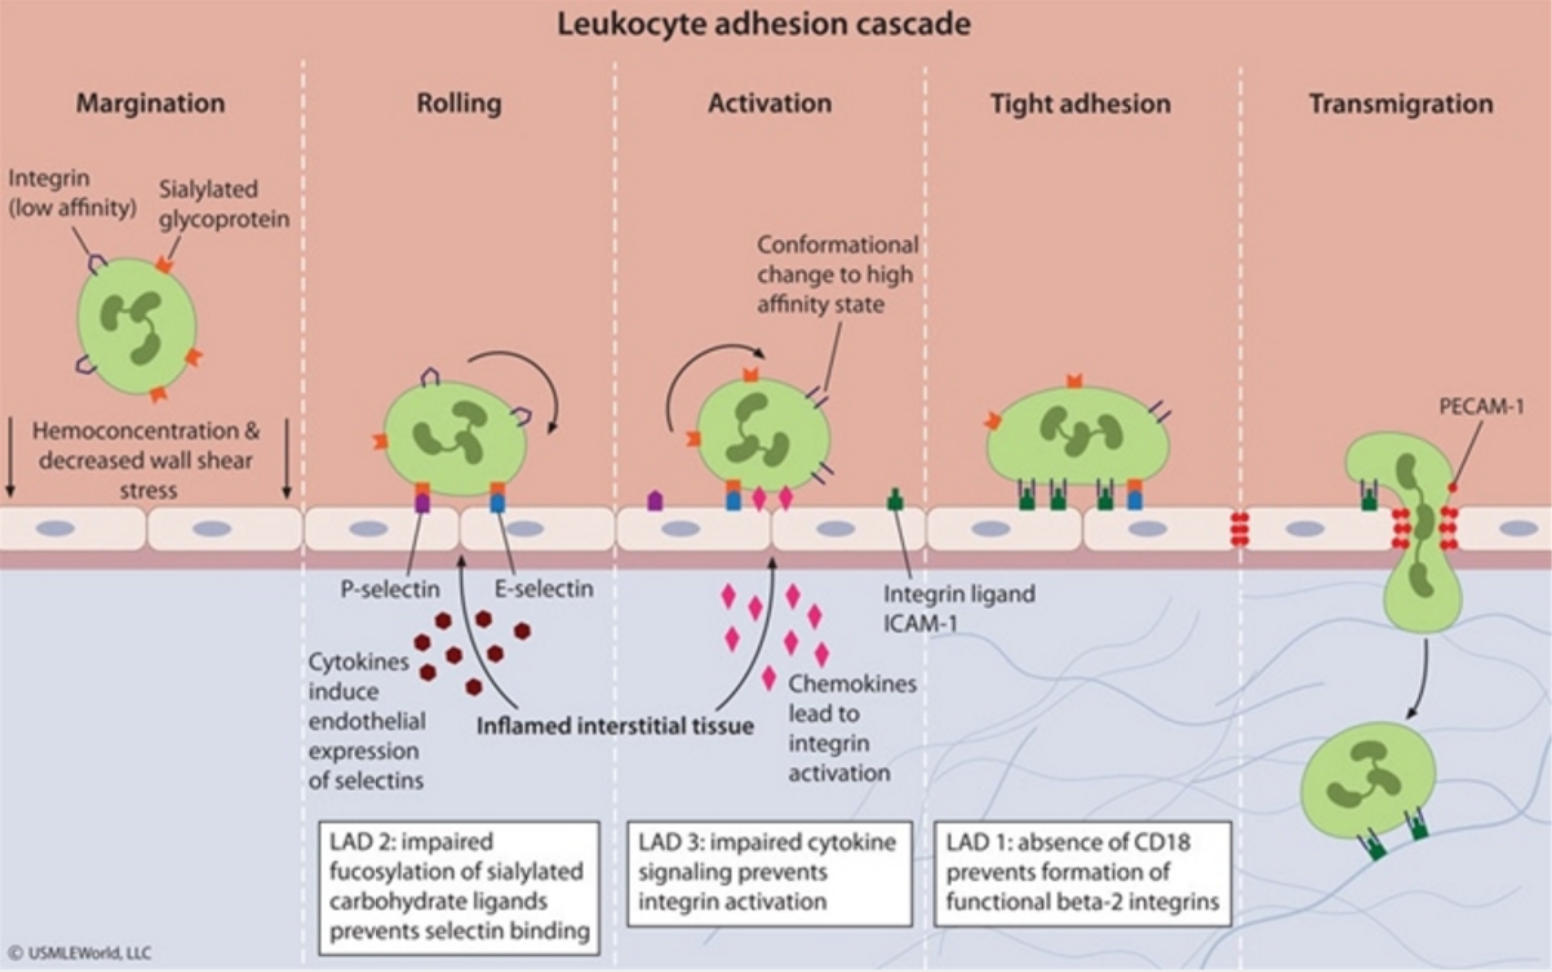
156
What are the clinical features of leukocyte adhesion deficiency (3)?
Delayed umbilical separation (neutrophils are partially responsible for detachment)
recurrent bacterial infections that lack pus
increased circulating neutrophils (marginated pool unable to adhere)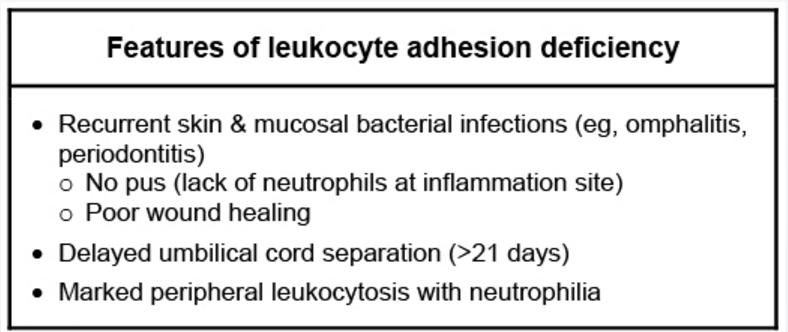
recurrent bacterial infections that lack pus
increased circulating neutrophils (marginated pool unable to adhere)
157
During transmigration/chemotaxis, what chemical attractants do neutrophils follow?
bacterial products, IL-8, LTB4, and C5a (should look familiar)
158
What is phagocytosis, and what are its targets?
Cellular consumption of pathogens or necrotic tissue
159
What factors enhance phagocytosis?
Opsonins: IgG and C3b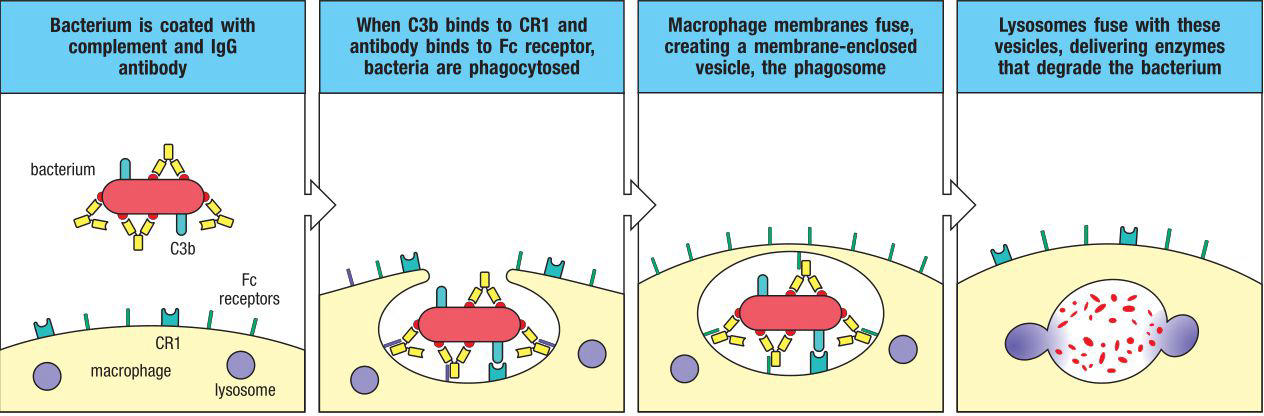
160
How does phagocytosis occur?
Pseudopods extend from leukocytes to form phagosomes, which are internalized and merge with lysosomes to produce phagolysosomes
161
What are the 3 phases of acute inflammation?
Fluid phase (brings serum and its factors in), Neutrophil phase (peaks around 24 hr), and
Macrophage phase (peaks around 2-3 days).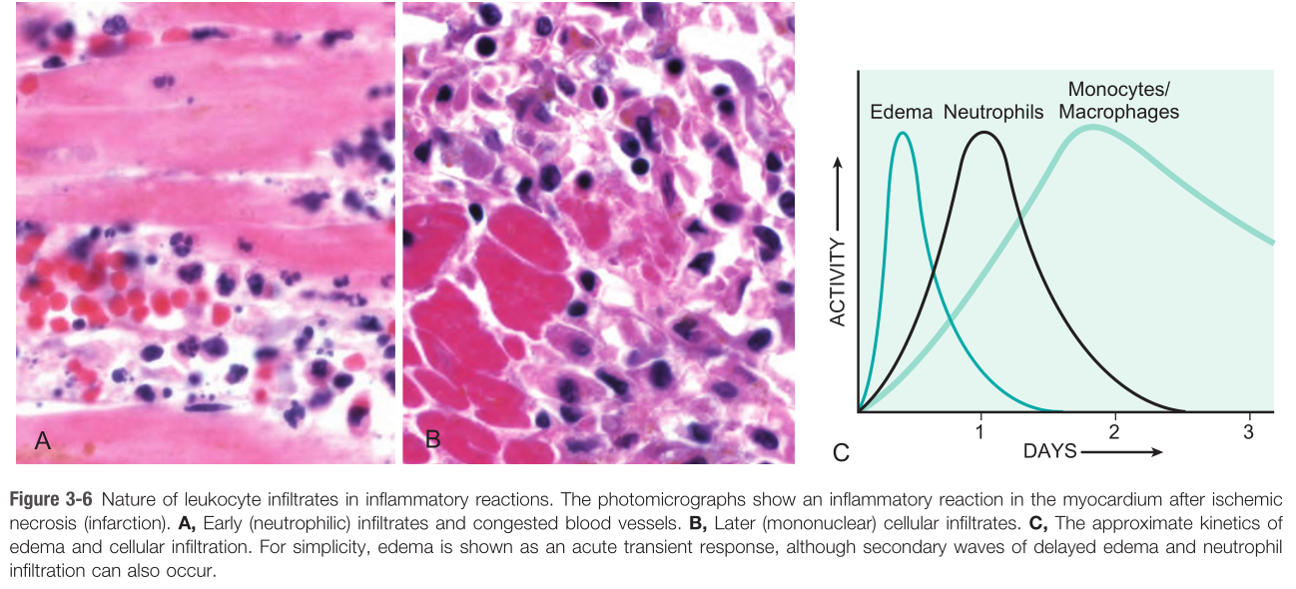
Macrophage phase (peaks around 2-3 days).
162
What is Chediak-Higashi syndrome? What are the 6 clinical symptoms?
A autosomal recessive protein trafficking defect characterized by impaired phagolysosome formation.
1) Recurrent pyogenic infections
2) Neutropenia (no microtubules for cell div ⇒ intrameduallary death of Nφ)
3) Giant granules in leukocytes (fusion of granules)
4) Defective primary hemostasis (defective dense granules in platelets)
5) Albinism
6) Peripheral neuropathy (long axons require transport)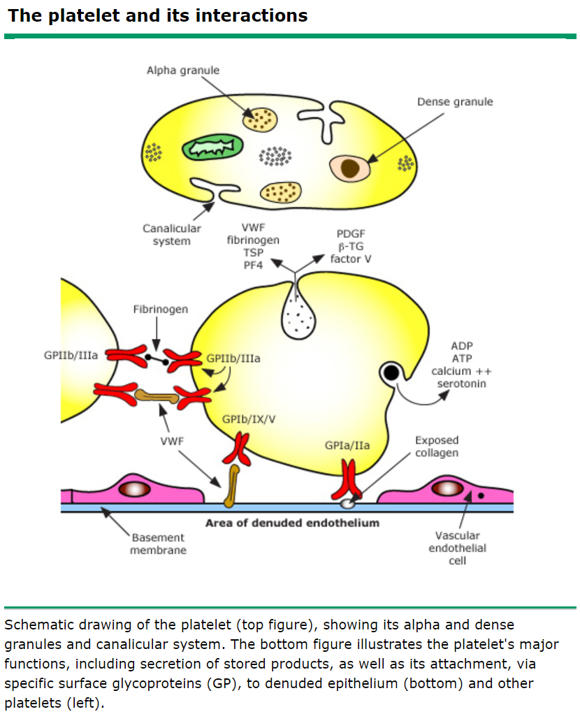
1) Recurrent pyogenic infections
2) Neutropenia (no microtubules for cell div ⇒ intrameduallary death of Nφ)
3) Giant granules in leukocytes (fusion of granules)
4) Defective primary hemostasis (defective dense granules in platelets)
5) Albinism
6) Peripheral neuropathy (long axons require transport)
163
Where does the marginated pool of neutrophils primarily exist within the body?
The lung vasculature
164
What are the 2 mechanisms of phagolytic killing? Which is most effective?
O2-dependent (most effective, involves oxidants and bleach)
O2-independent (involves lysozyme and major basic protein)
O2-independent (involves lysozyme and major basic protein)
165
What broader pathway is the oxidative burst part of? Describe the entire pathway, paying special attention to the enzymes involved:
Oxidative burst is the first step in producing HOCl (bleach) in the phagolysosomes.
1. O2 is converted to superoxide by NADPH oxidase.
2. Superoxide is converted to H2O2 by superoxide dismutase (SOD)
3. H2O2 is converted to HOCl by myeloperoxidase (MPO)
1. O2 is converted to superoxide by NADPH oxidase.
2. Superoxide is converted to H2O2 by superoxide dismutase (SOD)
3. H2O2 is converted to HOCl by myeloperoxidase (MPO)
166
What is chronic granulomatous disease (CGD) (also state inheritence pattern)?
An AR or XLR inherited defect in NADPH oxidase, impairing production of superoxide from oxygen, which in turn impairs O2-dependent killing.
167
What infections are patients with CGD inclined to acquire?
Infection with catalase(+) organisms, specifically:
Pseudomonas
S. aureus
Nocardia
Aspergillus
Candida
Serratia (nosocomial)
Burkholderia cepacia (“foot rot”)
E. coli
Listeria
Staphylococci
H. pylori
Pseudomonas
S. aureus
Nocardia
Aspergillus
Candida
Serratia (nosocomial)
Burkholderia cepacia (“foot rot”)
E. coli
Listeria
Staphylococci
H. pylori
168
What is the screening test for CGD?
*Current clinical standard is the dihydrorhodamine flow cytometry test
Nitroblue tetrazolium test. Test is negative in CGD.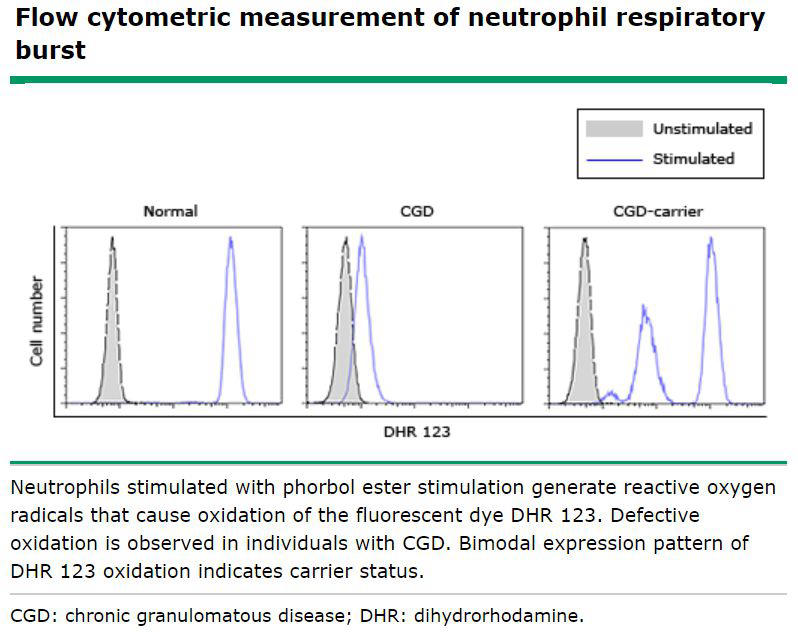
Nitroblue tetrazolium test. Test is negative in CGD.
169
What are the molecular and infectious consequences of MPO deficiency?
Inability to convert H2O2 to HOCl, which increases the risk for Candida infections.
However, most patients are asymptomatic
However, most patients are asymptomatic
170
Can you detect MPO deficiency with nitroblue tetrazolium test?
No, nitroblue tetrazolium test can only screen for presence/absence of NADPH oxidase
171
What enzymes are contained within macrophage and eosinophil secondary granules, respectively?
Lysozyme in macrophages, major basic protein in eosinophils.
172
Describe resolution of a pyogenic infection:
Neutrophils undergo apoptosis and disappear within 24 hours after resolution of the inflammatory stimulus
173
Why do catalase(+) organisms and not catalase(-) cause infection in chronic granulomatous disease?
Even in the absence of NADPH oxidase (which normally functions to produce H2O2), H2O2 produced by phagocytosized bacterial organisms can be converted to HOCl by MPO.
However, catalase(+) organisms degrade the H2O2 they produce, leaving the leukocyte completely unable to make HOCl
However, catalase(+) organisms degrade the H2O2 they produce, leaving the leukocyte completely unable to make HOCl
174
Where do monocytes become macrophages?
In peripheral tissue
175
How do macrophages enter the tissue in inflammation?
Same way as all leukocytes (margination, rolling, adhesion, transmigration, chemotaxis, phagocytosis).
176
How do macrophages kill pathogens?
Injestion (phagocytosis) and enzymatic degradation (e.g. lysozyme) in secondary granules (O2-independent killing).
177
What anti-inflammatory cytokines produced by macrophages initiate infection resolution?
IL-10, TGF-β
178
Macrophages can direct the progression of inflammation in 4 ways - what are they?
1) Continued acute inflammation
2) Abscess
3) Chronic inflammation
4) Resolution and healing
2) Abscess
3) Chronic inflammation
4) Resolution and healing
179
What is continued acute inflammation? What cytokine is it mediated by?
Inflammation with persistent pus formation. IL-8 from macrophages recruits additional neutrophils.
180
What is an abscess?
Acute inflammation surrounded by fibrosis, which is mediated by macrophages via fibrogenic growth factors and cytokines.
181
Generally speaking, how is chronic inflammation mediated by macrophages?
Macrophages continue to present antigen to activate CD4+ helper T cells, which secrete cytokines that promote chronic inflammation.
182
What are 4 general stimuli for chronic inflammation?
Persistent infection (most common cause, e.g. viruses, mycobacteria, parasites, fungi); autoimmune disease;
foreign material;
and some cancers.
foreign material;
and some cancers.
183
What the most common cause of chronic inflammation?
Persistent infection
184
What makes up the TCR complex? What does it do?
TCR and CD3. Recognizes antigen presented on MHC molecules.
185
What MHC molecules do CD4 cells use? CD8?
CD4 - MHC IICD8 - MHC I
186
What 2 signals are required for T cell activation?
Binding of antigen/MHC complex to TCR,Co-stimulation - B7/CD28 interaction for CD4+, IL-2 for CD8+
187
What is the 2nd signal for CD4 helper T cell activation?
B7 (on APC) binds CD28 (on CD4+ T cell)
188
What cytokines do Th1 cells secrete? What functions do they perform?
IFN-γ has 3 key functions: 1) activates macrophages
2) promotes class-switching from IgM to IgG
3) skews helper response towards Th1
IL-2 - co-stimulation for CD8+ T cell activation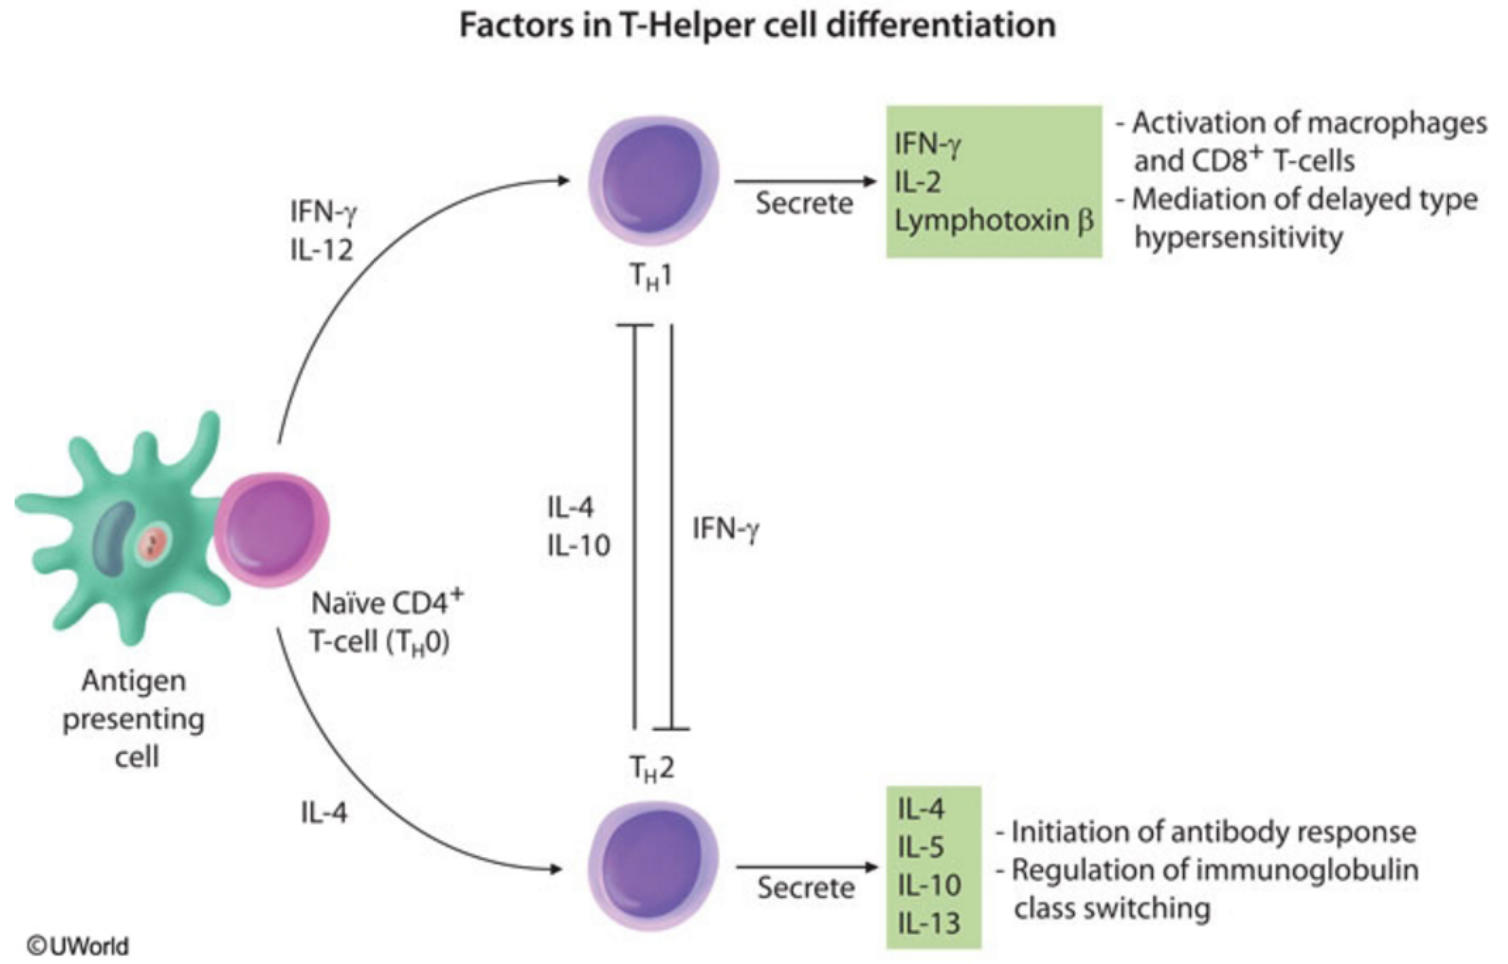
2) promotes class-switching from IgM to IgG
3) skews helper response towards Th1
IL-2 - co-stimulation for CD8+ T cell activation
189
What cytokines do Th2 cells secrete? What are their functions?
IL-4 (facilitates B cell class switching to IgG and IgE)
IL-5 (eosinophil chemotaxis and activation, maturation of B cells to plasma cells, and class switching to IgA)
IL-10 (Th2 skewing)
IL-13 (functions like IL-4)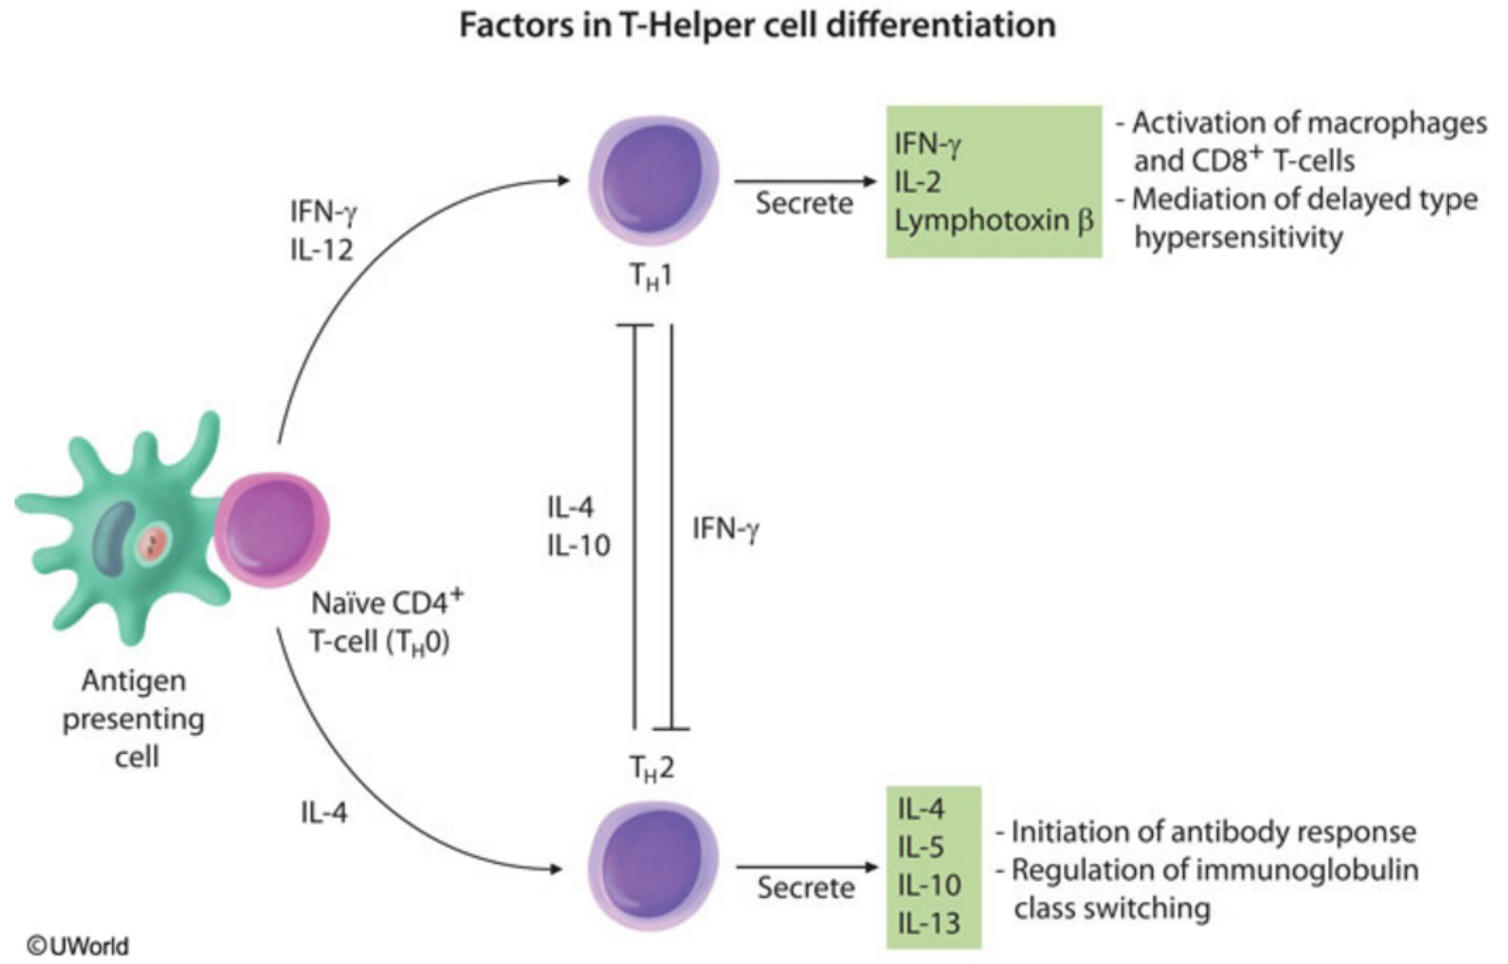
IL-5 (eosinophil chemotaxis and activation, maturation of B cells to plasma cells, and class switching to IgA)
IL-10 (Th2 skewing)
IL-13 (functions like IL-4)
190
What cells express MHC I? What does MHC I do?
Expressed on all nucleated cells in the body and platelets (RBCs are the only exception).
MHC I presents intracellular antigen to CD8 T cells
*Interesting to note, the body has developed mechanisms for dealing with pathogens that disrupt MHC I killing - namely, NK cells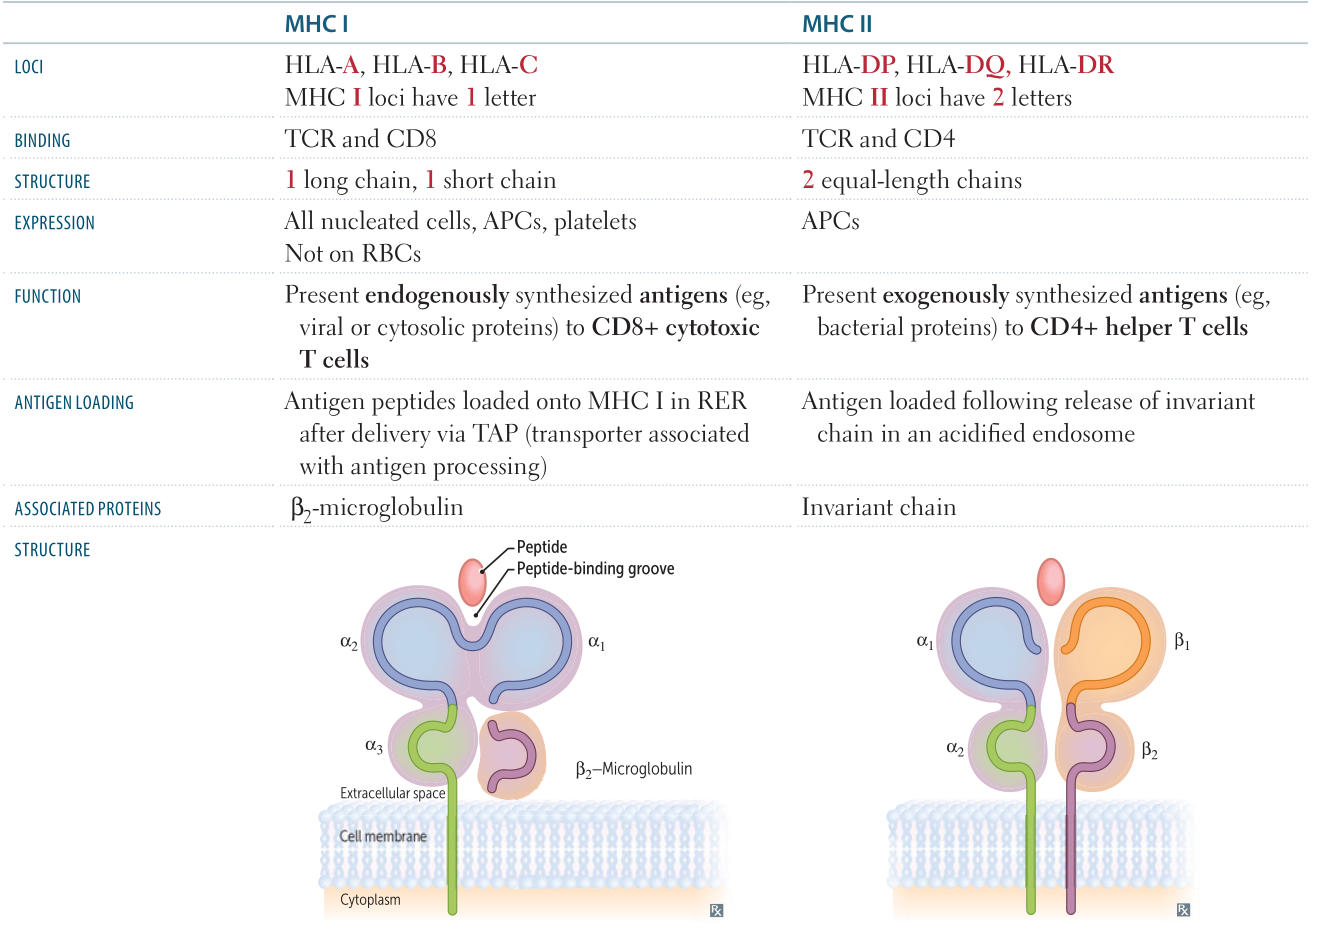
MHC I presents intracellular antigen to CD8 T cells
*Interesting to note, the body has developed mechanisms for dealing with pathogens that disrupt MHC I killing - namely, NK cells
191
How are B cells activated (2 pathways)?
1) Antigen binds to surface IgM or IgD; results in maturation to IgM or IgD secreting plasma cells.
-or-
1) B cell presents antigen to CD4+ helper T cells via MHC class II
2) CD40 (on B cells) binds to CD40L (on CD4 T cell)
3) CD4 T cell secretes IL-4 and IL-5 to induce class switching, hypermutation, maturation
-or-
1) B cell presents antigen to CD4+ helper T cells via MHC class II
2) CD40 (on B cells) binds to CD40L (on CD4 T cell)
3) CD4 T cell secretes IL-4 and IL-5 to induce class switching, hypermutation, maturation
192
What is the 2nd signal for B cell activation?
CD40 (on B cell) interaction CD40L (on helper T cell)
193
What is the 2nd signal for CD8 T cell activation?
IL-2 from CD4 Th1
194
How do cytotoxic CD8+ T cells kill (2 pathways)?
1) secretion of perforin or granzyme 2) by the expression of FasL, which binds Fas on target cells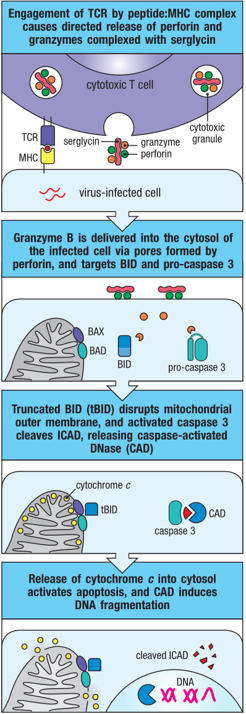
195
What's the defining key feature of granulomas?
Epithelioid histiocytes
196
Describe the structure of a granuloma:
A collection of epithelioid histiocytes (macrophages with abundant pink cytoplasm), surrounded by giant cells and a rim of lymphocytes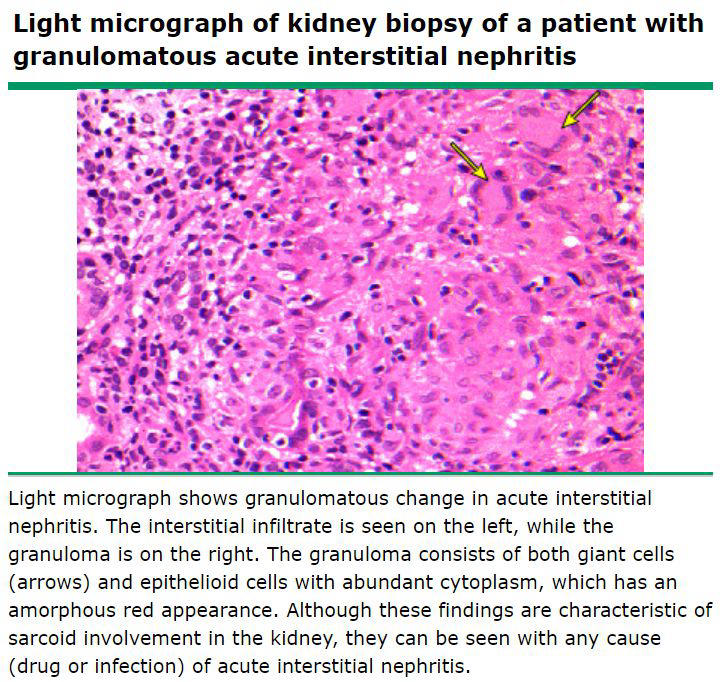
197
What are 2 broad categories of chronic inflammation?
Granulomatous and non-granulomatous
198
What are the 2 categories of granulomatous inflammation?
Caseating and non-caseating
199
What distinguishes caseating granulomas from non-caseating granulomas? What organisms cause caseating granulomas?
Central necrosis (interior cells lack nuclei). Characteristic of tuberculosis and fungal infections
200
Describe non-caseating granulomatous inflammation. Common causes?
Lacks central necrosis.
Reaction to foreign material
sarcoidosis
beryllium exposure
Crohn disease
Bartonella henselae
sarcoidosis:
beryllium:
Crohn:
Bartonella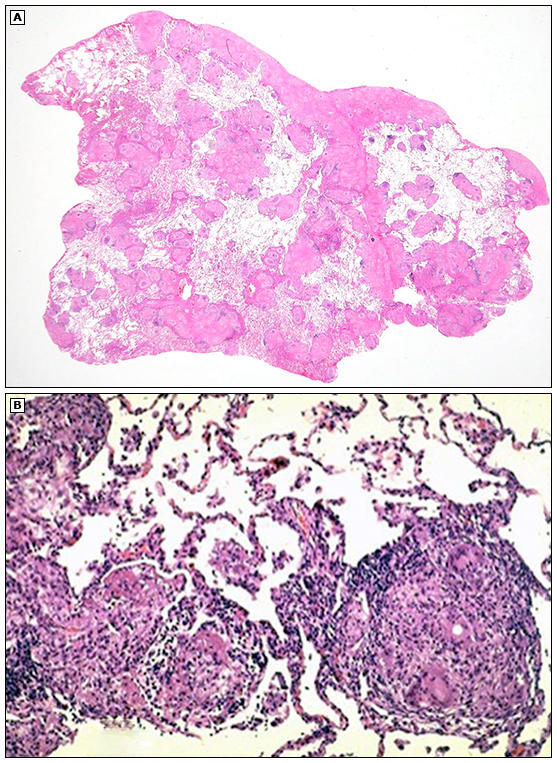
Reaction to foreign material
sarcoidosis
beryllium exposure
Crohn disease
Bartonella henselae
sarcoidosis:
beryllium:
Crohn:
Bartonella
201
What disease is associated with stellate-shaped granulomas?
Cat scratch disease (Bartonella)
202
What is the hallmark lesion in Crohn disease? Ulcerative colitis?
Crohn: Non-caseating granulomas.
UC: Crypt abscesses.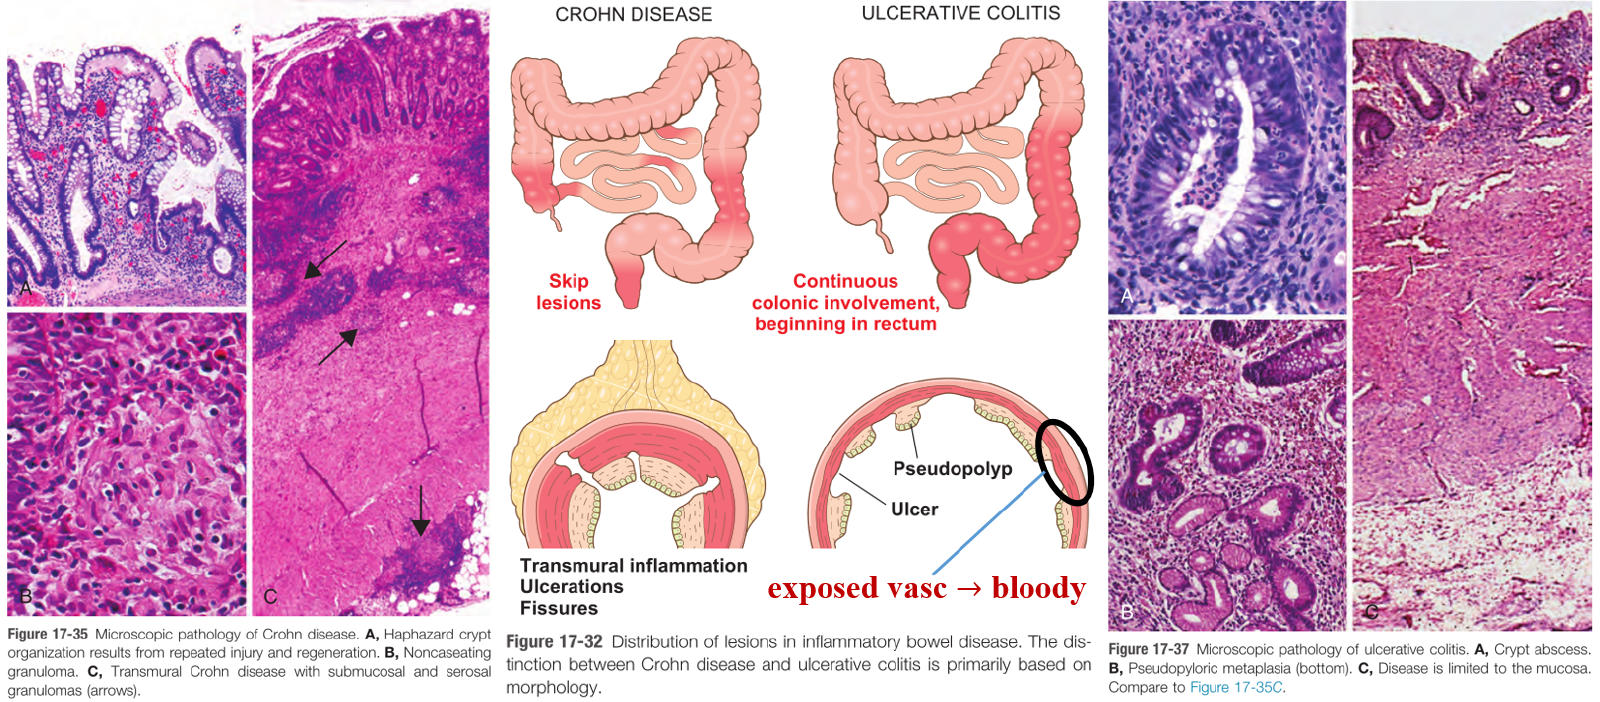
UC: Crypt abscesses.
203
What stains can you use to determine the etiology of a caseating granuloma?
AFB (Ziehl Neelsen) stain to detect TB.
GMS (silver) stain to detect fungus.
GMS (silver) stain to detect fungus.
204
What are the steps involved in granuloma formation?
1) Macrophages process and present antigen to CD4 T cells on MHC II
2) Macrophages then secrete IL-12, which induces CD4 cells to differentiate into the Th1 subtype.
3) Th1 cells secrete IFN-γ, which converts macrophages to epithelioid histiocytes and giant cells.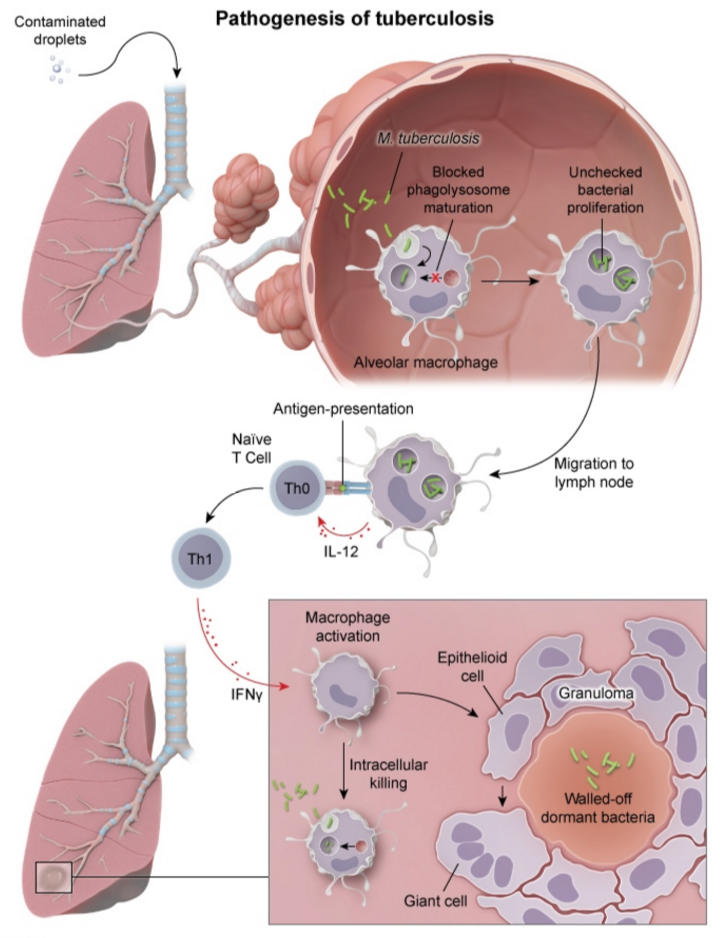
2) Macrophages then secrete IL-12, which induces CD4 cells to differentiate into the Th1 subtype.
3) Th1 cells secrete IFN-γ, which converts macrophages to epithelioid histiocytes and giant cells.
205
What are the primary immunodeficiencies (8)?
DiGeorge syndromeSevere Combined Immunodeficiecy (SCID)
Common Variable Immunodeficiency (CVID)
X-linked agammaglobulinemia (XLA)
IgA deficiency
Hyper-IgM syndrome
Wiskott-Aldrich syndrome
Complement deficiencies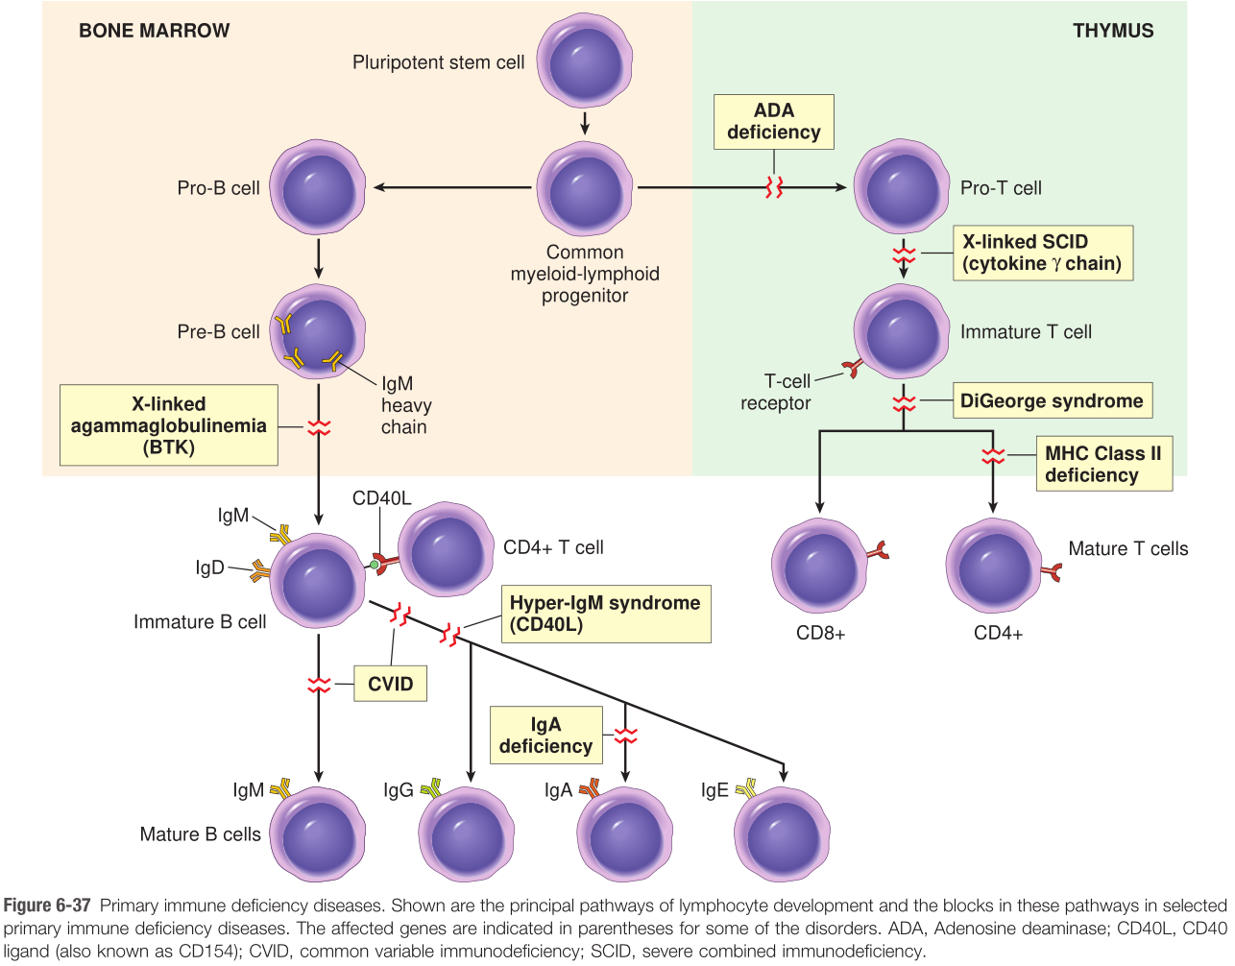
Common Variable Immunodeficiency (CVID)
X-linked agammaglobulinemia (XLA)
IgA deficiency
Hyper-IgM syndrome
Wiskott-Aldrich syndrome
Complement deficiencies
206
SLE represents what type of hypersensitivity?
Type mixed typeII/III (immune-complex mediated)
*If they ask you for one or the other on step, the answer is Type III.
*If they ask you for one or the other on step, the answer is Type III.
207
What is Mixed Connective Tissue Disease (MCTD)? What is a classic "presenting complaint"?
An autoimmune disease of proximal muscles with mixed features of SLE, systemic sclerosis, and polymyositis.
"Patient complains of difficulty combing hair or walking up stairs."
"Patient complains of difficulty combing hair or walking up stairs."
208
What is the difference between regeneration and repair?
Regeneration is replacement of damaged tissue with native tissue.
Repair refers to replacement with a fibrous scar.
Repair refers to replacement with a fibrous scar.
209
What is Familial Mediterranean Fever?
Dysfunction of neutrophils (AR); occurs in persons of Med origin. Presents with episodes of fever and acute serosal inflammation (pericardium, MI, appendicitis)
High SAA (acute phase reactant) attacks deposits as AA amyloid.
High SAA (acute phase reactant) attacks deposits as AA amyloid.
210
Classic clinical findings of systemic amyloidosis (5)?
Nephrotic Syndrome: kidney is most commonly involvedRestrictive Cardiomyopathy
Tongue Enlargement
Malabsorption
Hepatosplenomegaly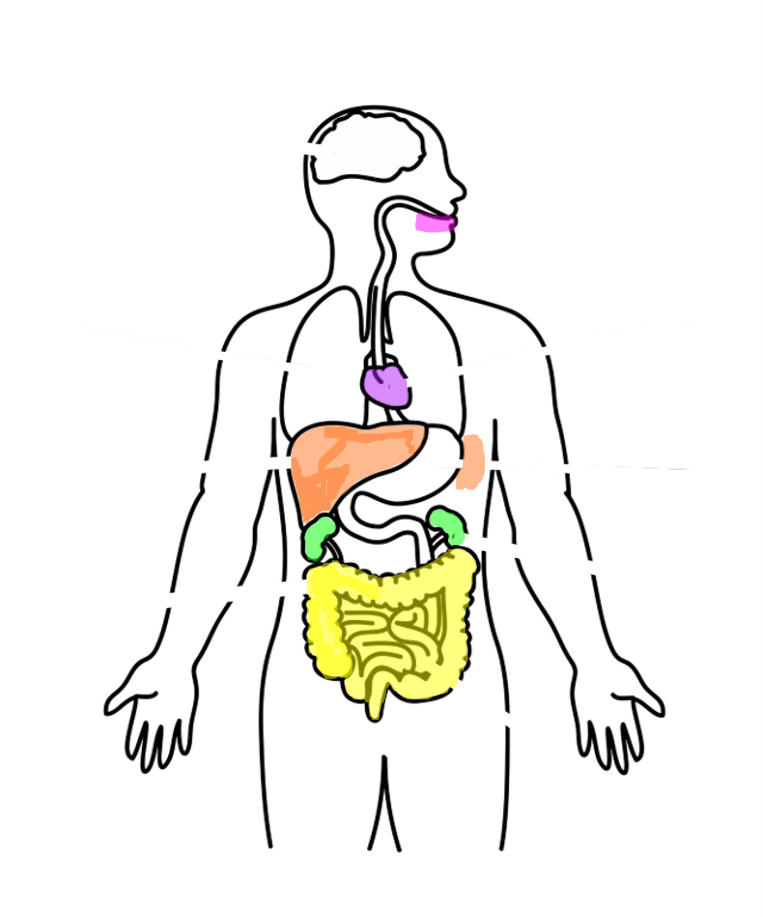
Tongue Enlargement
Malabsorption
Hepatosplenomegaly
211
What is senile cardiac amyloidosis?
Non-mutated serum transthyretin deposits in the heart.
ASYMPTOMATIC.
Commonly seen in the elderly. (25% of eldrly >80 y/o)
*Contrast to familial amyloid cardiomyopathy
ASYMPTOMATIC.
Commonly seen in the elderly. (25% of eldrly >80 y/o)
*Contrast to familial amyloid cardiomyopathy
212
What is familial amyloid cardiomyopathy?
Mutated serum transthyretin deposits in the heart (ATTR). Leads to restrictive cardiomyopathy.
5% of african americans carry mutated gene.
*Contrast to senile cardiac amyloidosis
5% of african americans carry mutated gene.
*Contrast to senile cardiac amyloidosis
213
Compare and contrast Familial Amyloid Cardiomyopathy and Senile Cardiac Amyloidosis:
Familial amyloid cardiomyopathy: Mutated serum transthyretin deposits in the heart. Leads to restrictive cardiomyopathy.
5% of african americans carry mutated gene.
Senile Cardiac Amyloidosis:
Non-mutated serum transthyretin deposits in the heart. ASYMPTOMATIC.
Commonly seen in the elderly.
5% of african americans carry mutated gene.
Senile Cardiac Amyloidosis:
Non-mutated serum transthyretin deposits in the heart. ASYMPTOMATIC.
Commonly seen in the elderly.
214
What kind of amyloidosis are noninsulin-dependent diabetics (T2DM) at risk for developing?
Amylin deposits in islets of pancreas
*Amylin is derived from insulin
*Amylin is derived from insulin
215
What is the type of amyloid that is deposited in dialysis associated amyloidosis?
β2-microglobulin deposits in joints. This protein is normally filtered by kidneys, is not filtered by dialysis. β2-microgoblulin is a structural component of MHC1.
216
How is amyloid associated with medullary carcinoma of the thyroid?
Classic histology is tumor cells with an amyloid background.
Calcitonin deposits also seen within the tumor
*Note, MCT is a cancer of the parafollicular (C) cells of the thyroid.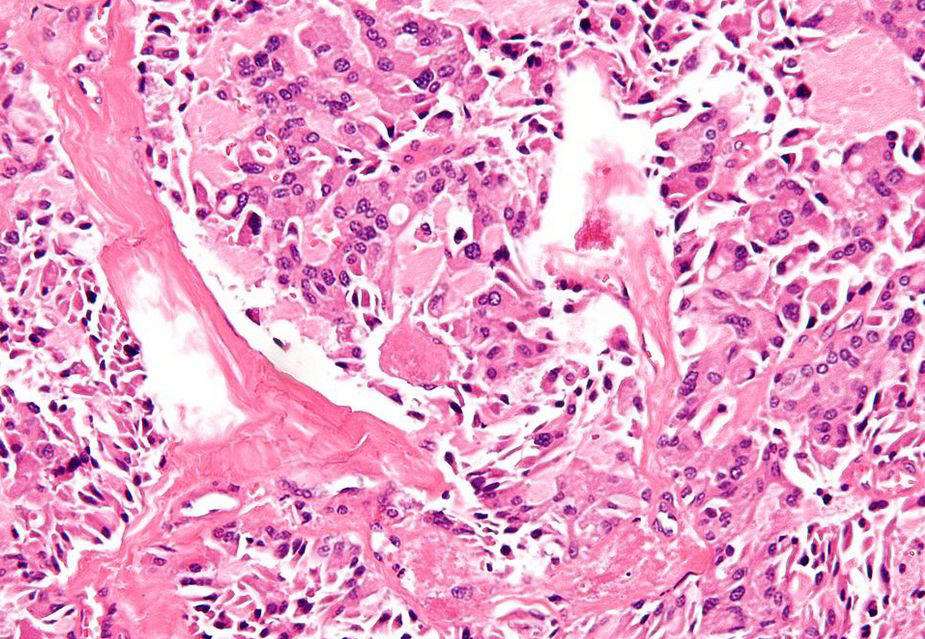
Calcitonin deposits also seen within the tumor
*Note, MCT is a cancer of the parafollicular (C) cells of the thyroid.
217
What is the most common immunodeficiency?
IgA deficiency. Remember that most patients are asymptomatic.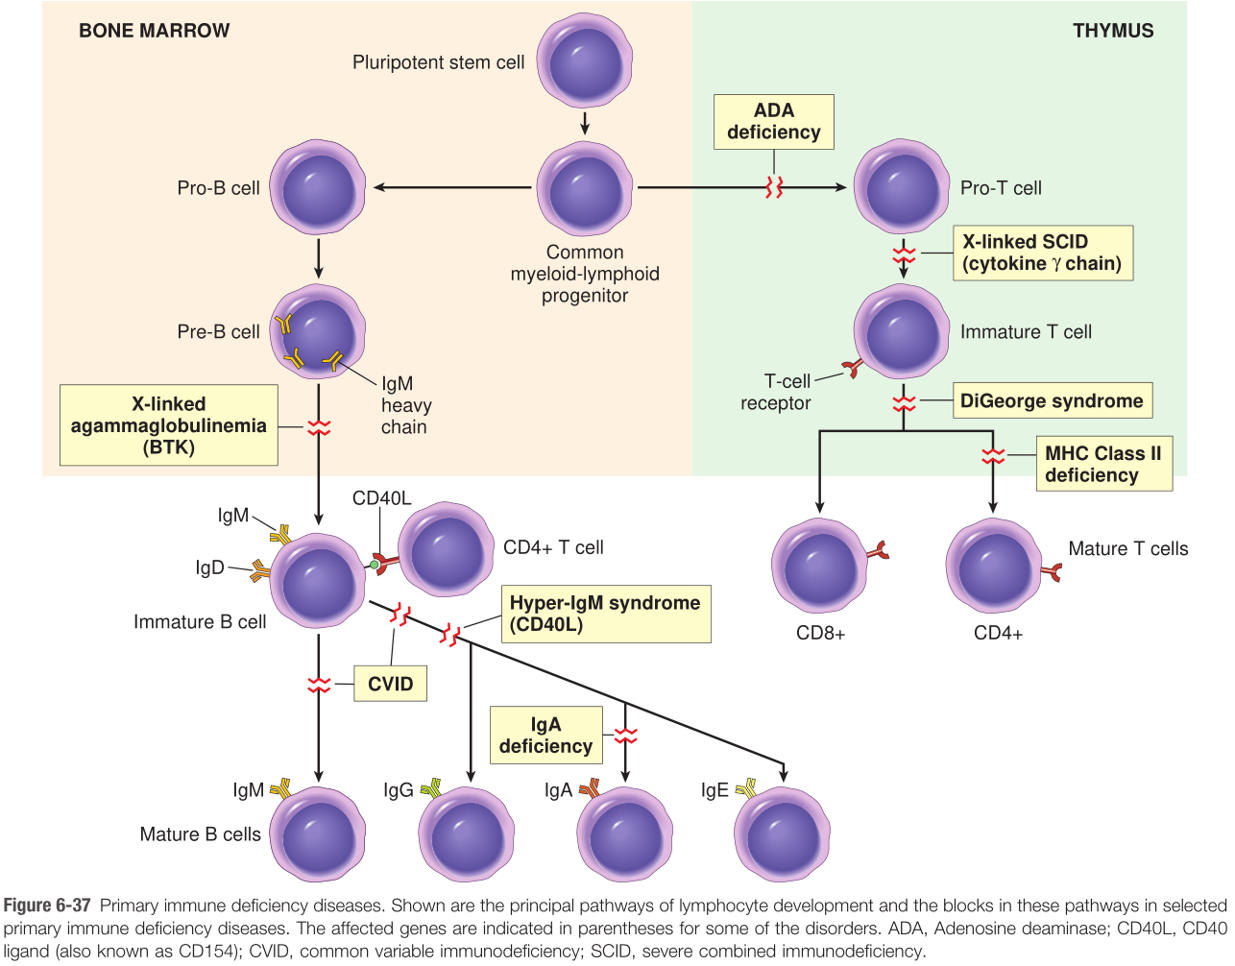
218
Where does T cell negative selection occur?
In the medulla of the thymus.
*Positive selection occurs in the cortex
*Positive selection occurs in the cortex
219
What cells can present self-antigen to the T cell during Negative Selection (2)?
The Medullary Epithelial Cell or a Dendritic Cell.
220
What is AIRE?
AutoImmune REgulator - a transcription factor expressed by medullary epithelial cells of the thymus that expresses self-antigen.
221
Where are the stem cells in the small and large bowel located?
Mucosal Crypts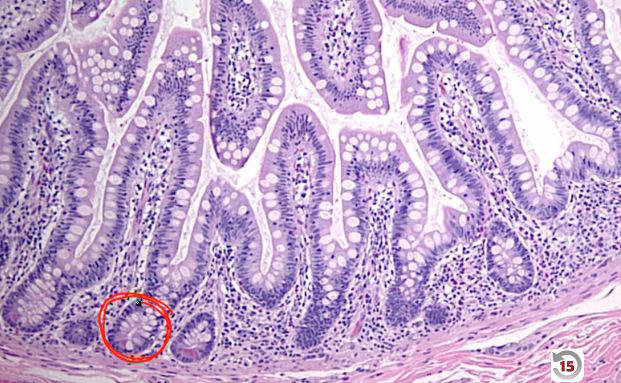
222
Where are the stem cells of the skin located?
In the basal layer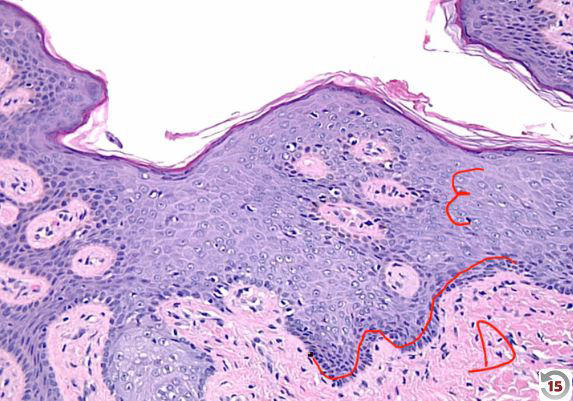
223
What is the stem cell of the lung?
Type II Pneumocytes
224
What are the three types of tissues (based on regenerative capacity)?
Labile Tissues: continuously cycle to regenerate tissue (Small & Large Bowel, Skin, BM)
Stable Tissues: quiescent, but can reenter cell cycle (regeneration of liver by hyperplasia if resected, cells of proximal collecting tubule after acute tubular necrosis).
Permanent Tissue: lack significant regerative potential (myocardia, skeletal muscle, neurons)
Stable Tissues: quiescent, but can reenter cell cycle (regeneration of liver by hyperplasia if resected, cells of proximal collecting tubule after acute tubular necrosis).
Permanent Tissue: lack significant regerative potential (myocardia, skeletal muscle, neurons)
225
What does granulation tissue consist of (3 important components)?
Fibroblasts (deposits Type III collagen: will be replaced by Type I collagen when scar begins to form)Capillaries (provide nutrients)
Myofibroblasts (contract wound)
Myofibroblasts (contract wound)
226
What is collagenase? What cofactor does it require?
Collegenase removes Type III collagen and requires zinc as a cofactor.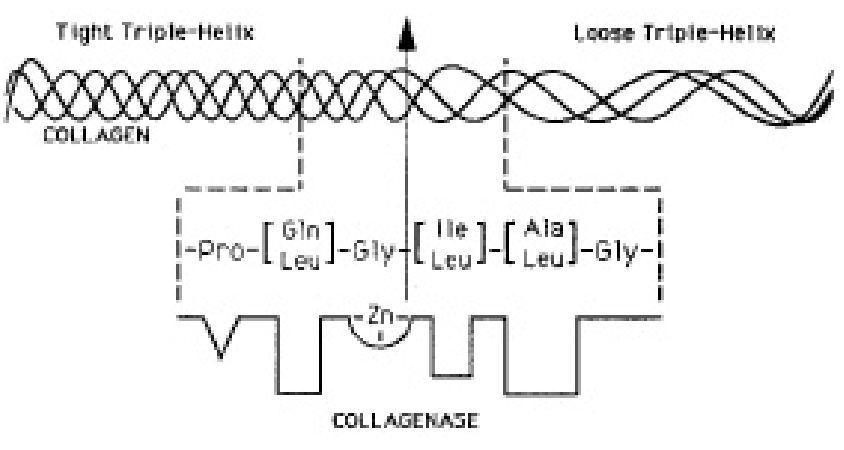
227
What are the two types of cutaneous healing?
Primary intention: wound edges brought together (suture); no scarSecondary intention: edges are not approximated; granulation tissue fills the defect
228
What cell is responsible for mediating wound contraction?
Myofibroblasts
229
What are four possible causes of delayed wound healing? How does each cause a delay?
1) Infection2) Vitamin C deficiency (required for hydroxylation of Pro/Lys)
3) Copper deficiency (lysyl oxidase required for cross-linking of collagen)
4) Zinc deficiency (required for collegenase to convert T3 to T1 collagen)
3) Copper deficiency (lysyl oxidase required for cross-linking of collagen)
4) Zinc deficiency (required for collegenase to convert T3 to T1 collagen)
230
What are keloids? What material are they made of?
Excess production of scar tissue out of proportion to the wound, characterized by excess Type III collagen.
More common in african americans (genetically predisposed)
Affectes earlobes, face, and UEs.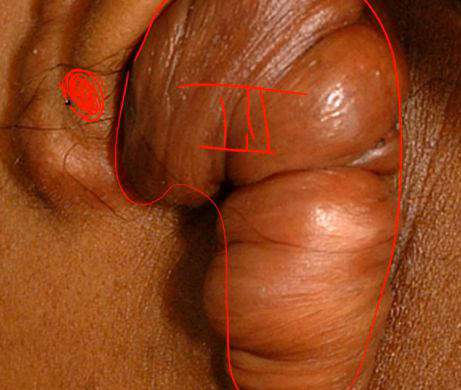
More common in african americans (genetically predisposed)
Affectes earlobes, face, and UEs.
231
What is the key distinguishing characteristic of neoplasia?
Monoclonality: Neoplastic cells (benign or malignant) are derived from a single progenitor.
232
How is the clonality of B cells determined?
Ig light chain phenotype (kappa or lamba)
Normal kappa:lambda ratio is 3:1
In a polyclonal proliferation, the ratio would remain the same.
In a monoclonal proliferation, the ratio would change (↑ or ↓)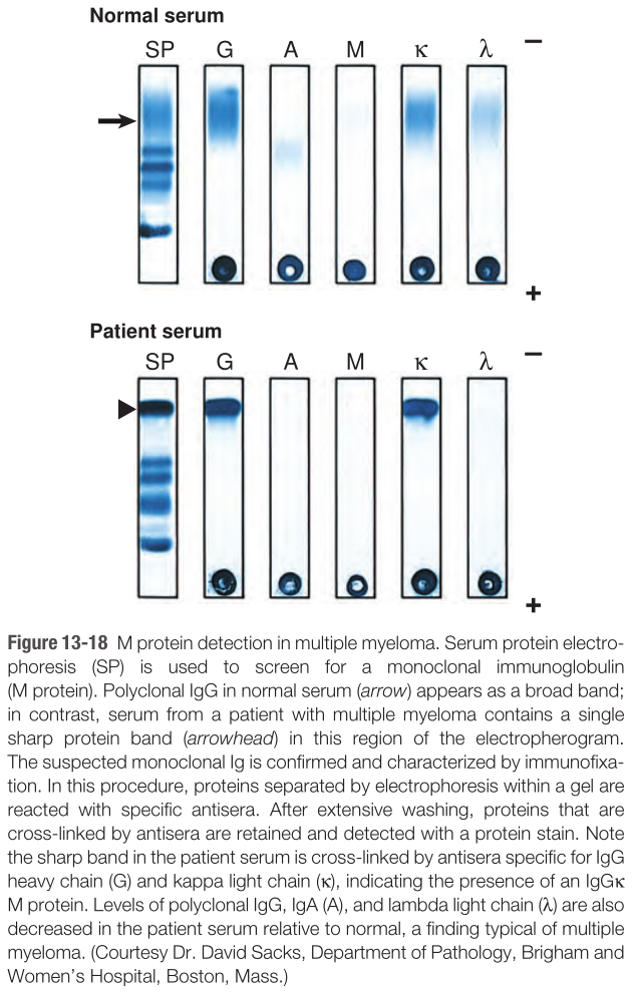
Normal kappa:lambda ratio is 3:1
In a polyclonal proliferation, the ratio would remain the same.
In a monoclonal proliferation, the ratio would change (↑ or ↓)
233
3 major causes of death in adults:
1. Coronary artery disease2. Cancer
3. Cerebrovascular Disease
3. Cerebrovascular Disease
234
3 major causes of death in children:
1. Accidents2. Cancer
3. Congenital defects
3. Congenital defects
235
Cancer begins as a single mutated cell. How many divisions occurs before the earliest symptoms arise?
Approximately 30 divisions occur before the earliest symptoms arise.
236
What cancer is associated with Aflatoxin?
Hepatocellular Carcinoma
*Derived from Aspergillus, which can contaminate stored grains.
*Derived from Aspergillus, which can contaminate stored grains.
237
What cancers are associated with alkylating agents?
Leukemia/lymphoma
*long term side effect of chemotherapy.
*long term side effect of chemotherapy.
238
What cancers are associated with alcohol consumption (2)?
Squamous cell carcinoma of oropharynx and upper esophagus
Hepatocellular carcinoma
Hepatocellular carcinoma
239
What cancers are associated with arsenic exposure (3)?
Squamous cell carcinoma of the skinLung cancer (arsenic is present in cigarette smoke)
Angiosarcoma of the liver
Angiosarcoma of the liver
240
What cancers are associated with asbestos exposure?
Lung cancer (bronchogenic carcinoma)Mesothelioma
*Exposure to asbestos is more likely to lead to lung cancer rather than mesothelioma.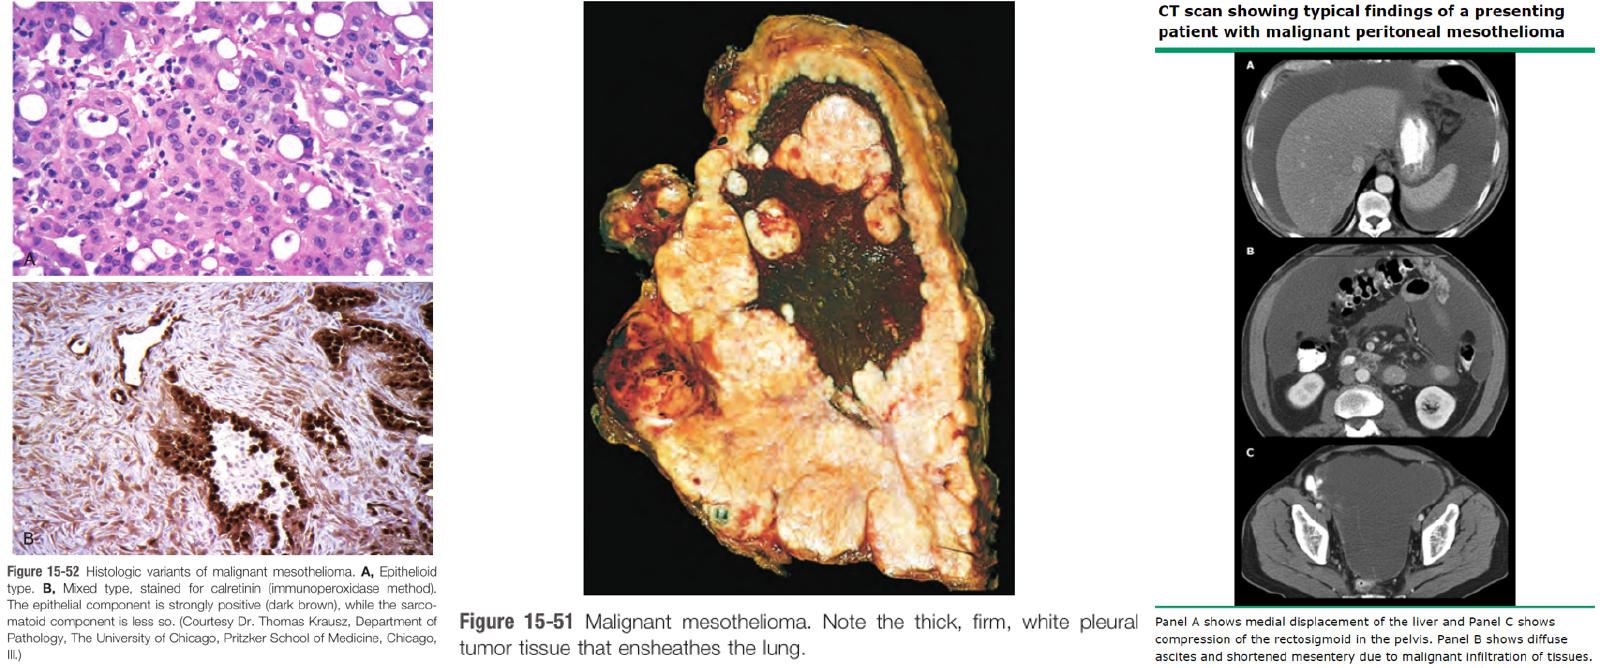
*Exposure to asbestos is more likely to lead to lung cancer rather than mesothelioma.
241
What cancers are associated with smoking (5)?
Carcinoma of the oropharynx,
Esophagus,
Lung,
Kidney, and
Bladder
*Polycyclic hydrocarbons are particularly carcinogenic.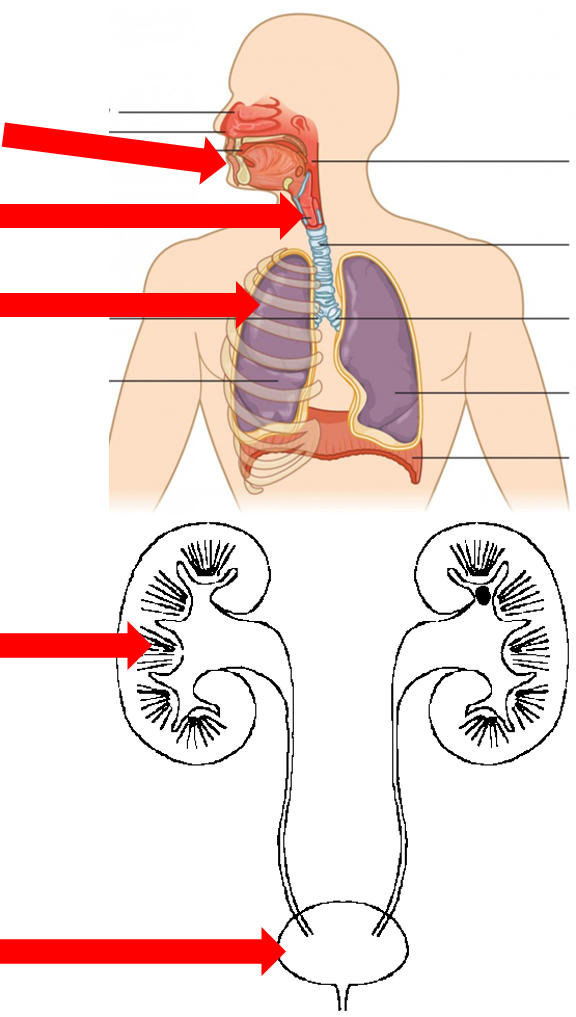
Esophagus,
Lung,
Kidney, and
Bladder
*Polycyclic hydrocarbons are particularly carcinogenic.
242
What cancer is associated with nitrosamines?
Gastric adenocarcinoma (intestinal type)
*Found in smoked foods; responsible for high rate of stomach carcinoma in Japan.
Memory Tips:
NITROsamine - can eat something cooked w/ nitro fuel
naphTHYLamine - "filling" is a bladder problem (filling the stomach? no problem!)
*Found in smoked foods; responsible for high rate of stomach carcinoma in Japan.
Memory Tips:
NITROsamine - can eat something cooked w/ nitro fuel
naphTHYLamine - "filling" is a bladder problem (filling the stomach? no problem!)
243
What cancer is associated with naphthylamine?
Urothelial carcinoma of the bladder
*Naphthylamine is derived from cigarette smoke
Memory Tips:
NITROsamine - can eat something cooked w/ nitro fuel
naphTHYLamine - "filling" is a bladder problem (filling the stomach? no problem!)
*Naphthylamine is derived from cigarette smoke
Memory Tips:
NITROsamine - can eat something cooked w/ nitro fuel
naphTHYLamine - "filling" is a bladder problem (filling the stomach? no problem!)
244
What cancer is associated with vinyl chloride?
Angiosarcoma of the liver
*Occupational exposure used to make PVC pipes.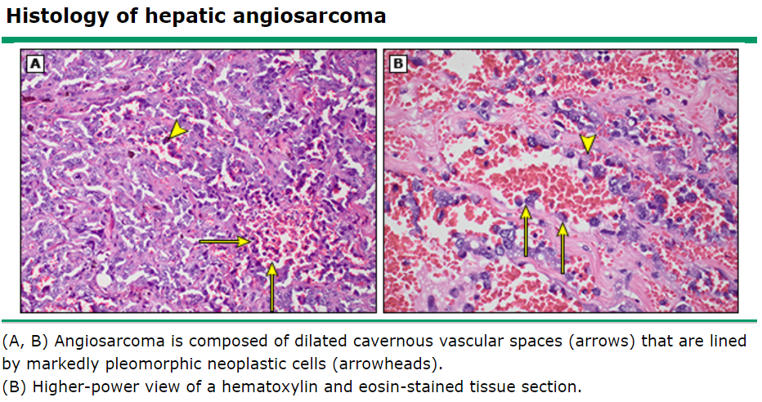
*Occupational exposure used to make PVC pipes.
245
What cancer is associated with nickel, chromium, beryllium, or silica?
Lung carcinoma
246
What cancers are associated with EBV (4)?
Nasopharyngeal Carcinoma (Chinese males & africans)Burkitt Lymphoma
CNS Lymphoma in AIDS
Hodgkin Lymphoma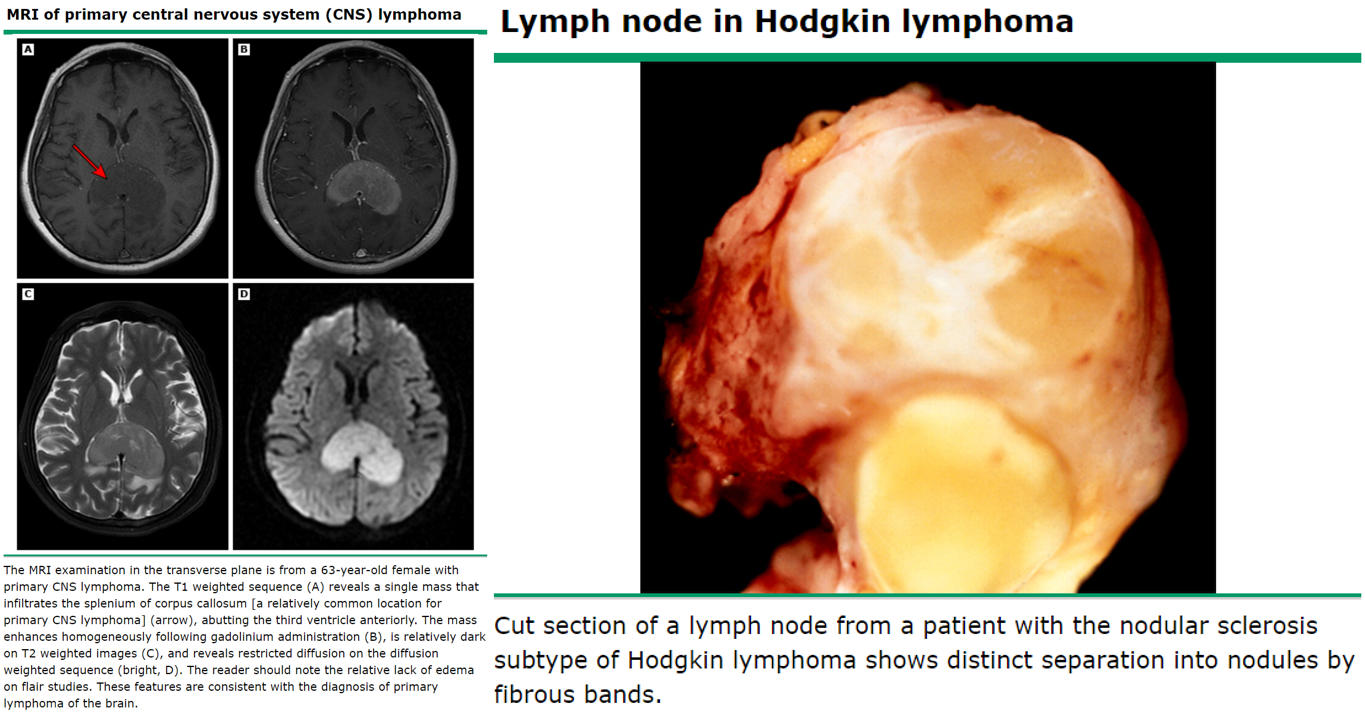
CNS Lymphoma in AIDS
Hodgkin Lymphoma
247
What cancers are associated with HHV-8? Which patients get this and what would be the treatment for each?
Kaposi Sarcoma (carcinoma of endothelial cells in the skin)
1. Older Eastern European Males; excision
2. AIDS patients; HAART (Highly Active Antiretroviral Therapy)
3. Transplant Patients; reduce immunosuppression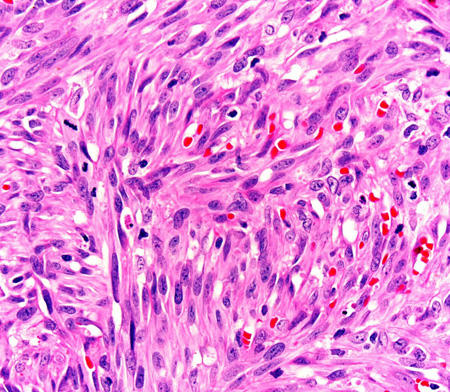
1. Older Eastern European Males; excision
2. AIDS patients; HAART (Highly Active Antiretroviral Therapy)
3. Transplant Patients; reduce immunosuppression
248
What cancer is associated with HBV and HCV?
Hepatocellular carcinoma
249
What cancer is associated with HTLV-1?
Adult T Cell Leukemia/Lymphoma
250
What cancers are associated with HPV 16, 18, 31, 33?
Squamous cell carcinoma of the vulva, vagina, anus, and cervix;
Adenocarcinoma of the cervix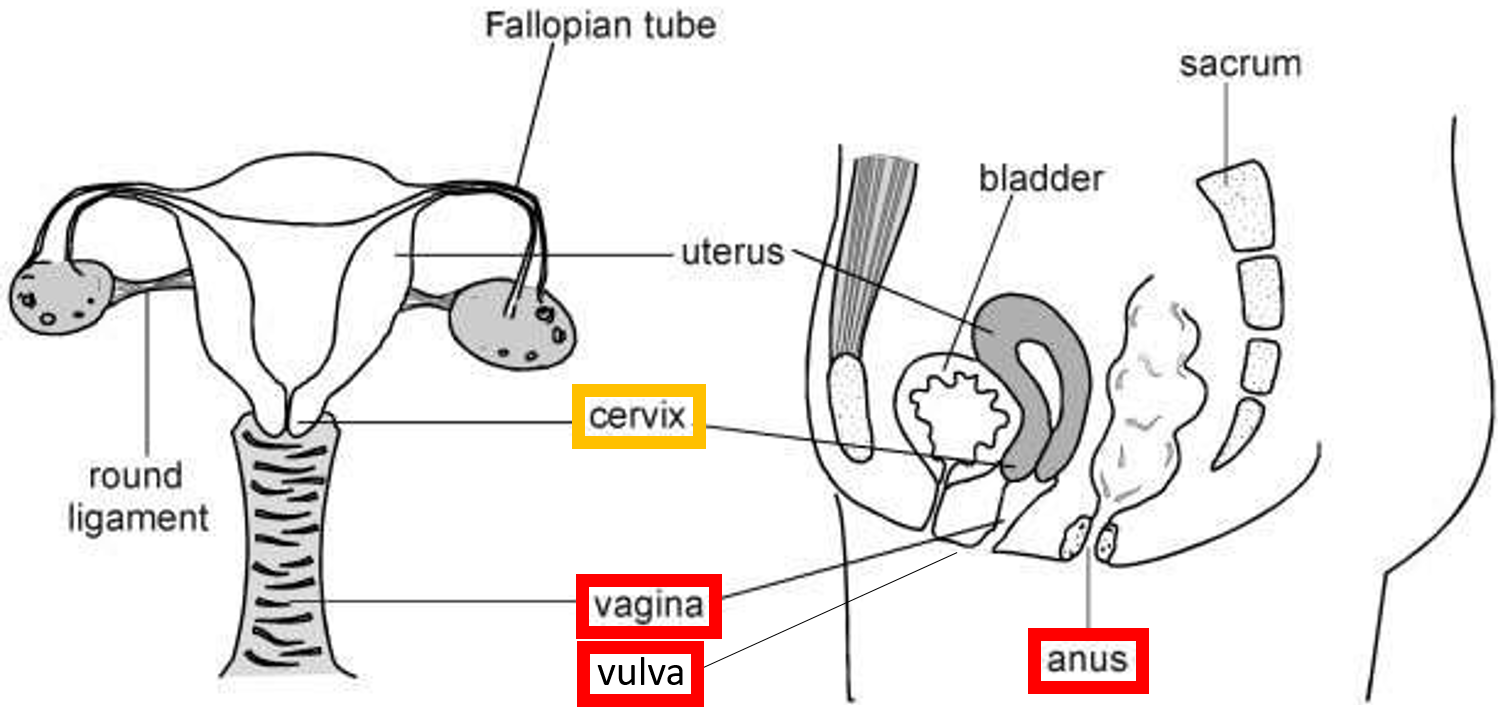
Adenocarcinoma of the cervix
251
What cancers are associated with ionizing radiation (nuclear reactor accidents and radiotherapy)?
Papillary carcinoma of the thyroidAML
CML
*Generates hydroxyl free radicals.
Memory Tip:
Associate "nuclear blasts" with "blast crises"
CML
*Generates hydroxyl free radicals.
Memory Tip:
Associate "nuclear blasts" with "blast crises"
252
What cancers are associated with non-ionizing radiation (UVB sunlight)?
Basal Cell CarcinomaSquamous Cell Carcinoma
Melanoma
*Results in formation of pyrmidine dimers in DNA, which are normally excised by restriction endonuclease. Ergo, patients with Xeroderma Pigmentosum develop these cancers
Melanoma
*Results in formation of pyrmidine dimers in DNA, which are normally excised by restriction endonuclease. Ergo, patients with Xeroderma Pigmentosum develop these cancers
253
Which proto-oncogene is dysfunctional in astrocytoma? How does it become aberrantly expressed?
PDGF-β, hence fibrous growths. Autocrine loop/overexpression.
*Tie-in: remember that scleroderma also involves a postive feedback loop involving PDGF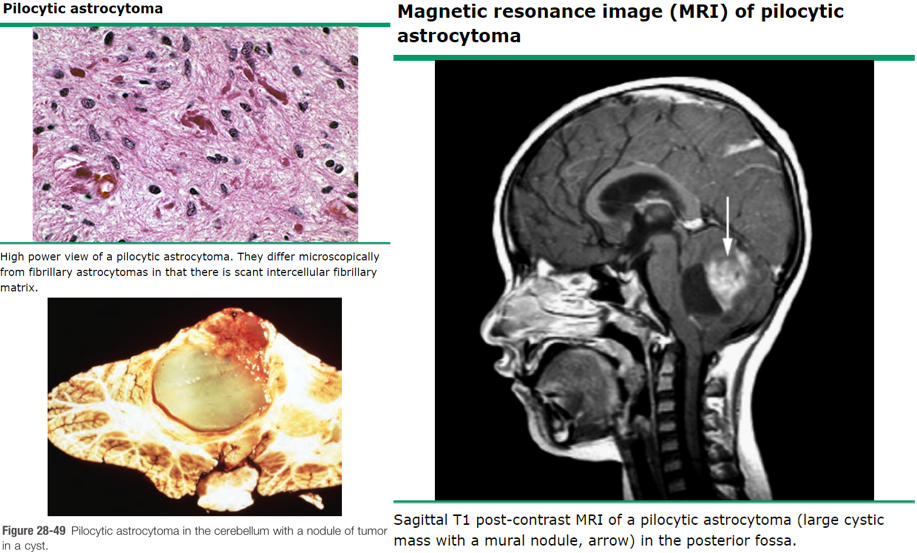
*Tie-in: remember that scleroderma also involves a postive feedback loop involving PDGF
254
What cancer is associated with ERBB2 overexpression? What mechanism leads to this overexpression?
ERBB2 (HER2/neu) - Breast Cancers; amplification
* Epidermal growth factor receptor
* Epidermal growth factor receptor
255
What (3) cancer syndromes/cancers are associated with RET mutations? What kind of mutation is typical?
MEN2A
MEN2B
Sporadic medullary carcinoma of thyroid (*note: often seen in MEN2A and 2B)
Often a point mutation
*RET neural growth factor receptor
*Important to remember: medullary carcinoma of the thyroid is a malignancy of the C cells (calcitonin producing). Classic histology is malignant cells amongst a background of amyloid protein.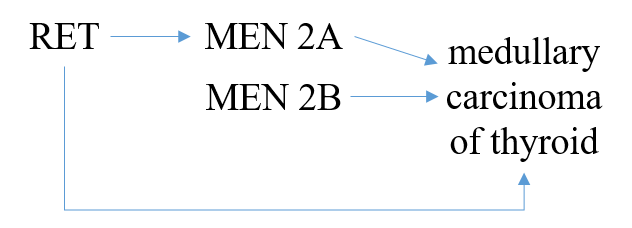
MEN2B
Sporadic medullary carcinoma of thyroid (*note: often seen in MEN2A and 2B)
Often a point mutation
*RET neural growth factor receptor
*Important to remember: medullary carcinoma of the thyroid is a malignancy of the C cells (calcitonin producing). Classic histology is malignant cells amongst a background of amyloid protein.
256
What cancer is associated with a KIT mutation? What type of mutation is it?
Gastrointestinal Stromal Tumor (GIST)
Point mutation
*KIT stem growth factor receptor
Point mutation
*KIT stem growth factor receptor
257
Ras mutations are associated with what cancers? What kind of mutation?
Carcinomas, melanoma, lymphoma
Point mutation
E.g. present in
90% of pancreatic adenocarcinomas and cholangiocarcinomas,
50% of colon, endometrial, and thyroid cancers,
30% of lung adenocarcinomas and myeloid leukemias
Remember that vemurafenib (B-Raf inhibitor) treats metastatic melanoma
*RAS gene familly - signal transducer (GTP-binding proteins)
Point mutation
E.g. present in
90% of pancreatic adenocarcinomas and cholangiocarcinomas,
50% of colon, endometrial, and thyroid cancers,
30% of lung adenocarcinomas and myeloid leukemias
Remember that vemurafenib (B-Raf inhibitor) treats metastatic melanoma
*RAS gene familly - signal transducer (GTP-binding proteins)
258
What are the 3 MYC family regulators? What cancers is each associated with?
c-MYC: Burkitt Lymphoma L-MYC: Lung carcinoma (smaLL ceLL)
N-MYC: Neuroblastoma
*MYC Nuclear regulators (transcription factors)
Memory Tip:
Cancer cells are "CLoNes" of one another
N-MYC: Neuroblastoma
*MYC Nuclear regulators (transcription factors)
Memory Tip:
Cancer cells are "CLoNes" of one another
259
Cyclin D1 rearrangment is associated with what cancer? CDK4 amplification?
CCND1 (Cyclin D1) - Mantle Cell Lymphoma - t(11:14)CDK4 - Melanoma
*Cell cycle regulators - CCD1 (Cyclin D1) & CDK4 (Cyclin-dependent kinase)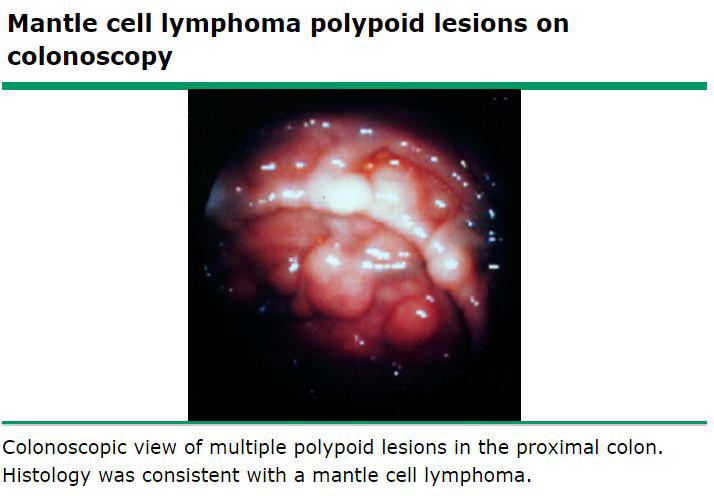
*Cell cycle regulators - CCD1 (Cyclin D1) & CDK4 (Cyclin-dependent kinase)
260
p53 regulates progression from which cell cycle checkpoint? What will it do in the event of reparable DNA damage?
Regulates G1 → S progression
In response to fixable damage, p53 slows the cell cycle and upregulates DNA repair enzymes.
In response to fixable damage, p53 slows the cell cycle and upregulates DNA repair enzymes.
261
What cellular progression checkpoint does Retinoblastoma protein (Rb) regulate? How does it do this?
Like p53, regulates progression from G1 to S phase.
1) Rb is normally bound to E2F (transcription factor).
2) When Rb is phosphorylated by Cyclin D/CDK4, it releases E2F
Rb mutation results in constitutively active E2F
Loss of Rb, E2F is constitively active --> TUMOR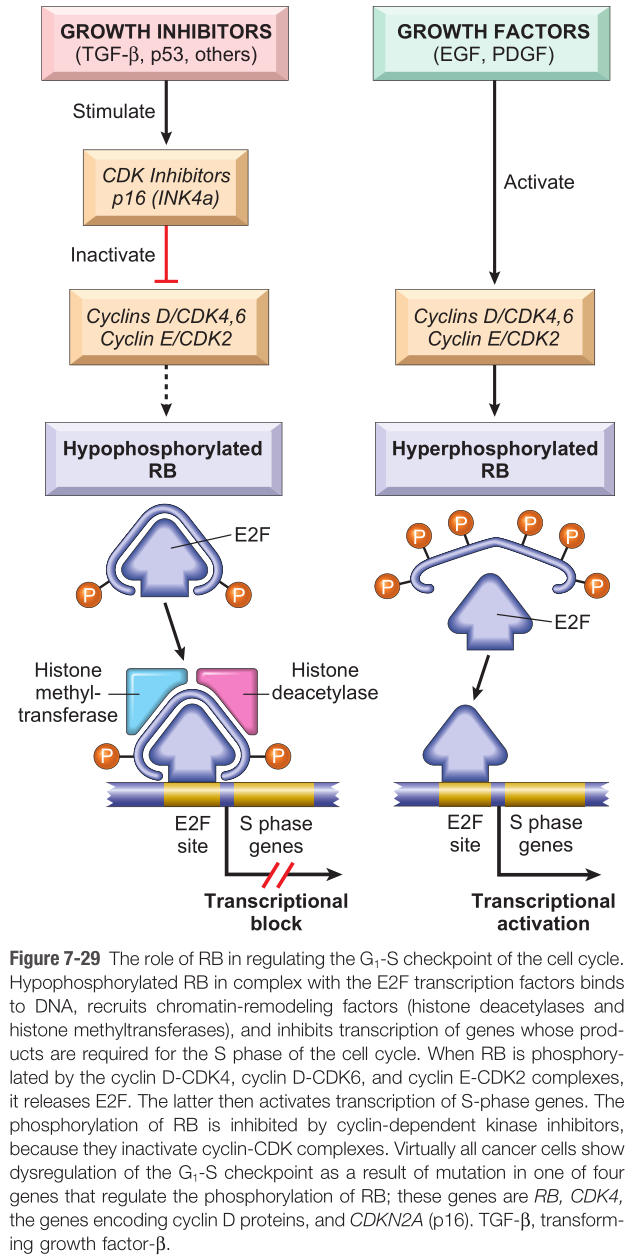
1) Rb is normally bound to E2F (transcription factor).
2) When Rb is phosphorylated by Cyclin D/CDK4, it releases E2F
Rb mutation results in constitutively active E2F
Loss of Rb, E2F is constitively active --> TUMOR
262
How will sporadic vs. germline mutation of Rb present?
Sporadic: unilateral retinoblastoma
Germline (familal): bilateral retinoblastoma and osteosarcoma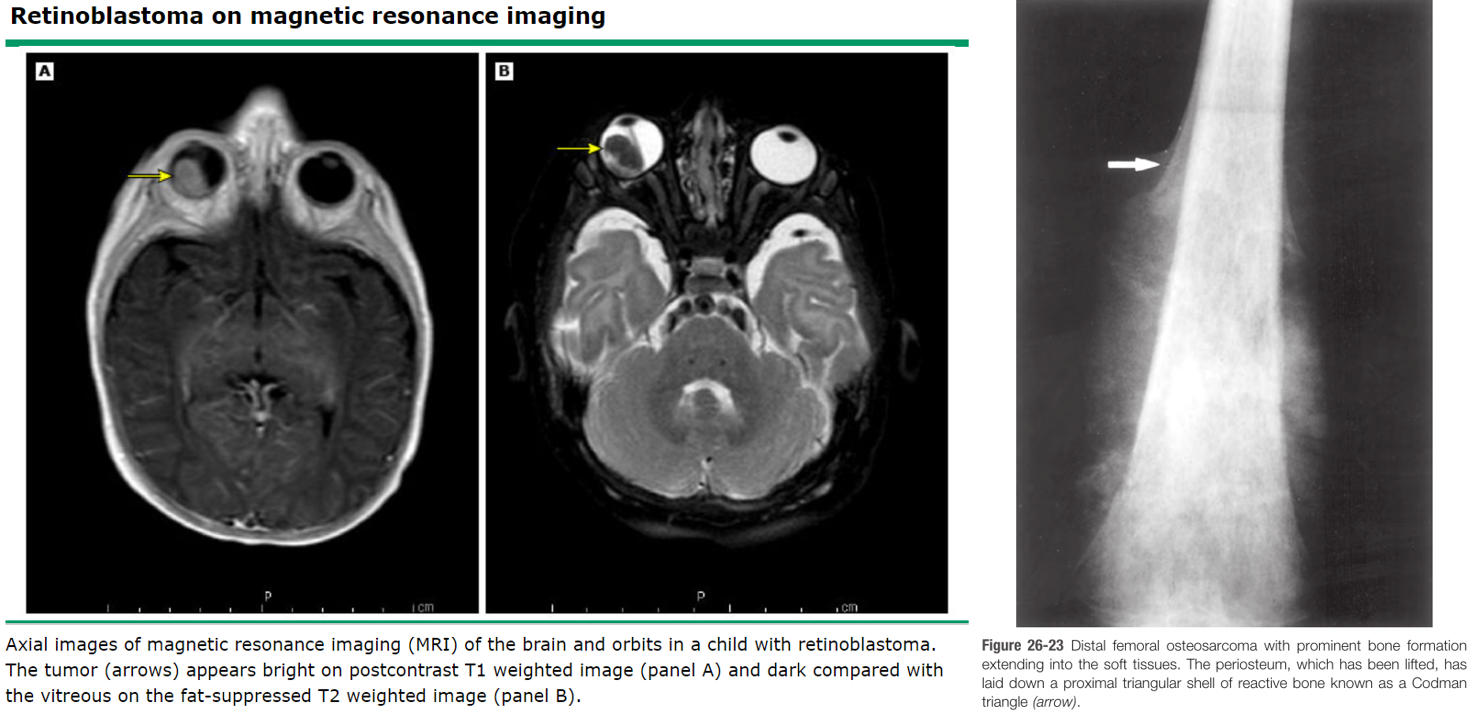
Germline (familal): bilateral retinoblastoma and osteosarcoma
263
What is the function of Bcl2?
Broadly: to prevent apoptosis in healthy cells and induce it in damagd cells.
Specifically: blocks release of cytochrome c through Bak/Bax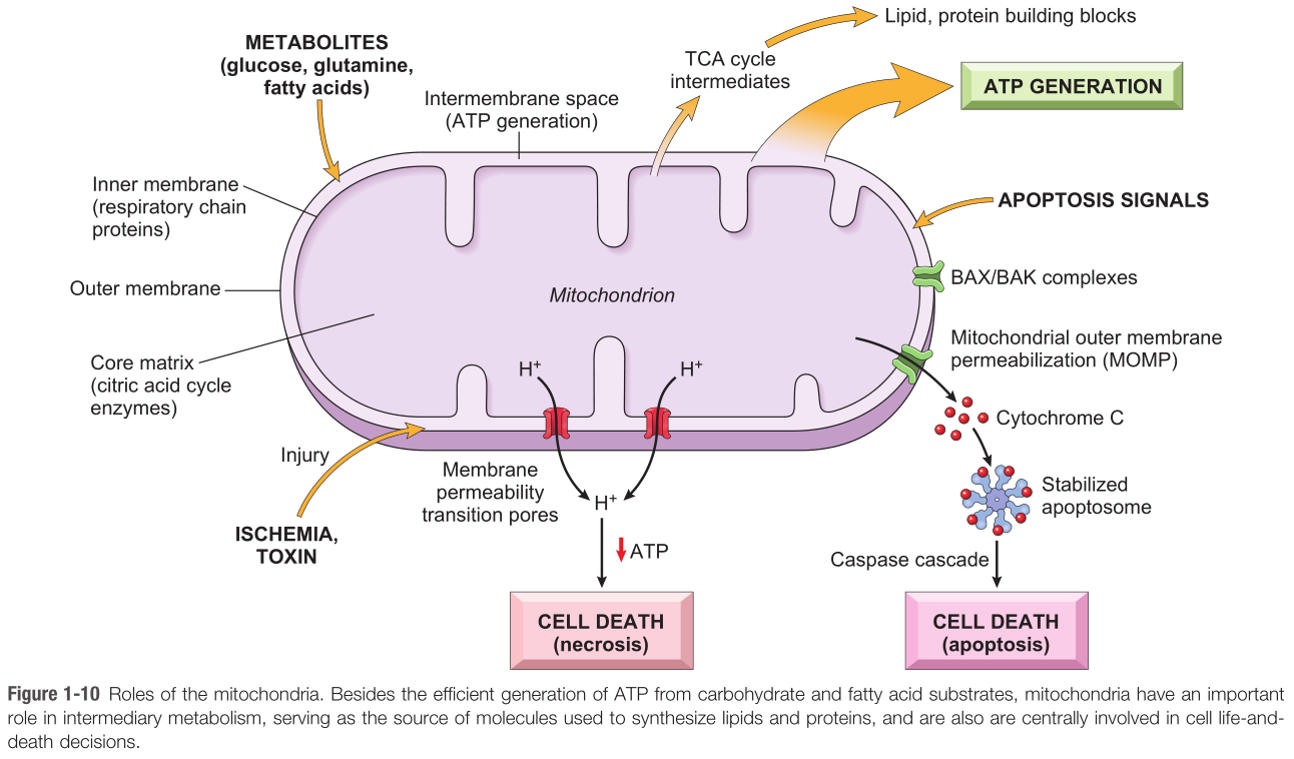
Specifically: blocks release of cytochrome c through Bak/Bax
264
How does a constitutively active Bcl2 induce follicular lymphoma pathogenesis?
1) Mitochondrial membrane further stabilized by Bcl2 overexpression2) B cells that would undergo apoptosis during somatic hypermutation in the lymph node germinal center accumulate
265
What two growth factors are commonly produced by tumor cells? Why?
FGFVEGF
*Required for angiogenesis
*Required for angiogenesis
266
Tumor cells often evade immune surveillance by?
Downregulating MHC I
*Reminder that immunodeficiency increases risk for cancer
*Reminder that immunodeficiency increases risk for cancer
267
The process of tumor invasion and spread is well-modeled by considering the epithelial tumor. What are the 5 steps of epithelial tumor invasion and spread?
1. Downregulation of E-cadherin leads to disassociation of cells
2. Cells attach to laminin (anchors cells to basal lamina)
3. Cell destroy basement membrane via type IV collagenase
4. Cells attach to fibronectin in the ECM and spread locally
5. Cells enter into blood vessels or lymphatics and metastasize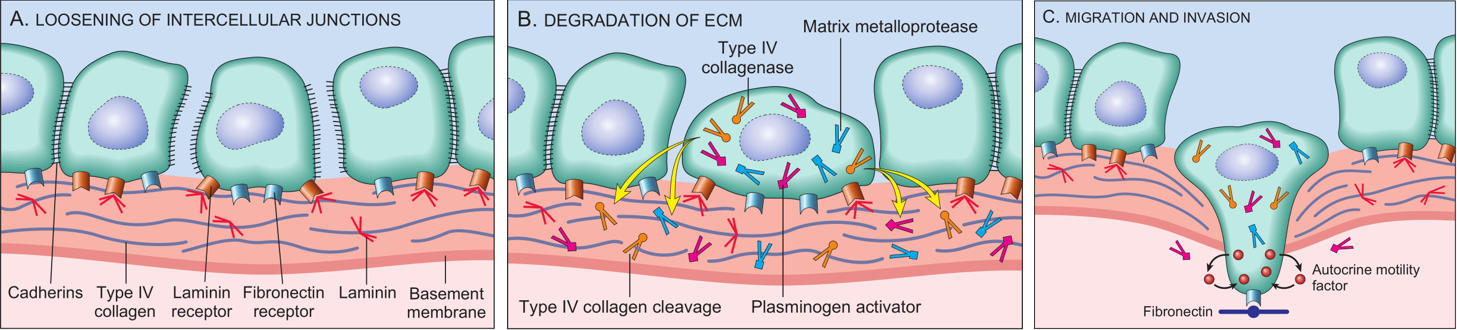
2. Cells attach to laminin (anchors cells to basal lamina)
3. Cell destroy basement membrane via type IV collagenase
4. Cells attach to fibronectin in the ECM and spread locally
5. Cells enter into blood vessels or lymphatics and metastasize
268
Lymphatic spread is most characteristic of carcinomas. However, some carcinomas spread hematogenously - which ones?
HCC (Hepatic Vein)
Choriocarcinoma (trophoblastic malignant cancer. Remember what trophoblast do!)
Renal Cell Carcinoma (Renal Vein)Follicular Carcinoma of Thyroid
"Hematogenously spreading Cancers Reign Foolishly"
Choriocarcinoma (trophoblastic malignant cancer. Remember what trophoblast do!)
Renal Cell Carcinoma (Renal Vein)Follicular Carcinoma of Thyroid
"Hematogenously spreading Cancers Reign Foolishly"
269
Seeding of body cavities is characteristic of what cancer?
Ovarian Carcinoma
Omental Caking is characteristic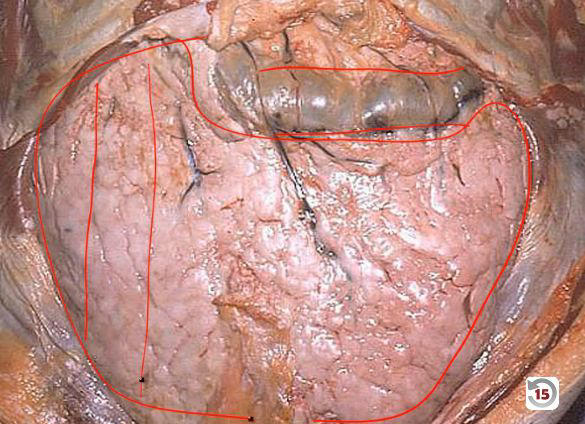
Omental Caking is characteristic
270
What tissue type is keratin positive?
Epithelium
271
What tissue type is vimentin positive?
Mesenchyme
272
What tissue type is desmin positive?
Muscle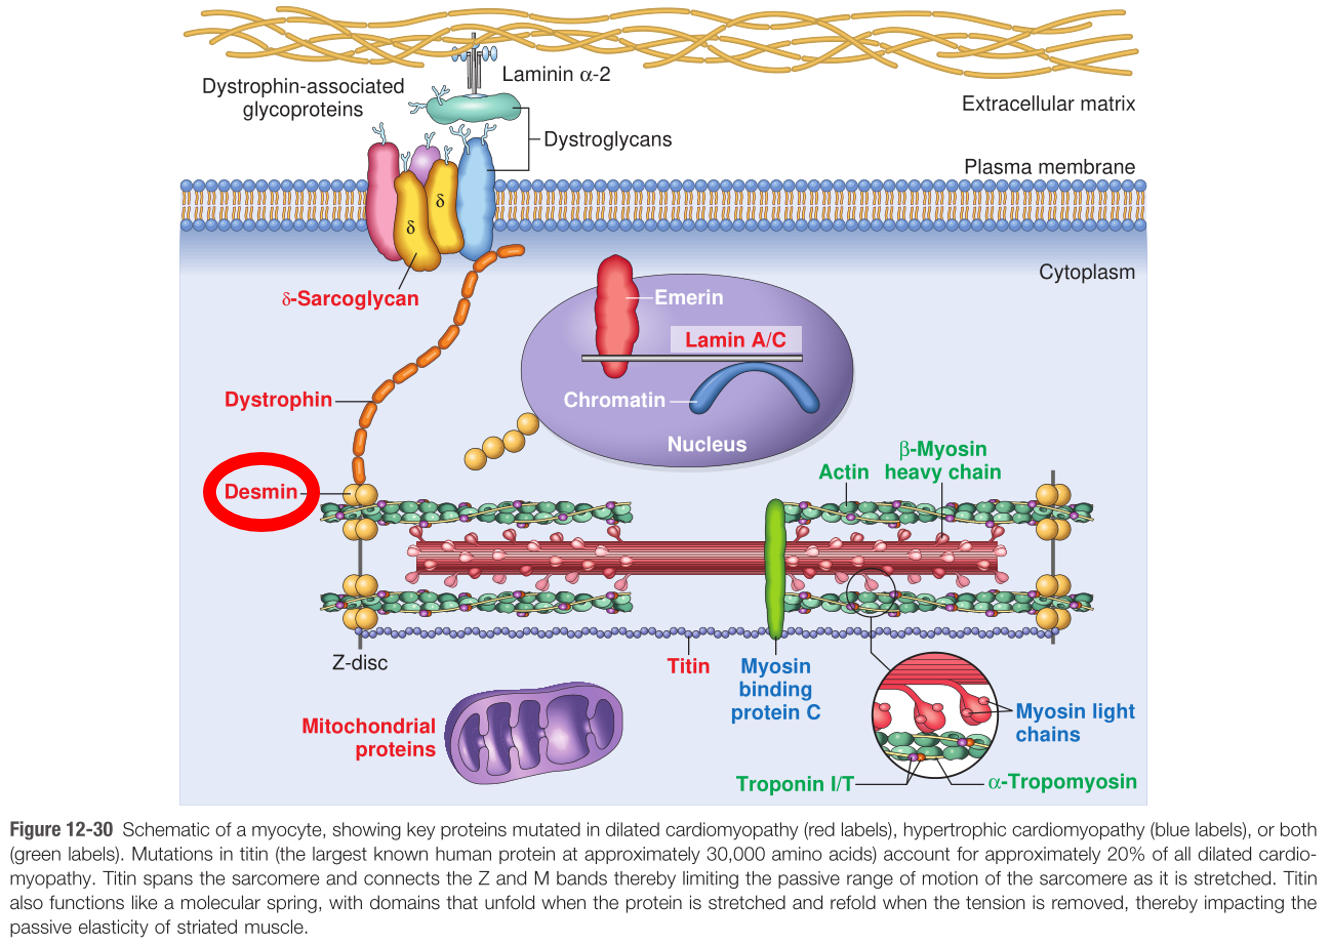
273
What tissue type is GFAP positive?
Neuroglia
CNS glial cells:
- oligodendrocytes
- astrocytes
- ependymal cells
- microglia
PNS glial cells:
- Schwann cells
- satellite cells
CNS glial cells:
- oligodendrocytes
- astrocytes
- ependymal cells
- microglia
PNS glial cells:
- Schwann cells
- satellite cells
274
What tissue type is neurofilament positive?
Neural tissue
275
What cell type is thyroglobulin positive?
Thyroid follicular cells
276
What cell type is chromogranin positive?
Neuroendocrine cells (e.g. small cell lung carcinoma, carcinoid tumors)
277
What cancers/tumors are S-100 positive? (3)
MelanomaSchwannoma
Langerhans cell histiocytosis
Langerhans cell histiocytosis
278
What causes DiGeorge Syndrome?
22q11 microdeletion which causes third and fourth pharyngeal pouches to never form. Thymus and parathyroid glands are absent as a result.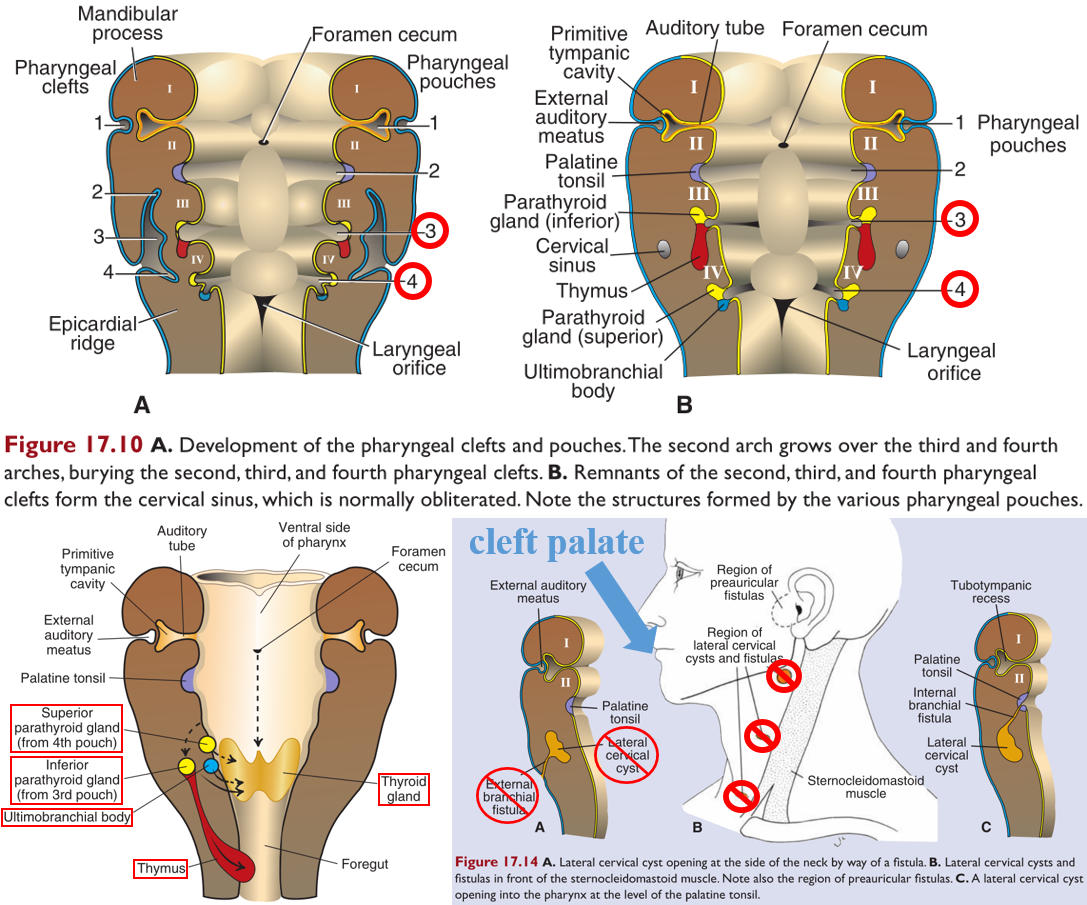
279
What are the 3 most common cardiac abnormalities seen in DiGeorge syndrome?
1) Interrupted aortic arch2) Truncus arteriosus
3) Tetrallogy of Fallot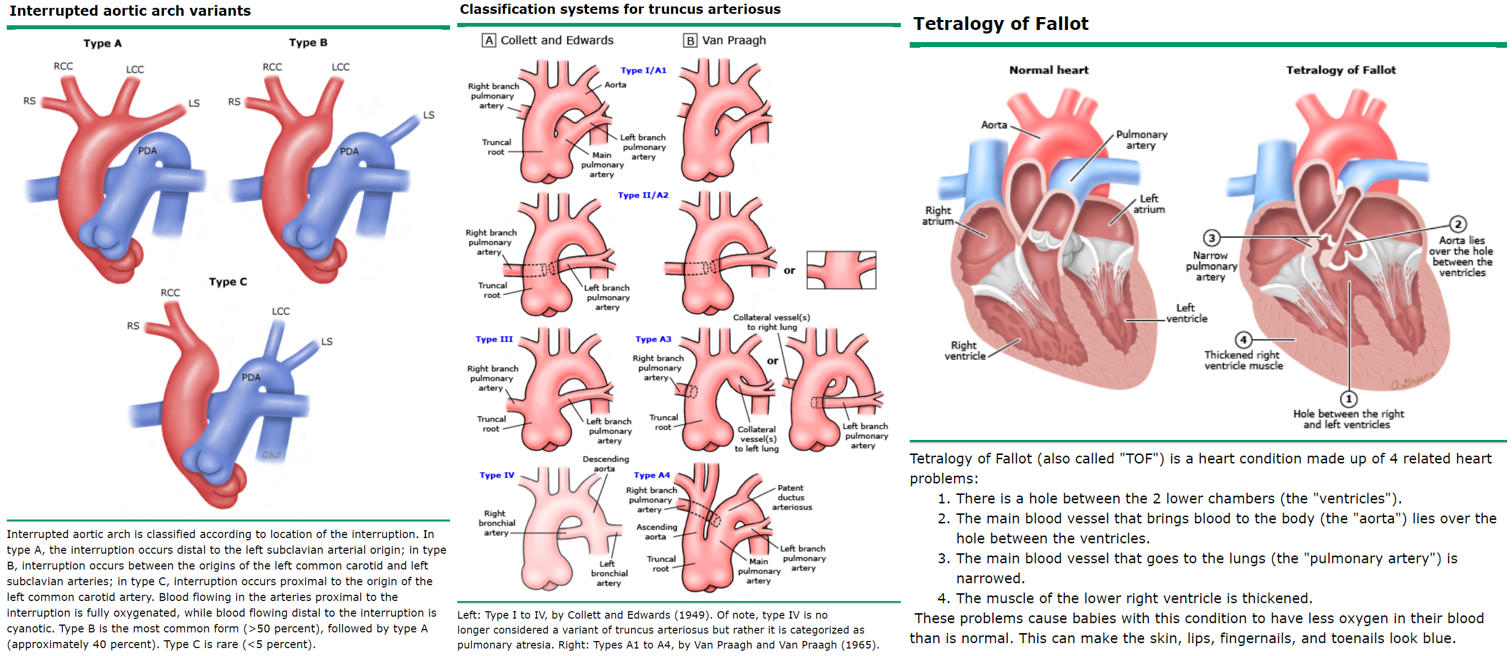
3) Tetrallogy of Fallot
280
What is the mnemonic for the symptoms of DiGeorge?
CATCH-22
Cardiac abnormalities
Abnormal facies
Thymic aplasia
Cleft palate
Hypocalcemia
chromosome 22q11 microdeletion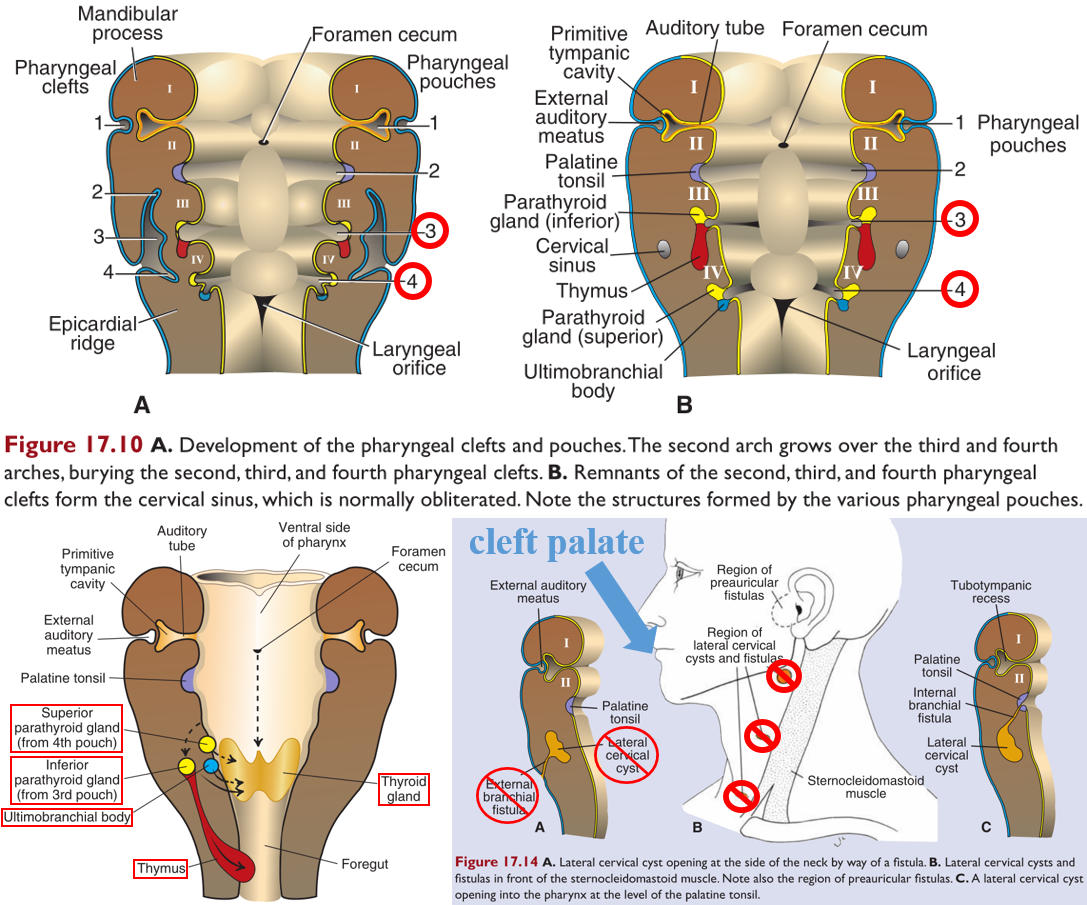
Cardiac abnormalities
Abnormal facies
Thymic aplasia
Cleft palate
Hypocalcemia
chromosome 22q11 microdeletion
281
What are three causes of severe combined immunodeficiency (SCID)?
1) Cytokine receptor defects (IL-2R defect most common) - no signal to T or B cells to mature and proliferate
2) Adenosine deaminase (ADA) deficiency - causes toxic buildup of metabolites in lymphocytes
(*remember 2-CDA tox in Hairy Cell Leukemia)
3) MHC Class II deficiency - inability to activate CD4+ helper T cells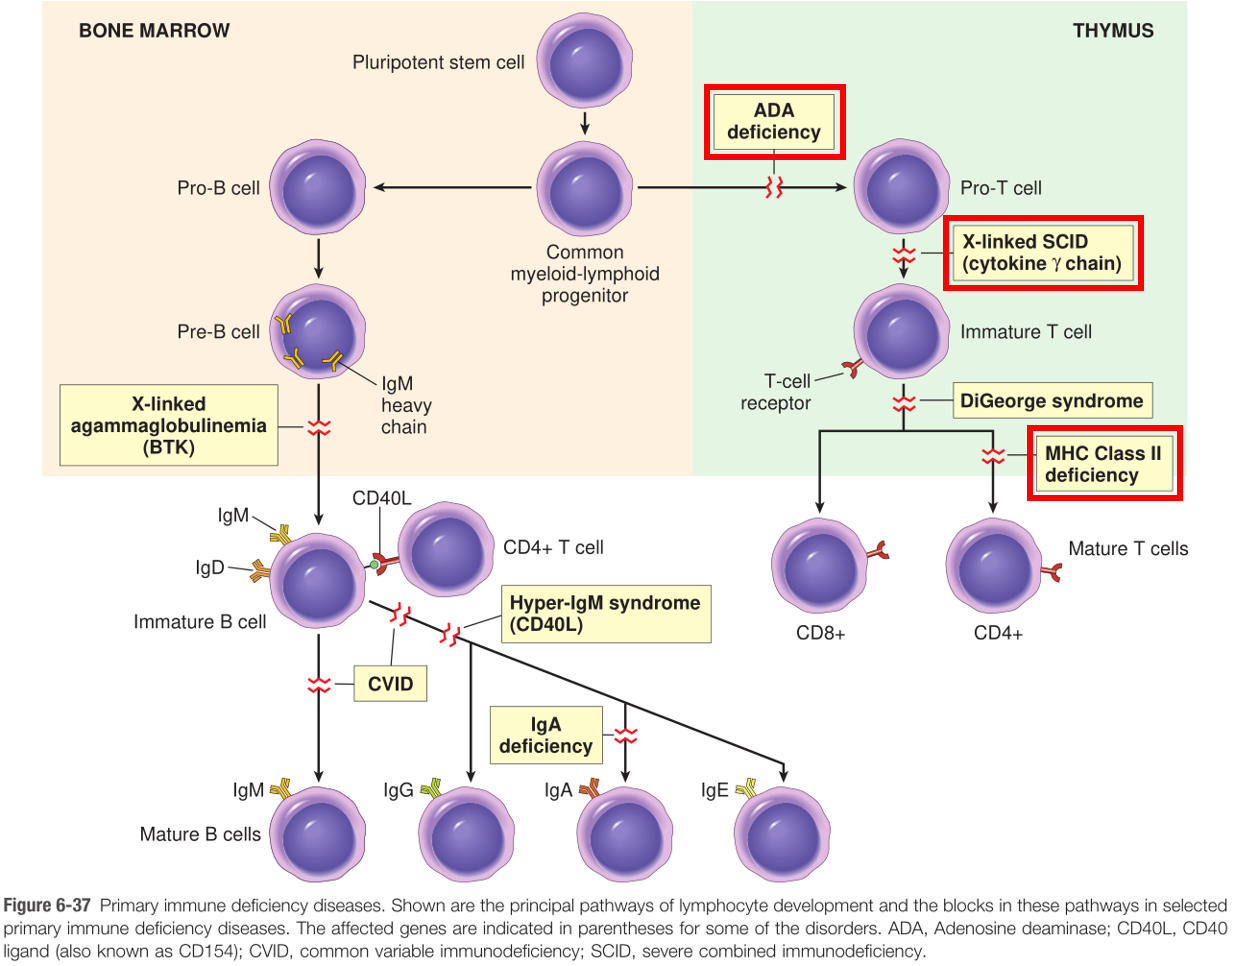
2) Adenosine deaminase (ADA) deficiency - causes toxic buildup of metabolites in lymphocytes
(*remember 2-CDA tox in Hairy Cell Leukemia)
3) MHC Class II deficiency - inability to activate CD4+ helper T cells
282
What kinds of infections are people with SCID susceptible to?
All of them
283
What class of therapeutics is contraindicated in patients with SCID? Name examples.
Live vaccines
"Live! One night only! See small yellow rotating chickens get vaccinated with Sabin's and MMR! Incredible!
Smallpox,
yellow fever,
rotavirus,
varicella,
sabin polio,
MMR,
intranasal flu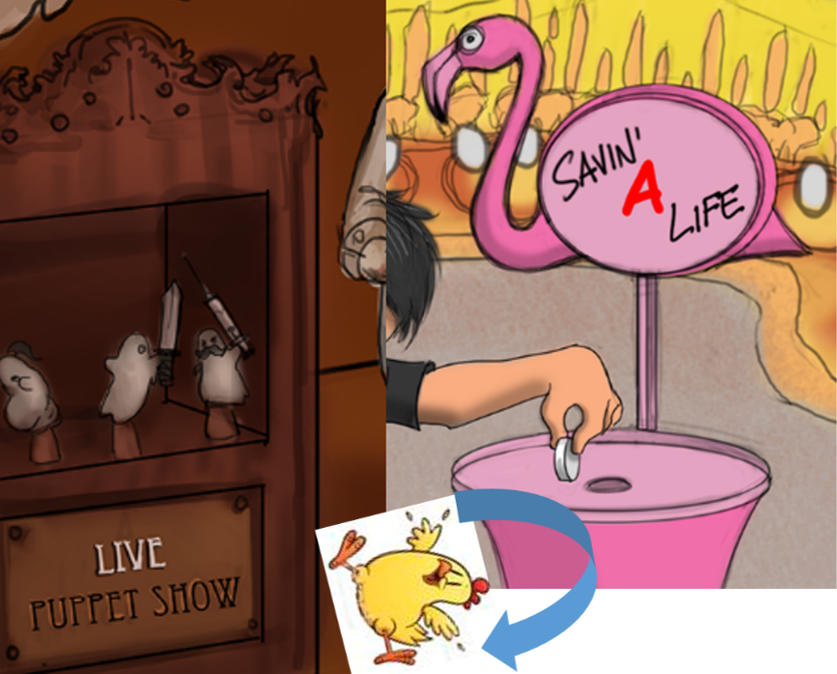
"Live! One night only! See small yellow rotating chickens get vaccinated with Sabin's and MMR! Incredible!
Smallpox,
yellow fever,
rotavirus,
varicella,
sabin polio,
MMR,
intranasal flu
284
What is the treatment for SCID?
1) Sterile Isolation (bubble)2) Stem cell transplantation
285
What causes X-linked agammaglobulinemia (XLA)?
Mutated Bruton Tyrosine Kinase (BTK) results in lack of immunoglobulin due to impaired B cell maturation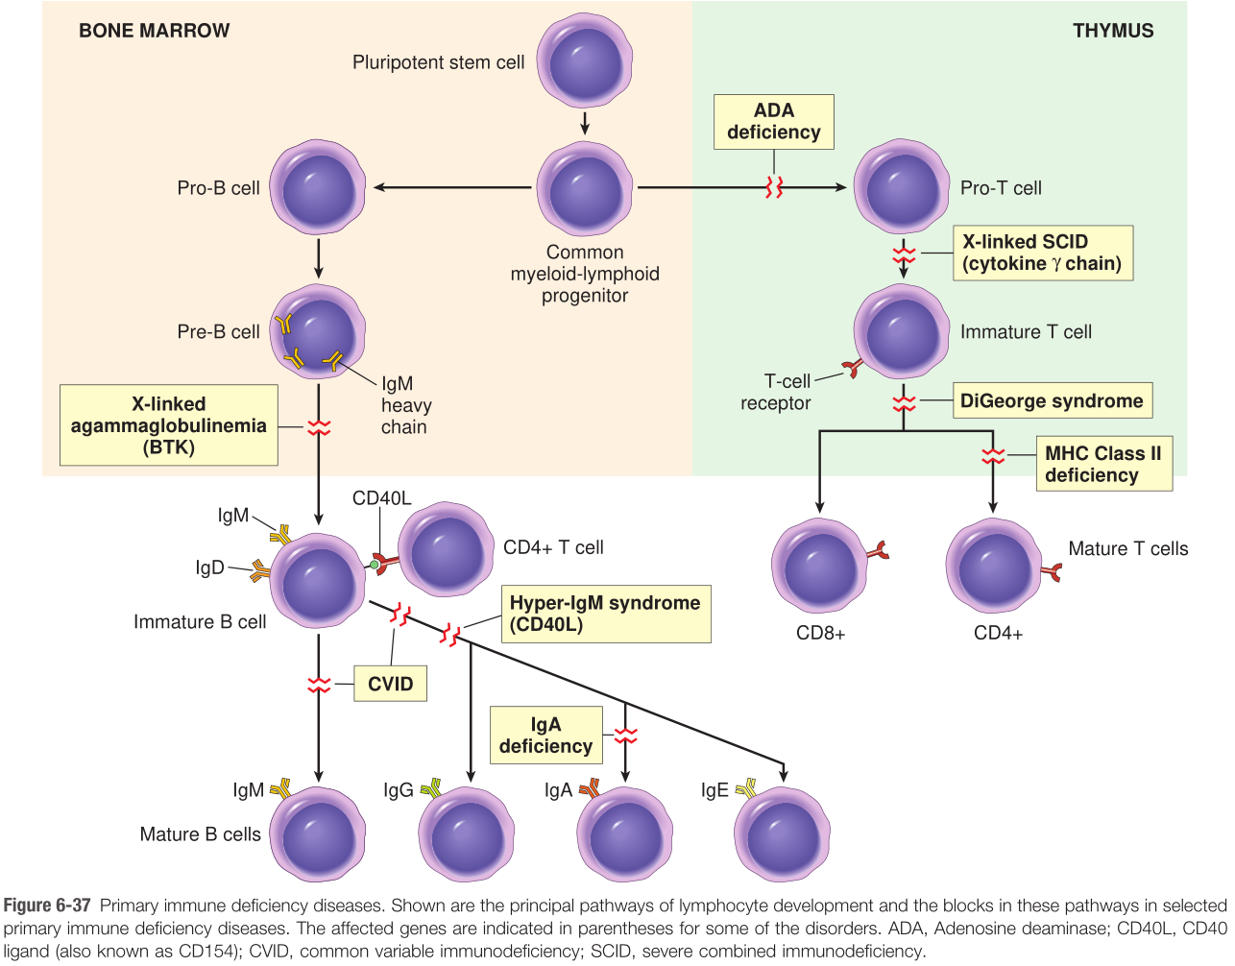
286
When does XLA first present? Why does it take this long?
6 months; maternal antibodies still protective at this time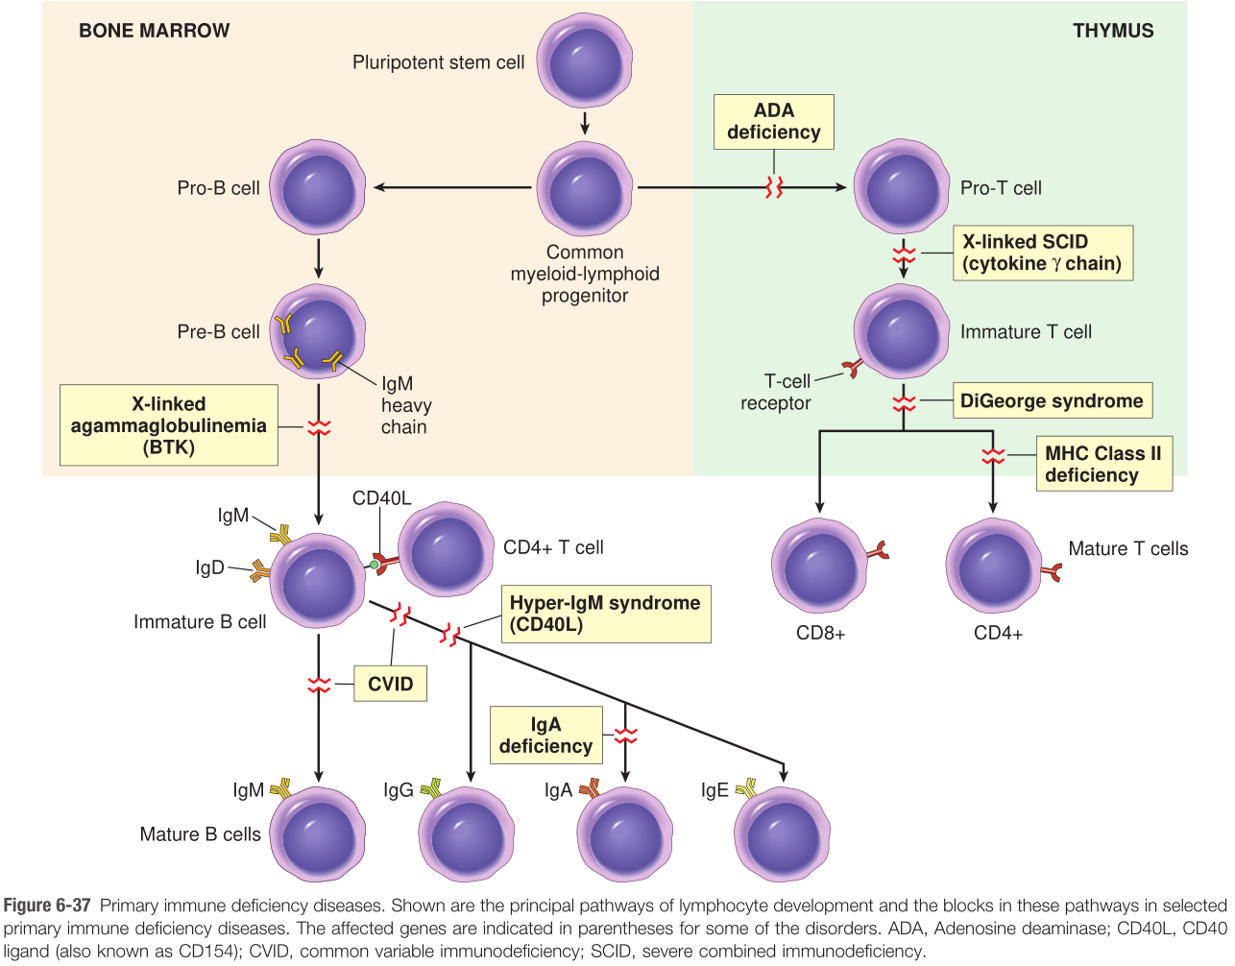
287
What infections are common in patients with XLA (3)?
1) Bacterial2) Enteroviruses (polio, coxsackie)
3) Giardia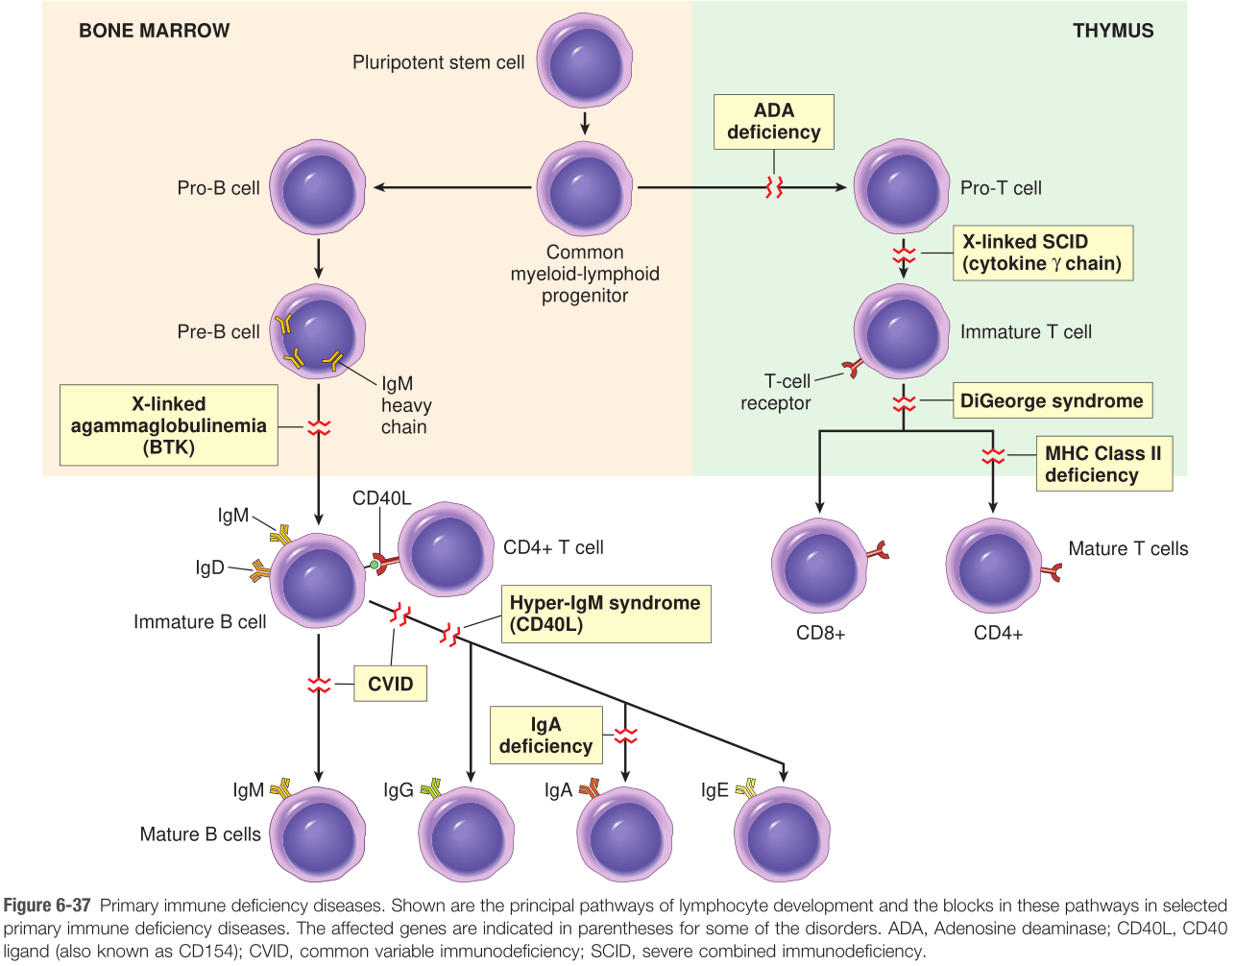
3) Giardia
288
What therapeutic must be avoided in patients with XLA?
Live vaccines
"Live! One night only! See small yellow rotating chickens get vaccinated with Sabin's and MMR! Incredible!
Smallpox,
yellow fever,
rotavirus,
varicella,
sabin polio,
MMR,
intranasal flu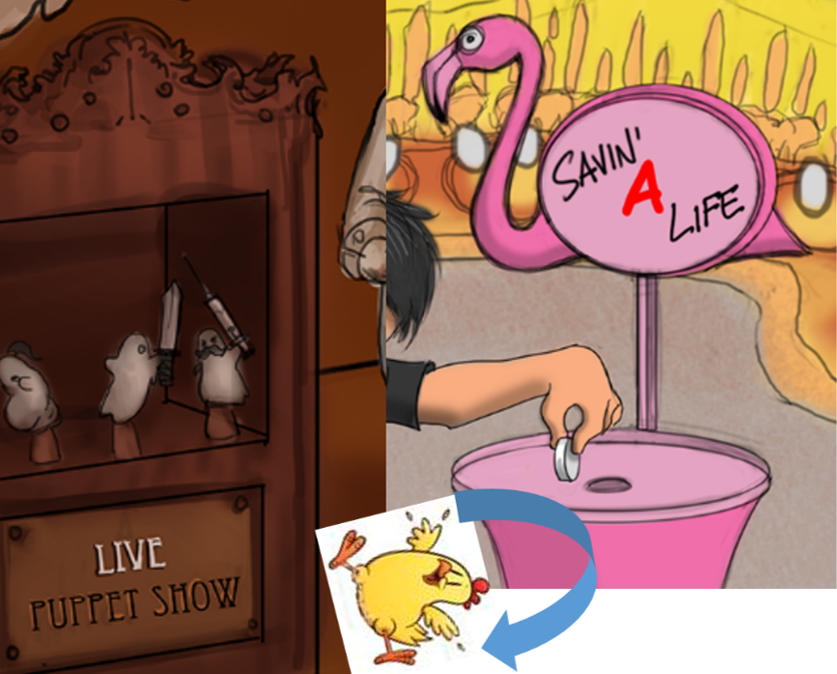
"Live! One night only! See small yellow rotating chickens get vaccinated with Sabin's and MMR! Incredible!
Smallpox,
yellow fever,
rotavirus,
varicella,
sabin polio,
MMR,
intranasal flu
289
What causes common variable immunodeficiency (CVID)?
Low immunoglobulin due to a variety of B cell or helper T cell defects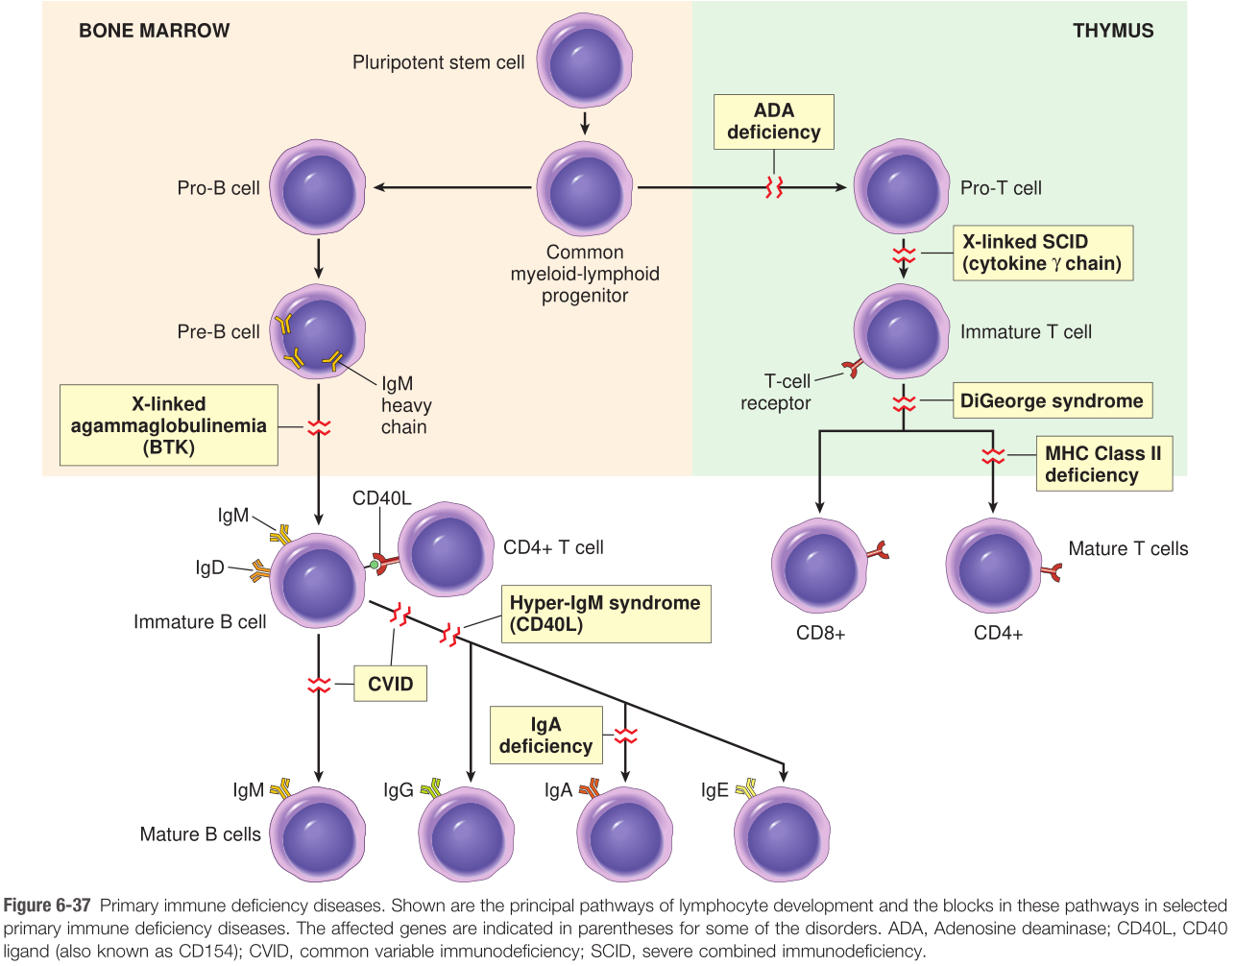
290
CVID increases risk for the development of what two noninfectious conditions?
1) Autoimmune disease2) Lymphoma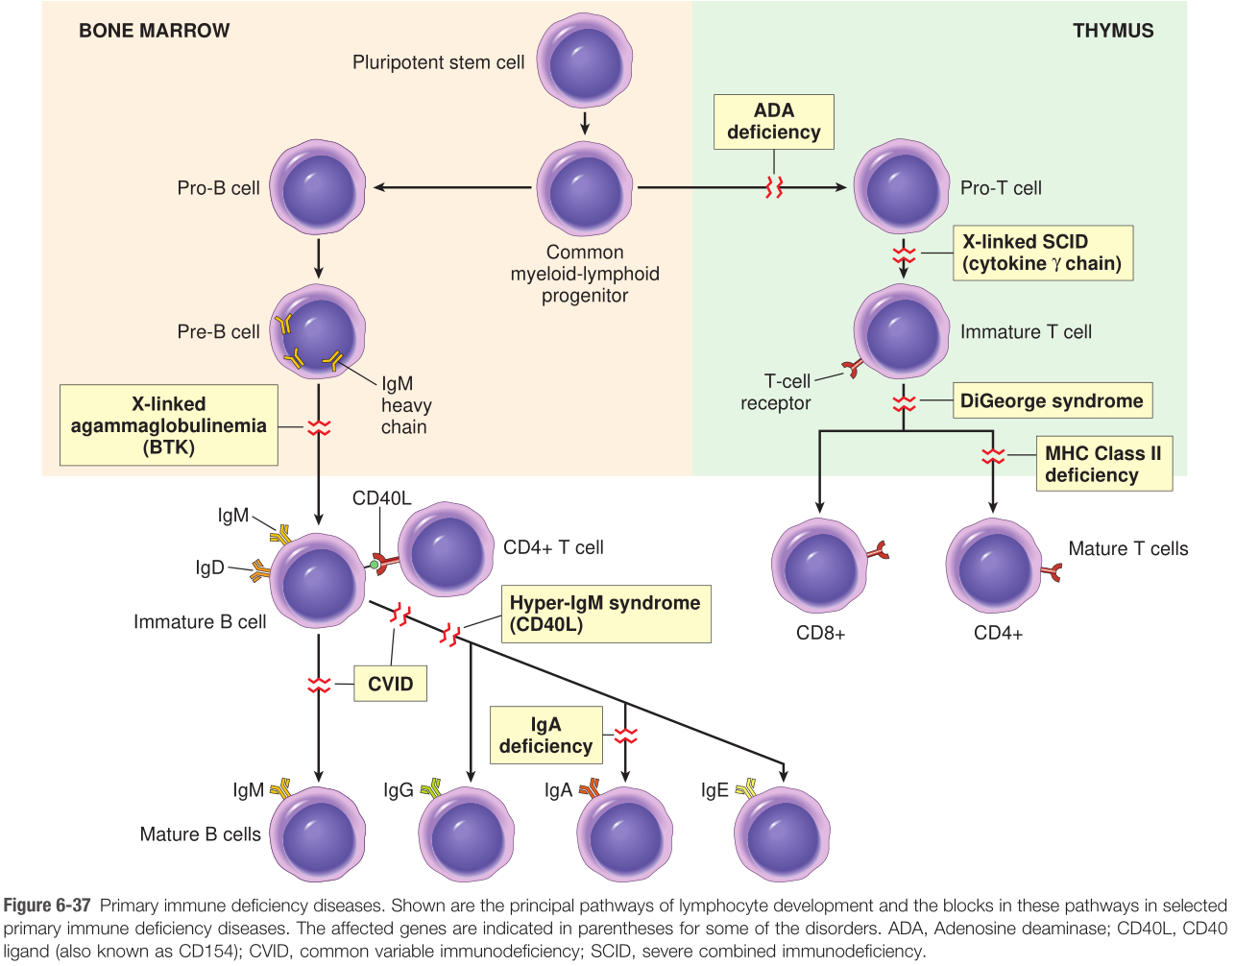
291
IgA deficiency presents with an increased risk for developing what kinds of infection? What autoimmune disease is it associated with?
1) Mucosal infection - particularly viral.
2) Associated with Celiac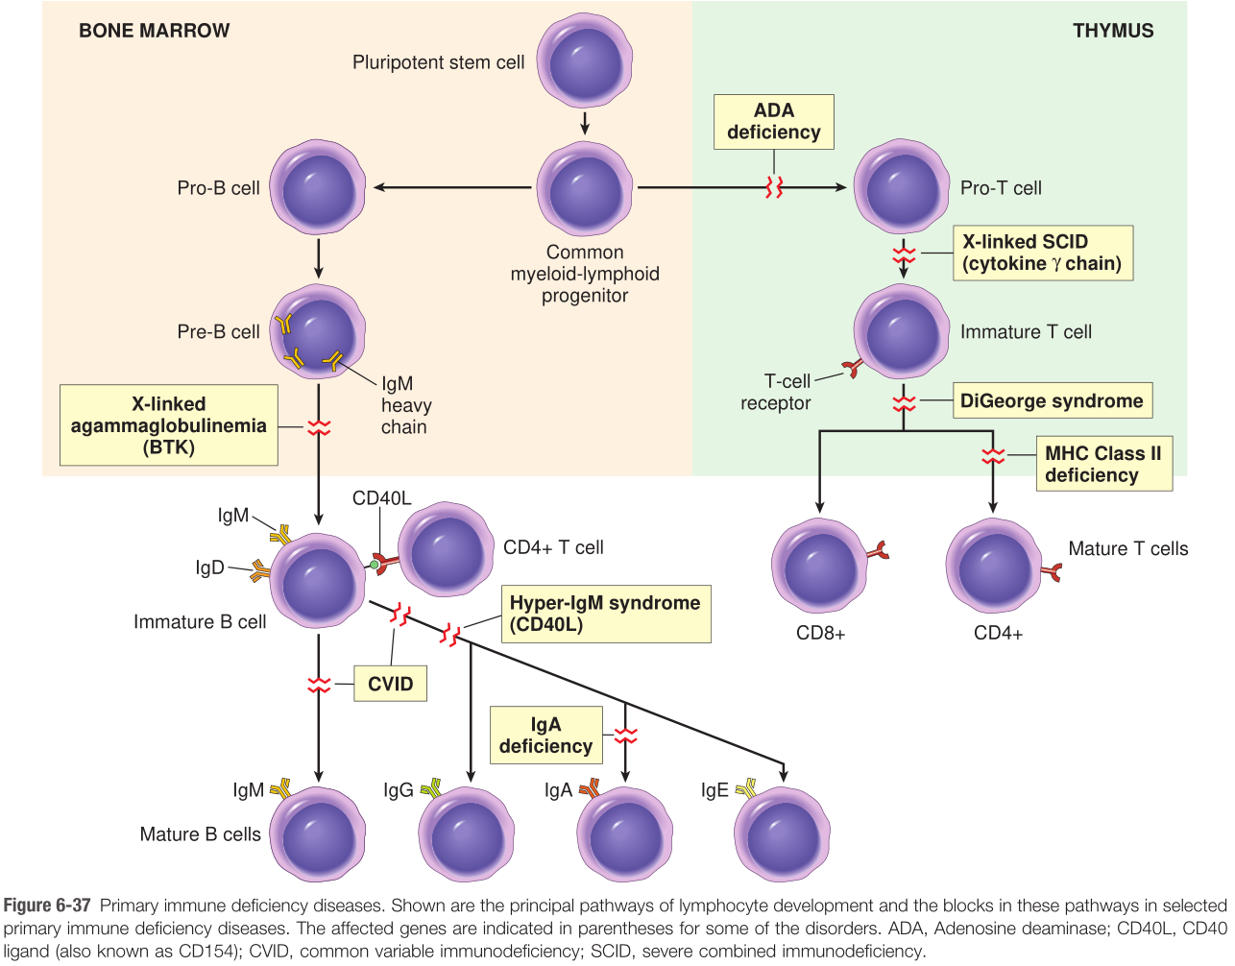
2) Associated with Celiac
292
Hyper IgM syndrome is caused by what?
A mutation in either CD40 on B cells or CD40L on helper T cells.
B cells are unable to get co-stimulation, and subsequently unable to class-switch
vs. Waldenström Macroglobulinemia (B-cell lymphoma)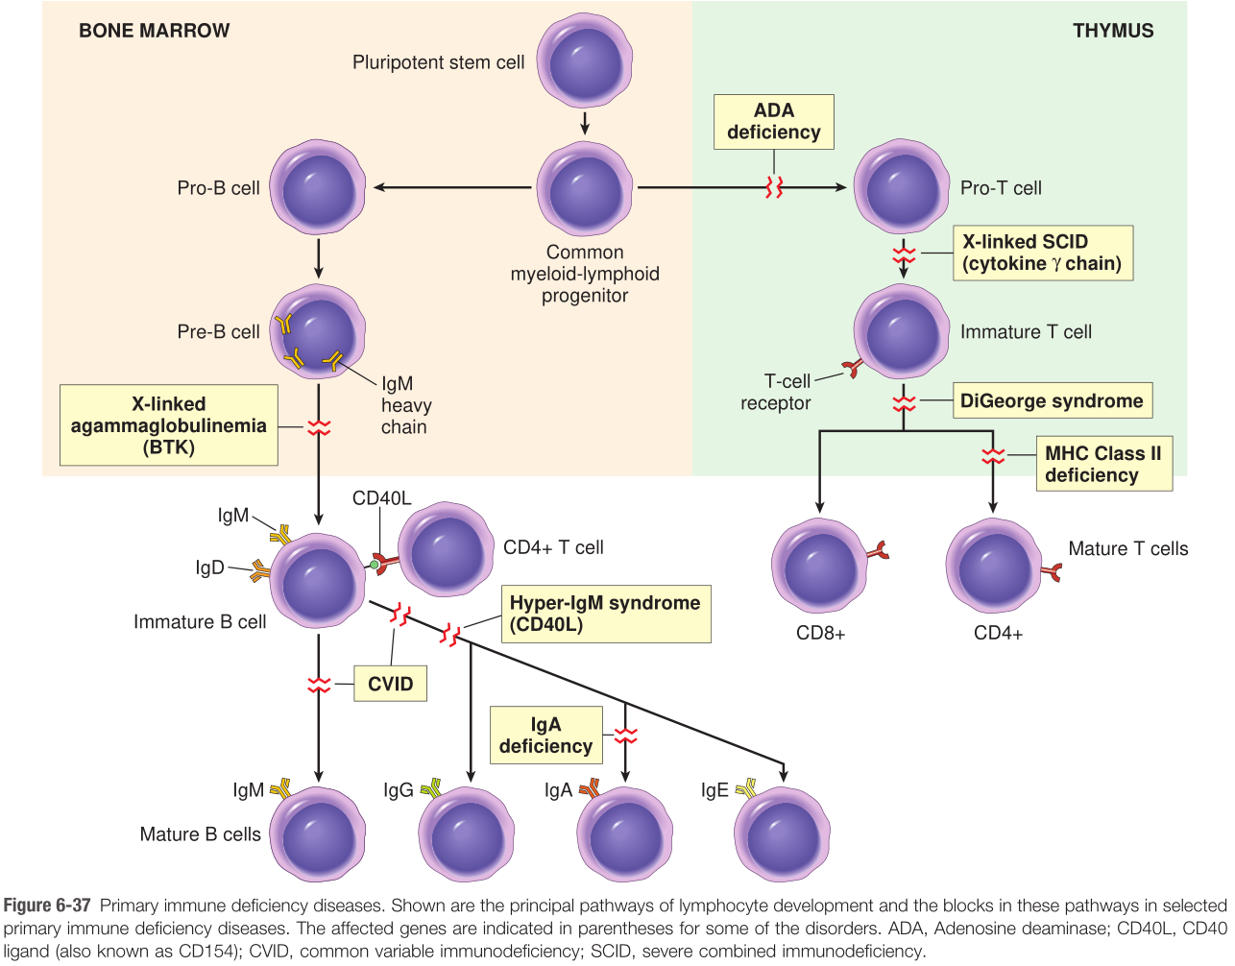
B cells are unable to get co-stimulation, and subsequently unable to class-switch
vs. Waldenström Macroglobulinemia (B-cell lymphoma)
293
What kinds of infection are typical of hyper IgM syndrome?
Pyogenic infections (poor opsonization)at mucosal sites (low IgA, IgG, IgE)
294
Wiskott-Aldrich syndrome is characterized by a triad of what 3 clinical findings
1) thrombocytopenia (defective platelets)2) eczema (defective lymphocytes)
3) recurrent infections (defective lymphocytes)
Pathophysiology:
X-linked recessive,
mutant WASP (normally links membrane receptors to cytoskeleton),
petechiae due to ↓Plt
Tx: HSC transplant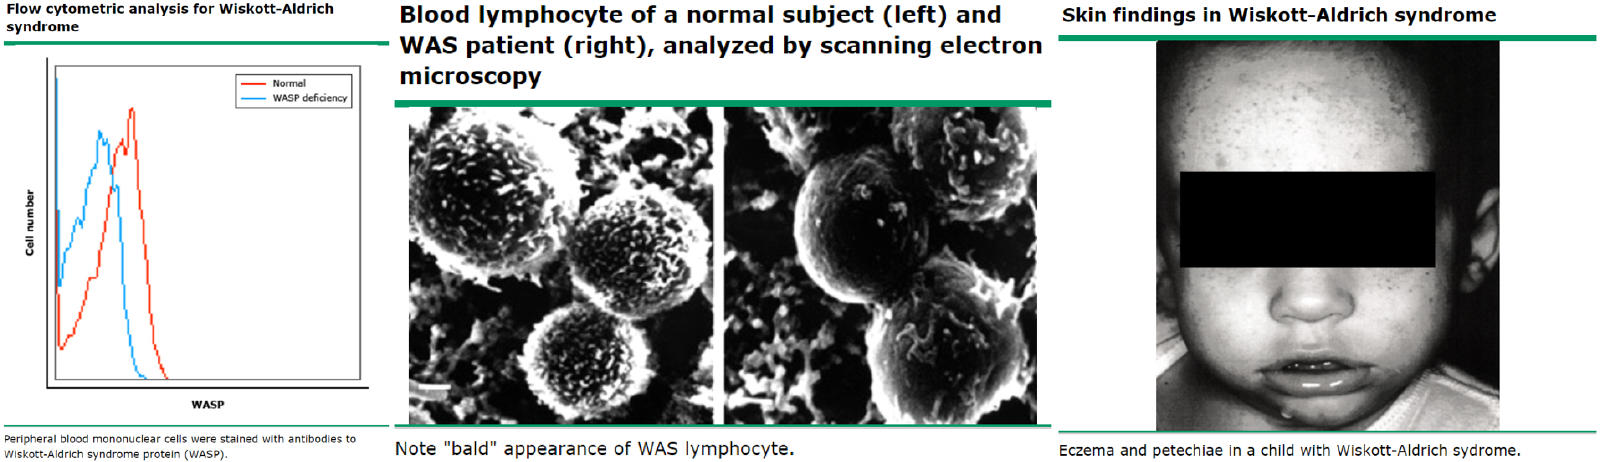
3) recurrent infections (defective lymphocytes)
Pathophysiology:
X-linked recessive,
mutant WASP (normally links membrane receptors to cytoskeleton),
petechiae due to ↓Plt
Tx: HSC transplant
295
C5-C9 deficiency renders a patient susceptible to what kinds of infection?
Neisseria spp - meningitis and gonorrheae
296
C1 inhibitor (or "esterase") deficiency results in what clinical condition?
Hereditary angioedema, which is characterized by edema of the skin and mucosal surfaces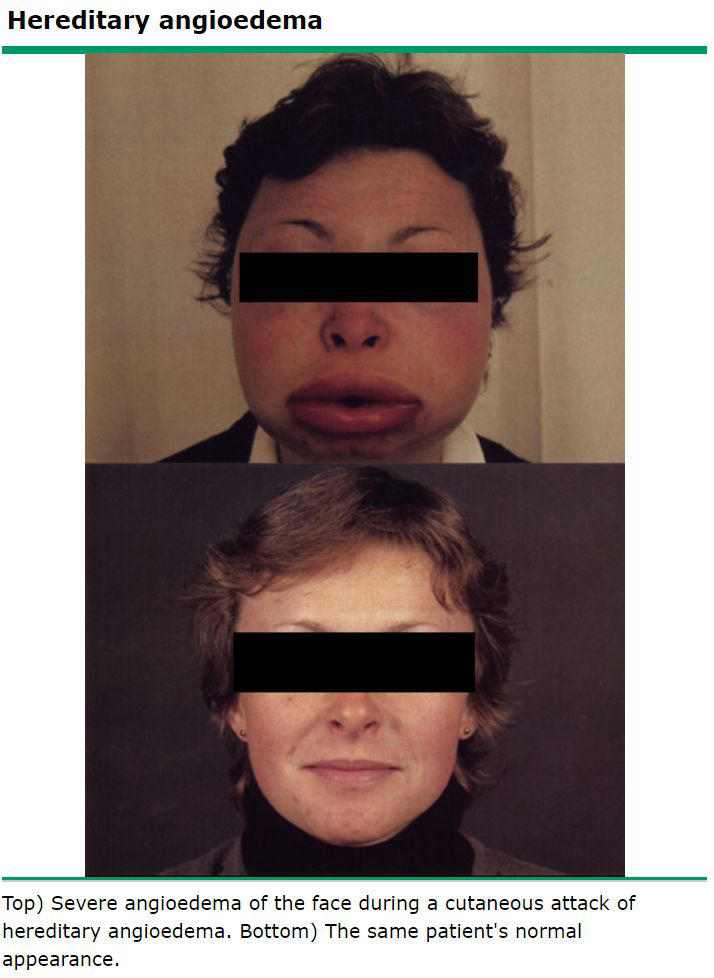
297
What antibody is associated with mixed connective tissue disease?
Anti-U1 ribonucleoprotein
298
Under what circumstance(s) does a scar form?
1) When wound disrupts regenerative stem cells (e.g. cut through stratum basale)
2) In tissues without regerative capacity (brain, heart)
2) In tissues without regerative capacity (brain, heart)
299
What role does collagenase play in scar formation?
Replaces type III collagen with denser, sturdier type I collagen.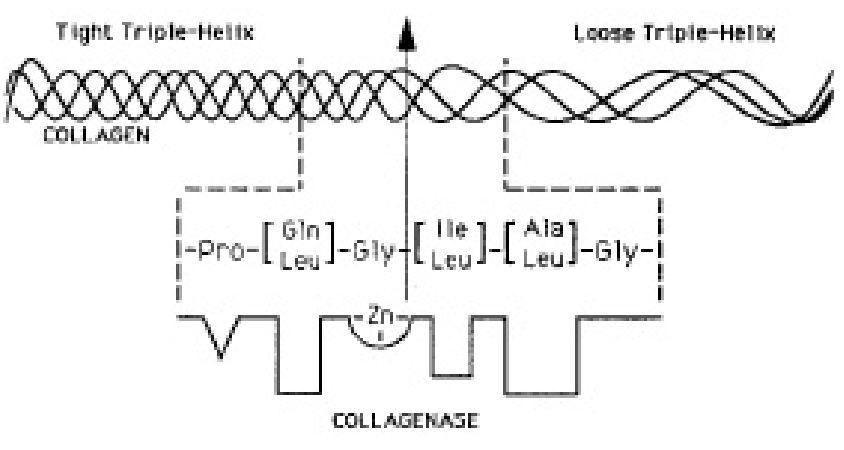
300
List the 5 important mediators of tissue regeneration and the roles they play:
1) TGF-α: epithelial and fibroblast growth factor2) TGF-β: fibroblast growth factor, inhibits inflammation
3) PDGF: growth factor for endothelium, smooth muscle, and fibroblasts
4) FGF: important for angiogenesis and skeletal muscle development (ironically not fibroblasts)
5) VEGF: important for angiogenesis
3) PDGF: growth factor for endothelium, smooth muscle, and fibroblasts
4) FGF: important for angiogenesis and skeletal muscle development (ironically not fibroblasts)
5) VEGF: important for angiogenesis
71 cartes de plus dans OutLearn. Ouvrir le deck complet
Plus de flashcards : Médecine et santé
Back muscle IdentificationMédecine et santé · AnglaisEshaAVCMédecine et santé · FrançaisClaraPhysiology of The NeuronMédecine et santé · AnglaisSarahSystème lymphatiqueMédecine et santé · FrançaisMevludeWeek 8: Prescription Drugs C/N/BMédecine et santé · LatinVictorPNP Management: Hepatitis, TB, and AllergiesMédecine et santé · AnglaisAddieLecture 4 - Autoimmunity Pt2Médecine et santé · Anglaisun étudiant OutLearnHistology: Connective TissueMédecine et santé · AnglaisKrisMedCardsPain: Pathways and ProstaglandinsMédecine et santé · AnglaisRyanBone Histology (Lab 4)Médecine et santé · AnglaisKrisMedCards2- région cervicale antérieureMédecine et santé · FrançaisOcéanedigestionMédecine et santé · AnglaisK
Tous les decks : Médecine et santé
Révise ces decks dans l’app
Gratuit sur iPhone, Android, Mac et le web. Ajoute n’importe quel deck à ton compte en un tap.

