Lecture 7 - hemoglobinopathies (final)
Study these flashcardsFree · spaced repetition · iPhone, Android, Mac & web
All cards
1
What is the definition of hemoglobinopathies?
abnormality in Hb structure and function due to mutation in 1+ globin genes
2
What are the factors affecting Hb function?
1. type of amino acid substituted
2. location in globin chain
3. number of genes mutated
2. location in globin chain
3. number of genes mutated
3
What is the impact of zygosity?
pt is homozygous (disease), clinical picture more severe than heterozygous (trait)
4
What are the homozygous variants of hemoglobinopathies?
HB S
Hb C
Hb D-Punjab
Hb E
Hb C
Hb D-Punjab
Hb E
5
What are the chains in Hb S? What does it lead to?
a2b2
severe hemolytic anemia, sickling
severe hemolytic anemia, sickling
6
What are the chains in Hb C? What does it lead to?
A2b2
mild hemolytic anemia
mild hemolytic anemia
7
What are the chains of Hb D-Punjab? What does it lead to?
A2b2
no anemia
no anemia
8
What is replaced in Hb D-Punjab?
121 Gln (glutamine)
9
What is replaced in Hb E?
26 Lys
10
What are the chains in Hb E? What does it lead to?
A2b2
mild Microcytic anemia
mild Microcytic anemia
11
What are the heterozygous Hb variants?
Hb M-Saskatoon
Hb Bethesda
Hb Kansas
Hb Bethesda
Hb Kansas
12
What is Hb M-Saskatoon associated with?
Methemoglobinemia and cyanosis
13
What are the chains for Hb M-Saskatoon?
A2b2 ^ (63Tyr)
14
What is Hb Bethesda associated with?
Increased oxygen affinity
15
What are the chains in Hb Bethesda?
A2b2^(145His)
16
What is Hb Kansas associated with?
Decreased oxygen affinity
17
What are the chains in Hb Kansas?
A2b2 ^ (102Thr)
18
What are the two kinds of unstable hemoglobins?
1. Hb precipitates as Heinz bodies
2. Tetramer of normal chains
2. Tetramer of normal chains
19
What Hb does Hb precipitate as Heinz bodies?
Hb hammersmith
Hb Zurich
Hb Ann Arbor
Hb Zurich
Hb Ann Arbor
20
What Hb has tetramer of normal chain?
(Only in alpha thalassemia)
Hb H (beta4)
Hb Bart (gamma4)
Hb H (beta4)
Hb Bart (gamma4)
21
What is the structural formula of Hemoglobin S?
a2b2^(6Glu->Val)glutamine->valine
22
What are the alleles for trait and disease of Hb S?
Trait: AS
Disease: SS
Disease: SS
23
What is the frequency in population of Hb S?
Globally the sickle gene occurs highest in:
sub-Saharan Africa
Arab-India
Americas
Eurasia
Southeast Asia
sub-Saharan Africa
Arab-India
Americas
Eurasia
Southeast Asia
24
What is the malaria species involved with Hb S?
Plasmodium falciparum. Sickle Cell Trait (SCT) gives protection against this parasite.
25
What is the mechanism of AS protection against P falciparum?
Selective destruction of RBCs containing parasites decreases number of malarial organisms and increases the time for immunity to develop
26
What influences the 2 forms of RBCs in Hb S?
oxygenated and deoxygenated
27
What is the process of sickling in Hb S disease (SS)?
when oxygen saturation decreases to <85%
28
What is the process of sickling in Hb S trait?
sickling does not occur unless oxygen saturation is <40%
29
What are the two kinds of sickling in Hb S?
reversible
irreversible
irreversible
30
When does reversible sickling occur in Hb S?
Hb S containing RBCs that change shape in response to oxygen tension
responsible for vasocclusive crisis
responsible for vasocclusive crisis
31
What is irreversible sickling?
sickle cells do not change their shape regardless of the change in O2 tension or degree of Hb polymerization
Seen on PBS as actual sickle cells
Seen on PBS as actual sickle cells
32
What age does Hb S occur?
6 months after birth
33
What are the types of crises in Hb S?
1. vasocclusive 'painful' sequestration
2. chronic hemolytic, megaloblastic
3. aplastic
2. chronic hemolytic, megaloblastic
3. aplastic
34
What happens in vasocclusive/ painful splenic sequestration crises in Hb S?
dropping of Hb to <6g/ dl (mostly in infants and young adults) could lead to autosplenectomy
35
What causes hemolytic megaloblastic crises in Hb S?
due to folate depletion
36
What is associated with aplastic crises in Hb S?
common life-threatening hematologic complications usually associated with parvo B19 infection
37
What are the risk factors for initiation of vasoocclusion in Hb S?
polymerization
decreased deformability
sickle cell endothelial cell adherence
WBC/ platelet activation
decreased deformability
sickle cell endothelial cell adherence
WBC/ platelet activation
38
What can trigger initiation of vasoocclusion in Hb S?
acidosis, hypoxia, dehydration, infection/ fever,
extreme exposure to cold
extreme exposure to cold
39
What is the lab dx of Hb S dependent on?
type of HA
blood smear eval
retic count!!
MCV and RDW
cell counts
BM studies
blood smear eval
retic count!!
MCV and RDW
cell counts
BM studies
40
What would CBC and PBF of Hb S present as?
increase nRBC/ polychromatic
MCH and MCV normal
sometimes RDW increase
leukocytosis (neutrophilia) & thrombocytosis
MCH and MCV normal
sometimes RDW increase
leukocytosis (neutrophilia) & thrombocytosis
41
Why is retic high in Hb S?
(305%) bc BM is responding properly
42
What happens if Hb S is present but have low retic count?
could signal aplastic crisis
43
What are the 2 ways to test for Hb S?
tube solubility test
Hb electrophoresis
Hb electrophoresis
44
What is the principle of tube solubility test?
deoxygenated Hb S less soluble in solution, generating turbidity
(reducing agent sodium dithionite)
(reducing agent sodium dithionite)
45
How do you get false negatives of Hb S from tube solubility test?
infants younger than 6 mo &
in low HCT
in low HCT
46
When do you get false positives of Hb S from tube solubility test?
hyperlipidemia
too much blood added to the tube
too much blood added to the tube
47
What is the principle of Hb electrophoresis?
separation of Hb molecules in an electric field primarily as a result of differences in total molecular charge
48
What are the 2 approaches of electrophoresis?
alkaline (pH 8.4)
acid (pH 6.2)
acid (pH 6.2)
49
What happens in alkaline conditions of electrophoresis?
Hb molecules assume a negative charge and migrate toward the anode
(on cellulose acetate or recently agarose)
(on cellulose acetate or recently agarose)
50
What happens in acidic conditions of electrophoresis?
some Hb assume a negative charge and migrate toward the anode, whereas others are positively charged and migrate toward the cathode
51
Label the electrophoresis pattern at each band (cellulose acetate pH 8.4)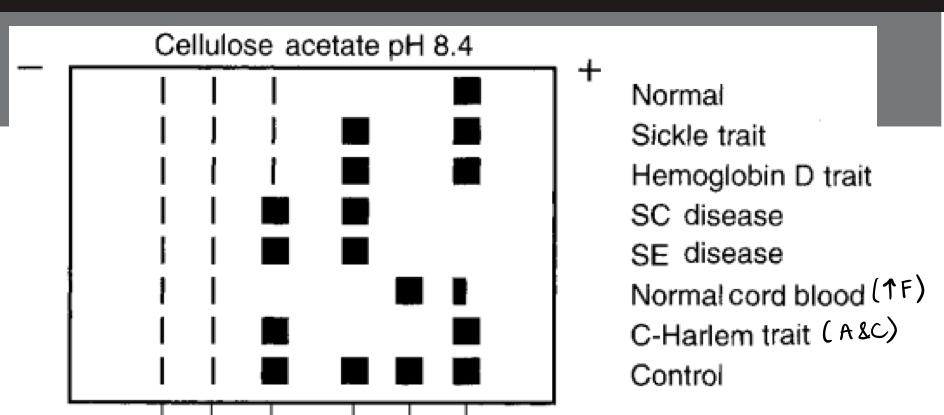
A. A
B. F
C. S, D, G
D. A2, C, E, o
B. F
C. S, D, G
D. A2, C, E, o
52
Label the electrophoresis pattern at each band (citrate agar pH 6-6.2)
A. F
B. A, D, G, E, O
C. S
D. C
B. A, D, G, E, O
C. S
D. C
53
What does Hb S migrate with on alkaline electrophoresis?
Hb S migrates with Hb D and Hb G
54
How do you separate Hb S from the other Hb on electrophoresis?
using citrate agar (acidic)
Hb D and G separate
Hb D and G separate
55
How can Hb D and Hb G be further differentiated from Hb S?
they produce a negative result on Hb solubility test
56
What does Hb C migrate with on alkaline electrophoresis?
Hb C migrate with Hb A2, Hb E, and Hb O
57
How do you separate Hb C from the other Hb on electrophoresis?
separates from A2, E, and O on acid electrophoresis
58
What do each of these bands indicate?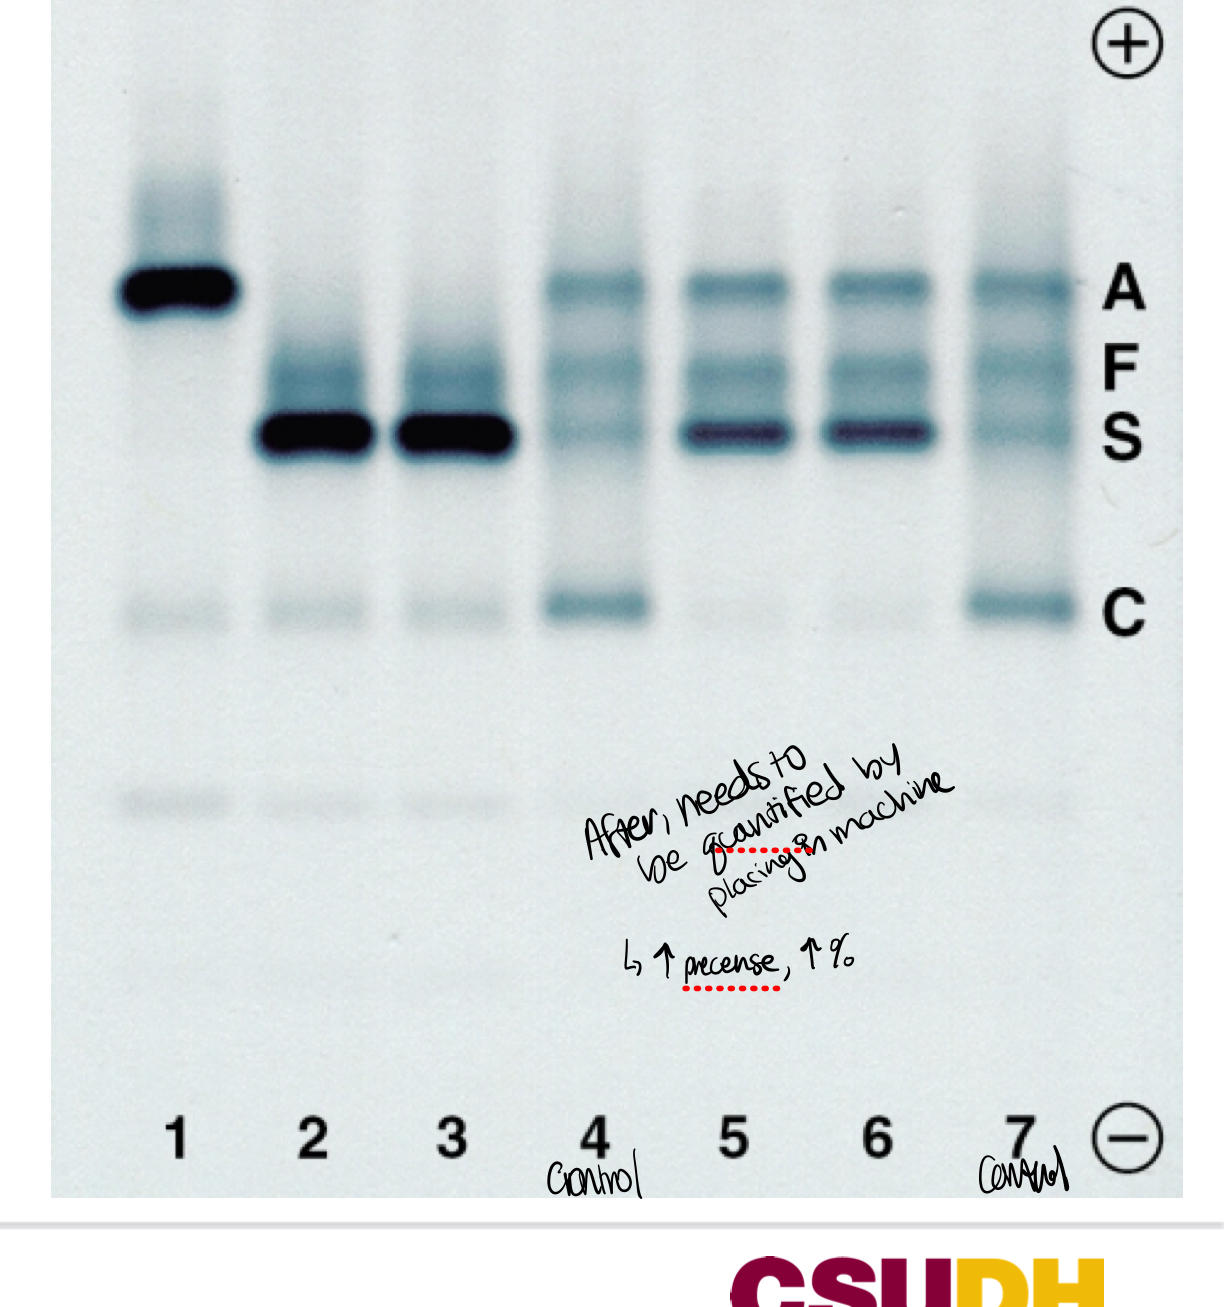
1. normal adult
2&3. SS
5&6. Sickle cell anemia recently transfused
2&3. SS
5&6. Sickle cell anemia recently transfused
59
How do you know if pt has sickle cell anemia but was recently transfused?
presence of Hb A from the transfused RBCs in addition to Hb S on electrophoresis
60
What does Sickle cell trait (SCT) refer to?
heterozygous (Hb AS)
describes benign condition that does not affect mortality/ morbidity except under extreme exertion
describes benign condition that does not affect mortality/ morbidity except under extreme exertion
61
What is the PBS for SCT?
normal RBC morphology (with a few target cells)
no abnormalities in leukocytes/ thrombocytes
no abnormalities in leukocytes/ thrombocytes
62
What are the hemoglobin solubility screening test for SCT?
positive
63
How is SCT diagnosed?
by detecting presence of Hb S and Hb A on hemoglobin electrophoresis or HPLC
64
What are the Hb levels for SCT on electrophoresis?
approx 40% Hb S and approx 60% more Hb A;
Hb A2 normal or slight increase
Hb F level within reference
Hb A2 normal or slight increase
Hb F level within reference
65
What is the most common non-sickling variant in the US and 3rd most common in the world?
Hb C
66
How is Hb C defined?
by the structural formula a2B2^(6Glu→lys)
in which lysine replaces glutamic acid in position 6 of B chain
in which lysine replaces glutamic acid in position 6 of B chain
67
How is Hb C diff from Hb S?
Hb C polymer structure differ under high oxygen tension;
Hb S polymers long/ thin, Hb C are short, thick crystals within RBCs
Hb S polymers long/ thin, Hb C are short, thick crystals within RBCs
68
How does homozygous Hb C present? (CC)
manifests as milder disease compared to SCD,
mild splenomegaly and hemolysis may be present
Vasoocclusion does not occur
mild splenomegaly and hemolysis may be present
Vasoocclusion does not occur
69
How does heterozygous Hb C present (AC)?
asymptomatic
70
What is the type of anemia present in Hb C?
mild-moderate
normocytic normochromic in Hb CC
normocytic normochromic in Hb CC
71
What is the presentation of Hb C on blood smear?
occasional micro/ hypo
marked increase in target cells
nRBCs
marked increase in target cells
nRBCs
72
What is the retic count of Hb C?
slightly to moderately high (2-3%)
73
Describe Hb CC electrophoresis.
NO Hb A present in CC
Hb C >90%
Hb F <7%
Hb A2 ~2%
Hb C >90%
Hb F <7%
Hb A2 ~2%
74
Describe Hb AC electrophoresis.
60% Hb A
30% Hb C
30% Hb C
75
Describe Hb C alkaline electrophoresis.
Hb C migrates at the same position as Hb A2, E, & O-Arab
76
What kind of crystals are seen in Hb C?
'bars of gold'
77
Where is Hb E normally found?
southeast Asia
highest incidence in Thailand
highest incidence in Thailand
78
What is the aa substitution in Hb E?
a2B2^(26Glu→Lys)
79
What is Hb E trait vs disease?
EE (disease): mild anemia with microcytes & target cells
AE (trait): asymptomatic
AE (trait): asymptomatic
80
What does Hb EE need to be differentiated from?
IDA, B-thal minor
81
How is Hb E associated with malaria?
because highest incidence in areas where malaria is present, it is though that P falciparum multiplies more slowly in Hb EE RBCs than Hb AE or Hb AA RBCs;
Mutation may give some protection against malaria
Mutation may give some protection against malaria
82
What are the results of Hb solubility test for Hb E?
negative
must be confirmed using electrophoresis or HPLC
must be confirmed using electrophoresis or HPLC
83
Describe Hb E (homozygous) disease lab dx.
>90% Hb E
mild anemia (Hb 11-13 g/ dl)
low MCV (55-65 fl)
few-many target cells
normal retic
mild anemia (Hb 11-13 g/ dl)
low MCV (55-65 fl)
few-many target cells
normal retic
84
Describe Hb E trait lab dx
approx 25-30% Hb E
normal Hgb levels
MCV of 65 fl
target cells
slight erythrocytosis
normal Hgb levels
MCV of 65 fl
target cells
slight erythrocytosis
85
What does Hb E migrate with on alkaline electrophoresis?
Hb C, O, A2
86
What is the electrophoresis pattern of Hb E on citrate (acid) electrophoresis?
Hb E separated from Hb C but it comigrates with Hb A & O
87
What is the most common compound heterozygous syndrome?
Hb SC
88
What is the cause and distribution of Hb SC?
aa substitutions
ethnic distribution: 25% W Africa
1 in 833 births/ year in US
ethnic distribution: 25% W Africa
1 in 833 births/ year in US
89
What are the clinical features of Hb SC?
milder than SS, may cause vasoocclusion
90
What are the lab features of Hb SC on CBC?
mild normocytic, normochromic anemia
with many features associated with sickle cell anemia
Hb ~11-13 g/ dl
retic is 3-5%
with many features associated with sickle cell anemia
Hb ~11-13 g/ dl
retic is 3-5%
91
What is the presentation of Hb SC blood smear?
few sickle cells
target cells
intraerythrocytic SC crystals
target cells
intraerythrocytic SC crystals
92
What is the Hb solubility test result of Hb SC?
positive
93
What are the Hb SC electrophoresis results?
Hb C and Hb S migrate in almost equal amts (45%) on alkaline electrophoresis
Hb F is normal
Hb F is normal
94
What kind of Hgb does thalassemia have?
normal Hgb structure but the production amount changes
95
What mutation results in B-thal?
mutations in B gene cluster on chromosome 11;
results in B chain production
results in B chain production
96
What is responsible for α-thal?
deletion of one or more α gene
affects a chain production
affects a chain production
97
What is the general pathophysiology of thalassemias?
globin shortages
globin excesses
globin excesses
98
What age can B-thal be detected?
6 months to 1 year
99
What age can α-thal be detected?
during fetal life
100
What is the genetic designation of B0?
no β chains are produced β0/ β0
does not produce Hb A (α2β2)
does not produce Hb A (α2β2)
101
What is the genetic designation of B+?
partial deficiency of β chains (ranging from 5-30%)
decrease in production of Hb A
decrease in production of Hb A
102
What is the genetic designation of B^silent?
minimal reductions in β chain production, mild or silent clinical states
(aka silent carrier)
(aka silent carrier)
103
What is the genetic designation of δβ0?
no δ or β chains are produced
in homozygous δβ0/ δβ0, no Hb A or Hb A2 (α2δ2) is produced
in homozygous δβ0/ δβ0, no Hb A or Hb A2 (α2δ2) is produced
104
What is the genetic designation of α+ trait?
deletion of either α1 or α2 globin gene on chr 16; results in decreased production of α chains from that chromosome
- α haplotype
- α haplotype
105
What is the genetic designation of α0 trait?
deletion of both α1 or α2 globin gene on chr 16; results in no production of α chains from that chromosome
- - haplotype
- - haplotype
106
What are the genes for β thal minor?
β+/ β
107
What are the genes for β thal major?
β0/ β0
108
What are the genes for B thal intermedia?
δβ0/ δβ0
109
What are the genes for β thal silent carrier?
βsilent/ β
110
What are the major characteristic for silent carrier thalassemia?
asymptomatic; normal hematologic parameters
111
What are the major characteristic for thalassemia minor?
asymptomatic;
mild anemia
microcytic hypochromic
mild anemia
microcytic hypochromic
112
What are the major characteristic for thalassemia major?
transfusion-dependent thalassemia,
severe anemia
microcytic hypochromic
severe anemia
microcytic hypochromic
113
What are the major characteristic for thalassemia intermedia?
non transfusion dependent
mild to mod anemia
microcytic hypochromic
mild to mod anemia
microcytic hypochromic
114
What happens in β thal minor?
one β gene mutated, the other one is normal
115
What are the Hb levels in beta thal minor?
11-15 g/ dl in men
10-13 g/ dl in women
slight asymptomatic anemia
10-13 g/ dl in women
slight asymptomatic anemia
116
What is the RBC morph of β thal minor?
slightly increased, micro/ hypo
MCV<75 MCH<26
poik (targets, ellipto)
basophilic stippling
MCV<75 MCH<26
poik (targets, ellipto)
basophilic stippling
117
What Hb types & % are present in the most common β thal minor syndromes (β0/ β & β+/ β)?
Hb A 92-95%
Hb A2 elevated (3.5% to 7.0%)
Hb F 1-5%
Hb A2 elevated (3.5% to 7.0%)
Hb F 1-5%
118
What is present in BM studies of β thal minor?
mild-mod erythroid hyperplasia with minimal ineffective erythropoiesis
119
Is β thal major hetero or homo?
homozygous
120
What is the age of diagnosis for β thal major?
6 mo to 2 yrs
121
What is the level of β chain production of β thal major?
no Hb A
Hb F 95%
Hb F 95%
122
What are the Hb levels of β thal major?
usually <7
but could be 2-4
but could be 2-4
123
How does Hb F help in β thal major?
high affinity for oxygen
124
What is the blood smear eval of thalassemia (major)?
poikilocytosis
elliptocytes, schistocytes, target cells, tear drop, spherocytes, hypochromic, microcytosis
basophilic stippling, nRBCs
(basically all morphology)
elliptocytes, schistocytes, target cells, tear drop, spherocytes, hypochromic, microcytosis
basophilic stippling, nRBCs
(basically all morphology)
125
What kind of physical changes can be seen in β thal major?
bone changes
126
What are the type of mutations in α thal?
normal αα/ αα
silent αα/ α-
α thal trait -α/-α or αα/--
Hb H -α/ --
Hb Barts/ hydrops fetalis --/ --
silent αα/ α-
α thal trait -α/-α or αα/--
Hb H -α/ --
Hb Barts/ hydrops fetalis --/ --
127
What is the genetic defect of Hb H?
3 α genes deleted (--/ -α)
β chain tetramers form (β4)
β chain tetramers form (β4)
128
What Hb is present in newborn with α thal (Hb H disease)?
10-40% of Hb Bart (y4)
w/ remainder being Hb F and Hb A
w/ remainder being Hb F and Hb A
129
What happens after γ and β switch (in relation to α thal- Hb H disease)?
Hb H replaces most of Hb Bart
Hb H is 1-40% with reduced amt of Hb A2,
traces of Hb Bart, and remainder Hb A
Hb H is 1-40% with reduced amt of Hb A2,
traces of Hb Bart, and remainder Hb A
130
What are the clinical features of Hb H disease?
mild-mod chronic hemolytic anemia
Hb 7-10 g/ dl with retic 3-10%
Hb 7-10 g/ dl with retic 3-10%
131
What is the RBC morph of Hb H?
Hb H inclusions (brilliant cresyl blue)
golf ball appearance
golf ball appearance
132
What is the definition of hydrops fetalis (Bart's)?
homozygous α0-thalassemia (--/ --)
results in no α chain production
results in no α chain production
133
What are the clinical features of hydrops fetalis?
without intrauterine transfusion, fetus becomes severely anemia, which leads to cardiac failure and edema in fetal subcutaneous tissues
134
What is the RBC morph of hydrops fetalis?
fewer RBC, RBC inclusions
135
What is important for dx of thalassemia?
HISTORY & physical exam
(bc thalassemia belt where high incidence of thal)
(bc thalassemia belt where high incidence of thal)
136
What is the main dx of thalassemia seen in PBS?
hypo/ micro
MCV MCH MCHC Low
RDW normal (thal minor)
RDW high (thal major)
OF (not helpful, usually low in minor bc target cells, resistant to lysis)
Hb electrophoresis
MCV MCH MCHC Low
RDW normal (thal minor)
RDW high (thal major)
OF (not helpful, usually low in minor bc target cells, resistant to lysis)
Hb electrophoresis
137
Name this electrophoresis //4. B+T
5. B0T
6. BT trait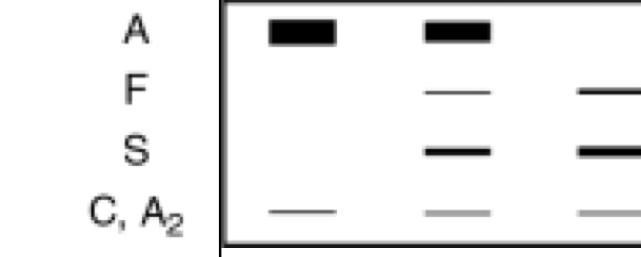
5. B0T
6. BT trait
1. Normal
2. Sickle trait
3. Sickle anemia
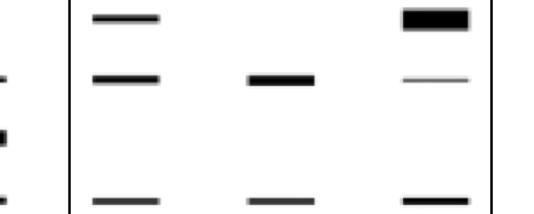
2. Sickle trait
3. Sickle anemia
138
How can you indicate difference between beta thal minor and IDA?
thal has hx in family (IDA happens regardless)
RBC/ MCV < 13 favors thal minor
RBC/ MCV > 13 favors IDA
IDA has FEP or ZPP
Iron studies
RBC/ MCV < 13 favors thal minor
RBC/ MCV > 13 favors IDA
IDA has FEP or ZPP
Iron studies