02+ABO+BLOOD+GRP
Study these flashcardsFree · spaced repetition · iPhone, Android, Mac & web
All cards
1
Which is the first identified human blood group system? & is the most significant blood group for transfusion practice?
ABO BLOOD GROUP SYSTEM
2
Why is the ABO blood group system unique?
Only blood group that has naturally-occuring Abs; it does not require the presence of a foreign RBC ag to illicit the production of the ABO Abs.
3
What is another name for ABO Abs?
Isohemagglutinins
4
What is another name for ABO Antigens?
Hemagglutinogen
5
How are ABO antibodies created? ( in general) and what are they referred to as?
they likely develop because of exposure to substances in the environment; "EXPECTED" Abs
6
What are the common isohemagglutinins found in ABO blood group system?
Anti-A & Anti-B
7
What type of immunoglobulin are ABO isohemagglutinins? and what can they readily activate?
IgMs (which readily activate the normal C' cascade)
8
What happens when there is a transfusion of incomptible RBCs?
Intravascular hemolysis to potential renal failure to death.
9
Should ABO typing test always be 100% correct/accurate? who said so?
Yes! always! ; TJC & CAP PT.
10
What are the 3 common allele system?
A, B, & H (O)
11
How is the ABH/O inherited? how are they expressed?
1 ABO autosomal gene from each parent, straight/forward Mendelian genetics/inheritance patterns; CODOMINANT.
12
True/false: The A & B genes are co-dominant
TRUE
13
Is the "O" gene recessive or dominant?
recessive
14
What is the "O" gene considered as? and why?
Amorph (gene passed down but not expressed); does not produce a transferase enzyme and results in no detectable O ag.
15
Where is ABO locus?
Chromosome 9
16
If both parents are type A, can they produce a type O baby?
YES:); Both parents have an O allele.
17
What are the possible genotypes for
O,
A,
B, AND
AB?
O,
A,
B, AND
AB?
HH (OO),
AA OR AO,
BB OR BO, AND
AB
AA OR AO,
BB OR BO, AND
AB
18
What antigen is on the RBC with a"O PHENOTYPE"? What Ab is circulating?
H; Anti-A, Anti-B, and Anti-A, B
19
What antigen is on the RBC with a"A PHENOTYPE"? What Ab is circulating?
A phenotype; Anti-B
20
What antigen is on the RBC with a"B PHENOTYPE"? What Ab is circulating?
B phenotype; Anti-A
21
What antigen is on the RBC with a"AB PHENOTYPE"? What Ab is circulating?
A and B; none
22
What are ABO antigens made out of? ( in general)
Carbohydrate (sugar) structure.
23
What genes affect the expression of the antigens on RBCs?
ABO, Hh, and Sese genes
24
How are ABO antigens created?
specific glycosyl-transferases add individual sugars sequentially to sites on sugar chains on the common precursor substance.
25
What is the H precursor substance made out of?
4-sugar chain: Glucose (Glu); Galactose (Gal); N-acetylglucosamine (GlcNAc); Galactose (Gal)
26
What type of chain is "4-sugar chain: Glucose (Glu); Galactose (Gal); N-acetylglucosamine (GlcNAc); Galactose (Gal)"? and what is the linkage?
Type 2; with beta 1 -> 4 linkage on the RBC surface antigen.
27
What is another name for the H gene?
FUT 1 gene
28
What are the possible genotypes for H gene?
HH
Hh,
and
hh
Hh,
and
hh
29
Is little "h" an amorph?
YES! and very rare
30
Is the H gene inherited with the ABO genes?
No, it is inherited independently
31
Is the H gene required for A OR B antigens? and why?
YES! H gene produces the α-2-Lfucosyltransferase that adds L-frucose to the precursor substance.
32
What is required to create an H antigen?
attachment of L-fucose (Fuc)
33
Type 1 oligosaccharide chain structures are for _______
Body fluids and secretions
34
Type 2 oligosaccharide chain structures are for _______
RBCs, body fluids and secretions
35
What enzyme does the A gene produce to create the A antigen? and which sugar is added to the H antigen?
α-3-N-acetylgalactosaminyltransferase; GalNAc (N-acetyl-D-galactosamine) sugar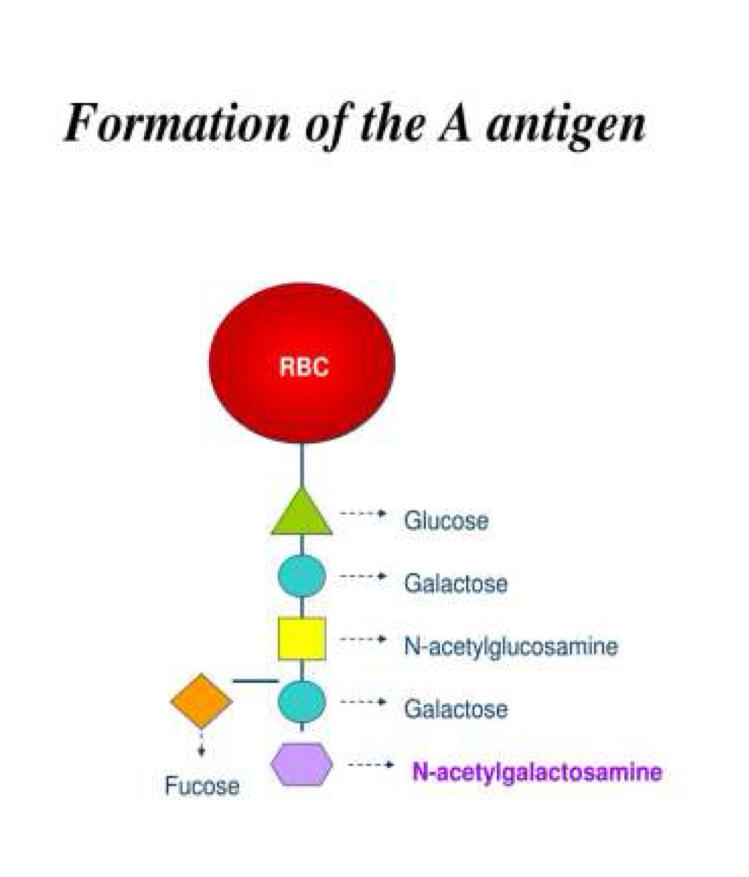
36
What enzyme does the B gene produce to create the B antigen? and which sugar is added to the H antigen?
α-3-D-galactosyltransferase; Gal (D-galactose) sugar 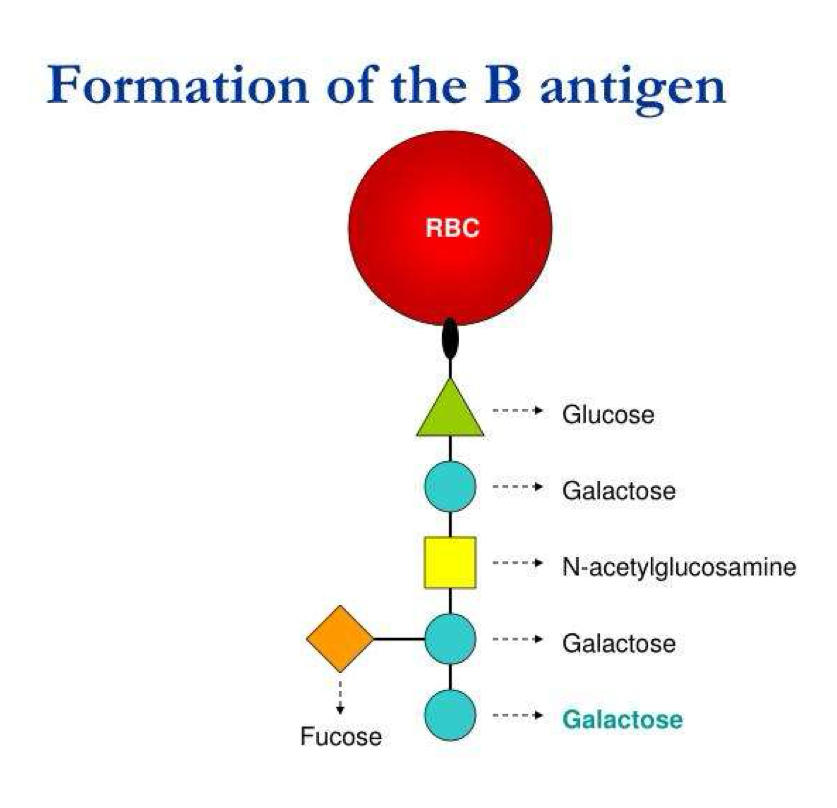
37
For the AB phenotype, which enzyme competes more efficiently for the H antigen?
B enzyme.
alpha-3-D galactosyltransferase
alpha-3-D galactosyltransferase
38
What is the % of human population that has the H gene?
>99.99%
39
Can A and B blood types have subgroup and what are subgroups?
yes! Subgroups usually have a lower number of A or B antigens on the RBC and it is inherited
40
From greatest to least amounts, what is the density of H antigens on cells?
O > A2 > B > A2B > A1 > A1B
41
What is another name for the hh genotype?
Bombay
42
How is the hh phenotype noted as?
Oh <- little "h"
43
What antigens are present on RBC for a person who has bombay? what about expected plasma antibodies?
No A, B, or H; POTENT Anti-H, Anti-A and Anti-B
44
What chromosome is the H (FUT 1) gene located on?
Chromosome 19
45
What chromosome is the Se (FUT 2) gene located on?
Chromosome 19
46
What chromosomes if the ABO gene located on?
Chromosome 9
47
If a patient contains the Se gene, what does that mean?
Patient is a secretor aka H substance is found in secretions.
48
If a patient contains the "se" gene, what does that mean?
Patient is a non-secretor; Silent/Amorph
49
What are the possible genotypes for secretor gene?
SeSe, Sese, or sese
50
What does it mean if a patient has the Se (secretor gene)?
Can release their A or B blood type markers (antigens) into gastrointestinal, genitourinary, and respiratory tract secretions, as well as in milk, sweat, tears, and amniotic fluid (NOT in CSF).
51
Which statement best describes how secreted blood group antigens appear in body fluids?
A) They are always attached to proteins in all body fluids.
B) They are mostly glycoproteins (mucins), but in milk and urine, they can also be free oligosaccharides.
C) They only exist as free oligosaccharides in all secretions.
D) They are only found in cerebrospinal fluid (CSF).
A) They are always attached to proteins in all body fluids.
B) They are mostly glycoproteins (mucins), but in milk and urine, they can also be free oligosaccharides.
C) They only exist as free oligosaccharides in all secretions.
D) They are only found in cerebrospinal fluid (CSF).
B) They are mostly glycoproteins (mucins), but in milk and urine, they can also be free oligosaccharides.
52
What type of secreted antigens are seen in milk and urine?
free oligosaccharides aka free floating sugar molecules
53
Secreted antigens are mostly what type of antigens?
glycoproteins aka mucins aka proteins with sugar chains
54
What is the Se (secretor gene) responsible for?
aka the FUT2 gene is responsible for producing the H antigen in secretions, which is required as a base for making A and B antigens in fluids like saliva, sweat, and mucus.
55
What % of the population are secretors of A, B, AND/OR H? what is the genotype for secretors?
80%; SeSe or Sese
56
What % of the population are nonsecretors? what is the genotype for nonsecretors?
20%; sese
57
Is "se" an amorph allele or not?
YES
58
Where are glycolipids usually found?
imbedded in cell membranes
59
Where are glycoproteins usually found?
secreted into exocrine fluids
60
Does Fycosly-transferase add L-frucose to make H antigen primarily on Type-1 or Type-2 chains?
Type-1 chains
61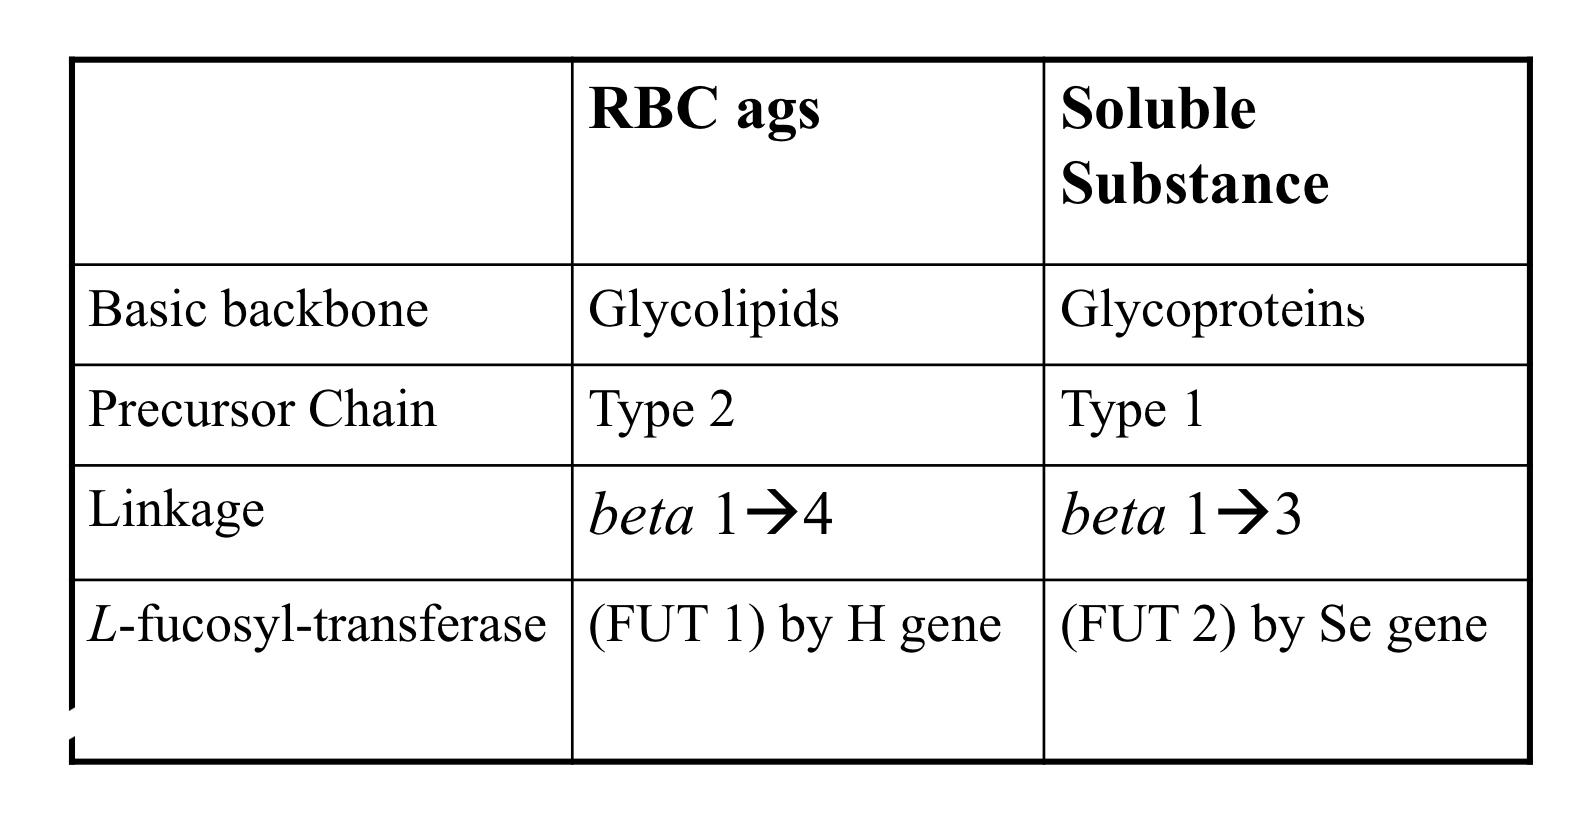
Fill in the chart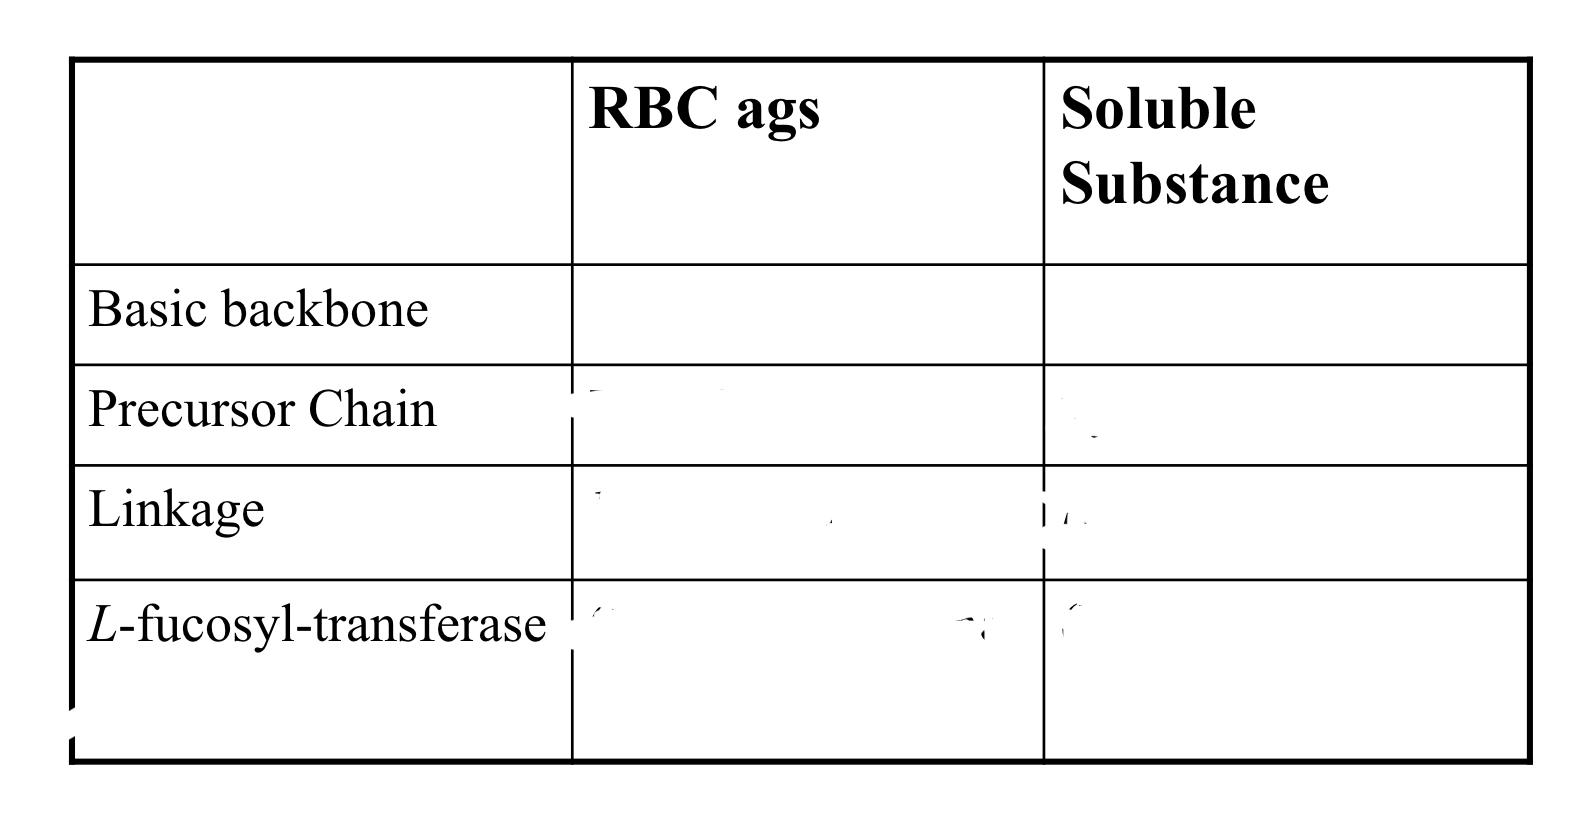
62
If patient is a non-secretor, what is the ABO phenotype, ag present and secreted antigen? (change this question)
Oh; NO A, B, H; NO A, B, H
63
Why do patients with ABO phenotype (Oh) bombay and Sese or Sese genotype NOT secrete A, B, H antigens?
Secreted genes only work when H antigens are present; in Oh individuals, there is no H antigen to secrete because FUT1 is nonfunctional.
64
What is not produced in hh genotype (Bombay)? specifically
No L-frucosyl-transferase produced
No H substance / no H ag
No A or B antigens present on RBCs
Only precursor substance found on RBCs
No H substance / no H ag
No A or B antigens present on RBCs
Only precursor substance found on RBCs
65
What reagents do Bombay RBCs NOT agglutinate with? what blood type is this?
Anti-A, Anti-B, Anti-A, B, or Anti-H; O-type
66
What naturally occuring antibodies in the plasma to bombay people have?
Anti-A, Anti-B, Anti-A, B, and POTENT Anti-H
67
What blood ABO blood group would you use to transfuse this patient: Oh bombay?
the only safe blood type for transfusion is Bombay (Oh) blood.
68
What are the subgroups for A gene?
A1 & A2
69
What enzyme does A1 & A2 encode for? and what does it do?
α-3-N-acetyl-galactos-aminyl-transferase puts an immunodominant sugar N-acetyl-D-galactose on H ag
70
Which subgoup of A gene is more potent? and why?
A1 gene is very potent and produces much more enzyme than the A2 gene.
71
Which subgroup A1 or A2 gene is more prevalent? (more common)
A1 > A2
72
What is the genotype for A1 phenotype?
A1A2
73
What is the genotype for A2 phenotype?
A2A2 or A2O
74
True/false: most group A infants "appear to be" A2 at birth. and why?
True; ABH antigens are not yet fully developed.
75
True/false: A2 cells always react well with Anti-A reagent
FALSE
76
How many antigens/cell do Type A1 and type A2 have? (Quantitative differences)
Type A1 = 800,000 - 1,200,000
Type A2 ~ 250,000
Type A2 ~ 250,000
77
What % of A2 people have anti-A1 in sera?
1-8%
78
What % of A2B people have anti-A1 in sera?
22-35%
79
What does it mean when A1 enzyme transferase is 5-10x more active?
it converts most of the H ag to the A1 antigen.
80
What are the reactions with Anti-A and Anti-A1 (lectin) for A1 patient?
Anti-A: +
Anti-A1 (lectin): +
Anti-A1 (lectin): +
81
What are the reactions with Anti-A and Anti-A1 (lectin) for A2 patient?
Anti-A: +
Anti-A1 (lectin): -
Anti-A1 (lectin): -
82
What are the frequency of A subgroups: Type A1
Type A1:
% of A types = 80
% of all A types (A, AB) = 33
% of A types = 80
% of all A types (A, AB) = 33
83
What are the frequency of A subgroups: Type A2
Type A2:
% of A types = 20
% of all A types (A, AB) = 8
% of A types = 20
% of all A types (A, AB) = 8
84
What are weak A subgroups?
rare variations of blood type A where the A antigen is present in very small amounts on red blood cells due to a mutant A allele inheritance. These subgroups have weaker reactions with anti-A reagents, making them harder to detect.
85
What are the different types of weak A subgroups and what % of all A types does it consist of?
A(3), A(x), A(Bantu), A(el)
86
How are weak A subgroups detected?
1. Anti-A,B sera obtain/manufactured from O donors
2. Anti-H
3. Adsorption-elution tests with Anti-A
4. Saliva studies for A and H ags
5. Monoclonal Ab reagents are commonly used and because of their specificity, it makes weak subgroup reactions nearly irrelevant
~also look for presence of Anti-A1 in the patient sera of A2 & A2B phenotypes.
2. Anti-H
3. Adsorption-elution tests with Anti-A
4. Saliva studies for A and H ags
5. Monoclonal Ab reagents are commonly used and because of their specificity, it makes weak subgroup reactions nearly irrelevant
~also look for presence of Anti-A1 in the patient sera of A2 & A2B phenotypes.
87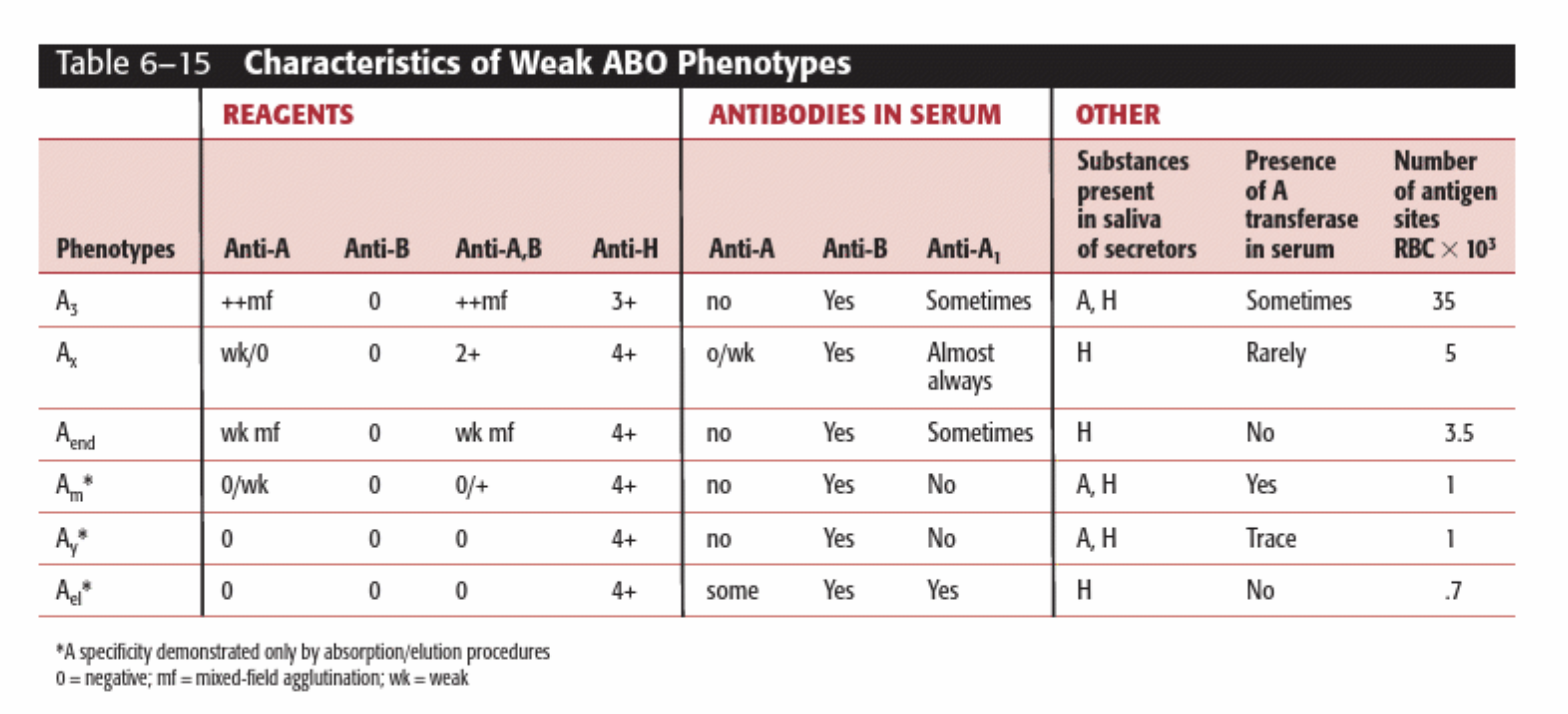
88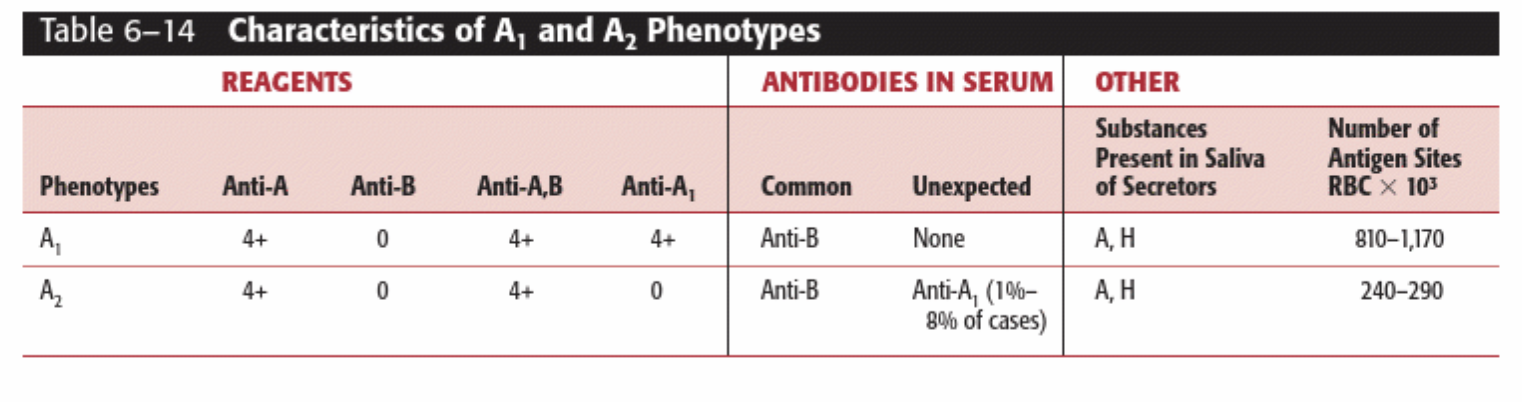
89
Which subgroups are rare?
B subgroups and weak subgroups
90
How are B subgroups detected?
Classified and detected similarly to A subgroups i.e. absorption-elution technique
91
Does an "anti-B1" exist?
No, only anti-A1 for A subgroup.
92
What is a "CIS AB"?
a rare and unusual inheritance pattern of the AB blood group. in Cis AB, both A and B antigens are encoded on the same chromosome and inherited together from one parent, rather than one from each.
93
Normally, what would be the offspring type for AB parent + O Parent?
AO, AO, BO, AND BO;
50% A TYPE, 50% B TYPE.
50% A TYPE, 50% B TYPE.
94
What are the gene mutations identified in CIS AB patients?
single transferase capable of transferring both GalNAc and Gal.
95
What is serum?
fluid portion of blood that remains after clotting has occurred. It is essentially plasma without clotting factors (such as fibrinogen).
96
What is plasma?
liquid component of blood that carries cells and proteins throughout the body. It makes up about 55% of total blood volume and serves as the transport medium for nutrients, hormones, waste products, and other substances. contains clotting factors
97
What does the purple top tube contain? and what does it contain?
EDTA; contains RBCs and plasma
98
What does the red top tube contain? and what does it contain?
clot activator; contains serum and a clot
99
How is serum and plasma separated from RBCs?
spin specimen tube
100
What does the pink top tube contain (not the anticoagulant)? and what is it considered to be?
Contains RBCs and plasma; the official BB specimen
101
What does EDTA stand for?
Ethylenediaminetetrasscetic acid
102
How many forms of EDTA are there? & what are they?
2 types: K2 EDTA - dried form coated along sides of plastic specimen tube
&
K3 EDTA - liquid form found in glass specimen tubes
&
K3 EDTA - liquid form found in glass specimen tubes
103
What does EDTA do?
Binds Ca2+ to prevent clotting
104
Which type of EDTA is used in hematology and for why?
Both K2 & K3 (purple tube) for CBCs, differential smears, platelet counts, sed rates, etc.
105
Where do Red top tubes usually go? (what department)
Chemistry
106
What type of anticoagulant does the Red Top Tube contain?
NO ANTICOAGULANT/ADDITIVES; just a plain glass or plastic tube
107
What should you do prior to performing BB tests for red top tube?
spin specimen tube for approx. 5 minutes
108
What is the serum (red top tube) tested for? what about the RBCs?
Antibody detection & identification.
Sloughed-/sluffed-off RBCs are used for blood typing.
Sloughed-/sluffed-off RBCs are used for blood typing.
109
What type of additive does the pink top tube have?
K2 EDTA - dried form coated along sides of a plastic specimen tube.
110
Why does the pink top tube NOT have liquid K3?
Liquid K3 causes a slight dilution in the patient's plasma which may result in te undetection of a low-titer antibodies; however, hematology analyzers account for the diltuion effect from K3 EDTA tubes when analyzing the CBC.
111
Which top tube is preferred for blood bank testing?
pink top tube
112
If there is no pink top tube, but only purple tob tube, what should you make sure first?
Ensure you use the K2 EDTA plastic tube, NOT the liquid K3 glass tube.
113
Blood banking reagents are categorized in 5 basic groups:
1. Antisera
2. Red Cell Reagent
3. Antiglobulin Reagents
4. Potentiators/Enhancement Media
5. Lectins
2. Red Cell Reagent
3. Antiglobulin Reagents
4. Potentiators/Enhancement Media
5. Lectins
114
What is Antisera?
possess antibodies (Abs) of known specificity
115
What is Red Cell Reagent?
RBCs that possess antigens of known specificity
116
What are Antiglobulin reagents?
detects IgG and/or complement (C') on RBCs
117
What are Potentiators/Enhancement Media?
Reagent used to increase antibody uptake to the corresponding antigen OR enhance RBC agglutination.
118
What are Lectins?
Plant extracts that react to specific human RBC antigens
119
What are the 8 lectin reagents?
Dolichos biflorus
Ulex europaeus
Vicia graminea
Iberus amara
Arachis hypogae
Glycine soja
Salvia sclarea
Salvia horminum
Ulex europaeus
Vicia graminea
Iberus amara
Arachis hypogae
Glycine soja
Salvia sclarea
Salvia horminum
120
What are the Antigen specificity for
Dolichos biflorus
Ulex europaeus
Vicia graminea
Iberus amara
Arachis hypogae
Glycine soja
Salvia sclarea
Salvia horminum
Dolichos biflorus
Ulex europaeus
Vicia graminea
Iberus amara
Arachis hypogae
Glycine soja
Salvia sclarea
Salvia horminum
Dolichos biflorus -- A1
Ulex europaeus -- H
Vicia graminea -- N
Iberus amara -- M
Arachis hypogae -- T
Glycine soja -- Differentiates polyagglutination
Salvia sclarea -- Tn
Salvia horminum -- Differentiates polyagglutination
Ulex europaeus -- H
Vicia graminea -- N
Iberus amara -- M
Arachis hypogae -- T
Glycine soja -- Differentiates polyagglutination
Salvia sclarea -- Tn
Salvia horminum -- Differentiates polyagglutination
121
When using any BB reagents, you must strictly follow these guidelines:
1. Carefully review the package inserts
2. Adhere to the package insert instruction for use
3. Adhere to the manufacturer's restrictions & precautions - know your reagent's limitations
2. Adhere to the package insert instruction for use
3. Adhere to the manufacturer's restrictions & precautions - know your reagent's limitations
122
What type of immunoglobulins are in blood bank reagents- ANTISERA?
IgM, IgG, and IgA
123
What is IgM usually contained in?
"saline" media
124
What is IgG usually contained in?
a "potentiator" media to enhance reactivity to RBCs OR in a "saline" media to react at the AHG phase of testing (antiglobulin reagent)
125
What is IgA usually contained in?
There is no known IgA reagent at this time.
126
what are the 2 types of BB reagents- antisera?
Polyclonal vs monoclonal
127
What are 3 facts about polyclonal antisera?
- Usually an immune response.
- Produced by multiple B-cell lines.
- Broader specificity due to mixture of antibodies to multiple epitopes.
- Produced by multiple B-cell lines.
- Broader specificity due to mixture of antibodies to multiple epitopes.
128
What are 3 facts about monoclonal antisera?
- Produced by a single b-cell line
- Specificity directed at single epitope (best type of reagent)
- Identical antibody molecules.
- Specificity directed at single epitope (best type of reagent)
- Identical antibody molecules.
129
What are advantages to using antisera monoclonal antibodies?
- Unlimited production
- No human source - animal source antibody usually obtained through hydridoma technology
- IgM antibody, so direct agglutination occurs in shorter time
- No contaminating antibodies
- Standardized reagents
- Very little or no variation between batches.
- No human source - animal source antibody usually obtained through hydridoma technology
- IgM antibody, so direct agglutination occurs in shorter time
- No contaminating antibodies
- Standardized reagents
- Very little or no variation between batches.
130
Why are Red Cell Reagents used in BB?
- Used with patient sera to identify patient antibodies that are present
- Used as "positive" and "negative" controls, when using a specific antisera reagent.
- Used as "positive" and "negative" controls, when using a specific antisera reagent.
131
What testing is done for RBC antigens?
Forward type/ group
132
What testing is done for plasma/ serum?
Reverse type/ group
133
which reagents are used for "forward" and "reverse" typing?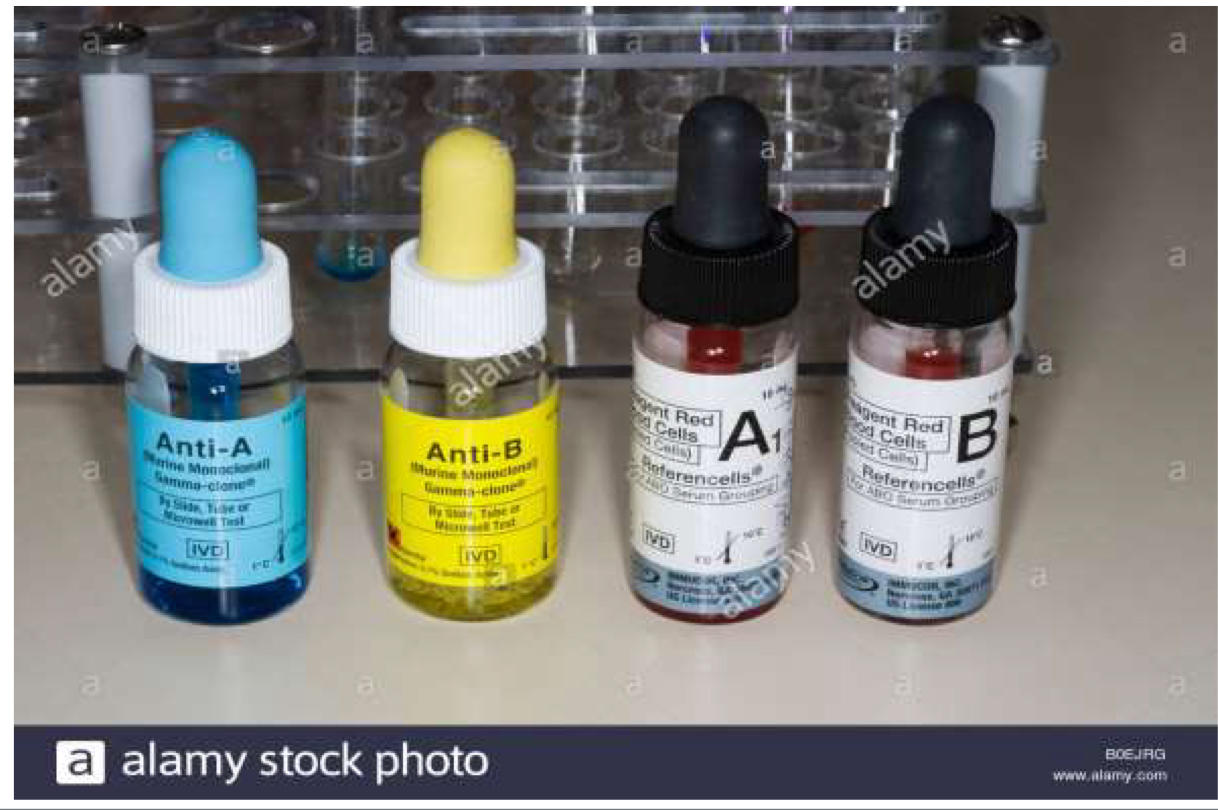
Forward - left
Reverse - right
Reverse - right
134
What is always performed for FORWARD TYPE?
Unknown RBCs + Anti-A = aggl?
Unknown RBCs + Anti-B = aggl?
Unknown RBCs + Anti-B = aggl?
135
What is optionally performed for FORWARD TYPE?
Unknown RBCs + Anti-A, B = aggl.? (subgroup)
Unknown RBCs + Anti-H = aggl.? (Bombay)
Unknown RBCs + Anti-A1 = aggl.? (A subgroup)
Lectins: Anti-A1 (Dolichos biflores); Anti-H (Ulex europeous)
Unknown RBCs + Anti-H = aggl.? (Bombay)
Unknown RBCs + Anti-A1 = aggl.? (A subgroup)
Lectins: Anti-A1 (Dolichos biflores); Anti-H (Ulex europeous)
136
What is the Anti-A,B reagent known as? and what does it contain?
- "group O" typing sera;
- contains anti-A, B of IgG2 subclass
- contains anti-A, B of IgG2 subclass
137
What grading does forward typing typically give?
4+ reactions, unless subgroup or mixed field.
138
why is the "reverse" type / group performed?
to detect circulating antibodies to A, B, AB, OR H
139
What is always performed for Reverse typing?
Unknown serum + A1 cells = aggl.?
Unknown serum + B cells = aggl.?
Unknown serum + B cells = aggl.?
140
What is optionally performed for Reverse typing?
Unknown serum + O cells = aggl.? (Bombay or unexpected alloantibodies)
141
Why should Reverse typing not be performed on children < 6 months?
heir immune system is immature, and they have not yet produced their own ABO antibodies (anti-A and anti-B). Instead, any antibodies present in their plasma are likely passively acquired maternal antibodies that crossed the placenta during pregnancy. This can lead to misleading results in ABO typing.
142
True/false: Type O people have higher titers of Anti-A than do B people.
True
TITERS VARY
TITERS VARY
143
What complications can occur due to the titer variation in type O people?
becuase o people have high titers of Anti-A than do B people, it may cause seriou/fatal incompatible transfusion reactions
&
May cause severe Hemolytic Disease of the Fetus & Newbord (HDFN); usually seen in group O mothers giving birth to group A neonates.
&
May cause severe Hemolytic Disease of the Fetus & Newbord (HDFN); usually seen in group O mothers giving birth to group A neonates.
144
What are the specific antibodies in the ABO blood group system?
Anti-A and Anti-B
145
What type of antibodies are present in Group O individuals?
Anti-A and Anti-B IgM antibodies
146
What additional antibody is present in Group O individuals?
Anti-A,B (an IgG2 subclass antibody)
147
Is Anti-A,B in Group O individuals a combination of Anti-A and Anti-B?
No, Anti-A,B is a single "cross-reacting" IgG antibody unique to Group O individuals.
148
At what age are adult levels of antibodies generally reached?
By age 5-10
149
At what age are there decreased ABO titers due to aging and weakened immune system?
> 65 years.