Lecture 5 - Renal and Metabolic Disease
Study these flashcardsFree · spaced repetition · iPhone, Android, Mac & web
All cards
1
What are the 4 types of renal diseases? what gets affected
Glomerular
Tubular
Interstitial
Vascular
Tubular
Interstitial
Vascular
2
What types of disease is glomerular split up into?
Primary and secondary diseases; most often immune mediated
3
What are primary glomerular diseases?
a group of kidney diseases that damage the glomeruli, the kidney's filtering units
4
What are examples of primary glomerular diseases?
Acute/chronic glomerular nephritis;
5
What are secondary glomerular diseases?
kidney conditions that have an identifiable underlying cause, such as an infection or systemic disease
6
What is an example of secondary glomerular disease?
Diabetes mellitus, lupus erythematosus
7
What are tubular renal diseases a result of?
Toxic or infectious substances
8
What are interstitial renal diseases a result of?
Result from toxic or infectious substances
9
What is the cause of vascular renal diseases?
Caused by a reduction in renal perfusion that induces morphologic and functional changes in kidney.
10
Glomerular diseases that damage glomeruli include?
immunologic, metabolic, and hereditary
11
Morphological changes in glomerulus are mostly ______
Immune mediated
12
Give examples of 2 types of morphologic changes in glomerulus.
Cellular proliferation and glomerular basement thickening
13
What happens during cellular proliferation in glomerulus?
Increased numbers of endothelial and other cells in glomerular tuft
14
What causes cellular proliferation in glomerulus?
drawn by a local chemotactic response
15
What happens during glomerular basement thickening in glomerulus?
includes any process that results in enlargement of basement membrane (immune complexes and diabetes)
16
what happens when there is a destruction in the layers of the glomerulus? what gets affected?
GFR
17
Destruction of the glomerulus causes what type of uria? other causes?
Oliguria - more water in the blood and hypertension: can't filter the blood well
18
What can be found in the urine when there destruction in the layers of the glomerulus? (nephritic)
WBC, albumin, RBCs
19
What are the 6 clinical features of glomerular disease?
Hematuria
Proteinuria
Oliguria
Azotemia
Edema
Hypertension
Proteinuria
Oliguria
Azotemia
Edema
Hypertension
20
What is hematuria?
blood in urine
21
What is Azotemia?
condition in which you have too much nitrogen, creatinine and other waste products in your blood.
22
How does a person get an Edema?
loss of protein (albumin) in blood vessel
water comes out of the capillary tubes and goes TO the tissue and causes inflammation and hypertension (oncotic pressure).
water comes out of the capillary tubes and goes TO the tissue and causes inflammation and hypertension (oncotic pressure).
23
How much proteinuria is needed to diagnose Nephrotic syndrome?
Heavy proteinuria (≥3 g/day)
24
What is the result of Nephrotic syndrome? (what is seen in the urine)
a kidney disease that causes the kidneys to leak too much protein into the urine
25
What does hypoproteinemia usually lead to?
Hypoalbuminemia - loss of albumin
26
What starts to increase when protein is being lost in the urine?
LIPIDS: hyperlipidemia/ lipiduria (oval fat bodies)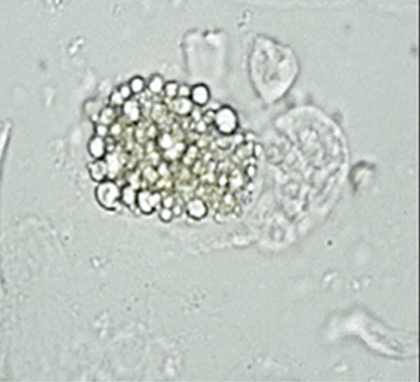
27
What happens to the oncotic pressure in the blood during Edema?
oncotic pressure goes down and fluid leaks out of the vasculature into the surrounding tissue.
28
What causes nephrotic syndrome?
when the filtering units of the kidney are damaged
29
what structures in the nephron do not cause nephrotic syndrome?
diseases that affect tubules and interstitium.
30
What are the clinical symptoms presented in nephritic syndrome? (4)
a clinical syndrome that presents as
1.Hematuria 2.Oliguria 3.Azotemia 4.Hypertension
1.Hematuria 2.Oliguria 3.Azotemia 4.Hypertension
31
Where is the damage in nephritic syndrome?
within the glomeruli
32
What do the hemodynamic changes in nephritic syndrome cause? (immediately)
decreased glomerular filtration rate, manifested clinically as oliguria and azotemia
33
Why does hypertension occur in nephritic syndrome?
result of fluid retention and increased renin released from ischemic kidneys.
34
What are the 2 types of glomerulonephritis? (Nephritic diseases)
Acute glomerulonephritis and rapid (crescentic) glomerulonephritis
35
What are the 6 types of nephrotic syndrome?
1.Membranous glomerulonephritis
2.Minimal change disease
3.Focal segmental glomerulonephritis
4.Membranoproliferative glomerulonephritis
5.Immunoglobulin A (IgA) nephropathy <-Berger Disease
6. Chronic glomerulonephritis
2.Minimal change disease
3.Focal segmental glomerulonephritis
4.Membranoproliferative glomerulonephritis
5.Immunoglobulin A (IgA) nephropathy <-Berger Disease
6. Chronic glomerulonephritis
36
What is acute glomerulonephritis?
inflammation of the tiny filters in the kidneys (glomeruli).
37
Is acute glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Antibody-mediated
38
Is Rapid (crescentic) glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Antibody-mediated
39
Is Membranous glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Antibody-mediated
40
Is Minimal change disease antibody mediated, t-cell mediated, or immune complex mediated?
T-cell immunity disfunction
41
Is Focal segmental glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Unknown! possibly a cirulating systemic factor; can reoccur after kidney transplant.
42
Is Membranoproliferative glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Immune complex or complement activation
43
Is Immunoglobulin A (IgA) nephropathy (Berger's Disease) antibody mediated, t-cell mediated, or immune complex mediated?
IgA mediated; complement activation.
44
Is Chronic glomerulonephritis antibody mediated, t-cell mediated, or immune complex mediated?
Variable
45
Which type of glomerulonephritis is associated with Steptoccus infection or skin infection?
Acute glomerulonephritis (AGN), poststreptococcal
46
Which type of nephortic syndrome is associated with adults?
Membranous glomerulonephritis
47
Which type of nephrotic syndrome is associated with children; caused after infection (lymphoma); no podocytes are present/damaged?
Minimal change disease
48
Which type of nephrotic syndrome is associated with some part of the glomerular; genetic in african americans and hispanic; happens after infection such as sickle cell disease?
Focal segmental glomerulonephritis
49
Which type of nephrotic syndrome is associated wtih proliferation of immune complex in basement membrane?
Membranoproliferative glomerulonephritis
50
which type of nephrotic syndrome is associated with muscosal infection; IgA mediated; mostly affects children and young adults?
Immunoglobulin A (IgA) nephropathy (Berger Disease)
51
Which type of nephrotic syndrome is associated with decreased renal function in 3 months?
Chronic glomerulonephritis
52
What is the typical outlook and pathogenesis for Acute Glomerulonephritis (AGN), poststreptococcal?
Outlook: Acute nephritic syndrome.
Pathogenesis: Antibody mediated.
Pathogenesis: Antibody mediated.
53
What glomerular changes are seen in Acute Glomerulonephritis (AGN)?
Cellular proliferation (diffuse), leukocytic infiltration, interstitial swelling.
54
What is the typical outlook and pathogenesis for Rapidly Progressive Glomerulonephritis (RPGN)?
Outlook: Acute nephritic syndrome.
Pathogenesis: Antibody mediated; often anti-GBM.
Pathogenesis: Antibody mediated; often anti-GBM.
55
What glomerular changes are seen in Rapidly Progressive Glomerulonephritis (RPGN)?
Cellular proliferation to form characteristic "crescents"; leukocytic infiltration, fibrin deposition, GBM disruptions.
56
What is the typical outlook and pathogenesis for Membranous Glomerulonephritis (MGN)?
Outlook: Nephrotic syndrome.
Pathogenesis: Antibody mediated.
Pathogenesis: Antibody mediated.
57
What glomerular changes are seen in Membranous Glomerulonephritis (MGN)?
Basement membrane thickening due to immunoglobulin (Ig) and complement (C) deposits, loss of foot processes (diffuse).
58
What is the typical outlook and pathogenesis for Minimal Change Disease (MCD)?
Outlook: Nephrotic syndrome.
Pathogenesis: T-cell immunity dysfunction, loss of glomerular polyanions.
Pathogenesis: T-cell immunity dysfunction, loss of glomerular polyanions.
59
What glomerular changes are seen in Minimal Change Disease (MCD)?
Loss of foot processes.
60
What is the typical outlook and pathogenesis for Focal Segmental Glomerulosclerosis (FSGS)?
Outlook: Proteinuria variable; subnephrotic to nephrotic.
Pathogenesis: Unknown; possibly a circulating systemic factor; can reoccur after kidney transplant.
Pathogenesis: Unknown; possibly a circulating systemic factor; can reoccur after kidney transplant.
61
What glomerular changes are seen in Focal Segmental Glomerulosclerosis (FSGS)?
Sclerotic glomeruli with hyaline and lipid deposits (focal and segmental); diffuse loss of foot processes; focal IgM and C3 deposits.
62
What is the typical outlook and pathogenesis for Membranoproliferative Glomerulonephritis (MPGN)?
Outlook: Depends on type, either nephrotic syndrome or hematuria/proteinuria. Pathogenesis: Immune complex or complement activation.
63
What glomerular changes are seen in Membranoproliferative Glomerulonephritis (MPGN)?
Cellular proliferation (mesangium); leukocytic infiltration; IgG and complement deposits.
64
What is the typical outlook and pathogenesis for IgA Nephropathy?
Outlook: Recurrent hematuria and proteinuria.
Pathogenesis: IgA mediated; complement activation.
Pathogenesis: IgA mediated; complement activation.
65
What glomerular changes are seen in IgA Nephropathy?
Deposition of IgA in mesangium; variable cellular proliferation.
66
What is the typical outlook and pathogenesis for Chronic Glomerulonephritis?
Outlook: Chronic renal failure.
Pathogenesis: Variable.
Pathogenesis: Variable.
67
What glomerular changes are seen in Chronic Glomerulonephritis?
Hyalinized glomeruli.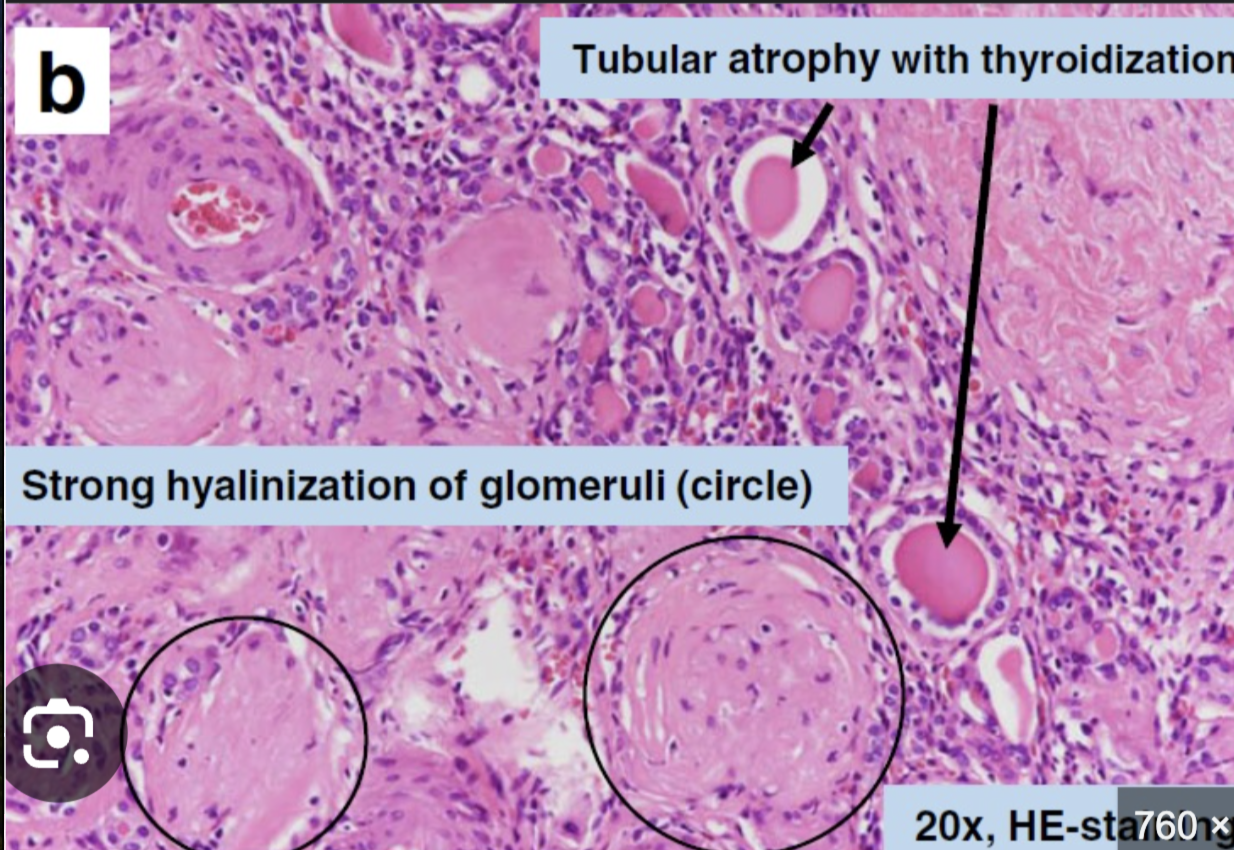
68
what are the 3 types of systemic diseases and (secondary) glomerular damage?
1.Systemic lupus erythematosus (SLE)
2.Diabetes Mellitus
3. Amyloidosis
2.Diabetes Mellitus
3. Amyloidosis
69
what is system lupus erthematosus (SLE)?
Autoimmune disorder with immune complex deposits
70
What is Diabetes mellitus?
Carbohydrate metabolism disorder due to lack of insulin or cellular resistance to insulin
71
What is amyloidosis?
Group of systemic diseases involving many organs; characterized by deposits of amyloid, a pathologic protein substance. 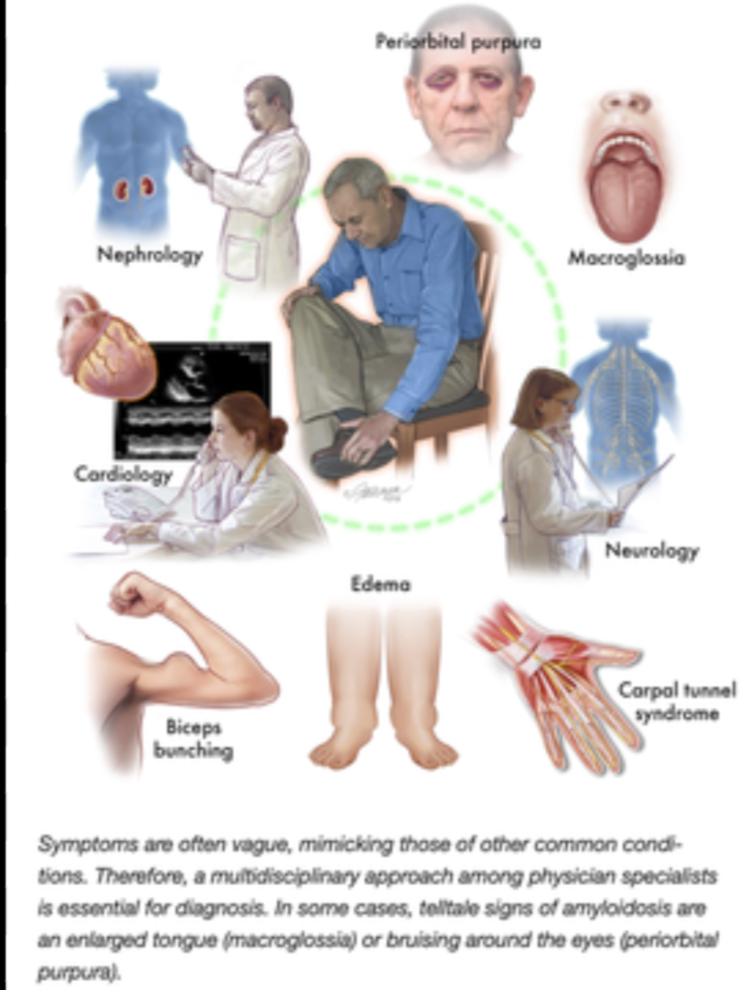
72
what does amyloidosis damage?
destroys the glomerular.
73
what does Diabetes mellitus cause in the kidneys?
thickening of basement membrane which causes glomerular schlerosis.
74
What are symptoms of SLE system lupus erythematosus?
Butterfly rash and joint pain
75
What are the 2 types of tubular disease?
1.Acute tubular necrosis (ATN)
2.Tubular dysfunction
2.Tubular dysfunction
76
What can Acute tubular necrosis be identified as? (2)
Ischemic ATN & Toxic ATN
77
What is Ischemic ATN?
a type of acute kidney injury (AKI) that occurs when the kidneys are damaged due to a lack of blood flow and oxygen
Seen in sepsis, shock, trauma
Seen in sepsis, shock, trauma
78
What is Toxic ATN?
occurs when the tubular cells are exposed to a toxic substance
From exogenous or endogenous nephrotoxins
From exogenous or endogenous nephrotoxins
79
what are the 4 types of tubular dysfunction?
1.Fanconi’s syndrome
2.Cystinosis and cystinuria
3.Renal glucosuria
4.Renal tubular acidosis
2.Cystinosis and cystinuria
3.Renal glucosuria
4.Renal tubular acidosis
80
Cystinuria - found in urine
What condition is this?
Cystinuria - found in urine
81
What is Fanconi's syndrome?
dysfunction in proximal tubules; aminoacids excreted in urine due to exposure to lead or hereditary disease
82
What is renal glucosuria?
a rare condition in which too much of the simple sugar glucose is removed through the urine.
83
what is renal tubular acidosis?
when the kidneys do not remove acids from the blood into the urine as they should.
renal tubules become acidic because of the impaired ability to exchange sodium and potassium.
renal tubules become acidic because of the impaired ability to exchange sodium and potassium.
84
What are the various tubulointerstitial disease/infections? (5)
1.Urinary tract infections (UTIs)
2.Acute pyelonephritis
3.Chronic pyelonephritis
4.Acute interstitial nephritis (AIN)
5.Yeast infections
2.Acute pyelonephritis
3.Chronic pyelonephritis
4.Acute interstitial nephritis (AIN)
5.Yeast infections
85
What it this skin rash assoicated to?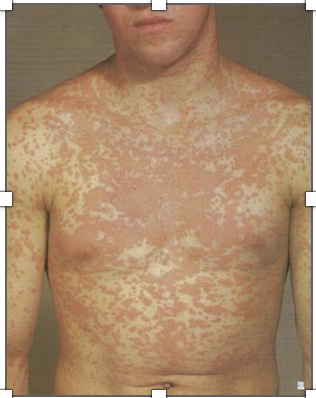
acute interstitial nephritis (AIN)
86
What are the 2 different types of UTIs?
upper and lower
87
Where is the infection in upper UTIs?
Kidney infection
88
Where is the infection in lower UTIs?
bladder infection
89
What organism is reponsible for UTIs?
E. coli
90
Who gets UTIs more often?
Women > Men
91
What is acute pyelonephritis?
Bacterial kidney infection
92
What is Chronic pyelonephritis?
infection caused by Backflow of urine from bladder to kidney
93
What is Acute interstitial nephritis (AIN)?
is characterized by the presence of inflammatory infiltrates and edema within the interstitium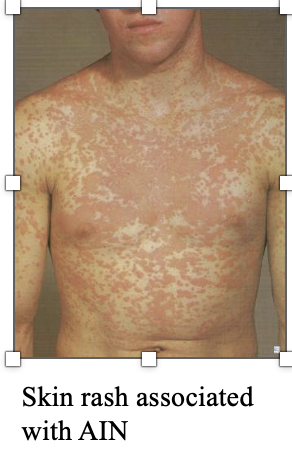
94
What is a yeast infection?
a fungal infection caused by an overgrowth of the yeast Candida
95
Acute renal failure
Sudden decrease in glomerular filtration rate (GFR), azotemia, and oliguria.
96
Chronic renal failure
Progressive loss of renal function
97
what type of damages are there in Acute Renal Failure?
Functional abnormality; but no cellular changes
98
What is Acute renal failure classified as?
Prerenal, renal, and postrenal
99
What classifies chronic renal failure?
hypertrophy of remaining healthy nephrons, not clinically recognizable until 80% to 85% function lost
100
What conditions are seen in chronic renal failure?
Azotemia, acid-base imbalance, abnormal calcium (Ca) and phosphate (PO4) metabolism.
101
What happens in postrenal (after the kidney) acute renal failure?
obstruction of urethra
102
What happens in (before the kidney) acute prerenal failure?
decrease blood flow to kidney
103
What happens in acute renal failure?
damage to epithelial cells
104
What can chronic renal failure lead to?
End-stage renal disease
105
What is renal calculi?
also known as kidney stones, are solid masses of minerals and salts that form in the kidneys
Aggregates of mineral salts in a matrix of proteins and lipids
Aggregates of mineral salts in a matrix of proteins and lipids
106
What precentage of calcium do renal calculi have?
>75%
107
What mineral does Renal calculi mostly contain?
calcium
108
where can renal calculi be found?
renal calyces, renal pelvis, ureters or bladder
109
What factors influence calculi formation?
Supersaturation of chemical salts in urine;
Optimal urinary pH;
Urinary stasis;
Treatment depends on type and size of stones
Optimal urinary pH;
Urinary stasis;
Treatment depends on type and size of stones
110
Give an example of how renal calculi are formed?
A person that lives a sedentary life has an increased concentration of urine; therefore, calcium/salts form crystals or stones.
111
What is isohydric?
having the same or constant pH, or the same concentration of hydrogen ions
112
What are risk factors for renal calculi? (5)
Immobility
Sedentary lifestyle
Dehydration
Metabolic disturbances
History of Renal calculi
Sedentary lifestyle
Dehydration
Metabolic disturbances
History of Renal calculi
113
What is the pathophysiology (step 1) of renal calculi?
1: Slow urine flow, resulting in supersaturation of the urine with the particular element that first become crystallized and later become stone.
114
What is the pathophysiology (step 2) of renal calculi?
Damage to the lining of the urinary tract
115
What is the pathophysiology (step 3) of renal calculi?
Decreased inhibitor substances in the urine that would otherwise present supersaturation and crystalline aggregation.
116
What type of kidney stones are these?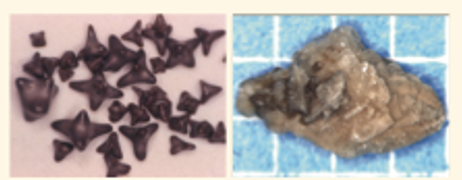
Calcium-based stones
117
What type of kidney stones are these?
Struvite stones
118
What type of kidney stones are these?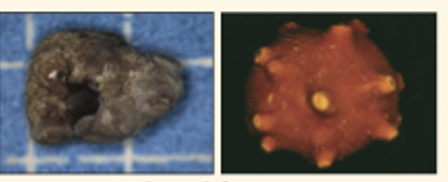
Uric acid stones
119
What type of kidney stones are these?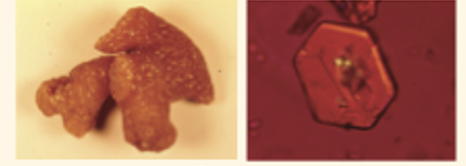
Cystine stones
120
Struvite stones are due to what?
UTI
121
Uric acids stones are due to what?
foods with high protein
122
Cystine stones are due to what?
Cystinosis. forms crystals first and then stones
123
What are amino acid metabolism disorders? ((6) - body can't break down certain amino acids
Cystinosis and cystinuria - can affect kidneys and eyes
Maple syrup urine disease (MSUD) - can't break down isoleucine, leucine, and valine
Phenylketonuria (PKU) - build up of PKU causing mental retardation
Alkaptonuria - accumulation of hyperpigmented substances (black urine)
Tyrosinuria - can't break down tyrosine
Melanuria - melanin
Maple syrup urine disease (MSUD) - can't break down isoleucine, leucine, and valine
Phenylketonuria (PKU) - build up of PKU causing mental retardation
Alkaptonuria - accumulation of hyperpigmented substances (black urine)
Tyrosinuria - can't break down tyrosine
Melanuria - melanin
124
What are amino acid metabolism disorders? definition
body can’t break down certain amino acids for whatever reason
125
What is maple syrup urine disease (MSUD)?
): inherited and where there is not enough BCKAD enzyme to break down isoleucine and leucine and valine; Amino acids accumulate in brain (children’s brain is damaged). Babies develop sleepiness or irritability. Screened at the newborn stage.
126
What is phenlketonuria (PKU)?
rare inherited disorder that causes an amino acid called phenylalanine to build up in the body.
127
What is alkaptonuria?
black urine disease, is a very rare inherited disorder that prevents the body fully breaking down two protein building blocks: tyrosine and phenylalanine
128
What is tyrosinuria?
a condition where there is an abnormally high level of tyrosine in the urine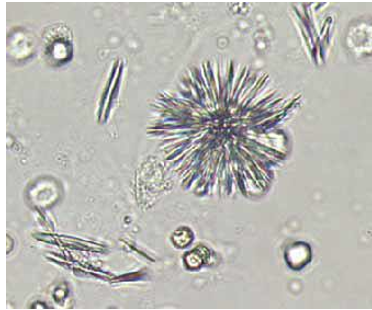
129
What is melanuria?
a medical condition that refers to the presence of dark-colored urine due to an increased amount of melanin or its precursors in the urine.
130
Why does alkaptonuria happen? pathophys
Phenylalanine can't convert to tyrosine which causes pigmentation in eyes, skin
131
If tyrosine can't be converted from phyelalanine, what happens?
PKU
Albinism
Creatinism
Tyrosinosis
Alkaptonuria
Albinism
Creatinism
Tyrosinosis
Alkaptonuria
132
what metabolic disorder is this?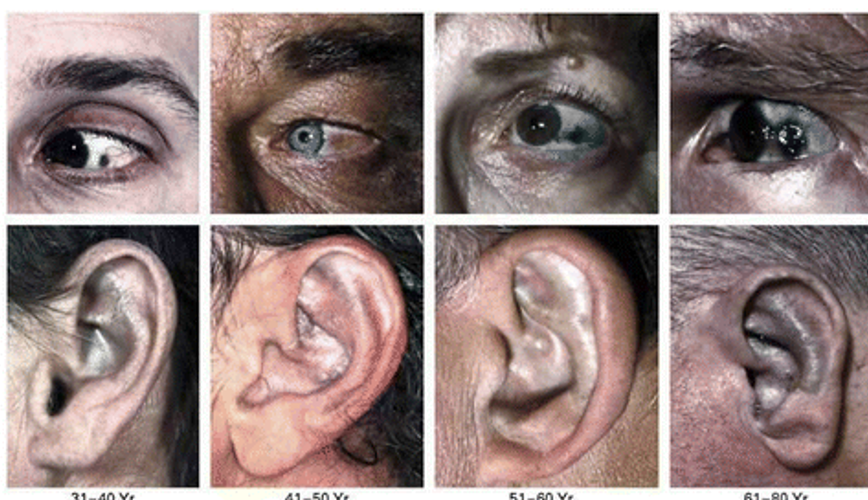
Alkaptonuria
133
Albinism is due to what?
mutation of certain gene that affects melanin production.
134
what is another clinical feature of alkaptonuria?
urine becomes oxidized in the air 
135
What is cretinism?
a condition of abnormal mental and physical development resulting from a deficiency of thyroid hormone in fetal or early life
136
Type 1 diabetes mellitus is due to what?
Pancrease can't produce insulin. genetics; low production of the insulin by the pancrease, glucose stays in the blood
137
Type 2 diabetes mellitus is due to what?
90% (no receptors on cells) occurs mostly after age 30; obesity; solute diuresis; solute in urine; has glucose and salt.
138
What is porphyrias?
Liver disorder; increase porphryins; skin is photosensitive; color of urine is purple.