Pediatric Seizures
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Goals of therapy
Obtain the greatest possible seizure control with minimal side effects
Prevent the occurrence of emotional and behavioral aberrations
Prevent the occurrence of emotional and behavioral aberrations
2
Principles of Antiepileptic Drug Therapy
❖ Establish diagnosis and exclude remedial causes
❖ Select primary drug most appropriate for seizure type and your patient
❖ Choosing an antiepileptic drug
❖ Seizure type & severity
❖ Medication history
❖ Ageender
❖ Drug interactions
❖ Concurrent diseases
❖ Select primary drug most appropriate for seizure type and your patient
❖ Choosing an antiepileptic drug
❖ Seizure type & severity
❖ Medication history
❖ Ageender
❖ Drug interactions
❖ Concurrent diseases
3
Titrate dose to achieve...
Desired serum concentration
4
Consider ____ antiepileptic drug concentration
Free
5
Be certain your patient is _________ before labeling them as refractory to current therapy
Compliant
6
First generation AEDs
❖Phenobarbital
❖Phenytoin (Dilantin®)
❖Ethosuximide (Zarontin®)
❖Diazepam (Valium®)
❖Carbamazepine (Tegretol®)
❖Valproic acid (Depakene®, Depakote®, Depacon®)
❖Phenytoin (Dilantin®)
❖Ethosuximide (Zarontin®)
❖Diazepam (Valium®)
❖Carbamazepine (Tegretol®)
❖Valproic acid (Depakene®, Depakote®, Depacon®)
7
Second generation AEDs
❖ Felbamate (Felbatol®)
❖ Gabapentin (Neurontin®)
❖ Lamotrigine (Lamictal®)
❖ Topiramate (Topamax®)
❖ Tiagabine (Gabitril®)
❖ Levetiracetam (Keppra®)
❖ Oxcarbazepine (Trileptal®)
❖ Zonisamide (Zonegran®)
❖ Vigabatrin (Sabril®)
❖ Rufinamide (Banzel®)
❖ Clobazam (Onfi®)
❖ Gabapentin (Neurontin®)
❖ Lamotrigine (Lamictal®)
❖ Topiramate (Topamax®)
❖ Tiagabine (Gabitril®)
❖ Levetiracetam (Keppra®)
❖ Oxcarbazepine (Trileptal®)
❖ Zonisamide (Zonegran®)
❖ Vigabatrin (Sabril®)
❖ Rufinamide (Banzel®)
❖ Clobazam (Onfi®)
8
First versus Second Generation
❖Comparison between first and second generation agents
❖ Efficacy
❖ Safety
❖ First generation agents associated with high incidence and intolerable neurotoxicity
❖ Second generation agents - fewer side effects
❖ Second generation agents have less drug interaction potential
❖ Second generation agents less likely to require therapeutic drug monitoring
❖ Efficacy
❖ Safety
❖ First generation agents associated with high incidence and intolerable neurotoxicity
❖ Second generation agents - fewer side effects
❖ Second generation agents have less drug interaction potential
❖ Second generation agents less likely to require therapeutic drug monitoring
9
Initiation of AED
❖ Initiate with monotherapy
❖ Recurrence of absence, myoclonic, and infantile spasms is certain $\rightarrow$ initiate anticonvulsant
❖ Single episode of afebrile tonic-clonic seizure with normal EEG $\rightarrow$ advised not to initiate anticonvulsant
❖ Have not shown to improve long-term prognosis
❖ > 2 afebrile seizures within 6-12 months $\rightarrow$ initiate anticonvulsant
10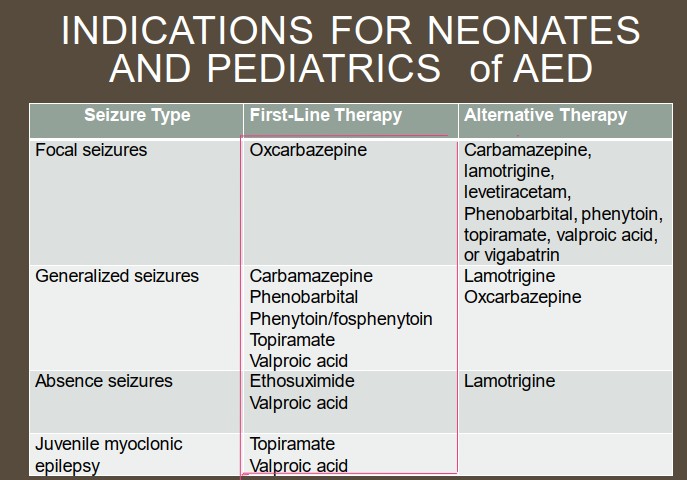
Bildverdeckung: nenne die verdeckten Beschriftungen
11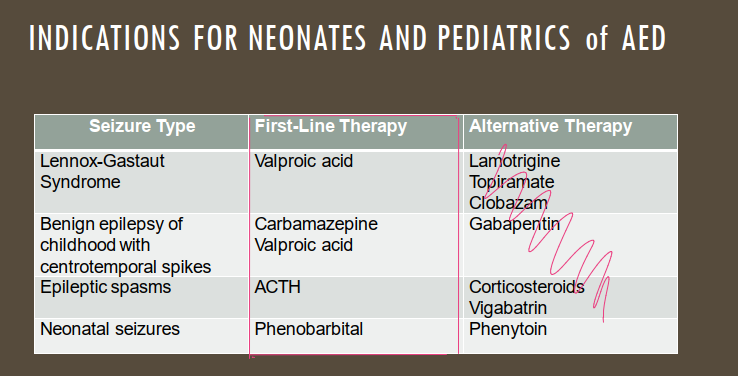
Bildverdeckung: nenne die verdeckten Beschriftungen
12
Therapeutic Drug Monitoring
❖ At the initiation of drug therapy
❖ During accelerated growth
❖ $\uparrow$ seizure or toxicity
❖ Other considerations
❖ During accelerated growth
❖ $\uparrow$ seizure or toxicity
❖ Other considerations
13
Infantile/Epileptic Spasms
● Definition: an epileptic disorder of infancy and early childhood
● Incidence: 2 to 3 cases per 10,000 live births
● Risk factors:
● Genetic predisposition
● Brain injury
● Typical onset: 4-8 months old but can happen after infancy (epileptic spasms)
● Pathophysiology of infantile spasms unknown
● Abnormalities in the hypothalamic-pituitary-adrenal axis are likely involved
14
Clinical Manifestations of Infantile Spasms
● West Triad:
○ Arrest of psychomotor development
○ Hypsarrhythmia
○ Spasms
● Infantile spasms involve a bilateral forward flexion of the arms and trunk
● Spasms typically occur in clusters of 2 to 100 within a minute
● Clusters generally occur upon waking up or before falling asleep
● Poor prognosis
● 50% of patients will experience seizures later in life
● 90% develop psychomotor retardation
15
Diagnosis of Infantile Spasms
EEG findings: hypsarrhythmia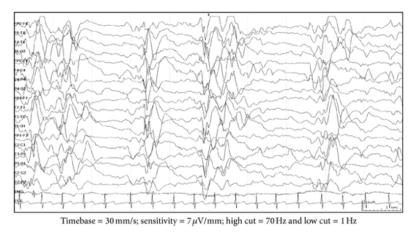
16
Adrenocorticotropic Hormone (ACTH)
First line for infantile spasms
MOA: Promotes the release of adrenal steroids, decreasing production of corticotropin-releasing hormone (CRH)
After 2 weeks of treatment, dosing is gradually tapered and discontinued over a 2-week period
AE: Increase in BP, risk of infection, fever, changes in mood/behavior, allergic reactions
Long term use: cardiac and cerebral hypertrophy
Effect on adrenal glands: decreased/increased cortisol
17
Vigabatrin (Sabril)
Place in Therapy:
•2nd-line for infantile spasms
Exception: patients with infantile spasms AND tuberous sclerosis complex (then used first line)
MOA: Irreversibly inhibits GABA transaminase (GABA-T), increasing GABA levels within the brain
AE: Skin rash, constipation, vomiting, diarrhea, drowsiness, irritability
BBW: Vision loss - REMS program
Administration: powder packets in 10 mL of water
18
Corticosteroids
The evidence is insufficient to recommend the use of prednisolone, dexamethasone, and methylprednisolone as being as effective as ACTH for short-term treatment of infantile spasms
19
Status Epilepticus (SE)
❖ 5 minutes or more of
Continuous clinical and/or electrographic seizure activity
OR
Recurrent seizure activity without recovery (returning to baseline) between seizures
❖ Classifications
Generalized convulsive SE (GCSE)
Non-convulsive SE (NCSE)
Refractory SE (RSE)
Continuous clinical and/or electrographic seizure activity
OR
Recurrent seizure activity without recovery (returning to baseline) between seizures
❖ Classifications
Generalized convulsive SE (GCSE)
Non-convulsive SE (NCSE)
Refractory SE (RSE)
20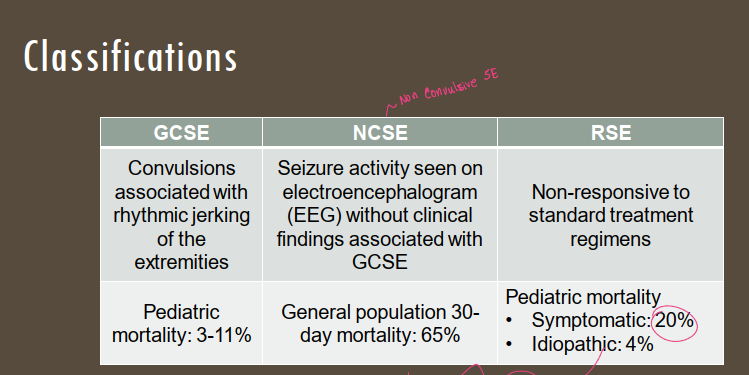
Bildverdeckung: nenne die verdeckten Beschriftungen
21
Bildverdeckung: nenne die verdeckten Beschriftungen
22
Bildverdeckung: nenne die verdeckten Beschriftungen
23
Bildverdeckung: nenne die verdeckten Beschriftungen
24
Bildverdeckung: nenne die verdeckten Beschriftungen
25
Bildverdeckung: nenne die verdeckten Beschriftungen
26
Potential Causes of SE: Pediatric Population
❖ Most common
Prolonged febrile seizures
❖ Frequent
CNS infections, especially bacterial meningitis
Inborn errors of metabolism
Rare genetic disorders affecting energy production
Ex: galactosemia, phenylketouria
Ingestion
Prolonged febrile seizures
❖ Frequent
CNS infections, especially bacterial meningitis
Inborn errors of metabolism
Rare genetic disorders affecting energy production
Ex: galactosemia, phenylketouria
Ingestion
27
Treatment Of SE: Stabilization
❖ Timeline: 0-5 minutes
❖ Interventions
1. Stabilize patient
2. Time seizure from its onset, monitor vital signs
3. Assess and address oxygenation
4. Initiation EEG monitoring
5. Collect finger stick blood glucose and address as needed
6. Attempt IV access and collect applicable labs
❖ Interventions
1. Stabilize patient
2. Time seizure from its onset, monitor vital signs
3. Assess and address oxygenation
4. Initiation EEG monitoring
5. Collect finger stick blood glucose and address as needed
6. Attempt IV access and collect applicable labs
28
Treatment Of SE: Initial Therapy
❖ Timeline: 5-20 minutes
❖ Benzodiazepines are the initial therapy of choice
Choose one of the following 3 equivalent first line options with dosing and frequency:
IM midazolam (Level A)
IV lorazepam (Level A)
IV diazepam (Level A)
❖ If none of the three options above are available, choose one of the following:
IV phenobarbital (Level A)
Rectal diazepam (Level B)
Intranasal or buccal midazolam (Level B)
29
Treatment Of SE: Second Therapy
❖ Timeline: 20-40 minutes
❖ No evidence based preferred second therapy of choice:
Choose one of the following second line options and give as a single dose
IV fosphenytoin (Level U)
IV valproic acid (Level B)
IV levetiracetam (Level U)
If none of the options above are available, IV phenobarbital is an alternative (Level B)
❖ No evidence based preferred second therapy of choice:
Choose one of the following second line options and give as a single dose
IV fosphenytoin (Level U)
IV valproic acid (Level B)
IV levetiracetam (Level U)
If none of the options above are available, IV phenobarbital is an alternative (Level B)
30
Treatment Of SE: Third Therapy
❖ Timeline: 40-60 minutes
❖ No clear evidence to guide therapy in this phase (Level U)
❖ Choices include:
Repeat second line therapy OR
Anesthetic doses of either midazolam, pentobarbital, or propofol
❖ No clear evidence to guide therapy in this phase (Level U)
❖ Choices include:
Repeat second line therapy OR
Anesthetic doses of either midazolam, pentobarbital, or propofol
31
Rectal Agents
Absorbed by the rectum’s blood vessels through the
gastrointestinal tract to the circulatory system
Rapidly absorbed to CNS due to richly vascular tissue of rectum
Some AEDs cannot be absorbed rectally due to poor
absorption/solubility (e.g. lorazepam)
Preferred agent: Diazepam (Diastat ®)
Onset: 2-10 minutes, Tmax: 5-20 minutes
Bioavailability: highly variable (50-100%)
Rectal instillation
32
Intranasal Agents
Delivers AED directly to the blood and cerebrospinal fluid via the nasal mucosa
Attributed to vascular tissue of nares
Rapid onset of action
Under ideal conditions, most medication absorbed and reaches cerebral cortex within 2-5 minutes
Attributed to vascular tissue of nares
Rapid onset of action
Under ideal conditions, most medication absorbed and reaches cerebral cortex within 2-5 minutes
33
Intranasal Diazepam (Valtoco)
Indication: > 6 years of age; Acute treatment of intermittent, stereotypic episodes offrequent seizure activity that are different from patient’s usual seizure pattern in patients with epilepsy
Contraindications
Hypersensitivity to diazepam
Acute narrow angle glaucoma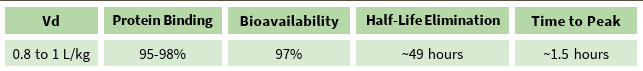
Contraindications
Hypersensitivity to diazepam
Acute narrow angle glaucoma
34
Intranasal Midazolam (Nayzilam)
Indication: > 12 years of age; acute treatment of intermittent, stereotypic episodes of frequent seizure activity that are different from patient’s usual seizure pattern in patients with epilepsy
Contraindications
Hypersensitivity to midazolam
Acute narrow angle glaucoma
Contraindications
Hypersensitivity to midazolam
Acute narrow angle glaucoma
35
Pediatric Febrile Seizures
❖ Febrile seizures are the most common neurologic disorder of children
Age-dependent phenomenon
Common between 14–18 months of age
May appear within 6 months and 5 years of age
Affects ≈ 2 - 4 percent of children < 5 years of age
❖ Up to 5% of children will have a febrile seizure in their life
1 of 3 children with a febrile seizures will have at least one more during childhood
36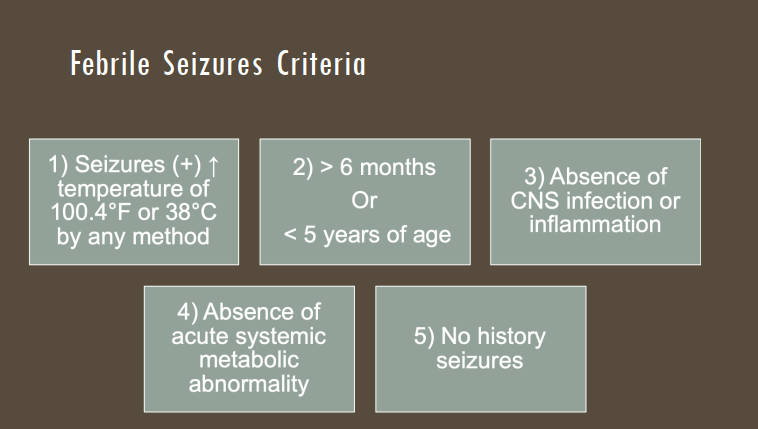
Bildverdeckung: nenne die verdeckten Beschriftungen
37
Bildverdeckung: nenne die verdeckten Beschriftungen
38
Bildverdeckung: nenne die verdeckten Beschriftungen
39
Bildverdeckung: nenne die verdeckten Beschriftungen
40
Bildverdeckung: nenne die verdeckten Beschriftungen
41
Bildverdeckung: nenne die verdeckten Beschriftungen
42
Bildverdeckung: nenne die verdeckten Beschriftungen
43
Bildverdeckung: nenne die verdeckten Beschriftungen
44
Bildverdeckung: nenne die verdeckten Beschriftungen
45
Bildverdeckung: nenne die verdeckten Beschriftungen
46
Bildverdeckung: nenne die verdeckten Beschriftungen
47
Bildverdeckung: nenne die verdeckten Beschriftungen
48
Bildverdeckung: nenne die verdeckten Beschriftungen
49
Bildverdeckung: nenne die verdeckten Beschriftungen
50
Bildverdeckung: nenne die verdeckten Beschriftungen
51
Clinical Features of Febrile Seizures
Appears on 1st day of illness; initial sign of illness w/ increased temperature.
Sudden tightening and contracting of muscles on both sides of the body: rhythmic jerking of body
Loss of control of bodily fluids
Vomiting
Bite their tongue
Cyanosis
Sudden tightening and contracting of muscles on both sides of the body: rhythmic jerking of body
Loss of control of bodily fluids
Vomiting
Bite their tongue
Cyanosis
52
Febrile Seizures Risk Factors
High fever, viral infection, and a family history of febrile seizures
53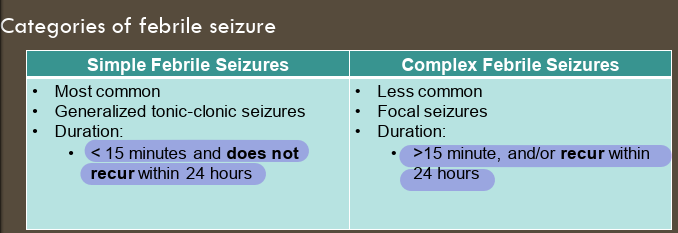
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Bildverdeckung: nenne die verdeckten Beschriftungen
55
Bildverdeckung: nenne die verdeckten Beschriftungen
56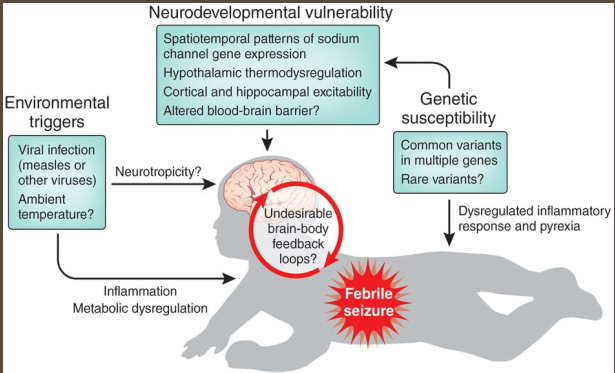
Bildverdeckung: nenne die verdeckten Beschriftungen
57
Bildverdeckung: nenne die verdeckten Beschriftungen
58
Bildverdeckung: nenne die verdeckten Beschriftungen
59
Bildverdeckung: nenne die verdeckten Beschriftungen
60
Bildverdeckung: nenne die verdeckten Beschriftungen
61
Bildverdeckung: nenne die verdeckten Beschriftungen
62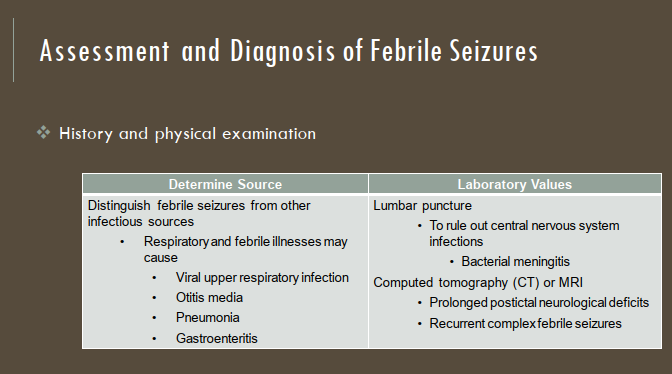
Bildverdeckung: nenne die verdeckten Beschriftungen
63
Bildverdeckung: nenne die verdeckten Beschriftungen
64
Bildverdeckung: nenne die verdeckten Beschriftungen
65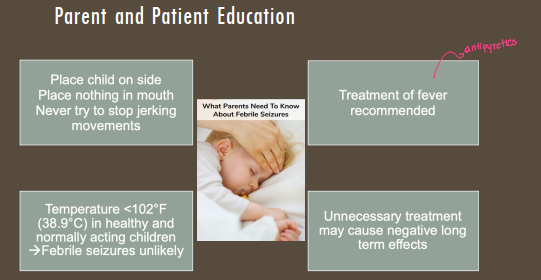
Bildverdeckung: nenne die verdeckten Beschriftungen
66
Bildverdeckung: nenne die verdeckten Beschriftungen
67
Bildverdeckung: nenne die verdeckten Beschriftungen
68
Bildverdeckung: nenne die verdeckten Beschriftungen
69
Bildverdeckung: nenne die verdeckten Beschriftungen
70
Bildverdeckung: nenne die verdeckten Beschriftungen
71
Bildverdeckung: nenne die verdeckten Beschriftungen
72
Bildverdeckung: nenne die verdeckten Beschriftungen
73
Bildverdeckung: nenne die verdeckten Beschriftungen
74
Bildverdeckung: nenne die verdeckten Beschriftungen
75
Risk Factors For Recurrence of Febrile Seizures
❖ Age at onset < 18 months
❖ History of febrile seizure in 1st degree relative
❖ Relatively low grade fevers associated with seizure
▪ <102.2 °F or 39°C
❖ Shorter duration of fever before seizure
▪ <1 hour
❖ Multiple seizures during the same febrile illness
❖ Day nursery attendance
❖ History of febrile seizure in 1st degree relative
❖ Relatively low grade fevers associated with seizure
▪ <102.2 °F or 39°C
❖ Shorter duration of fever before seizure
▪ <1 hour
❖ Multiple seizures during the same febrile illness
❖ Day nursery attendance
76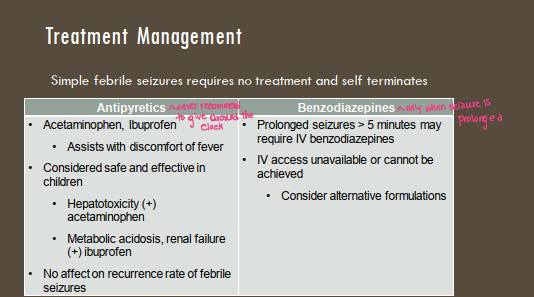
Bildverdeckung: nenne die verdeckten Beschriftungen
77
Bildverdeckung: nenne die verdeckten Beschriftungen
78
Bildverdeckung: nenne die verdeckten Beschriftungen
79
Prophylactic AEDs
Recurrent brief febrile seizures do not warrant treatment: increased risk factors $\rightarrow$ increased recurrence
No $\uparrow$ risk of brain injury
No benefit in preventing febrile seizures with intermittent medications
Prolonged or repetitive seizures despite BZDs: may be treated with additional AEDs; status epilepticus treatment
No $\uparrow$ risk of brain injury
No benefit in preventing febrile seizures with intermittent medications
Prolonged or repetitive seizures despite BZDs: may be treated with additional AEDs; status epilepticus treatment
Mehr Karteikarten: Medizin und Gesundheit
Blood supply to the brain and spinal cordMedizin und Gesundheit · EnglischSammieNeurotransmittersMedizin und Gesundheit · EnglischAdUvertMedicine typesMedizin und Gesundheit · EnglischNovaUnit 1 - Circulatory SystemMedizin und Gesundheit · EnglischAnantMedical Terminology J-RMedizin und Gesundheit · EnglischKayleeBiologyMedizin und Gesundheit · EnglischBaoGiardia lambliaMedizin und Gesundheit · EnglischJESSQTRANClinical Microscopy (P2 Fecalysis)Medizin und Gesundheit · EnglischMARIAAmniotic FluidMedizin und Gesundheit · EnglischJESSQTRANLiver DiseaseMedizin und Gesundheit · EnglischfaithSinnesfysiologi / NervcellenMedizin und Gesundheit · SchwedischAlilproRespiratory systemMedizin und Gesundheit · EnglischKayleigh
Alle Decks: Medizin und Gesundheit
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

