Household Poisons
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Risk factors for pediatric exposures
1. Ease of access
2. Climbing
3. Mouthing
4. Look like non-toxic items
2. Climbing
3. Mouthing
4. Look like non-toxic items
2
When is an ingestion considered “non-toxic”?
o Product is known to have low toxicity in amount ingested
o Details of the exposure are known (ideally witnessed)
Identification of active ingredients
Time, amount and route of exposure
Single substance only
o Patient is asymptomatic
o Examples of non-toxic or minimally toxic substances
Air fresheners, cosmetics, crayon/markers
Deodorant, glow sticks, lip balm
Sidewalk chalk, silica gel, superglue
3
CLEANING PRODUCTS
CAUSTICS
Caustic = xenobiotic → both functional + histologic damage on contact with tissues
Typically classified dichotomously (e.g. either acids or alkalis)
o Acids = proton donors (cause significant injury at pH <2)
o Alkalis = proton acceptors (cause significant injury at pH >12)
Extent on injury is determined by several factors
o pH
o Concentration
o Volume
o Formulation (liquid vs. solid)
o Duration/extent of contact with tissues
o Penetration coefficient
o Gastric contents (oral exposures)
o Titratable acid/alkaline reserve
4
Household caustics
o Acids
Hydrochloric (muriatic) acid: toilet bowl cleaners, mold/mildew removers
Oxalic acid: furniture refinishers, metal polishes
Phosphoric acid: toilet bowl cleaners, rust removers
Sulfuric acid: automobile batteries, drain opener
o Alkalis
Ammonium hydroxide: grease removers, glass cleaners, metal polishes/cleaners, hair dyes/tints, jewelry cleaners, wax removers, floor strippers
Sodium hydroxide (lye): paint removers, drain cleaners/openers, oven cleaners, automatic dishwasher detergents, hair relaxer
Sodium hypochlorite: bleach, swimming pool chlorinator
5
Epidemiology of Household Cleaner Poisoning
o Children
1,000 children hospitalized each year for an average of 4 days
Direct hospital costs: \$22 million
o Adolescents and adults
Intent = deliberate self-harm attempts
large volumes ingested
Clinical manifestations typically more severe
• Hospitalization rates: children 39% vs. adults 48%
• Require treatment: children 8% vs. adults 81%
o Worldwide
Public education campaigns
• Africa: sodium hydroxide stored in soda bottles
• Iran: 68.3% of unintentional exposure occurred in the kitchen
• Great Britain: direct ingestion of oven cleaning products/contaminated food
Difference in regulation = differences in access
• US: Federal Hazardous Substances Act + Poison Prevention Packaging Act
• Acid ingestions more common in Asia vs. western countries
o Taiwan: 48% of cases involved industrial cleaners
o Iran: hydrochloric acid accounts for 70% of caustic ingestions in adults
Suicide prevention resources
• China, India, Pakistan, Bangladesh, Sri Lanka: women commonly use caustics to commit suicide
• Tunisia: majority of caustic ingestions occurred in women 20-29 years old
6
Alkalis vs. acids
o Alkalis: dissociated hydroxide ions (OH-) → liquefactive necrosis
Protein dissolution, collagen destruction, fat saponification
Cell membrane emulsification, transmural thrombosis, cell death
continuous penetration until OH- neutralized by the tissues
o Acids: dissociated H+ ions → coagulative necrosis
Edema, erythema, mucosal sloughing, ulceration and necrosis
eschar formation = prevents deeper tissue penetration
7
Clinical manifestations of cleaning product toxicity
o All routes of exposure: severe pain at site (lips, mouth, throat, abdomen, eyes, skin)
o Ocular: vision changes, redness, ulceration
o Dermal: local tissue damage, vesicle formation
o Pulmonary: dyspnea, respiratory compromise, pneumonitis, pulmonary edema
o Gastrointestinal
Oropharyngeal: edema + burns, excessive salivation
Esophageal: dysphagia, odynophagia
Gastric: epigastric pain, hematemesis
Complications: sepsis, perforation, stricture formation + narrowing of lumen
8
Diagnosis of cleaning product toxicity
o Laboratory evaluation (limited clinical utility, can aid in planning)
Basic metabolic panel
Serum pH, lactic acid (metabolic acidosis ± anion gap – including alkali ingestions)
CBC, coagulation panel, blood typing + cross-match
o Imaging
Chest + abdominal radiographs (detect gross esophageal or gastric perforation + strictures)
Endoscopy for all intentional ingestions or unintentional + stridor or >2 (pain, vomiting, drooling)
Ideally should be performed within 12 hours of ingestion (no later than 24 hours)
Should visualize esophagus, stomach + proximal duodenum
If grade IIb or III esophageal burns prevent endoscopy → CT or surgical exploration
9
Management of cleaning product toxicity
o Decontamination (oral and dermal exposures)
Remove clothing, jewelry, etc. + copious irrigation with water
Blisters should be popped
No role for gastric decontamination (activated charcoal, induction of emesis, etc.)
Dilutional therapy (e.g. drinking water): avoid unless asymptomatic + within first few first few minutes of ingestion
o Symptomatic and supportive care
Basic resuscitative principles: airway inspection and intubation
Airway inflammation: dexamethasone
Hypotension (third spacing or perforation): IV fluid repletion
Surgical intervention as necessary
No role for empiric antibiotics (only if source of infection is identified)
10
Ocular exposures to Cleaning Supplies
o Remove contact lenses, false eye lashes, etc.
o Immediate + copious irrigation
Hold eyes open for continuous irrigation for at least 15 minutes
Use room temperature (tepid) water or 0.9% sodium chloride
• Tilt head to the side and pour water over bridge of nose
• “Burrito method” in children: place arms at their sides and wrap in towel
o Some situations warrant hospital evaluation/care
Refer if: strong or concentrated caustic or pain, swelling, lacrimation, or photophobia despite irrigation
At healthcare facility
• Test pH of fluid in conjunctival sac (litmus paper) – goal pH 7
• Specially designated lenses placed below the eyelids that enable direct flushing (+ local anesthetic)
11
Hydrofluoric Acid
Liberation of F- ions leads to toxicity (not H+)
12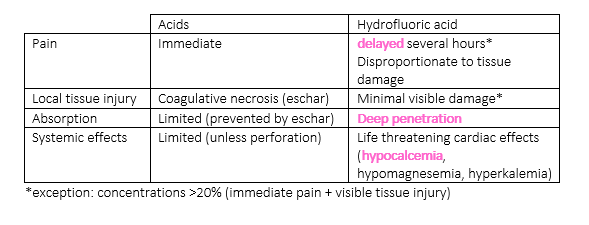
Bildverdeckung: nenne die verdeckten Beschriftungen
13
Bildverdeckung: nenne die verdeckten Beschriftungen
14
Bildverdeckung: nenne die verdeckten Beschriftungen
15
Bildverdeckung: nenne die verdeckten Beschriftungen
16
Bildverdeckung: nenne die verdeckten Beschriftungen
17
Clinical manifestations of Hydrofluoric Acid Toxicity
Unintentional (dermal, ocular)
• Dermal: blanching, coagulative necrosis (>20%)
• Ocular: stromal corneal edema, conjunctival ischemia, sloughing, long term dry eye
• Pulmonary: throat burning, shortness of breath, ulceration, pulmonary edema
Intentional (oral)
• Almost invariably fatal
• Precipitous deterioration
• Gastrointestinal: significant gastritis, vomiting, abdominal pain
• Cardiac: hypocalcemia + hypomagnesemia + hyperkalemia → ventricular dysrhythmias
18
Management of Hydrofluoric Acid Toxicity
Decontamination (water or saline)
Airway management
• Especially if: inhalation or ingestions, vomiting or respiratory distress, altered mental status
• Avoid succinylcholine (hyperkalemia)
Pain control
• Topical calcium gluconate gels (commercially available or compounded)
• Avoid sedating analgesics (sedation is marker of systemic toxicity)
• Nebulized calcium for pulmonary exposures (4 mL 2.5% or 5% calcium gluconate solution)
Electrolyte repletion: calcium + magnesium
• Administer orally ASAP to prevent penetration (milk, calcium carbonate)
• Immediate IV repletion for severe toxicity: gluconate > chloride?
19
HYPOCHLORITES
Hypochlorite: aqueous solution formed by reaction of chlorine gas + water
Household bleach (3-5% sodium hypochlorite)
o Mechanism of toxicity: local irritant
o Clinical manifestations: mild-moderate irritation with no further injury expected (GI tract, eyes)
o Management: dilute with water (copious irrigation with tepid water in ocular exposures)
Industrial strength cleaners/swimming pool disinfectants (up to 20% hypochlorite)
o Mechanism of toxicity: corrosive
o Clinical manifestations: serious corrosive injury, dysphagia, severe pain, hematemesis, perforation
o Diagnosis: flexible endoscopy, chest and abdominal x-ray
o Management: symptomatic and supportive care
20
Combination of products
o Hypochlorite + acid = chlorine gas
o Hypochlorite + ammonia = chloramine gas
o Chlorine and chloramine are both irritant gases
Chlorine dissolution → hydrochloric acid + hypochlorous acid
Chloramine dissolution → hypochlorous acid + ammonia + oxygen radicals
o Affect moist mucus membranes (eyes, lungs, throat)
o Higher water solubility = faster time to symptoms onset: chlorine > chloramine
Dyspnea, wheezing, bronchospasm
Pulmonary edema
21
Management of Hypochlorite Toxicity
o Management: fresh air (supplemental oxygen/bronchodilators as needed)
22
DETERGENTS
3 major types: nonionic, anionic + cationic
Typically made up of 3 major components
o Soluble alkali salt: removes dirt + grease
o Surfactant: disperse grease into water
o Enzymatic agent: degrades stains and soils
Typically made up of 3 major components
o Soluble alkali salt: removes dirt + grease
o Surfactant: disperse grease into water
o Enzymatic agent: degrades stains and soils
23
Detergent Mechanism of toxicity
o Anionic and nonionic detergents: local tissue irritants
o Cationic detergents: precipitate and denature proteins
Quaternary ammonium compounds: keratolytic and corrosive effects
o Enzyme-containing detergents: release bradykinin + histamine → bronchospasm
o Cationic detergents: precipitate and denature proteins
Quaternary ammonium compounds: keratolytic and corrosive effects
o Enzyme-containing detergents: release bradykinin + histamine → bronchospasm
24
Clinical manifestations of Detergent Toxicity
o Vary based on active ingredients + concentration
o Serious morbidity and mortality are rare (cationic + dishwasher detergents = more dangerous)
o Gastrointestinal: vomiting, diarrhea, hematemesis, corrosive injuries (upper GI tract)
o Ocular exposures: mild to serious corrosive injury
o Serious morbidity and mortality are rare (cationic + dishwasher detergents = more dangerous)
o Gastrointestinal: vomiting, diarrhea, hematemesis, corrosive injuries (upper GI tract)
o Ocular exposures: mild to serious corrosive injury
25
Diagnosis of Detergent Toxicity
o Endoscopy if suspect corrosive injuries to GI tract
o CXR for pulmonary symptoms
o CXR for pulmonary symptoms
26
Management of Detergent Toxicity
o Decontamination: dilute with water or milk (water or saline only for ocular exposures)
o Symptomatic and supportive care
o Symptomatic and supportive care
27
Single-use detergent sacs
o Highly concentrated detergents surrounded by polyvinyl alcohol film
Usually contain: nonionic + anionic surfactants, fatty acids, ethanol, propylene glycol
o Mechanism of toxicity
Concentrated surfactants → irritant + corrosive
Propylene glycol, ethanol → CNS depression (especially in children)
o Clinical manifestations
Gastrointestinal: vomiting, diarrhea, esophageal/stomach burning + ulceration
Pulmonary: aspiration, pneumonitis, pulmonary edema, respiratory depression/failure, ARDS
CNS: CNS depression ranging from drowsiness → coma, seizures
Ocular: pain/irritation, conjunctivitis, corneal abrasions, ocular burns
Metabolic: metabolic acidosis, hyperlactatemia
28
HYDROGEN PEROXIDE (H2O2)
Oxidizer with weak antiseptic properties
o Household uses: mouth gargles, local wound care, hair bleaching
o Industrial uses: produce washing, bleaching textiles/wool, foam rubber/rocket fuel production
Generally available in 2 strengths
o Commercial/household (3-9%)
o Industrial use (27.5-70%)
o 35% solutions available from health food stores (“hyperoxygenation”)
29
H2O2 Mechanism of Toxicity
o Extent of injury/gas formation is determined by concentration of H2O2
o Local tissue injury
Low concentrations: irritant
High concentrations: corrosive
o Gas formation
H2O2 interacts with tissue catalase → O2 + H2O liberation
1 mL of 3% H2O2 → 10 mL O2 vs. 1 mL 35% H2O2 → >100 mL O2
o Local tissue injury
Low concentrations: irritant
High concentrations: corrosive
o Gas formation
H2O2 interacts with tissue catalase → O2 + H2O liberation
1 mL of 3% H2O2 → 10 mL O2 vs. 1 mL 35% H2O2 → >100 mL O2
30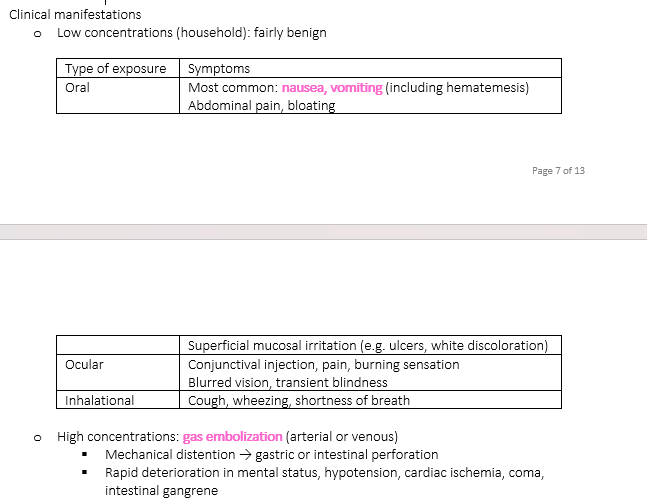
Bildverdeckung: nenne die verdeckten Beschriftungen
31
Bildverdeckung: nenne die verdeckten Beschriftungen
32
Bildverdeckung: nenne die verdeckten Beschriftungen
33
Bildverdeckung: nenne die verdeckten Beschriftungen
34
Bildverdeckung: nenne die verdeckten Beschriftungen
35
Bildverdeckung: nenne die verdeckten Beschriftungen
36
Diagnosis of H2O2 Toxicity
o Focused on detection of local tissue damage and gas embolism
o Local tissue damage (only if symptoms warrant)
Investigate if presentation consistent with esophageal, gastric or intestinal injury
Endoscopy
o Gas embolism
CXR (for gas on cardiac chambers, mediastinum + pleural space)
Abdominal x-ray (for gas in GI tract or portal system, also defines extent of bowel distention)
MRI or head CT (for brain and/or spinal cord lesions) – for any neurologic symptoms
37
Management of H2O2 Toxicity
o Low concentrations can usually be managed at home
Dilute with water (oral and ocular exposures)
Remove contaminated clothing + jewelry
o High concentrations require immediate evaluation
Decontamination
• Oral exposures: No role for gastric decontamination
• Ocular exposures: copious irrigation with tepid water
Monitor airway and intubate as needed
Trendelenburg position if evidence of gas in the heart
Consider gastric suctioning in setting of abdominal distention
Life threatening gas emboli: hyperbaric oxygen
38
ETHANOL
Found in a variety of household products
o Mouthwash (up to 75%)
o Hand sanitizer, rubbing alcohol (60-95%)
o Colognes, perfumes, aftershaves (40-60%)
o Food flavoring extracts (e.g. vanilla, almond, lemon) (~35%)
o Mouthwash (up to 75%)
o Hand sanitizer, rubbing alcohol (60-95%)
o Colognes, perfumes, aftershaves (40-60%)
o Food flavoring extracts (e.g. vanilla, almond, lemon) (~35%)
39
Ethanol Mechanism of toxicity
o Enhanced GABA effects + NMDA receptor blockade
o Oxidation of ethanol → ↑ acetyl-CoA + change in redox potential → hypoglycemia
More common in children and malnourished patients
o Oxidation of ethanol → ↑ acetyl-CoA + change in redox potential → hypoglycemia
More common in children and malnourished patients
40
Clinical manifestations of Ethanol Toxicity
o CNS depressant at low doses, general depressant at high doses (e.g. respiratory depressant)
o Hypoglycemia, vomiting
o Hypoglycemia, vomiting
41
Diagnosis of Ethanol Toxicity
o Majority of cases require observation only
o Changes in mental status → hospital evaluation
Serum ethanol
Complete metabolic panel (including blood glucose)
Head CT if altered mental status is inconsistent with measured serum ethanol
o Changes in mental status → hospital evaluation
Serum ethanol
Complete metabolic panel (including blood glucose)
Head CT if altered mental status is inconsistent with measured serum ethanol
42
Management of Ethanol Toxicity
o Symptomatic and supportive
CNS/respiratory depression: intubate as needed
Chronic EtOH abuse: thiamine, folic acid, fluid repletion, dextrose
o Hypoglycemia: dextrose supplementation as needed (sugary beverages)
CNS/respiratory depression: intubate as needed
Chronic EtOH abuse: thiamine, folic acid, fluid repletion, dextrose
o Hypoglycemia: dextrose supplementation as needed (sugary beverages)
43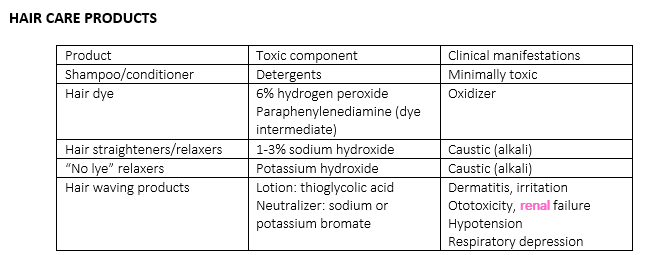
Bildverdeckung: nenne die verdeckten Beschriftungen
44
Bildverdeckung: nenne die verdeckten Beschriftungen
45
Bildverdeckung: nenne die verdeckten Beschriftungen
46
Bildverdeckung: nenne die verdeckten Beschriftungen
47
Bildverdeckung: nenne die verdeckten Beschriftungen
48
NAIL CARE PRODUCTS
Nail polish
o Ingredients: Butyl acetate, ethyl acetate
o Generally considered non-toxic in small amounts
Nail polish remover
o Ingredients: acetone, isopropanol
o CNS depression ± hypoglycemia → sugary beverage
Artificial nail remover
o Ingredient: acetonitrile (endogenously converted to cyanide)
o Automatic 24-hour hospital observation (symptoms can be delayed 8-14 hours)
Mild: nausea, vomiting, headache
Severe: weakness, respiratory depression, seizures, acidosis, shock, coma
49
DENTAL CARE PRODUCTS
Toothpaste
o Ingredient of concern: fluoride
o Requires enormous ingestion to cause toxicity (1 mg fluoride per gram of toothpaste)
o Limited to GI effects: nausea, vomiting, diarrhea
o Give milk (calcium will bind fluoride)
Denture cleaning tablets
o Ingredients: citric acid, sodium bicarbonate, borates
o Single, acute ingestion usually benign: nausea, vomiting, diarrhea (greenish-blue color)
o Chronic or large ingestions: dehydration, hypotension, lethargy, seizures, renal failure
Mouthwash
o Ethanol – previously covered
50
BATTERIES
Traditional lithium batteries = not a problem
o Treat like a foreign body: screen stool for passage of battery
button batteries (watches, hearing aids, cameras, etc.) = serious problem
o Contain caustic metal salts (mercuric chloride) leak
o Local discharge of electrical current
Obtain x-ray to localize
o Esophagus: emergent removal by endoscopy
o Stomach of intestine: only remove if signs of obstruction or perforation
51
MAGNETS
Single magnet = not a problem
o Manage as a foreign body ingestion at home
o Screen stool for passive of magnet
2 magnets or 1 magnet + metallic object= referral to healthcare facility
o Neodymium magnets are 10x stronger than other household magnets
o Attraction of adjacent magnets through different bowel loops obstruction or
Radio-opaque nature slows for easy detection
o X-ray: may need multiple views to determine if >1 magnet is ingested
Removal of the foreign bodies
o Endoscopic removal
o Surgery
52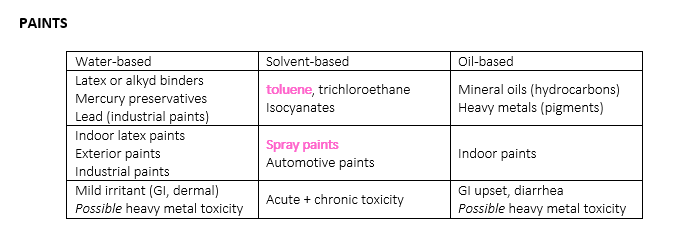
Bildverdeckung: nenne die verdeckten Beschriftungen
53
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Solvent-based paints: abuse potential
o Sniffing: inhalation directly from container
o Huffing: pour substance onto fabric and place over mouth/nose
o Bagging: instill solvent into plastic or paper bag and rebreathe from the bag
o Huffing: pour substance onto fabric and place over mouth/nose
o Bagging: instill solvent into plastic or paper bag and rebreathe from the bag
55
Bildverdeckung: nenne die verdeckten Beschriftungen
56
Sudden sniffing death syndrome
o Reports began in the 1960s of sudden cardiac arrest in young, otherwise healthy patients
o Common factor: inhalant use + sudden physical activity → death
o No other anatomical explanation for deaths
o Common factor: inhalant use + sudden physical activity → death
o No other anatomical explanation for deaths
57
Paint Mechanisms of Toxicity
o CNS
enhance GABAA receptor effects
Inhibit NMDA mediated current (dose dependent)
o Cardiac
Increased sensitivity or myocardium to epinephrine
Slow repolarization/conduction (Na, Ca, K channels)
o Pulmonary
Aspiration → direct pulmonary necrosis/inflammation
Ventilation/perfusion mismatch → hypoxia + bronchospasm
o Renal
metabolite → metabolic acidosis (hippuric acid)
Oxidative stress → proximal tubule dysfunction
58
Paint Clinical Manifestations
o CNS
Stage 1: euphoria → excitability, disinhibition + impulsive behavior
Stage 2: CNS depression (slurred speech, confusion, weakness) + hallucinations, tremors
Stage 3: seizures, coma, death
o Pulmonary: respiratory depression
o Cardiac: arrhythmias, brady-asystolic arrest
o Renal: renal dysfunction
o Dermal: irritation -> frostbite, perioral eczema
o Chronic abuse: muscle weakness, tremor, spasticity, peripheral neuropathy, mood changes, loos of coordination, gait disturbances, dementia, learning impairments
59
Paint Toxicity Management
o Gastrointestinal decontamination: no role (risk of aspiration > benefits)
o Airway management
Observe for symptom development for 6 hours
Symptoms usually = admission (unpredictable progression of symptoms)
No need for routine use of antibiotics or steroids
o Arrhythmias
Potential role for short-acting beta blockade
Avoid exogenous catecholamines in acute exposures (can precipitate arrhythmias)
o Electrolyte replacement
o Benzodiazepines for seizures/agitation
60
MOTHBALLS
Contain one of 3 main ingredients
o Paradichlorobenzene (most common in United States)
o Naphthalene (traditional mothballs – e.g. Enoz)
o Camphor (use restricted to Japan)
Difficult to distinguish based on appearance, odor, texture or size
Paradichlorobenzene
o Ingestions are usually innocuous + managed at home (exception: massive ingestions)
o Clinical manifestations: nausea, vomiting, headache
o Management: dilute with water (no milk – will enhance absorption), antiemetics if needed
Naphthalene
o Ingestion of >1 mothball must be referred to healthcare facility
o Mechanism of toxicity: oxidant stress hemolysis + methemoglobinemia
o Clinical manifestations: nausea, vomiting, lethargy, seizures, methemoglobinemia, hemolysis
Hemolysis + methemoglobinemia become clinically evident 24-72 hours post-ingestion → anemia (3-5 days)
Methemoglobinemia + hemolysis: tachycardia, tachypnea, cyanosis, jaundice, weakness, altered mental status
o Management: consider transfusion (packed red blood cells), methylene blue (1-2 mg/kg IV)
Camphor
o Ingestions >30 mg/kg must be referred to healthcare facility
o Mechanism of toxicity: unknown
o Clinical manifestations: nausea, vomiting, confusion, tremors, seizures
o Management: symptomatic + supportive, benzos → propofol, barbiturates
Mehr Karteikarten
First 20 Chemical ElementsNaturwissenschaften · LateinLukeMilady Chapter 8: Hair and Scalp Disorders and DiseasesEnglischSkippStudy Guide AnswersGeschichte und Geisteswissenschaften · Englischmrwright07New Hemolytic Analyzers (Hema Part 2)EnglischMARIAhistory Geschichte und Geisteswissenschaften · Englischaudreysurveillance at the abbatoirEnglischRosieSpectrumsEnglischBroccoliniProperty Quiz QuizletEnglischSamBook idiomsSprachen · Russisch → Englischanya€Act 2 scene 2Geschichte und Geisteswissenschaften · EnglischHassanPHRca Flashcards Full Set (Terms 1-205)EnglischKevinSoftware Engineering: Use CasesInformatik · EnglischJay
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

