Opioid-Related Disorders
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Narcotic
comes from Greek word stupor and originally referred to as a variety of substances that dulled the senses and relieved pain
2
Opioid
Opioid: natural, synthetic, or semi-synthetic chemicals that interact with opioid receptors on nerve cells in the body and brain and reduce pain signals
Opiate: naturally occurring opioid ex. Morphine, codeine
Semi-synthetic: Heroin, oxycodone
Synthetic: fentanyl, methadone
Opiate: naturally occurring opioid ex. Morphine, codeine
Semi-synthetic: Heroin, oxycodone
Synthetic: fentanyl, methadone
3
DSM-5: Opioid-Related Disorders
Opioid Intoxication
Opioid Withdrawal
Opioid Use Disorder
Opioid Withdrawal
Opioid Use Disorder
4
DSM-5: Opioid Intoxication
Recent use of an opioid.
Clinically significant problematic behavioral or psychological changes that developed during, or shortly after, opioid use.
Pupillary constriction and one (or more) of the following signs or symptoms developing during, or shortly after, opioid use:
Drowsiness or coma.
Slurred speech.
Impairment in attention or memory.
The signs or symptoms are not attributable to another condition or intoxication with another substance
5
DSM-5: Opioid Withdrawal
Presence of either of the following:
Cessation of (or reduction in) opioid use that has been heavy and prolonged (i.e., several weeks or longer).
Administration of an opioid antagonist after a period of opioid use.
Three (or more) of the following developing within minutes to several days after Criterion A:
Dysphoric mood.
Nausea or vomiting.
Muscle aches.
Lacrimation or rhinorrhea.
Pupillary dilation, piloerection, or sweating.
Diarrhea.
Yawning.
Fever.
Insomnia
6
DSM-5: Opioid-Use Disorder
A problematic pattern of opioid use leading to clinically significant impairment or distress, as manifested by at least two of the following, occurring within a 12-month period:
11 symptoms in total, highlights seen below:
Opioid are often taken in larger amounts or over a longer period than was intended
Unsuccessful efforts to cut down or control opioid use
Cravings
Recurrent opioid use resulting in a failure to fulfill major role obligations
Tolerance
Withdrawal
11 symptoms in total, highlights seen below:
Opioid are often taken in larger amounts or over a longer period than was intended
Unsuccessful efforts to cut down or control opioid use
Cravings
Recurrent opioid use resulting in a failure to fulfill major role obligations
Tolerance
Withdrawal
7
Etiology and Pathophysiology
Multifaceted
Biological
Environmental
Genetic
Psychosocial factors
Biological
Environmental
Genetic
Psychosocial factors
8
Racial Disparities
Black patients are half as likely to obtain follow up appointments for opioid use disorder care after discharge from the emergency room
Death Rates
Opioid overdose death rates have increased in black populations while leveling off in other populations
Access to Care
Counties with more black and Hispanic communities had more methadone clinics per capita
Counties with more white communities had more buprenorphine use per capita
Death Rates
Opioid overdose death rates have increased in black populations while leveling off in other populations
Access to Care
Counties with more black and Hispanic communities had more methadone clinics per capita
Counties with more white communities had more buprenorphine use per capita
9
Naloxone
Class:
Opioid antagonist
Place in therapy:
Opioid overdose
Mechanism of action:
Competitive antagonist at opioid receptors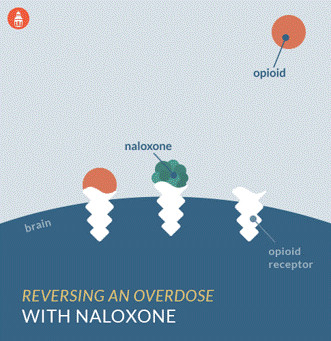
Opioid antagonist
Place in therapy:
Opioid overdose
Mechanism of action:
Competitive antagonist at opioid receptors
10
Naltrexone
Class:
Opioid antagonist
Place in therapy:
Opioid use disorder
Alcohol use disorder
Mechanism of action:
Antagonist at opioid receptors
Dosing:
Naltrexone tablet (Revia®): 50 mg oral daily
Naltrexone LAI (Vivitrol®): 380 mg IM every 4 weeks
Onset of action:
Can work within a few days, but maximum effects may not be seen for a few weeks
Pharmacokinetics:
Extensive first pass metabolism but the major metabolite (6-beta-naltrexol) is active
11
Buprenorphine
Class:
Opioid
Place in therapy:
Opioid withdrawal
Opioid use disorder
Mechanism of action:
Mu-opioid partial agonist
Only start if the patient is already in withdrawal (*at standard dosing), otherwise may cause withdrawal symptoms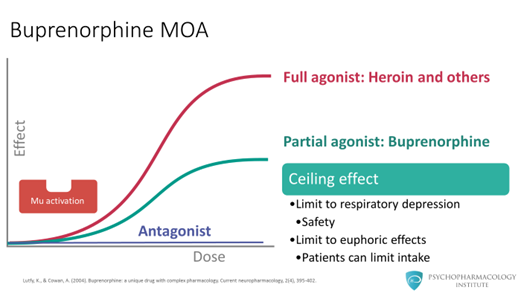
Opioid
Place in therapy:
Opioid withdrawal
Opioid use disorder
Mechanism of action:
Mu-opioid partial agonist
Only start if the patient is already in withdrawal (*at standard dosing), otherwise may cause withdrawal symptoms
12
Buprenorphine and Naloxone Combination
Class:
Opioid
Place in therapy:
Opioid withdrawal
Opioid use disorder
Mechanism of action:
Mu-opioid partial agonist and mu-opioid antagonist
Dosing:
Buprenorphine/naloxone sublingual (Suboxone®): 2/0.5 mg – 32/8 mg films and tablets
Buprenorphine/naloxone sublingual (Zubsolv®): 0.7/0.18 mg – 11.4/2.9 mg tablets
Onset of action:
Depends on product used
Pharmacokinetics:
Depends on product used
Side effects
Constipation
Headache
Nausea
Contraindications
Hypersensitivity
13
Methadone
Class:
Opioid
Place in therapy:
Opioid withdrawal
Opioid use disorder
Mechanism of action:
Mu-opioid agonist
Dosing:
2.5 – 120 mg oral concentrate daily
Onset of action:
0.5 – 2 hours
Pharmacokinetics:
Duration of action 24 – 36 hours for cravings
Side effects
Dizziness
Lightheadedness
Nausea/vomiting
Sweating
Contraindications
Acute or severe asthma
Paralytic ileus
Respiratory depression
14
Lofexidine (Lucemyra)
Alpha-2 receptor agonist
Less side effects than clonidine
hypotension, fatigue and weakness
Less side effects than clonidine
hypotension, fatigue and weakness
15
Opioid intoxication/overdose guidelines
First line — APA and ASAM recommend Naloxone
16
Bildverdeckung: nenne die verdeckten Beschriftungen
17
Bildverdeckung: nenne die verdeckten Beschriftungen
18
Bildverdeckung: nenne die verdeckten Beschriftungen
19
Bildverdeckung: nenne die verdeckten Beschriftungen
20
Bildverdeckung: nenne die verdeckten Beschriftungen
21
Bildverdeckung: nenne die verdeckten Beschriftungen
22
Bildverdeckung: nenne die verdeckten Beschriftungen
23
Bildverdeckung: nenne die verdeckten Beschriftungen
24
Bildverdeckung: nenne die verdeckten Beschriftungen
25
Bildverdeckung: nenne die verdeckten Beschriftungen
26
Clinical Opiate Withdrawal Scale
5-12 mild; 13-24 moderate; 25-36 moderately severe; 36+ severe withdrawal
27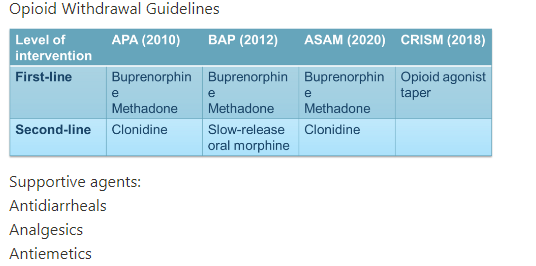
Bildverdeckung: nenne die verdeckten Beschriftungen
28
Bildverdeckung: nenne die verdeckten Beschriftungen
29
Bildverdeckung: nenne die verdeckten Beschriftungen
30
Bildverdeckung: nenne die verdeckten Beschriftungen
31
Bildverdeckung: nenne die verdeckten Beschriftungen
32
Bildverdeckung: nenne die verdeckten Beschriftungen
33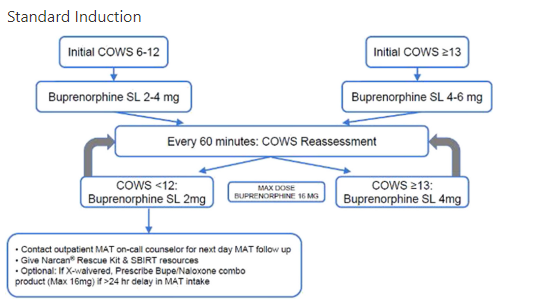
Bildverdeckung: nenne die verdeckten Beschriftungen
34
Bildverdeckung: nenne die verdeckten Beschriftungen
35
Bildverdeckung: nenne die verdeckten Beschriftungen
36
Bildverdeckung: nenne die verdeckten Beschriftungen
37
Bildverdeckung: nenne die verdeckten Beschriftungen
38
Bildverdeckung: nenne die verdeckten Beschriftungen
39
Bildverdeckung: nenne die verdeckten Beschriftungen
40
Bildverdeckung: nenne die verdeckten Beschriftungen
41
Bildverdeckung: nenne die verdeckten Beschriftungen
42
Bildverdeckung: nenne die verdeckten Beschriftungen
43
Bildverdeckung: nenne die verdeckten Beschriftungen
44
Bildverdeckung: nenne die verdeckten Beschriftungen
45
Bildverdeckung: nenne die verdeckten Beschriftungen
46
Bildverdeckung: nenne die verdeckten Beschriftungen
47
Bildverdeckung: nenne die verdeckten Beschriftungen
48
Bildverdeckung: nenne die verdeckten Beschriftungen
49
Bildverdeckung: nenne die verdeckten Beschriftungen
50
Bildverdeckung: nenne die verdeckten Beschriftungen
51
Bildverdeckung: nenne die verdeckten Beschriftungen
52
Bildverdeckung: nenne die verdeckten Beschriftungen
53
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Bildverdeckung: nenne die verdeckten Beschriftungen
55
Bildverdeckung: nenne die verdeckten Beschriftungen
56
Bildverdeckung: nenne die verdeckten Beschriftungen
57
Bildverdeckung: nenne die verdeckten Beschriftungen
58
Bildverdeckung: nenne die verdeckten Beschriftungen
59
Bildverdeckung: nenne die verdeckten Beschriftungen
60
Bildverdeckung: nenne die verdeckten Beschriftungen
61
Bildverdeckung: nenne die verdeckten Beschriftungen
62
Bildverdeckung: nenne die verdeckten Beschriftungen
63
Bildverdeckung: nenne die verdeckten Beschriftungen
64
Bildverdeckung: nenne die verdeckten Beschriftungen
65
Bildverdeckung: nenne die verdeckten Beschriftungen
66
Bildverdeckung: nenne die verdeckten Beschriftungen
67
Bernese Method
consists of initiating a low dose of 0.2 mg sublingual buprenorphine and slowly increasing the dose while continuing full opioid agonist therapy. Once buprenorphine has reached a sufficient dose, the full opioid agonist is discontinued without tapering.
68
Microinduction Protocol
method that includes starting with a low dose of buprenorphine that overlaps with other opioid use. The small buprenorphine dose increases over time and then tapering or cessation of opioid use at sufficient dose of buprenorphine (or sometimes an abrupt cessation). The goal is to transition patients to buprenorphine therapy without opioid withdrawal.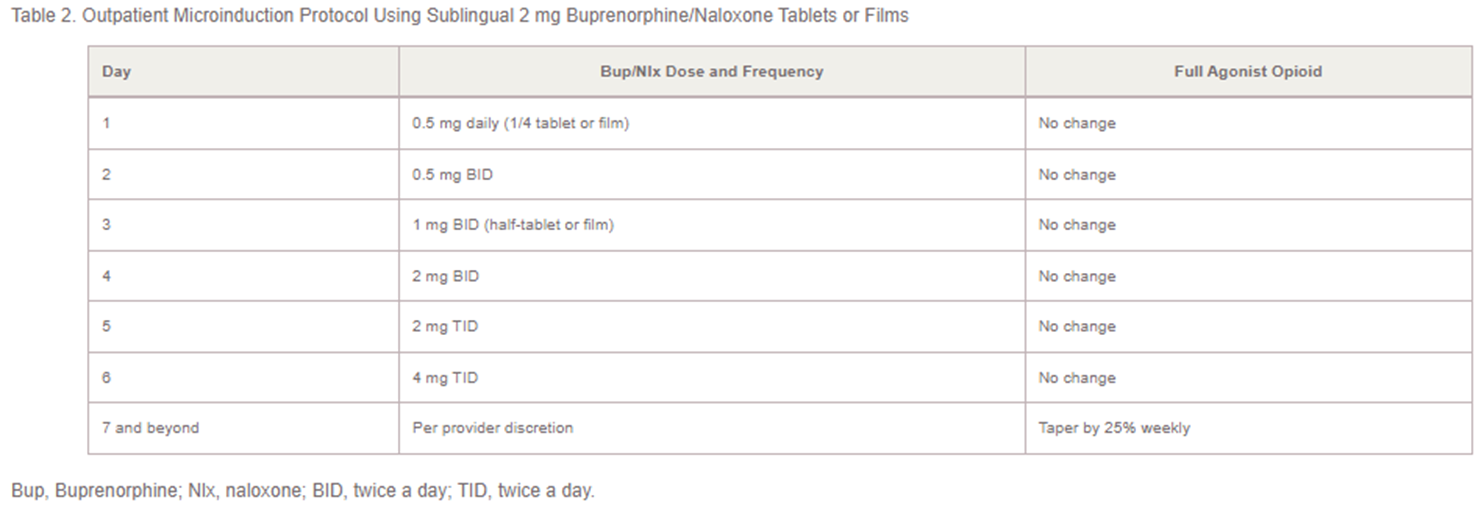
69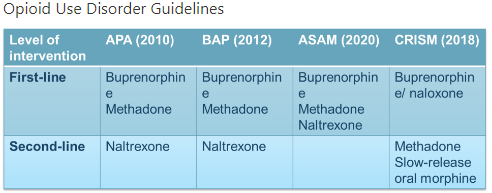
Bildverdeckung: nenne die verdeckten Beschriftungen
70
Bildverdeckung: nenne die verdeckten Beschriftungen
71
Bildverdeckung: nenne die verdeckten Beschriftungen
72
Practical Guidance for OUD
Provide low threshold rapid access to treatment
Provide non-punitive care
Check the Prescription Monitoring Program (PMP)
Provide non-punitive care
Check the Prescription Monitoring Program (PMP)
73
Harm Reduction
Reduces the risks of addiction
Maintains physiological need for opioid agonism
Maintains physiological need for opioid agonism
74
Naloxone Statistics
A study in Massachusetts showed
No difference in rates of opioid-related emergency department visits
No difference in hospital admissions in communities with low or high implementation of overdose education and naloxone distribution programs
Naloxone distribution programs were shown to:
prevent overdose deaths,
increase quality-adjusted life years (QALYs)
be highly cost-effective.
naloxone distribution was predicted to prevent 6 percent of overdose deaths
75
Cost Effectiveness of Treatments for Opioid Use Disorder
All forms of medications for the treatment of opioid use disorder were associated with cost savings compared with no treatment
\$25,000 – \$105,000 savings in lifetime costs per patient
\$25,000 – \$105,000 savings in lifetime costs per patient
76
Healthcare Professionals Perspectives
Generally negative
77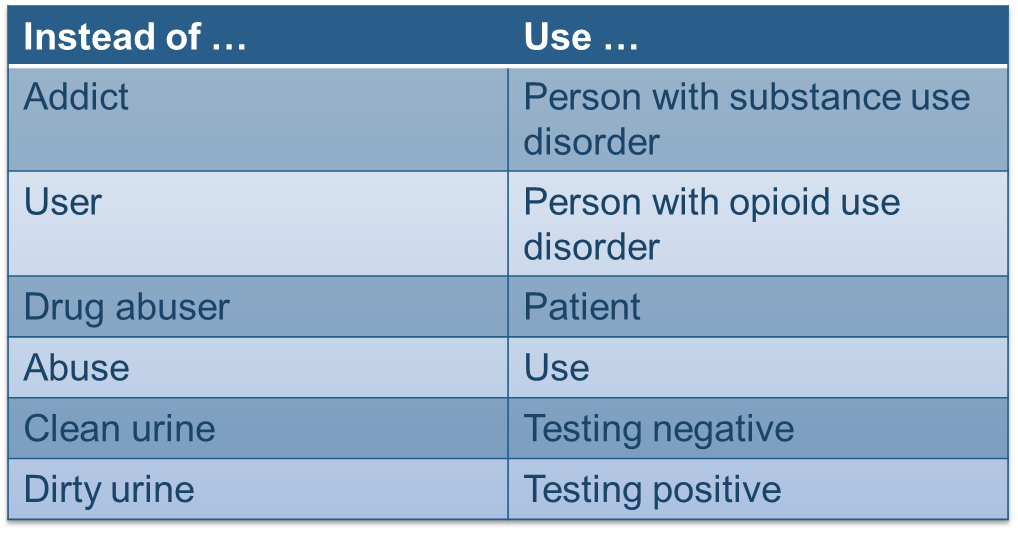
Bildverdeckung: nenne die verdeckten Beschriftungen
78
Pharmacists with SUD
1 in 10 pharmacists will suffer from a substance use disorder at some point during their lifetime
Mehr Karteikarten: Medizin und Gesundheit
PNP Management 3: Exam #3Medizin und Gesundheit · EnglischAddieSCORE 4-6Medizin und Gesundheit · Englischyyl10912 leadMedizin und Gesundheit · Englischcathsims06: The Blood SystemMedizin und Gesundheit · EnglischAndrewHuman Creutzfeldt-Jakob Disease (CJD)Medizin und Gesundheit · EnglischKatlynKEsérothérapie et vaccination Medizin und Gesundheit · FranzösischClaraCancer du colon Dr BROCCHI-JUNGMedizin und Gesundheit · FranzösischMevludeVitamins: Thiamine (B1)Medizin und Gesundheit · EnglischLaurenANS 2140L: Unit 2 - Bone and Joint TerminologyMedizin und Gesundheit · EnglischNateBiological Psychology and NeuroscienceMedizin und Gesundheit · EnglischAngelinaCommon PrefixesMedizin und Gesundheit · EnglischkaikaiInjectables brand/genericMedizin und Gesundheit · Englischkay24
Alle Decks: Medizin und Gesundheit
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

