Miscellaneous Movement Disorders
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Essential Tremor
Essential tremor (ET) is a common movement disorders, of which 50% of cases are inherited as an autosomal
dominant trait. It most often affects the hands and symptoms may be aggravated by stress, fatigue, caffeine
and temperature extremes.
dominant trait. It most often affects the hands and symptoms may be aggravated by stress, fatigue, caffeine
and temperature extremes.
2
Who Is At Risk for ET?
(+) Family History - dominant gene; one affected parent = 50% chance child will have it
Age > 40 years old
Age > 40 years old
3
Drugs that Worsen ET
Albuterol
Alcohol withdrawal
Amiodarone
Antidepressants
Cocaine
Corticosteroids
Cyclosporine
Lithium
Metoclopramide
Nicotine
Phenytoin
Procainamide
Pseudoephedrine
Alcohol withdrawal
Amiodarone
Antidepressants
Cocaine
Corticosteroids
Cyclosporine
Lithium
Metoclopramide
Nicotine
Phenytoin
Procainamide
Pseudoephedrine
4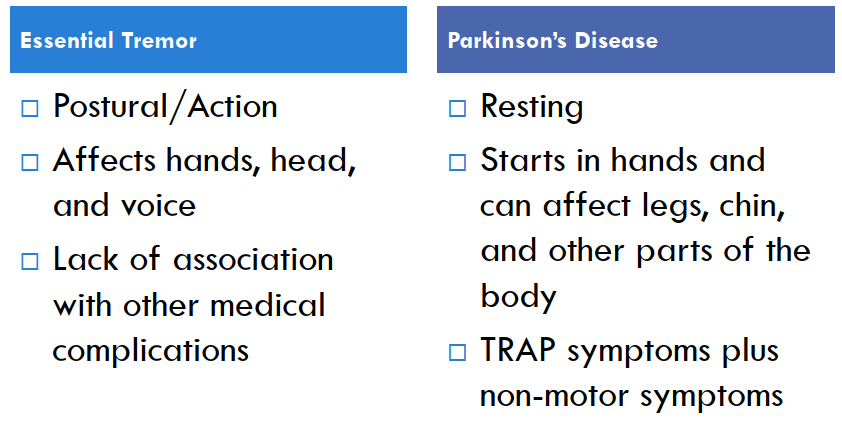
Bildverdeckung: nenne die verdeckten Beschriftungen
5
Bildverdeckung: nenne die verdeckten Beschriftungen
6
Complications of ET
Symptoms worsen over time
Can cause difficulty with activities of daily living:
Holding a cup/glass without spilling liquids
Eating normally
Putting on make-up or shaving
Talking
Writing legibly
Increased risk for psychosocial disability, anxiety, depression
Can cause difficulty with activities of daily living:
Holding a cup/glass without spilling liquids
Eating normally
Putting on make-up or shaving
Talking
Writing legibly
Increased risk for psychosocial disability, anxiety, depression
7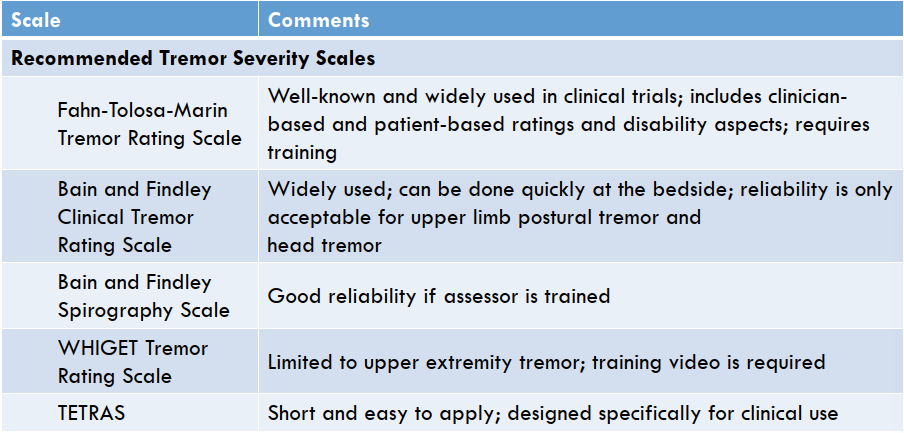
Bildverdeckung: nenne die verdeckten Beschriftungen
8
Bildverdeckung: nenne die verdeckten Beschriftungen
9
Bildverdeckung: nenne die verdeckten Beschriftungen
10
Bildverdeckung: nenne die verdeckten Beschriftungen
11
Bildverdeckung: nenne die verdeckten Beschriftungen
12
Bildverdeckung: nenne die verdeckten Beschriftungen
13
Bildverdeckung: nenne die verdeckten Beschriftungen
14
Bildverdeckung: nenne die verdeckten Beschriftungen
15
Management of ET
Behavioral Techniques and Physical Therapy
Relaxation therapy
Wrist weights
Minimizing exposure to agents that worsen tremor
Pharmacotherapy
Surgical Treatment
Unilateral thalamotomy
Deep brain stimulation (BDS of the ventral intermediate
(VIM) nucleus of the thalamus
Relaxation therapy
Wrist weights
Minimizing exposure to agents that worsen tremor
Pharmacotherapy
Surgical Treatment
Unilateral thalamotomy
Deep brain stimulation (BDS of the ventral intermediate
(VIM) nucleus of the thalamus
16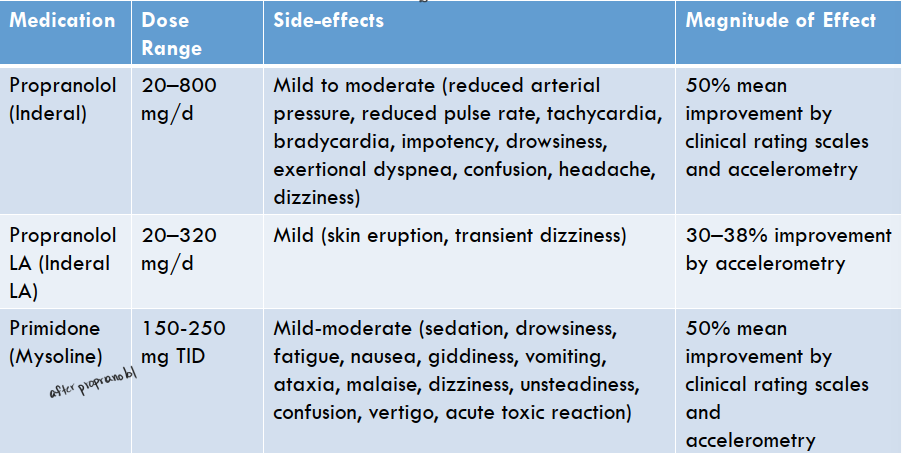
Bildverdeckung: nenne die verdeckten Beschriftungen
17
Bildverdeckung: nenne die verdeckten Beschriftungen
18
Propranolol
Usual effective dose: 20-120 mg/day
Effectiveness: Hand Tremor > Head Tremor
Tolerance:10-15% of responders develop tolerance after 1 year:
Dose increase
Switch to primidone
Add primidone
Common ADRs: light headedness, fatigue, impotence, bradycardia, reduced blood pressure
CIs: cardiogenic shock; uncompensated heart failure; sick sinus syndrome; severe sinus bradycardia; > 1st
degree heart block; bronchial asthma
Precautions: depression; diabetes; abrupt withdrawal
19
Primidone
Dosing: requires gradual titration from low doses (12.5 mg) to usual dose of 125–250 mg TID
Effectiveness: like propranolol
Common ADRs: sedation, drowsiness, nausea, vomiting, dizziness, ataxia, confusion, vertigo, and acute toxic
reaction.
CIs: porphyria; hypersensitivity to phenobarbital; pregnancy; breast-feeding
Precautions: abrupt withdrawal; suicidal ideation; blood dyscrasia
Monitoring: Complete blood count at baseline and every 6-12 months
20
Bildverdeckung: nenne die verdeckten Beschriftungen
21
Bildverdeckung: nenne die verdeckten Beschriftungen
22
Tics & TS
Tics are fast, repetitive muscle movements that result in sudden and difficult to control body jolts or sounds. TS is a condition diagnosed in patients who have two or more motor tics and at least one vocal tic and in whom tics have lasted for more than one year and started to occur before age 18 years old. There is no cure for TS, but treatment can help to control symptoms.
23
Tics
Brief, rapid, recurrent, and seemingly purposeless stereotyped motor contraction
24
Tourette's Syndrome (TS)
Characterized by multiple motor tics often accompanied by phonic tics
Waxing and waning course
Predominantly affects males
Associated behavioral disturbances:
Anxiety
Depression
Attention deficit hyperactivity disorder (ADHD)
Obsessive-compulsive disorder (OCD)
Waxing and waning course
Predominantly affects males
Associated behavioral disturbances:
Anxiety
Depression
Attention deficit hyperactivity disorder (ADHD)
Obsessive-compulsive disorder (OCD)
25
Etiology and Pathophysiology of Tourette's Syndrome
Four likely risk genes with multiple de novo damaging variants include:
WWC1
CELSR3
NIPBL
FN1
The risk of a family with one affected child having a second is about 25%
Overall, pathophysiology of TS is unknown:
Dopamine neurotransmission
Disinhibition of cortical-striatal-thalamic motor loop
Various second-messenger systems
WWC1
CELSR3
NIPBL
FN1
The risk of a family with one affected child having a second is about 25%
Overall, pathophysiology of TS is unknown:
Dopamine neurotransmission
Disinhibition of cortical-striatal-thalamic motor loop
Various second-messenger systems
26
Treatment of TS
Education and counseling
Pharmacotherapy - Indicated when the tics are disabling and interfere with quality of life
Options:
α-2 agonists
Neuroleptics
Other options:
Clonazepam
Tetrabenazine
Botulinum toxin injections
Pharmacotherapy - Indicated when the tics are disabling and interfere with quality of life
Options:
α-2 agonists
Neuroleptics
Other options:
Clonazepam
Tetrabenazine
Botulinum toxin injections
27
Alpha-2-agonists
Moderate efficacy
Agents
Clonidine 0.5-5 mg/day
Guanfacine 0.5-4 mg/day
Common ADRs:
Sedation
Headache
Dizziness
Irritability
Dry mouth
Particularly helpful in comorbid ADHD
Agents
Clonidine 0.5-5 mg/day
Guanfacine 0.5-4 mg/day
Common ADRs:
Sedation
Headache
Dizziness
Irritability
Dry mouth
Particularly helpful in comorbid ADHD
28
Neuroleptics
Improved efficacy compared to α-2 agonists
Agents
Atypical:
Aripiprazole 5-30 mg/day
Risperidone 0.5-16 mg/day
Olanzapine 1.25-10 mg/day
Ziprasidone 5-40 mg/day
Conventional:
Haloperidol 0.5-20 mg/day
Fluphenazine 0.5-20 mg/day
Pimozide 0.5-10 mg/day
Monitor for metabolic syndrome (atypical agents) and worsening movement disorders (conventional agents)
29
Other Options for TS
Clonazepam
Modest tic-suppressing effects when used BID to TID
Useful in patients with comorbid anxiety disorder
Common ADRs: sedation, unsteadiness
Tetrabenazine
Shown to reduce the number of motor and vocal tics and severity of symptoms
Children may tolerate higher doses than adults
Common ADRs: as noted under HD
Botulinum toxin injections
Consider when tics $\rightarrow$ social distress, discomfort, or self injury
May be preferred if tics have dystonic feature
Common ADRs: weakness, pain
30
Myoclonus
Myoclonus is a brief, rapid (<100 ms), shock-like, jerky movement consisting of single or repetitive muscle jerks. Myoclonus be focus, multifocal, segmental, or generalized. It can occur spontaneously, in associated with voluntary movement, or in response to external stimulus. Negative myoclonus consists of brief loss of muscle activity. Myoclonus can be severe and interfere with normal movement
31
How is Myoclonus Different from Tics
Not typically repetitive
Not suppressible
Can severely interfere with normal voluntary movement
Common associated features:
Nearly all cases (+) an additional movement disorder (e.g., ataxia, dystonia)
Majority of cases (+) cognitive decline and epilepsy
Not suppressible
Can severely interfere with normal voluntary movement
Common associated features:
Nearly all cases (+) an additional movement disorder (e.g., ataxia, dystonia)
Majority of cases (+) cognitive decline and epilepsy
32
Etiology of Myoclonus
Association with abnormal neuronal discharges in cortical, subcortical, brainstem, or spinal cord regions, particularly in association with hypoxemia encephalopathy, and neurodegeneration
Hereditary myoclonus
Reversible myoclonus can be seen with metabolic disturbances (renal failure, electrolyte imbalance,
hypocalcemia), toxins, and medications (e.g., serotonin syndrome)
Hereditary myoclonus
Reversible myoclonus can be seen with metabolic disturbances (renal failure, electrolyte imbalance,
hypocalcemia), toxins, and medications (e.g., serotonin syndrome)
33
Medication-Induced Myoclonus
Opiates
Antidepressants
Buspirone
Lithium
Antipsychotics
Antibiotics (β-lactam, quinolones, sulfonamides, aminoglycosides)
N-methyl-D-aspartate (NMDA) receptor antagonists (rare)
Antidepressants
Buspirone
Lithium
Antipsychotics
Antibiotics (β-lactam, quinolones, sulfonamides, aminoglycosides)
N-methyl-D-aspartate (NMDA) receptor antagonists (rare)
34
Treatment of Myoclonus
Manage underlying condition/remove offending agent
DBS in myoclonus dystonia
Pharmacotherapy:
≥1 GABAergic agents:
valproic acid (800–3000 mg/d)
piracetam (8–20 g/d)
clonazepam (2–15 mg/d)
levetiracetam (1000–3000 mg/d)
primidone (500–1000 mg/d)
Postanoxic myoclonus: 5-HTP + carbidopa
DBS in myoclonus dystonia
Pharmacotherapy:
≥1 GABAergic agents:
valproic acid (800–3000 mg/d)
piracetam (8–20 g/d)
clonazepam (2–15 mg/d)
levetiracetam (1000–3000 mg/d)
primidone (500–1000 mg/d)
Postanoxic myoclonus: 5-HTP + carbidopa
35
Restless Legs Syndrome (RLS)
RLS is often considered a sleep-wake disorder and is associated with 4 core symptoms:
1. An urge to move the legs usually caused or accompanied by unpleasant sensation in the legs
2. Symptoms that begin or worse with rest
3. Partial or complete relief by movement
4. Worsening during the evening or night
1. An urge to move the legs usually caused or accompanied by unpleasant sensation in the legs
2. Symptoms that begin or worse with rest
3. Partial or complete relief by movement
4. Worsening during the evening or night
36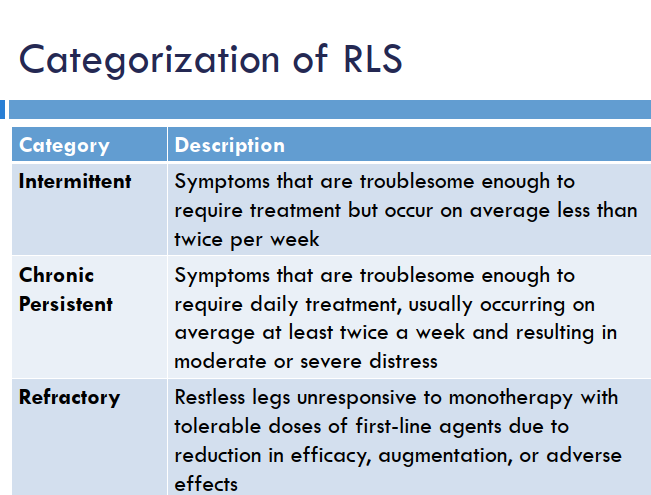
Bildverdeckung: nenne die verdeckten Beschriftungen
37
Bildverdeckung: nenne die verdeckten Beschriftungen
38
Bildverdeckung: nenne die verdeckten Beschriftungen
39
Etiology of RLS
Primary RLS: familial association
Secondary RLS:
Pregnancy
Neuropathy
End-stage renal disease
Iron deficiency
Secondary RLS:
Pregnancy
Neuropathy
End-stage renal disease
Iron deficiency
40
Treatment of RLS
Lifestyle modifications: avoid caffeine, alcohol, and nicotine
Non-pharmacologic treatment:
Pneumatic compression devices (AAN level B evidence)
Alternative options: mental alerting activities, vibrating pads underneath the legs, acupuncture, near-infrared spectroscopy, and repetitive transcranial magnetic stimulation
Pharmacologic treatment:
Iron supplementation in cases of deficiency
Alpha2-delta calcium channel ligands, dopamine agonists, carbidopa/levodopa, benzodiazepines, opioids
41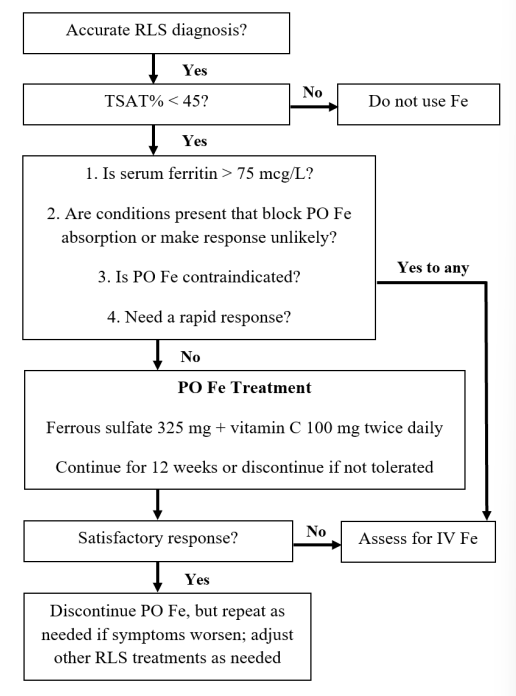
Bildverdeckung: nenne die verdeckten Beschriftungen
42
Bildverdeckung: nenne die verdeckten Beschriftungen
43
Bildverdeckung: nenne die verdeckten Beschriftungen
44
Bildverdeckung: nenne die verdeckten Beschriftungen
45
Bildverdeckung: nenne die verdeckten Beschriftungen
46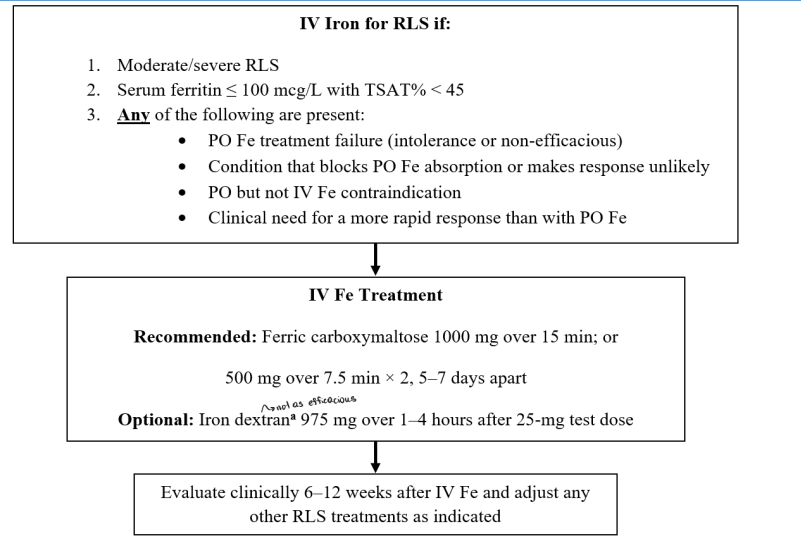
Bildverdeckung: nenne die verdeckten Beschriftungen
47
Bildverdeckung: nenne die verdeckten Beschriftungen
48
Bildverdeckung: nenne die verdeckten Beschriftungen
49
Pharmacotherapy of RLS
Intermittent: as needed administration of levodopa/carbidopa, low-potency opioids, or benzodiazepines
Chronic Persistent: alpha2-delta calcium channel ligands (first line), dopamine agonists (second line)
Refractory: combination therapy with alpha2-delta calcium channel ligands, dopamine agonists, or benzodiazepines, or monotherapy with an opioid
Chronic Persistent: alpha2-delta calcium channel ligands (first line), dopamine agonists (second line)
Refractory: combination therapy with alpha2-delta calcium channel ligands, dopamine agonists, or benzodiazepines, or monotherapy with an opioid
50
Augmentation in RLS
Most common complication and reason for discontinuing dopaminergics in RLS
Characterized by symptoms beginning earlier in the day and/or symptom location spreading to the
upper extremities
Prevention:
Avoid dopaminergics
Use the lowest effective dopaminergic dose
Characterized by symptoms beginning earlier in the day and/or symptom location spreading to the
upper extremities
Prevention:
Avoid dopaminergics
Use the lowest effective dopaminergic dose
51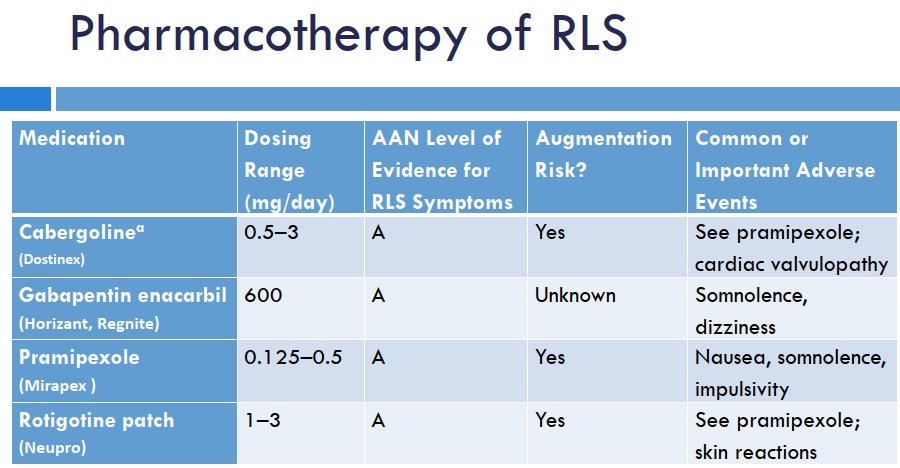
Bildverdeckung: nenne die verdeckten Beschriftungen
52
Bildverdeckung: nenne die verdeckten Beschriftungen
53
Bildverdeckung: nenne die verdeckten Beschriftungen
54
Bildverdeckung: nenne die verdeckten Beschriftungen
55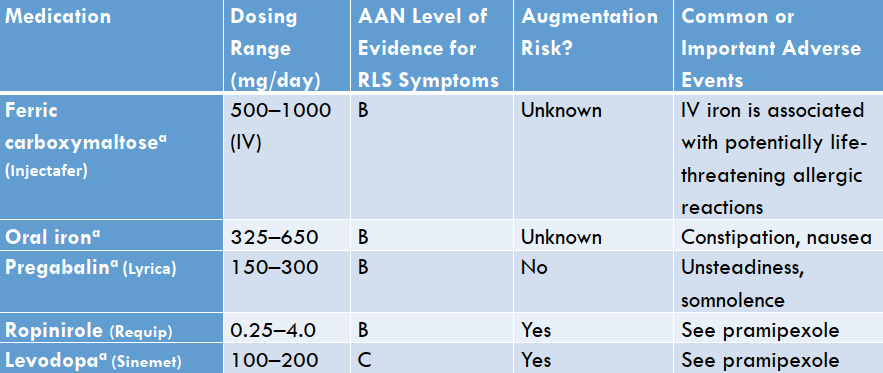
Bildverdeckung: nenne die verdeckten Beschriftungen
56
Bildverdeckung: nenne die verdeckten Beschriftungen
57
Bildverdeckung: nenne die verdeckten Beschriftungen
58
Bildverdeckung: nenne die verdeckten Beschriftungen
59
Bildverdeckung: nenne die verdeckten Beschriftungen
60
Huntington’s Disease
Huntington’s disease (HD) is a rare, incurable, neurodegenerative disorder of the central nervous system characterized by progressive worsening of motor, cognitive, psychiatric, and behavioral symptoms.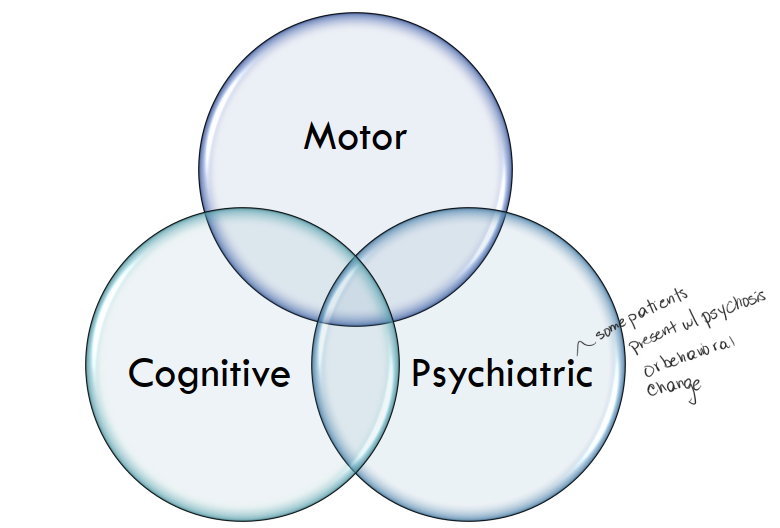
61
Who is at risk for Huntington's Disease
Huntington’s disease is inherited in an autosomal dominant fashion. The probability of each offspring inheriting an affected gene is 50%. Inheritance is independent of gender.
62
CAG Repeat in HD
Huntington's disease (HD) is a genetic disorder caused by an expansion of CAG (cytosine-adenine-guanine) trinucleotide repeats in the huntingtin (HTT) gene, located on chromosome 4.
Normally, the HTT gene contains a repeating sequence of CAG, but in people with HD, the number of CAG repeats in this region is expanded beyond a certain threshold. The size of the CAG repeat expansion determines when and how severe the symptoms of HD will appear.
Normally, the HTT gene contains a repeating sequence of CAG, but in people with HD, the number of CAG repeats in this region is expanded beyond a certain threshold. The size of the CAG repeat expansion determines when and how severe the symptoms of HD will appear.
63
What part of the brain does HD affect?
HD affects the whole brain, but certain areas are more vulnerable than others. Specifically, the basal ganglia – a group of nerves cell clusters, called nuclei. These nuclei play a key role in movement and behavior control and are the parts of the brain most prominently affected in early HD.
64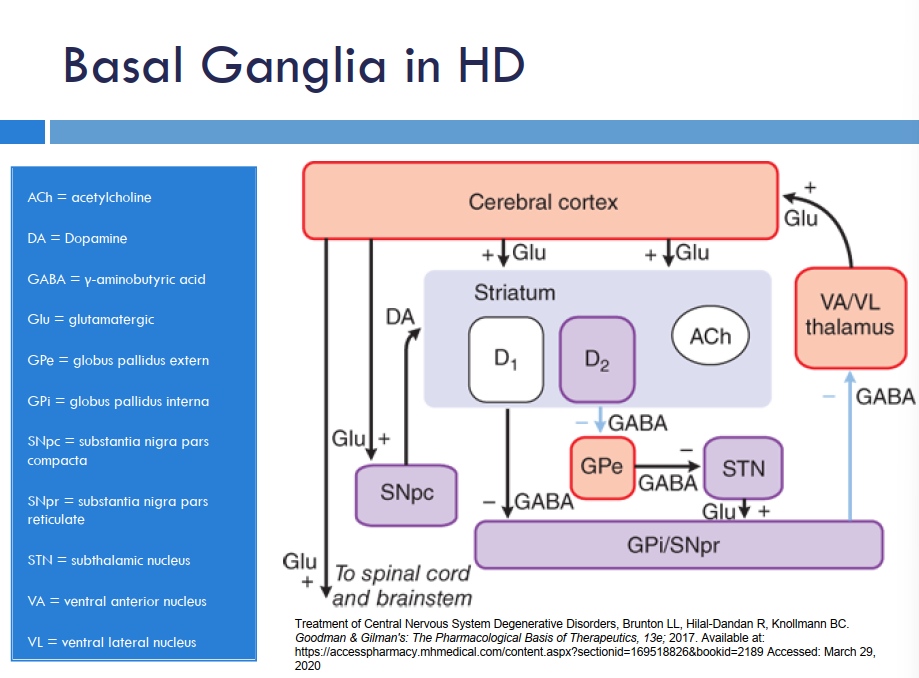
Bildverdeckung: nenne die verdeckten Beschriftungen
65
Bildverdeckung: nenne die verdeckten Beschriftungen
66
Bildverdeckung: nenne die verdeckten Beschriftungen
67
Bildverdeckung: nenne die verdeckten Beschriftungen
68
Bildverdeckung: nenne die verdeckten Beschriftungen
69
Evaluation of HD - Diagnosis
Unified Huntington’s Disease Rating Scale (UHDRS)
Gold-standard for evaluation of HD
Motor, cognitive, behavioral abnormalities, functional capacity
Motor symptoms are assessed using Total Motor Scale (TMS)
TMS Diagnostic Confidence Level (DCL) used to assess clinician’s confidence that symptoms represent HD
0 = normal
1 = nonspecific motor abnormalities
2 = motor abnormalities that may be signs of HD (50-89%)
3 = motor abnormalities that are likely signs of HD (90-98%)
4 = motor abnormalities that are unequivocal signs of HD (99%)
Diagnosis = Chorea + DCL 4
70
Evaluation of HD - Genetic Testing
• < 5% at-risk individuals choose to pursue predictive genetic testing
• Current guidelines recommend against genetic testing to predict diagnosis age
• High rate of completed suicide attempts amongst individuals with HD
• Current guidelines recommend against genetic testing to predict diagnosis age
• High rate of completed suicide attempts amongst individuals with HD
71
Pharmacotherapy – Chorea
Consider drug therapy if chorea $\rightarrow$ distress or discomfort
Monotherapy preferred
First line: tetrabenazine (Xenazine)
Alternatives: reserpine, neuroleptics (e.g.,
haloperidol, fluphenazine, risperidone, olanzapine)
Monotherapy preferred
First line: tetrabenazine (Xenazine)
Alternatives: reserpine, neuroleptics (e.g.,
haloperidol, fluphenazine, risperidone, olanzapine)
72
Tetrabenazine (Xenazine)
MOA: reversible inhibitor of VMAT2 $\rightarrow$ depletion of dopamine release by presynaptic striatal neurons
Genotyping for CYP2D6 is recommended when doses > 50mg/day are needed
Boxed Warning: increase the risk of depression and suicidal thoughts and behavior (suicidality) in patients with HD
CI: hepatic function impairment; active suicidality or untreated or inadequately treated depression; coadministration of monoamine oxidase inhibitors (MAOIs) or use of tetrabenazine within 2 weeks of discontinuation of MAOI therapy; coadministration with reserpine (≥20 days should pass after discontinuing reserpine before initiating tetrabenazine therapy) coadministration with deutetrabenazine or valbenazine
Common ADRs: sedation, depression, akathisia, worsening of voluntary motor control, QTc prolongation
73
Pharmacotherapy – Rigidity (HTD)
Description: increase in muscle tone leading to a resistance to passive
movement $\rightarrow$ limited range of motion
More common in juvenile onset
May be induced by tetrabenazine or neuroleptics
Recommended agents:
First line: levodopa (lower doses than in Parkinson’s disease)
Alternative: DA agonists
CAUTION: increased risk of psychosis with DA agonists
movement $\rightarrow$ limited range of motion
More common in juvenile onset
May be induced by tetrabenazine or neuroleptics
Recommended agents:
First line: levodopa (lower doses than in Parkinson’s disease)
Alternative: DA agonists
CAUTION: increased risk of psychosis with DA agonists
74
Pharmacotherapy – Myoclonus (HTD)
Description: brief, involuntary and sudden muscle contractions
Recommended agents:
First line: clonazepam or valproic acid (as monotherapy or in combination)
Alternative: levetiracetam
CAUTION: increased fall risk and somnolence with benzodiazepines
Recommended agents:
First line: clonazepam or valproic acid (as monotherapy or in combination)
Alternative: levetiracetam
CAUTION: increased fall risk and somnolence with benzodiazepines
75
Pharmacotherapy – Depression (HTD)
Studied agents: fluoxetine, carbamazepine
Recommended agents:
First line: selective serotonin reuptake inhibitors (SSRIs), serotonin norepinephrine reuptake inhibitors (SNRIs)
If sleep disturbance: mirtazapine
If recurrent depression: carbamazepine (adjunctively)
CAUTION: anticholinergic effects of antidepressants
Recommended agents:
First line: selective serotonin reuptake inhibitors (SSRIs), serotonin norepinephrine reuptake inhibitors (SNRIs)
If sleep disturbance: mirtazapine
If recurrent depression: carbamazepine (adjunctively)
CAUTION: anticholinergic effects of antidepressants
76
Pharmacotherapy – Irritability (HTD)
Recommended agents:
First line: SSRIs
Second line: SSRI + mirtazapine
If overt aggression: sedating antidepressant + neuroleptic
CAUTION: anticholinergic effects of antidepressants and neuroleptics
First line: SSRIs
Second line: SSRI + mirtazapine
If overt aggression: sedating antidepressant + neuroleptic
CAUTION: anticholinergic effects of antidepressants and neuroleptics
77
Pharmacotherapy – Anxiety (HTD)
Recommended agents:
First line: SSRI or SNRI
If breakthrough anxiety: as needed low-dose benzodiazepines
If treatment resistant: antidepressant + neuroleptic
CAUTION: anticholinergic effects of antidepressants and neuroleptics, increased fall risk and somnolence with benzodiazepines
First line: SSRI or SNRI
If breakthrough anxiety: as needed low-dose benzodiazepines
If treatment resistant: antidepressant + neuroleptic
CAUTION: anticholinergic effects of antidepressants and neuroleptics, increased fall risk and somnolence with benzodiazepines
78
Pharmacotherapy – Psychosis (HTD)
Recommended agents:
First line: low-dose antipsychotics
If rigid HD: clozapine, quetiapine, carbamazepine
CAUTION: reduced cognitive function and mobility
First line: low-dose antipsychotics
If rigid HD: clozapine, quetiapine, carbamazepine
CAUTION: reduced cognitive function and mobility
Mehr Karteikarten: Medizin und Gesundheit
KINE 3660 2Medizin und Gesundheit · EnglischNtxHynSJCTMedizin und Gesundheit · EnglischKarissaMaternal Newborn Medizin und Gesundheit · EnglischTaylor7. Mid. spinale - Micro. Sost. grigiaMedizin und Gesundheit · ItalienischWalterHomeostasis: Biology AQA GCSEMedizin und Gesundheit · EnglischIzzyMotorik & MuskelMedizin und Gesundheit · SchwedischAlilproles médicaments de la douleur palier 3 Medizin und Gesundheit · FranzösischClaraEndocrine TerminologyMedizin und Gesundheit · EnglischebradstreetCardiovascular System: Heart and VesselsMedizin und Gesundheit · EnglischTaylorChapter 5: Digestive System Medical TerminologyMedizin und Gesundheit · EnglischJulieLymphatic and Immune System FlashcardsMedizin und Gesundheit · EnglischVickyDigestive SystemMedizin und Gesundheit · EnglischEmely
Alle Decks: Medizin und Gesundheit
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

