Acetaminophen Toxicity
Diese Karteikarten lernenKostenlos · Spaced Repetition · iPhone, Android, Mac & Web
Alle Karten
1
Acetaminophen
N-acetyl-p-aminophenol (APAP)
o Analgesic + antipyretic (via inhibition of prostaglandin synthesis)
o Weak peripheral anti-inflammatory + antiplatelet properties
▪ Leading cause of acute liver failure in the United States
▪ Associated with largest number of overdose fatalities
o Analgesic + antipyretic (via inhibition of prostaglandin synthesis)
o Weak peripheral anti-inflammatory + antiplatelet properties
▪ Leading cause of acute liver failure in the United States
▪ Associated with largest number of overdose fatalities
2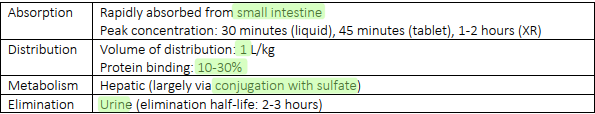
Bildverdeckung: nenne die verdeckten Beschriftungen
3
Bildverdeckung: nenne die verdeckten Beschriftungen
4
Bildverdeckung: nenne die verdeckten Beschriftungen
5
Bildverdeckung: nenne die verdeckten Beschriftungen
6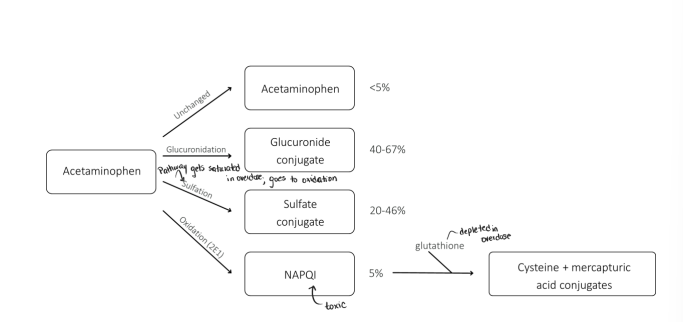
Bildverdeckung: nenne die verdeckten Beschriftungen
7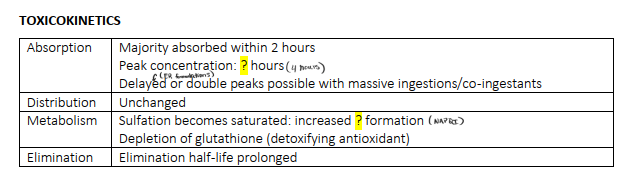
Bildverdeckung: nenne die verdeckten Beschriftungen
8
Bildverdeckung: nenne die verdeckten Beschriftungen
9
Bildverdeckung: nenne die verdeckten Beschriftungen
10
Bildverdeckung: nenne die verdeckten Beschriftungen
11
Hepatic Toxicity
o Binds to cysteine portion of mitochondrial proteins to produce protein adducts within the liver
o Alters mitochondrial function + impairs cellular defense vs. endogenous reactive oxygen species
o Covalently binds + arylates cellular proteins - apoptosis + cellular necrosis
o Hepatotoxicity in hepatic zone III (centrilobular)
o Alters mitochondrial function + impairs cellular defense vs. endogenous reactive oxygen species
o Covalently binds + arylates cellular proteins - apoptosis + cellular necrosis
o Hepatotoxicity in hepatic zone III (centrilobular)
12
Renal Toxicity
o Local production of NAPQI (via CYP2E1) - acute tubular necrosis
o Nephropathy via prostaglandin mediated renal medullary ischemia
o Inhibition of electron transport - metabolic acidosis (elevated lactate)
o Volume depletion + hepatorenal syndrome
o Nephropathy via prostaglandin mediated renal medullary ischemia
o Inhibition of electron transport - metabolic acidosis (elevated lactate)
o Volume depletion + hepatorenal syndrome
13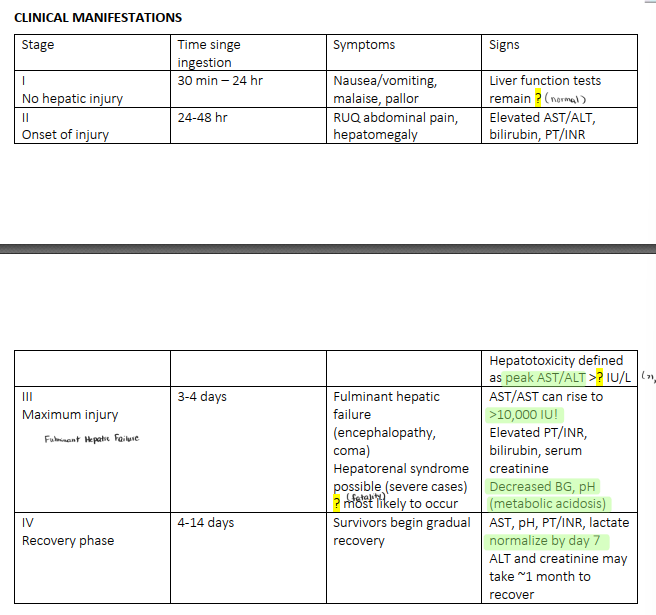
Bildverdeckung: nenne die verdeckten Beschriftungen
14
Bildverdeckung: nenne die verdeckten Beschriftungen
15
Bildverdeckung: nenne die verdeckten Beschriftungen
16
Bildverdeckung: nenne die verdeckten Beschriftungen
17
Diagnosis
Subjective (history of ingestion)
o Time of ingestion
o Amount ingested
▪ Lowest doses capable of causing toxicity: 7.5g in adults, 150 mg/kg in children
o Drug formulation (tablets vs. liquids)
o Reason for ingestion (intentional vs. accidental)
o Presence of co-ingestants
▪ Slows gastric motility: anticholinergics, opioids, sedative/hypnotics
▪ Inducers of CYP: isoniazid, phenytoin, carbamazepine, phenobarbital
▪ Food: slows absorption time
Objective (laboratory diagnostics
o Serum acetaminophen concentration (therapeutic = 10-30 mcg/mL)
o Markers of hepatic injury: AST/ALT
o Markers of hepatic function: PT/INR, lactate, phosphate, glucose, pH, creatinine
18
GI Decontamination
Appropriate to perform if
o Present shortly after ingestion
o No contraindications to decon (e.g. no risk of aspiration)
▪ Decon method of choice: Activated Charcoal
o Most effective if given within 1-2 hours of ingestion
o Can give beyond 2 hours if co-ingest xenobiotic that delays GI absorption
o Dosing: 1 g/kg (adults: ~50-100 g)
▪ Supplied as: 15 g, 25 g, 50 g (with and without sorbitol)
▪ To increase palatability: create slurry (1:8) with water
o Drug interaction: oral NAC (separate by 1-2 hours)
19
Manage Hepatic Injury
▪ Monitor + manage hypoglycemia
▪ Evaluate for coagulopathy + monitor for hemorrhagic complications
▪ Correction of coagulopathy reserved for: procedures, life-threatening bleeding
▪ Consider use of: phytonadione, fresh frozen plasma, prothrombin complex concentrate
▪ Evaluate for coagulopathy + monitor for hemorrhagic complications
▪ Correction of coagulopathy reserved for: procedures, life-threatening bleeding
▪ Consider use of: phytonadione, fresh frozen plasma, prothrombin complex concentrate
20
Manage manifestations of severe toxicity
▪ Renal dysfunction (e.g. extracorporeal support, etc.)
▪ Cerebral edema (e.g. cooling, hypertonic saline, etc.)
▪ Cerebral edema (e.g. cooling, hypertonic saline, etc.)
21
Psychiatric Evaluations
For intentional Ingestions
22
N-Acetylcysteine (NAC)
▪ Nearly 100% effective if administered within 8 hours of ingestion
▪ Formulations: IV (Acetadote) + oral (Mucomyst, Cetylev)
• PO: avoid if aspiration risk
• IV preferred in: fulminant hepatic failure, aspiration risk, and pregnancy
▪ In APAP overdose, it serves 3 distinct roles
• Limits formation of toxic metabolite (NAPQI)
• Increases capacity to detoxify NAPQI
• Decreases toxicity
23
NAC Mechanism
▪ Limits formation of NAPQI: increases metabolism via sulfation
• NAC = thiol-containing compound that increases intracellular cysteine
• Cysteine is a substrate for sulfation = more metabolism to nontoxic
metabolites
• Less metabolism via oxidation = less NAPQI formation
▪ Increases capacity to detoxify NAPQI: precursor/substitute for glutathione
• Rate-limiting step in synthesis of glutathione = availability of cysteine
• NAC increases intracellular cysteine > more glutathione > more NAPQI
breakdown
▪ Decreases toxicity: modulates cascade of inflammatory events
• Free radical scavenging, nonspecific antioxidant effects
• Increases oxygen deliverytilization (brain, heart, kidneys)
• Increases mitochondrial ATP production, alteration of microvascular tone
24
Indications to use NAC
▪ Using Rumack-Matthew nomogram: [APAP] over treatment line
▪ Any detectable level at 24 hours post-ingestion
▪ Ingested toxic amount + [APAP] not available within 8 hours of ingestion
▪ Risk of toxicity + time of ingestion cannot be determined
▪ Chronic ingestions: elevated AST or [APAP] (given time since last ingestion)
▪ Any detectable level at 24 hours post-ingestion
▪ Ingested toxic amount + [APAP] not available within 8 hours of ingestion
▪ Risk of toxicity + time of ingestion cannot be determined
▪ Chronic ingestions: elevated AST or [APAP] (given time since last ingestion)
25
Rumack-Matthew nomogram
Tool to determine risk of developing hepatotoxicity
• Line separates patients who do vs. don't develop hepatoxicity
• Based on oral ingestion
• Two lines: original data vs. treatment line
▪ Plot patient specific data to determine if antidote should be given
• Must know: hours since ingestion + initial [APAP]
• Use earliest possible time of ingestion (e.g. worst case scenario)
▪ Treat with antidote if above the treatment line
• Treat if 150 mcg/mL or above at 4 hours post-ingestion
• [APAP] to treat halves every 4 hours (e.g. 75 mcg/mL at 8 hours)
• Only useful up to 24 hours post-ingestion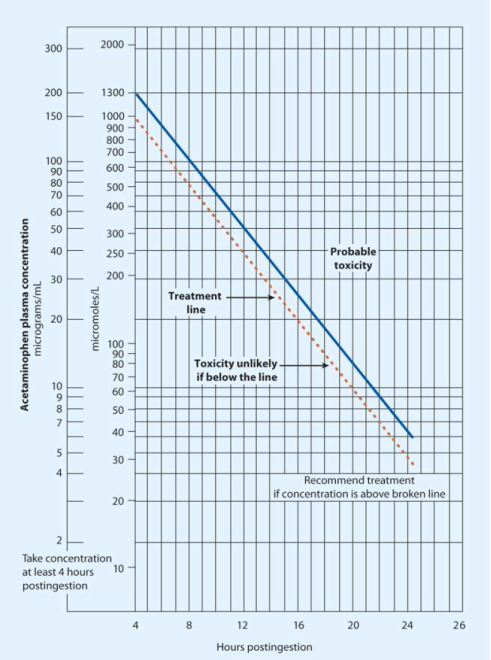
• Line separates patients who do vs. don't develop hepatoxicity
• Based on oral ingestion
• Two lines: original data vs. treatment line
▪ Plot patient specific data to determine if antidote should be given
• Must know: hours since ingestion + initial [APAP]
• Use earliest possible time of ingestion (e.g. worst case scenario)
▪ Treat with antidote if above the treatment line
• Treat if 150 mcg/mL or above at 4 hours post-ingestion
• [APAP] to treat halves every 4 hours (e.g. 75 mcg/mL at 8 hours)
• Only useful up to 24 hours post-ingestion
26
Dosing of oral NAC
Dosing (doses should be capped at 100 kg)
o Loading dose: 140 mg/kg
o Maintenance dose: 10 mg/kg every 4 hours x17 doses
o Regimen duration: 72 hours
o Loading dose: 140 mg/kg
o Maintenance dose: 10 mg/kg every 4 hours x17 doses
o Regimen duration: 72 hours
27
NAC Adverse Effects
Oral
o Nausea/vomiting (sulfur odor): if vomit within 1 hour of dose, repeat dose or use IV instead
o Consider further dilution or pre-treatment with antiemetic
o Avoid carbonated beverages!
IV
o Skin flushing (common in first 30-60 minutes, self-resolving)
o Anaphylactoid (not anaphylaxis!) reactions
o Nausea/vomiting (sulfur odor): if vomit within 1 hour of dose, repeat dose or use IV instead
o Consider further dilution or pre-treatment with antiemetic
o Avoid carbonated beverages!
IV
o Skin flushing (common in first 30-60 minutes, self-resolving)
o Anaphylactoid (not anaphylaxis!) reactions
28
Dosing of IV NAC
o Traditional 3-bag regimen
▪ 150 mg/kg over 1 hour (150 mg/kg/h)
▪ 50 mg/kg over 4 hours (12.5 mg/kg/h)
▪ 100 mg/kg over 16 hours (6.25 mg/kg/h)
o 2-bag regimen
▪ 200 mg/kg over 4 hours (50 mg/kg/h)
▪ 100 mg/kg over 16 hours (6.25 mg/kg/h)
o Regimen duration: 21 hours
▪ 150 mg/kg over 1 hour (150 mg/kg/h)
▪ 50 mg/kg over 4 hours (12.5 mg/kg/h)
▪ 100 mg/kg over 16 hours (6.25 mg/kg/h)
o 2-bag regimen
▪ 200 mg/kg over 4 hours (50 mg/kg/h)
▪ 100 mg/kg over 16 hours (6.25 mg/kg/h)
o Regimen duration: 21 hours
29
NAC Dose Adjustment
▪ Reasonable to give higher NAC doses in massive ingestions
• Anticipate elevated [APAP] for prolonged periods or secondary
elevations
• Risk of hepatotoxicity that increases linearly with increasing [APAP]
o Risk of hepatotoxicity increases at 300 mcg/mL and 500 mcg/mL lines
o Risk of coagulopathy increases at 900 mcg/mL line
▪ Massive ingestions $\rightarrow$ 35g ingested, initial [APAP] >300 mcg/mL line
30
Duration of Therapy
▪ Re-evaluate laboratory markers prior to the end of the regimen
o IV: draw labs 2 hours prior to end of final infusion
o PO: draw labs at 24 hours
▪ Discontinue NAC if
o Serum acetaminophen concentration is undetectable
o Improvement in AST
▪ 2 consecutive decreasing AST values
▪ AST <1,000 IU/L
▪ AST/ALT ratio of 0.4
o Resolution of coagulopathy: INR <2
▪ Continue NAC therapy if above criteria are not met
31
Prognosis
▪ Most common prognostic indicator is King's College Criteria
o Predicts who will survive without a transplant
o Interpret with caution: PT altered by concurrent NAC, phytonadione, PCC, FFP
o Survival rate if meet criteria and do not received transplant = 25-40%
▪ Patients who should be evaluated for transplant:
o Arterial pH <7.3 or lactate >3 mmol/L after fluid resuscitation OR
o Combination of: creatinine >3.3 mg/dL + PT >100 sec (or INR >6.5) + grade III or IV
encephalopathy
▪ Not useful as early predictor of need for transplant or transfer to transplant center
o Often meet these criteria too late in course of toxicity!
Mehr Karteikarten: Medizin und Gesundheit
Anthony's flash cardsMedizin und Gesundheit · PolnischnadsEbenen, Achsen, Richtungen und LageMedizin und Gesundheit · DeutschLisa(3) Thalamus cortex og hjernestammenMedizin und Gesundheit · NorwegischTobiasVaccine and Antibody DataMedizin und Gesundheit · EnglischLoganWinters bone Medizin und Gesundheit · Englischalvalymphoid rendszer Medizin und Gesundheit · UngarischRitikeXDD | NeuroscienceMedizin und Gesundheit · EnglischAdUvertchem exam 4Medizin und Gesundheit · EnglischMontanaKalima wa Nagham Vol. 2, Lesson 1 VocabMedizin und Gesundheit · ArabischBilalOpioids and PharmacologyMedizin und Gesundheit · EnglischEshaDigestive Pathophysiology Exam 3Medizin und Gesundheit · EnglischMadiruth2QCMs tissus conjonctifsMedizin und Gesundheit · FranzösischGloria
Alle Decks: Medizin und Gesundheit
Lerne diese Decks in der App
Kostenlos auf iPhone, Android, Mac und im Web. Füge jedes Deck mit einem Tipp zu deinem Konto hinzu.

